Understanding How Molecules Cross Cell Membranes
Cell membranes are selective barriers. Small nonpolar molecules slip through the lipid bilayer without help, but ions and larger polar substances need assistance. This is where membrane transport proteins come into play, and it's also where a common point of confusion appears in introductory biology courses. When I was reviewing transport mechanisms with students preparing for AP Biology, one question kept coming up. Students would read a textbook passage about glucose entering a cell and then get tripped up on whether it was active or passive. The terminology overlaps in ways that aren't immediately obvious, and the distinction matters for understanding everything from kidney function to nerve impulse transmission.
Unraveling The Mystery: Is Facilitated Diffusion Active Or Passive?
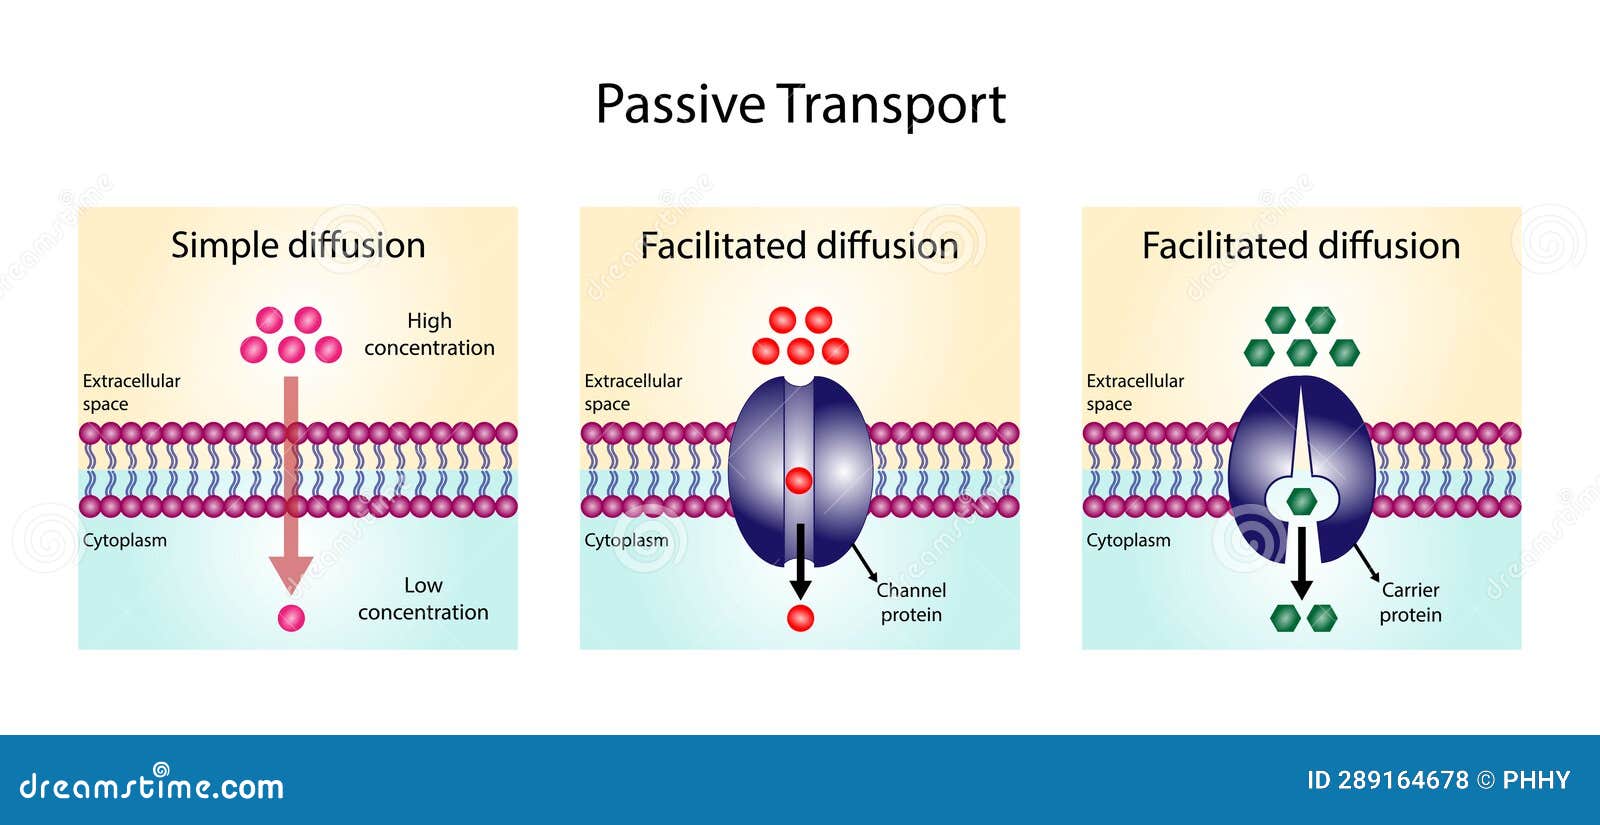
Facilitated diffusion is a form of passive transport. It does not require cellular energy in the form of ATP. The key word here is diffusion — molecules move down their concentration gradient, from an area of higher concentration to an area of lower concentration. The only difference between simple diffusion and facilitated diffusion is that proteins assist the movement. Without transport proteins, charged ions cannot cross the hydrophobic core of the membrane. Glucose is too large and polar to pass through by itself. So the cell uses channel proteins and carrier proteins to move these substances. The gradient does the work, not the cell. I ran into a specific problem last semester when a student insisted that facilitated diffusion must be active because "the cell is doing something by providing the protein." This is a legitimate confusion. The cell does expend energy to synthesize the transport protein, but that's a completely different energy cost than what active transport requires. The actual movement event costs nothing. Once the protein is embedded in the membrane, it functions like a toll booth that opens and closes without taking payment from the passing cars.
There are two main types of facilitated diffusion proteins. Channel proteins form aqueous pores across the membrane. Ion channels are highly specific — a potassium channel will generally not pass sodium ions, even though sodium is smaller. Some channels are always open, while others are gated and respond to voltage changes, ligand binding, or mechanical stretch. Aquaporins are a well-studied class of channel proteins that facilitate water movement across membranes at rates far exceeding what would occur through the lipid bilayer alone. Carrier proteins work differently. They bind the solute on one side of the membrane, undergo a conformational change, and release it on the other side. Glucose transporters, known as GLUT proteins, operate this way. GLUT1 is found in red blood cells and provides a baseline glucose uptake rate. GLUT4 is the insulin-responsive transporter stored in vesicles inside muscle and fat cells. When insulin signals the cell, those vesicles fuse with the membrane and dramatically increase glucose transport capacity. This is still facilitated diffusion. No ATP is hydrolyzed during the transport event itself. Here is a nuance that textbooks often gloss over. The direction of movement determines whether a process is active or passive, but the type of protein does not. Some people assume that because carrier proteins change shape, they must be using energy. Shape changes in proteins occur through thermal motion and binding energy, not necessarily through ATP hydrolysis. A carrier protein in facilitated diffusion uses the same molecular mechanics as one in active transport, but only the latter couples the conformational change to an energy source.
Get the Full Details
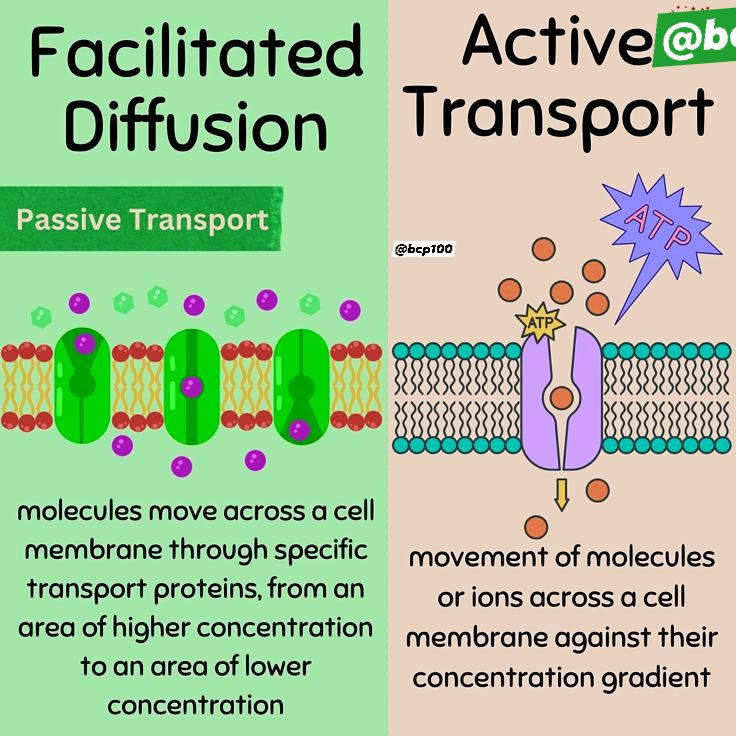
Secondary active transport sits in a gray area that causes even more confusion. The sodium-glucose cotransporter SGLT1 uses the energy stored in a sodium ion gradient to pull glucose into the cell against its concentration gradient. That sodium gradient is established by the Na+/K+ ATPase, which does consume ATP directly. SGLT1 itself does not touch ATP. It is an example of secondary active transport, and it is fundamentally different from facilitated diffusion, even though both involve carrier proteins. In practice, distinguishing these mechanisms requires looking at three things. First, check whether ATP is consumed during the transport event. Second, determine the direction of solute movement relative to its concentration gradient. Third, identify the protein class and whether it shows saturation kinetics, which both facilitated diffusion and active transport do, unlike simple diffusion. One counter-intuitive insight is that facilitated diffusion can reach a maximum rate. Carrier proteins have a finite number of binding sites, so once all sites are occupied, increasing the concentration gradient further produces no additional transport. This saturation behavior follows Michaelis-Menten kinetics, just like enzyme catalysis. The Km value for a given transporter reflects its affinity for the solute. A low Km means the protein binds tightly and operates efficiently even at low concentrations. This is physiologically important in tissues that need to scavenge nutrients from dilute environments, like the renal tubules reabsorbing glucose from filtrate.
Another point beginners often miss is that facilitated diffusion is reversible. If the concentration gradient flips, the solute flows in the opposite direction through the same protein. This is not true of active transport, which pumps in one direction as long as energy is supplied. The reversibility of facilitated diffusion is straightforward thermodynamics. The protein does not care which side has more solute, only that a gradient exists. There are scenarios where facilitated diffusion simply cannot handle the job. If a cell needs to accumulate a substance against a steep gradient, passive transport will never suffice. Red blood cells maintain a relatively flat glucose gradient and rely on GLUT1 for steady-state uptake. But intestinal epithelial cells must absorb glucose from the gut lumen where concentrations can be low, and they use SGLT1 instead. The choice of transporter reflects the physiological requirement, not a hierarchy of complexity. I encountered an edge case during a lab experiment measuring glucose uptake in isolated hepatocytes. We incubated liver cells with radiolabeled glucose at various external concentrations and plotted uptake rate against concentration. The curve rose steeply at first and then plateaued, clearly showing saturation. When we added competitive inhibitors like cytochalasin B, the plateau dropped, confirming that GLUT proteins mediated the transport. But when we poisoned the cells with cyanide to block ATP production, the saturation kinetics remained unchanged. That was the moment it clicked — the transport was entirely independent of cellular energy.
The clinical relevance of this distinction is substantial. Mutations in the GLUT4 gene or defects in its insulin-triggered translocation pathway underlie forms of insulin resistance seen in type 2 diabetes. Without enough GLUT4 on the cell surface, glucose enters muscle and fat cells too slowly, and blood glucose remains elevated despite high insulin levels. Understanding that this is a facilitated diffusion defect rather than an active transport problem directs therapeutic strategies toward improving insulin signaling and transporter trafficking, not toward pumping more energy into a system that already functions fine at the protein level. Another example involves hereditary fructose intolerance. The fructose transporter GLUT5 operates in the intestinal epithelium, and mutations here impair fructose absorption through facilitated diffusion. Patients experience gastrointestinal distress because unabsorbed fructose draws water into the intestinal lumen by osmosis. The mechanism is passive, but the consequences are very real. The distinction between active and passive transport also matters for drug delivery. Some pharmaceutical compounds are designed as prodrugs that hijack existing facilitated diffusion pathways. Amino acid transporters, for instance, can be exploited to move therapeutic molecules across the blood-brain barrier. The blood-brain barrier uses GLUT1 to allow glucose into the brain, and researchers have designed glucose-mimicking drug conjugates that ride this same route. Since GLUT1 mediates passive transport, the drug enters the brain without consuming the body's energy reserves, which would be a significant limitation if an active mechanism were required.
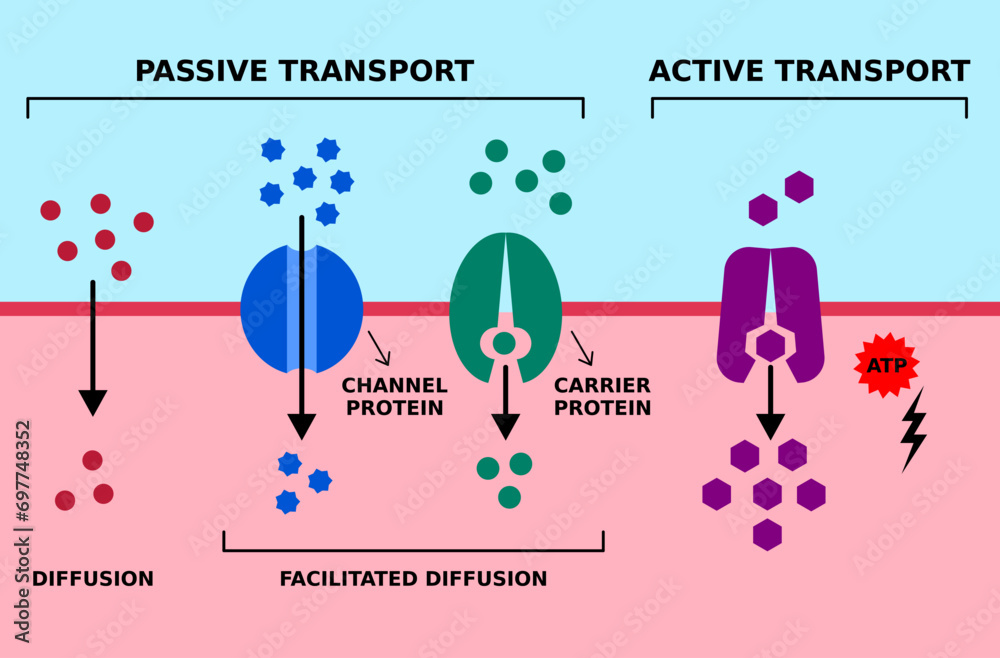
It is worth noting that facilitated diffusion has clear limitations. The cell cannot use it to create concentration differences. If you need 100 millimolar of an amino acid inside the cell and only 1 millimolar outside, facilitated diffusion will never achieve that. The gradient will equilibrate, and the intracellular concentration will at most equal the extracellular concentration, assuming no other processes remove the solute from the cytoplasm. For that, active transport is necessary. Additionally, the specificity of transport proteins means that cells must invest resources in synthesizing the right proteins for each solute they need to move. A cell that requires iron imports transferrin receptors and uses endocytosis, not facilitated diffusion, because iron handling involves oxidation state changes and storage in ferritin. The limitations of passive transport dictate the evolution of more complex mechanisms in specialized tissues. When studying for exams, a practical approach is to memorize a few canonical examples and reason from first principles. Glucose into red blood cells via GLUT1 — passive, facilitated diffusion. Glucose into intestinal cells via SGLT1 — secondary active transport. Potassium ions through leak channels — passive, facilitated diffusion. Calcium pumped out of cells by the Ca2+ ATPase — primary active transport. Each case follows logically from whether ATP is involved and whether movement is with or against the gradient.
The confusion between these categories is not a sign of weak understanding but rather a reflection of how the terminology maps onto biological reality in non-obvious ways. Proteins are involved in both passive and active transport. Both can show saturation. Both can be inhibited by specific molecules. The critical difference is energy coupling, and that difference determines whether the cell pays an ongoing metabolic cost to maintain a concentration gradient or simply waits for equilibrium to arrive. In my experience teaching this material, the most effective intervention is to have students draw concentration gradients alongside the transport proteins and label the direction of movement with arrowheads, then separately label whether ATP appears anywhere in the diagram. If the answer is no, and the arrow points down the gradient, the mechanism is facilitated diffusion, period. If ATP appears and the arrow points up the gradient, it is primary active transport. If a different gradient powers the movement without direct ATP use at the transporter, it is secondary active transport. This visual method cuts through the terminology fog in about five minutes. The broader lesson extends beyond membrane transport. Biology is full of cases where similar structures serve different functions depending on context, and the ability to distinguish based on underlying mechanics rather than surface features is a skill that applies to enzymology, signal transduction, gene regulation, and virtually every other area of cell biology. Facilitated diffusion is not a half-step between simple diffusion and active transport. It is a distinct mechanism with its own kinetics, its own proteins, and its own physiological role, and understanding it on its own terms removes the mystery entirely.