Understanding How the Hypothalamus and Pituitary Talk to Your Gonads
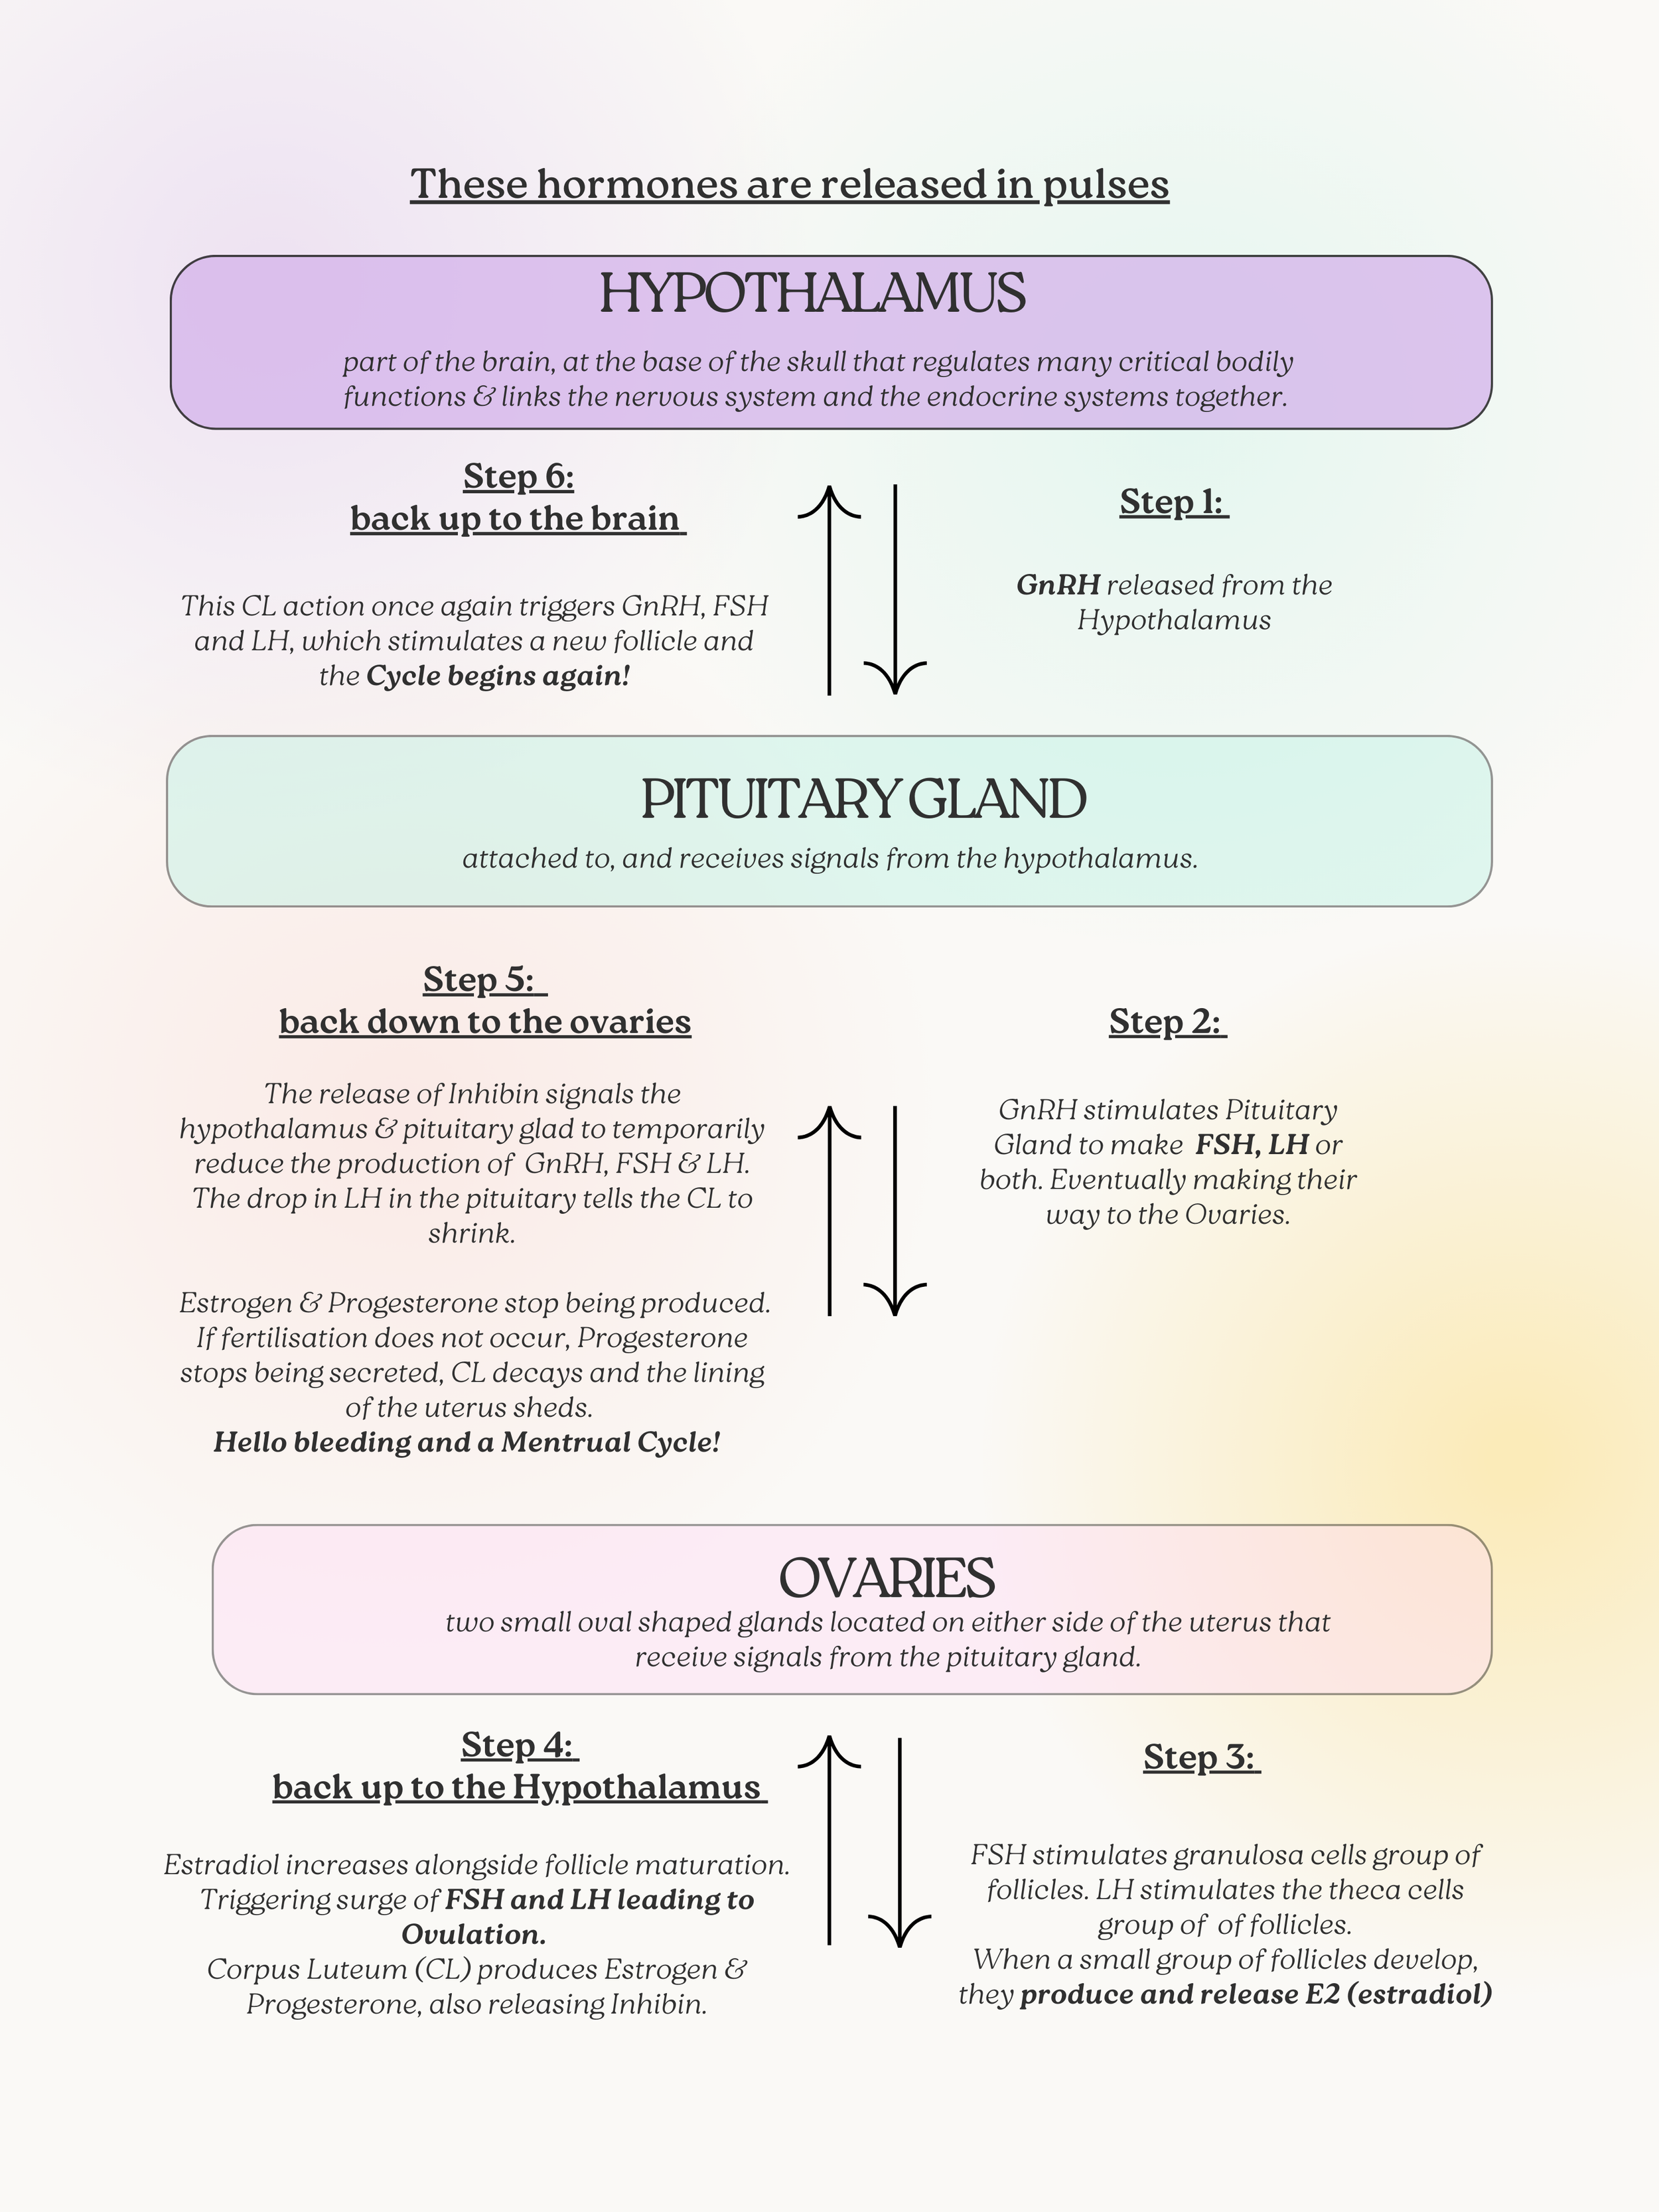
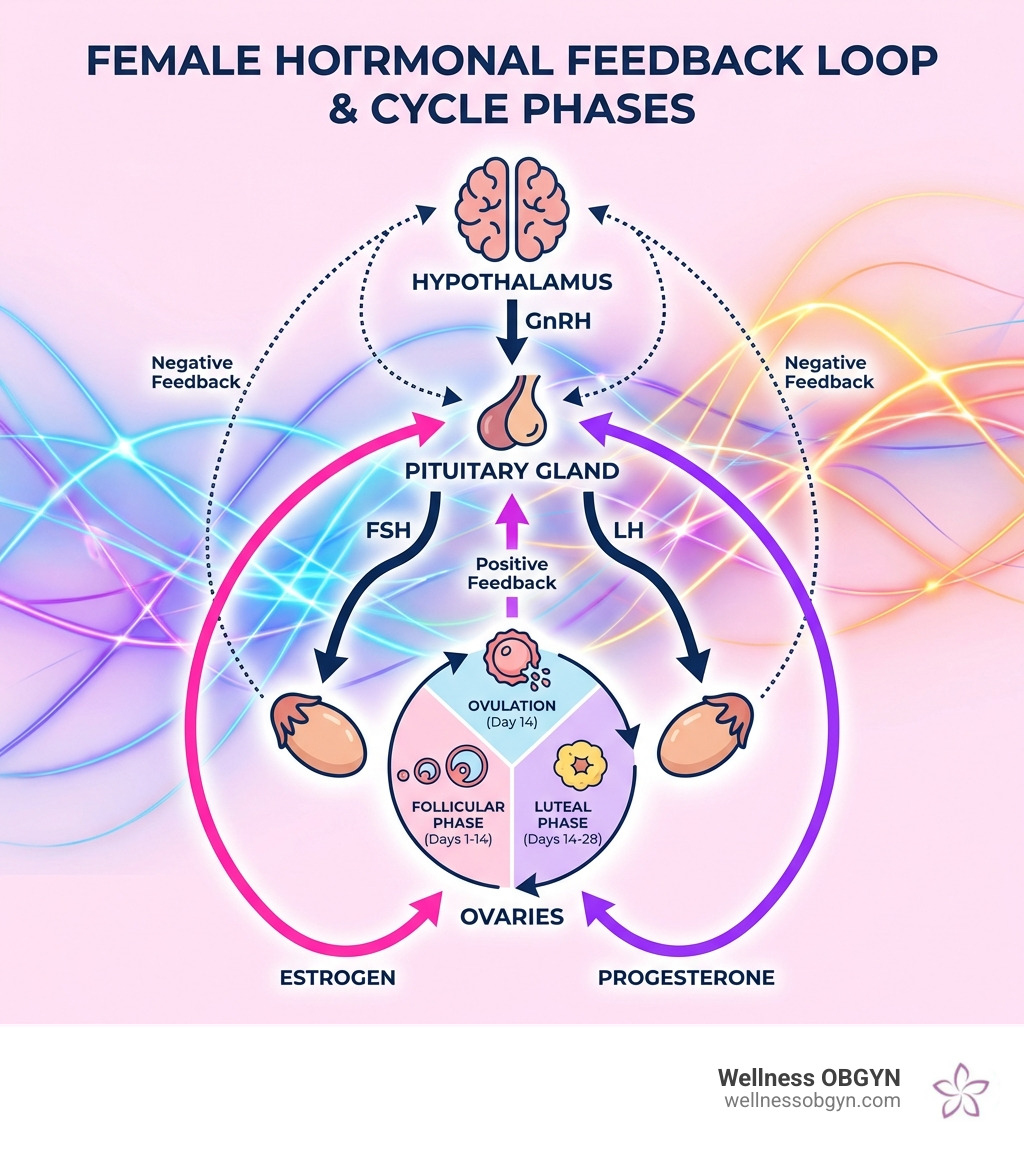
The GnRH feedback loop is one of those endocrine mechanisms that gets glossed over in textbooks but dominates clinical conversations once you actually work with patients who have hormonal dysregulation. It is not complicated in theory. The hypothalamus releases GnRH in pulses. Those pulses travel through the hypophyseal portal system to the anterior pituitary. The pituitary responds by secreting LH and FSH. Those gonadotropins then drive the ovaries or testes to produce sex steroids and inhibin. The sex steroids and inhibin feed back to both the pituitary and the hypothalamus to modulate further GnRH release. That is the loop. The practical reality of working with it is far messier. I spent years dealing with clients and patients whose lab work looked reasonable on paper but who still presented with symptoms that did not match their hormone levels. The classic example is a woman with normal basal LH and FSH but still struggling with anovulation. Most people stop at the numbers and declare the axis "normal." That is where the mistake happens. The problem was not the static values. It was the pulse frequency and amplitude of GnRH delivery itself, which standard panels do not capture. You can have perfectly adequate LH and FSH outputs while the upstream pulsatility is completely off rhythm. The practical way to approach this is to think about the loop as a dynamic oscillator rather than a static circuit. GnRH pulses occur roughly every 60 to 90 minutes in healthy premenopausal women. That interval shifts. Stress, body fat percentage, nutrition, and even sleep architecture all compress or stretch that interval. When the pulses become too frequent, the pituitary desensitizes. LH production skews higher relative to FSH. That is the mechanism behind what clinicians often casually label PCOS, when in many cases the root issue is simply altered GnRH pulse frequency driven by metabolic or stress signals upstream. When the pulses slow down too much, you get the opposite problem: low LH and FSH, suppressed ovulation, and a hypogonadal state that has nothing to do with primary ovarian failure.
I once worked with a client whose estradiol was in the low-normal range, progesterone was undetectable in the luteal phase, and her LH to FSH ratio looked borderline elevated. Standard protocol would have pointed toward a gonadotropin issue or early ovarian decline. Instead, we looked at the full picture. She was under significant life stress, sleeping poorly, and eating in a moderate caloric deficit. Her body was essentially treating reproduction as nonessential. We adjusted her energy availability, improved her sleep window, and monitored her cycle signs over three months. Her FSH normalized, her mid-luteal progesterone climbed into the functional range, and her cycle became regular. No medications were involved. The fix was removing the suppressive pressure on the hypothalamus so GnRH could resume normal pulsatility. Another angle people miss involves the negative versus positive feedback switch. Estrogen does not simply suppress the axis across the board. During the follicular phase, it exerts negative feedback, keeping LH and FSH in check. But once estradiol crosses a threshold and sustains it for roughly 36 hours, the feedback flips to positive, triggering the LH surge that precedes ovulation. That flip requires precise timing and adequate estrogen exposure. If someone has chronically low estrogen from excessive exercise, low body fat, or hypothalamic suppression, that positive feedback threshold is never reached, and ovulation does not occur. This is not theoretical. I have seen this pattern repeatedly in athletes and in people managing restrictive eating patterns. Their labs show low estradiol, low LH, low progesterone, and sometimes a slightly elevated FSH that gets misread as diminished ovarian reserve when it is actually just the hypothalamus pulling the plug on the entire system. There are also peripheral factors that distort the loop without being part of it directly. Aromatase activity in adipose tissue converts androgens to estrogens, which adds another layer of feedback complexity. This is why body composition changes can dramatically shift hormonal profiles independent of any direct intervention on the reproductive axis itself. Excess adiposity can create a state of chronic low-grade estrogenic stimulation that blunts the normal feedback sensitivity. The result is often irregular cycles, anovulation, and a lab profile that looks confusing unless you account for the adipose tissue contribution.
On the male side, the same loop operates with different reference ranges and slightly different pulse characteristics. Testosterone provides the primary negative feedback, along with inhibin B from the testes. The clinical relevance here tends to surface in cases of secondary hypogonadism, where the problem originates in the hypothalamus or pituitary rather than the testes. Kallmann syndrome is the extreme example, but milder forms of hypothalamic dysfunction are far more common and often go unrecognized because testosterone levels hover in the low-normal range while symptoms like low libido, fatigue, and reduced muscle mass persist. One counter-intuitive point worth emphasizing is that more GnRH stimulation is not always better. Continuous, non-pulsatile administration of GnRH actually suppresses the axis. This is the mechanism behind GnRH agonist therapies used for conditions like endometriosis, prostate cancer, and precocious puberty. The constant stimulation causes pituitary downregulation and eventual shutdown of LH and FSH secretion. The pulsatile nature is what keeps the system responsive. Any intervention that disrupts that rhythm, whether through chronic stress, extreme dieting, or certain medications, will disrupt the entire downstream cascade. The practical takeaway is that hormonal balance cannot be assessed accurately by looking at a single snapshot of LH, FSH, estradiol, or testosterone. You need to understand the dynamics of the loop. When labs look ambiguous, the first question should be whether the upstream signaling environment supports normal pulsatility. Sleep, caloric intake, body composition, stress load, and exercise volume all feed into that environment. Addressing those factors often resolves hormonal issues that no amount of targeted hormone supplementation can fix on its own.
Get the Full Details
For anyone trying to make sense of their own results or support someone who is, the most useful approach is to look at the pattern across multiple time points rather than fixating on individual values. A single lab draw tells you very little about a pulsatile system. Tracking cycles, noting symptoms, and repeating tests at meaningful points in the menstrual cycle provides a far clearer picture of what the feedback loop is actually doing.