What You Actually Need To Know About Balloon-Inflatable Devices in Cancer Surgery
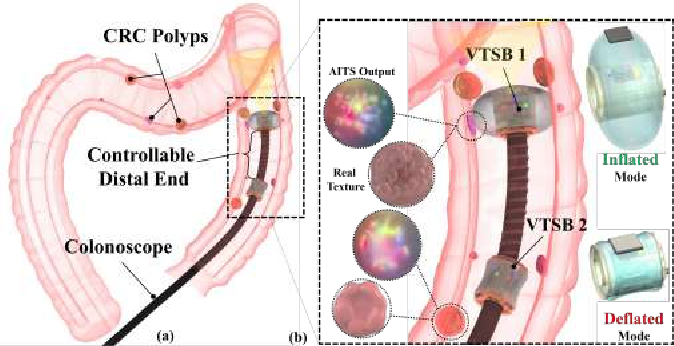
Balloon-inflatable devices have been showing up in surgical oncology more frequently over the last decade, and most people reading about them online have no idea what they actually do, let alone how they behave once they're inside a patient. I need to say this upfront: "Cancer-associated Balloon-inflatable" is not one single device or one single technology. It's a category that covers several different approaches, and the differences matter a lot when you're actually working with one in the OR. Let me explain the core idea first, then get into the specifics. A balloon-inflatable device in oncology surgery is typically a catheter-based system that gets positioned near or around a tumor. Once it's in place, the balloon inflates to accomplish whatever the clinical goal is — that could be marking the tumor boundaries for the surgeon, delivering localized treatment, creating space, or holding something steady while another step happens. The tumor itself doesn't inflate. The balloon does. The applications fall into a few buckets. Tumor localization is one. Surgeons use these balloons during minimally invasive procedures where they can't see or palpate the tumor directly. They insert the catheter, position it against the lesion, inflate gently, and then use imaging to confirm exactly where things are. The second bucket is intraoperative margin assessment. After a tumor is removed, a balloon device can be positioned at the resection site to help determine whether margins are clear. Third is localized drug delivery. Some systems use the balloon to hold chemotherapy agents or radiopharmaceuticals against a specific area. Fourth is space creation, which comes up in laparoscopic and robotic cases where the surgeon needs to separate tissue planes without cutting anything yet.
Here's the part most sources don't cover well: the inflation medium matters more than people realize. Most standard devices use saline for inflation, but in certain oncology cases, adding contrast dye to that saline makes a measurable difference in how well you can see the balloon under fluoroscopy or ultrasound. I found this out the hard way during a procedure where the balloon was nearly invisible on the imaging monitor because we'd inflated it with plain saline in a patient with a high BMI. The tumor margin was maybe two centimeters from the balloon edge and I couldn't tell if we were clear or not. We paused, withdrew the saline, and refilled with a 1:10 dilution of iodinated contrast in saline. The balloon immediately became visible on the imaging. That single change affected the entire course of the surgery.
How The Device Actually Works In Practice
The insertion process starts with image guidance. You're typically working under ultrasound, CT, or fluoroscopic guidance depending on the tumor location and the specific device you're using. The catheter gets advanced through a needle or a sheath, and you're positioning the deflated balloon adjacent to or surrounding the target area. This is where things get tricky because the balloon needs to sit in a specific plane relative to the tumor. Too superficial and you're not getting a true margin assessment. Too deep and you risk pushing the tumor or causing unnecessary trauma to surrounding structures. Inflation is done gradually. Most protocols call for small incremental volumes — I'm talking 1 to 3 milliliter increments depending on the device size and the clinical situation. You inflate, you pause for imaging, you check position, you decide whether to add more. Rushing this step is how complications happen. A balloon inflated too quickly can distort tissue anatomy, making it harder to assess margins accurately rather than easier. I've seen it happen more than once where the operator wanted to move fast because the patient was stable and everything looked straightforward, and the inflated balloon pushed the tumor into an adjacent structure that wouldn't have been affected otherwise. The result was ambiguous margins and a longer surgery than necessary. Deflation and removal follow a similarly careful process. You withdraw the inflation medium slowly while continuously monitoring with imaging. The balloon collapses and then you retract the catheter. If the device has a secondary function like drug delivery or radiation application, that step happens while the balloon is inflated and in position, which is why the timing and volume precision matters so much.
Get the Full Details
Common Pitfalls And What To Watch For
Balloon rupture is the most obvious risk, but it's also the least common problem with modern devices. What actually causes trouble more often is balloon migration. The balloon can shift after inflation, especially if the tissue planes are loose or if there's significant fluid movement in the operative field. I dealt with a case where the balloon migrated approximately 1.5 centimeters between my initial positioning and when I went to take post-inflation imaging. The migration wasn't dramatic enough to be obvious, but it was enough to throw off my margin assessment. The workaround was simple: after inflation, I taped the catheter external portion to the skin at the insertion site to prevent any movement, then took imaging immediately. Nothing fancy. Just restraint. Another issue is overinflation beyond the device's rated volume. Every balloon has a maximum safe inflation volume specified by the manufacturer. Going past that point doesn't just risk rupture — it can cause tissue ischemia at the contact points. The balloon presses against tissue and restricts blood flow. In oncology surgery where you're already dealing with compromised tissue around tumors, adding pressure ischemia to the mix isn't something you want to happen. The fix is reading the device specifications before you bring it into the OR and marking the maximum volume on the syringe with a permanent marker so you can't accidentally go past it. There's also the issue of uneven inflation. Balloons don't always expand symmetrically, especially if they're pressed against a firm mass like a tumor. One side might inflate more than the other, creating an uneven pressure distribution. This matters most for margin assessment because the side with less inflation might be sitting further from the actual tumor edge than you think. The solution is checking inflation symmetry under imaging before you proceed with whatever the next step is.
Device Selection And Limitations
Not every balloon-inflatable system works for every situation. The choice depends on tumor location, size, proximity to critical structures, and what you're trying to accomplish. Small peripheral lung tumors respond differently to balloon guidance than large central liver masses do. The device needs to match the anatomy. Some systems are designed for shallow, surface-level positioning while others are built for deeper, more conformal placement. Using the wrong one for the job leads to the kinds of problems I described above. The biggest limitation of balloon-inflatable devices in oncology is that they provide spatial information, not biological information. A balloon can tell you where the tumor boundary appears to be based on imaging and physical displacement, but it cannot tell you whether cells at the edge of what looks like a clear margin are actually cancerous. That requires histopathology. I've encountered situations where the balloon suggested a 5-millimeter margin was clear, but frozen section later showed positive cells within that 5 millimeters. The balloon was doing its job correctly — it was showing anatomical position — but anatomy and pathology don't always align perfectly. This is a fundamental limitation that no amount of technique improvement will solve. If you're working with devices in this category, the practical advice is straightforward. Get familiar with the specific device you're going to use before you need it. Run through the inflation and deflation cycles on a bench or simulation model. Know the maximum volumes, the inflation medium options, and the migration risks specific to that product. Check that your imaging equipment can visualize the balloon with whatever inflation medium you plan to use. And keep a second device available in case the first one fails or behaves unexpectedly. Things do fail in the OR, and having a backup ready takes thirty seconds to set up but can save you from a prolonged delay when it actually matters.
The technology itself is mature enough that the variables aren't the device — they're the operator's understanding of what the device can and cannot do, and the specific clinical context it's being applied to. Knowing that distinction makes the difference between a procedure that goes smoothly and one that drags on because someone learned something the hard way.