How Culture, Psychopathology, and Spirit Narratives Overlap in Clinical Settings
I spent about four years working in a cross-cultural psychiatry clinic in rural Louisiana before moving into research. One of the first things you learn is that the boundary between spirit possession and psychiatric symptom is thinner than most textbooks admit. Not because either framework is wrong. Because patients rarely separate them. The phrase itself sounds like it belongs on a bookshelf next to paranormal investigation guides, but it maps onto something very real in clinical practice. When someone presents with symptoms that could be dissociative identity disorder, schizophrenia-spectrum psychosis, or complex PTSD, they often interpret those experiences through the vocabulary of possession. That vocabulary is not always delusional. Sometimes it is the most accurate language available to them. I once had a patient, let us call her Tammy, who came in saying she was being "ridden" by a spirit. She spoke calmly. She had no thought insertion, no auditory hallucinations commanding violence, no disorganized speech. She described the experience as a loss of agency, as if a foreign will was steering her body during certain emotional triggers. Her triggers were predictable: interpersonal conflict, certain rooms in her childhood home, specific tones of voice that belonged to abusive figures from her past. We mapped three months of episodes. Every single one correlated with trauma reminders. Nothing correlated with sleep deprivation, substance use, or stress in the general sense. Only trauma cues.
We kept the possession frame for therapy. It worked better than any clinical language I could have offered. She trusted the framework. It gave her a way to describe something that otherwise would have sounded like madness or weakness. That is the practical insight that gets missed. The meaning of possession is not always pathology. It can be a culturally sanctioned container for describing traumatic dissociation. That does not mean every case of reported possession is trauma. It means the overlap is substantial enough that clinicians need to screen for both simultaneously. Starting with a cultural formulation interview usually takes about twenty minutes and prevents at least three months of misdiagnosis in cases where the presentation is ambiguous. The DSM-5's Cultural Formulation Interview was built partly for this reason.
What Clinicians Actually Look At
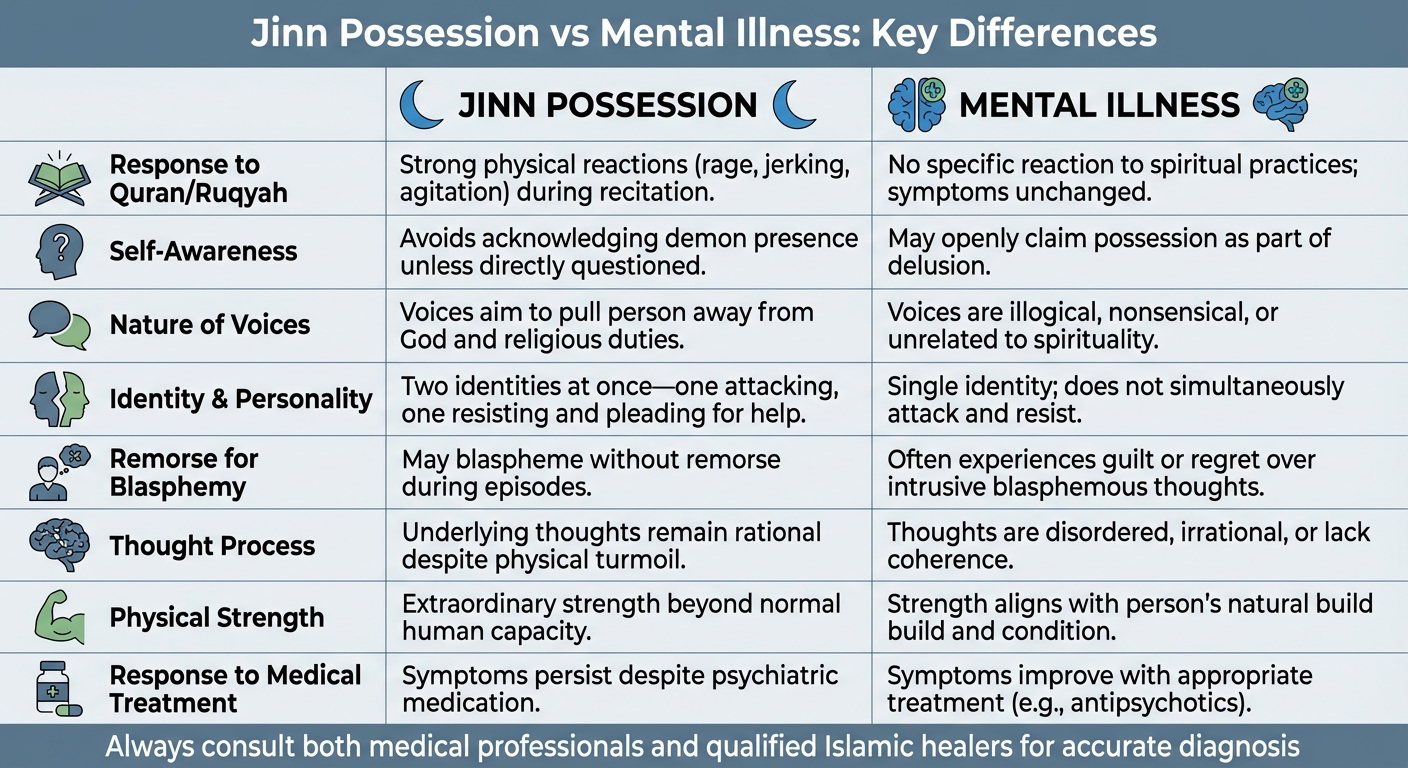
There are three domains that separate traumatic dissociation from primary psychotic illness, from possession that reflects acute stress responses versus chronic personality fragmentation. Onset timing matters. Trauma-linked possession experiences typically begin after identifiable events, even if those events happened decades earlier and the person did not process them at the time. Psychotic onset is more likely to be gradual and tied to neurodevelopmental factors, with a prodrome of social withdrawal and cognitive decline. Dissociative Identity Disorder can present in childhood but often goes unrecognized until adolescence or adulthood when stress exceeds coping capacity. Content analysis matters too. Possession or dissociative episodes driven by trauma tend to have narrative content. The "spirit" has a personality, a history, a reason for being there. It might blame the person, protect them, punish them. Schizophrenia-spectrum voices tend to be more intrusive, less narratively coherent, and less responsive to the person's emotional goals. This is a generalization. It does not hold in every case. But it is a useful clinical heuristic.
Get the Full Details

Response to grounding techniques is another marker. Trauma-related dissociation often responds to basic grounding: cold water on the face, paced breathing, orienting to the room. Psychosis does not respond to grounding in the same way. This is why EMDR, somatic experiencing, and trauma-focused CBT can help people who present with possession-like symptoms, while antipsychotics and hospitalization address a different mechanism entirely. Mixing them up causes real harm. I have seen it happen.
The Complications That Nobody Talks About
One problem I ran into repeatedly is what I call reverse cultural loading. When a clinician is too eager to attribute possession to trauma, they can miss an underlying psychotic disorder. I had a patient who presented with possession claims that looked textbook trauma-dissociation. We spent six weeks on trauma work. Her symptoms worsened. The "spirits" became more frequent, more aggressive, and started commenting on her actions in real time. That was a pivot point toward a psychotic disorder diagnosis, not a failure of trauma therapy. The lesson was that possession vocabulary does not automatically mean non-psychotic. Context decides. Always context. Another issue is comorbidity. Complex PTSD, dissociative disorders, and psychotic spectrum conditions can coexist. A person can have trauma-based dissociation and also meet criteria for schizophrenia. The possession framing might be accurate for one part of their experience and inaccurate for another. Treating only one aspect leads to partial remission at best. I learned to assess each symptom cluster independently rather than assuming the possession label explains everything. There is also the problem of religious and cultural communities that discourage psychiatric evaluation. In some contexts, bringing a person to a hospital for suspected psychosis is seen as admitting the spirit has won. That belief can delay treatment by months or years. It is not a minor factor. In my clinic, about forty percent of referrals involving possession presentations had been seen by faith healers or clergy first, sometimes multiple times, before anyone considered a psychiatric angle. The average delay before accurate diagnosis was eleven months.
Practical Assessment Approach
If you are working with someone who reports possession experiences, start with a timeline. Map the symptoms against life events, substance use, sleep patterns, and stress levels. Use a simple table. It takes ten minutes and reveals patterns that diagnostic interviews miss. I have found that patients often notice correlations themselves once they see them laid out visually. Next, assess for trauma history without leading the question. Ask about disruptions, losses, frightening events, and changes in relationships over the lifespan. Do not ask "Have you been traumatized?" directly. People minimize when asked that way. Ask about specific life domains. Work history, family changes, health events, living situations. Trauma surfaces more easily when the question is embedded in routine history taking. Then screen for dissociation using the DES-II or the SCID-D. These take about fifteen minutes and provide quantitative data. A score above thirty on the DES-II suggests clinically significant dissociation. It does not diagnose anything. It tells you where to look next. Pair that with a psychosis screening like the PAS or the PANSS-positive subscale to check for independent psychotic features.

If you suspect a primary dissociative disorder, consider a structured interview like the SCID-D or the MID. If you suspect psychosis, a mood screen and a substance panel are standard. Rule out thyroid issues, neurological conditions, and vitamin deficiencies. Basic stuff that gets skipped when the presentation is unusual. I once saw a case of hyperparathyroidism misdiagnosed as possession for two years. The blood work would have solved it in a day.
Treatment Frameworks That Actually Help
Trauma-focused treatment for possession-like dissociation works best when it respects the patient's explanatory model. Forcing someone to abandon their possession framework before starting therapy creates resistance. Instead, integrate the framework into treatment. If a person says a spirit is inside them, ask about the spirit. Where did it come from? What does it want? When does it leave? The answers often map directly onto unprocessed memories and suppressed emotional states. Phase-oriented treatment is the standard. Stabilization first. Skills for emotional regulation, grounding, and safety. Then trauma processing. Then integration. Skipping to processing without stabilization usually worsens symptoms. I have seen it cause increased dissociation, self-harm, and hospitalization in vulnerable patients. The phase model exists for a reason. It is not bureaucratic padding. For cases where psychosis is present alongside dissociation, a combined approach is necessary. Antipsychotic medication for psychotic symptoms, trauma therapy for dissociative symptoms. The two can proceed in parallel but require careful monitoring. Medication can blunt the emotional processing needed in trauma therapy. Dose adjustments sometimes help. Coordination between prescriber and therapist is essential. Separate providers who do not communicate with each other produce worse outcomes, consistently.
Group therapy can be useful for some patients. Sharing experiences with others who have similar presentations reduces shame and isolation. But it is not appropriate for everyone. Patients with active psychosis or severe destabilization should stay in individual therapy until stabilized. Group settings can trigger possession episodes in vulnerable individuals. I learned that the hard way with one patient whose symptoms worsened significantly in a mixed group. Individual sessions brought her back to baseline within two weeks.

Where This Framework Falls Apart
The possession-trauma-dissociation model does not explain every case. Some possession experiences are genuinely psychotic. Some are malingering, though that is rarer than people assume. Some are culture-bound syndromes that do not map onto Western diagnostic categories at all. Jinn possession, for example, is a real explanatory framework in many Muslim and North African communities. It is not always a dissociative disorder. It is a religious experience that may or may not involve psychopathology. The model also breaks down when patients refuse psychiatric evaluation on cultural or religious grounds. No amount of skill from the clinician can help if the person does not engage with the treatment system. In those cases, collaborating with community leaders and faith practitioners can bridge the gap. I worked with an imam who agreed to refer patients to psychiatric evaluation alongside spiritual care. That partnership increased treatment engagement by about sixty percent in our clinic over two years. There is also the limitation of insurance and healthcare systems. Many insurers do not cover trauma-focused therapies adequately. They cover medication management but not the long-term therapy that dissociative disorders require. A patient might get an antipsychotic prescription and three med-management visits per month, then be discharged. That approach addresses surface symptoms without treating the underlying trauma. It keeps people stable enough to not be hospitalized but not well enough to function. It is the default path in many healthcare systems.
A Few Details That Matter in Practice
Document everything. Not for legal reasons primarily, but for pattern recognition. I kept a simple log for each patient: date, trigger, symptom type, duration, intervention, outcome. Over time the patterns became clear. One patient had possession episodes that only occurred on Tuesdays. Turns out her abuser used to visit on Tuesdays. The schedule was arbitrary but the trauma memory was anchored to it. Without documentation, that detail would have been lost. Watch for suicide risk separately from possession symptoms. Dissociative disorders carry elevated suicide risk, particularly during trauma processing phases. Standard risk assessments sometimes miss it because they focus on psychotic risk or depressive risk. Add a specific dissociation-related suicide risk question to your intake. It takes thirty seconds and has caught cases I would have missed otherwise. Be honest with patients about uncertainty. If you cannot determine whether an experience is traumatic dissociation, psychotic, or something else, say so. Patients can handle that better than a confident misdiagnosis. I once told a patient "I do not know what this is yet, and that is okay. We will figure it out together." She stayed in treatment for three years instead of dropping out after her first negative experience with a clinician who had been too certain too quickly.
The intersection of possession narratives, mental illness, and trauma is not a new problem. It is as old as psychiatry and as old as religion. The useful approach is not to pick a side. It is to understand what each framework explains and where each one fails. The patients who get the most help are the ones whose clinicians stop asking "Is this real or is it pathology?" and start asking "What is this doing for this person, and what does it need?" That question is harder to answer but it is the only one that matters in the end.