Drug Screening Reality: What Actually Moves the Needle
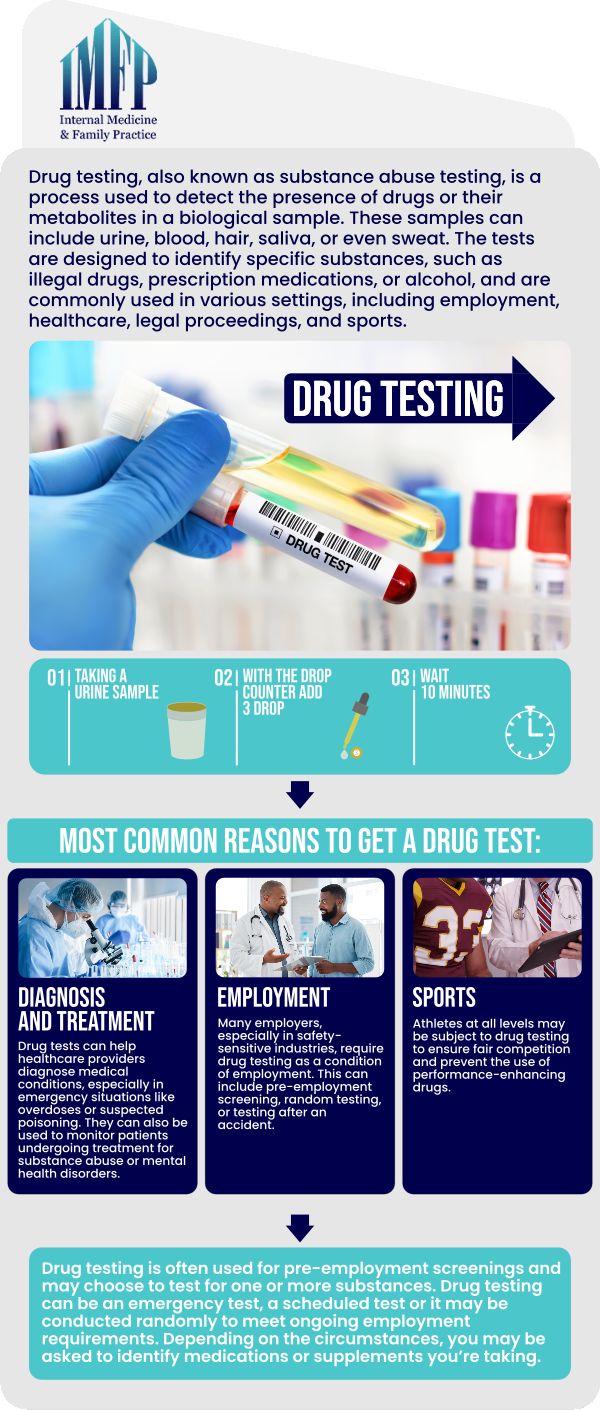
I spent eight years running pre-employment screens for a regional staffing firm. We processed roughly 400 tests a month across multiple employer sites. The people who kept coming back with questions weren't interested in compliance — they wanted to know how to circumvent the process. That's where sites like Drugtestcheck.com come into the picture, whether people are recommending them or warning against them. Let me explain how drug screening actually works before we get into the tools people use around it.
Unmasking Truth How Drugtestcheckcom Powers Precision Drug Screening
The site functions as an information hub. It aggregates data about drug testing methodologies, detection windows, and the products or methods people use to influence results. It doesn't run tests itself. It's a content platform that reviews dilution kits, synthetic urine products, mask agents, and educational guides about the testing lifecycle. The "precision" angle comes from understanding how different testing protocols — immunoassay screening versus GC/MS confirmation — create different vulnerability points. Here's how the process actually breaks down in practice.
How the Testing Pipeline Works
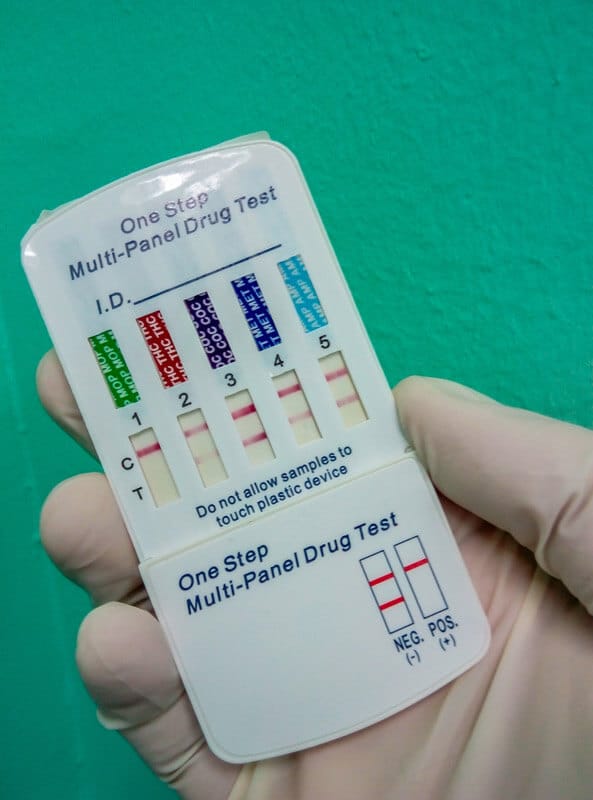
A standard workplace drug screen follows a two-tier model. First, the specimen hits an immunoassay cup or cartridge. This is the rapid screen. It looks for class-level presence of drug metabolites — THC-COOH, benzoylecgonine, oxycontin metabolites, and so on. The cutoff levels are set by SAMHSA guidelines for federally regulated tests: 50 ng/mL for the initial screen on most panels, 15 ng/mL for THC specifically in some newer panels. If the screen comes back positive at or above cutoff, the sample goes to a laboratory for gas chromatography/mass spectrometry confirmation. This is where the "precision" part happens. GC/MS can identify the exact molecular signature of a substance. It can distinguish between passive exposure and actual use. It can detect substances at concentrations as low as 10 to 15 ng/mL, sometimes lower depending on the lab's validation. The immunoassay is the weak point. It's designed for speed and cost, not accuracy. Cross-reactivity is real. Some over-the-counter medications trigger false positives on certain antibody-based screens. Ibuprofen has been known to flag on THC screens in older immunoassay formats. Pseudoephedrine can show up on amphetamine panels. The confirmatory test catches these errors, but the initial screen is where most of the noise lives.
Get the Full Details

What People Actually Use to Navigate This
The products and methods discussed on Drugtestcheck.com generally fall into three categories, and each has a different level of practical effectiveness depending on the test type and the laboratory's verification protocols. Dilution products work by increasing the volume of urine output while lowering metabolite concentration below the screening cutoff. The mechanism is straightforward — drink more water, take diuretics, use validated dilution kits that contain creatinine and specific gravity buffers. The problem is that modern labs check for dilution. They measure creatinine levels (must be above 20 mg/dL for a valid specimen), specific gravity (should fall between 1.001 and 1.020 for non-diluted urine), and pH. A dilute sample gets reported as dilute, not negative. Most employers treat a dilute result the same as a positive — they require a retest under observed conditions. Synthetic urine is the second category. These are manufactured urine substitutes designed to match the chemical composition of real human urine. The better products on the market include urea, creatinine, uric acid, and the right electrolyte balance. Temperature matching is critical — fresh urine comes out at body temperature, approximately 90 to 100 degrees Fahrenheit. If you're using a synthetic product, you need a heating element or a warm pocket to get it to that range within the two-minute window the collection officer is watching.
I ran into a specific edge case with synthetic urine about three years ago. We had a candidate whose sample tested perfectly clean on the screen but registered an unusual creatinine-to-urea ratio during the lab's validity testing. The lab flagged it. The candidate had used a high-quality synthetic product but hadn't accounted for the fact that some synthetic formulations have different creatinine profiles than human urine. The workaround would have been to mix a small amount of real urine into the synthetic sample to normalize the metabolite ratios, but that introduces its own problems if the real urine contains any trace metabolites from the person's actual use. Masking agents are the third category. These are chemical additives designed to interfere with the immunoassay reaction. Some contain oxidizing agents that break down metabolite molecules. Others use peroxidase-based chemistry. The issue with masking agents is that they don't just affect the target drug — they can alter the specimen's pH, creatinine, and other validity parameters. Labs are increasingly running extended validity panels that catch these alterations. A specimen with abnormally high nitrites or an impossible pH level gets rejected outright.
The Counter-Intuitive Stuff Beginners Miss
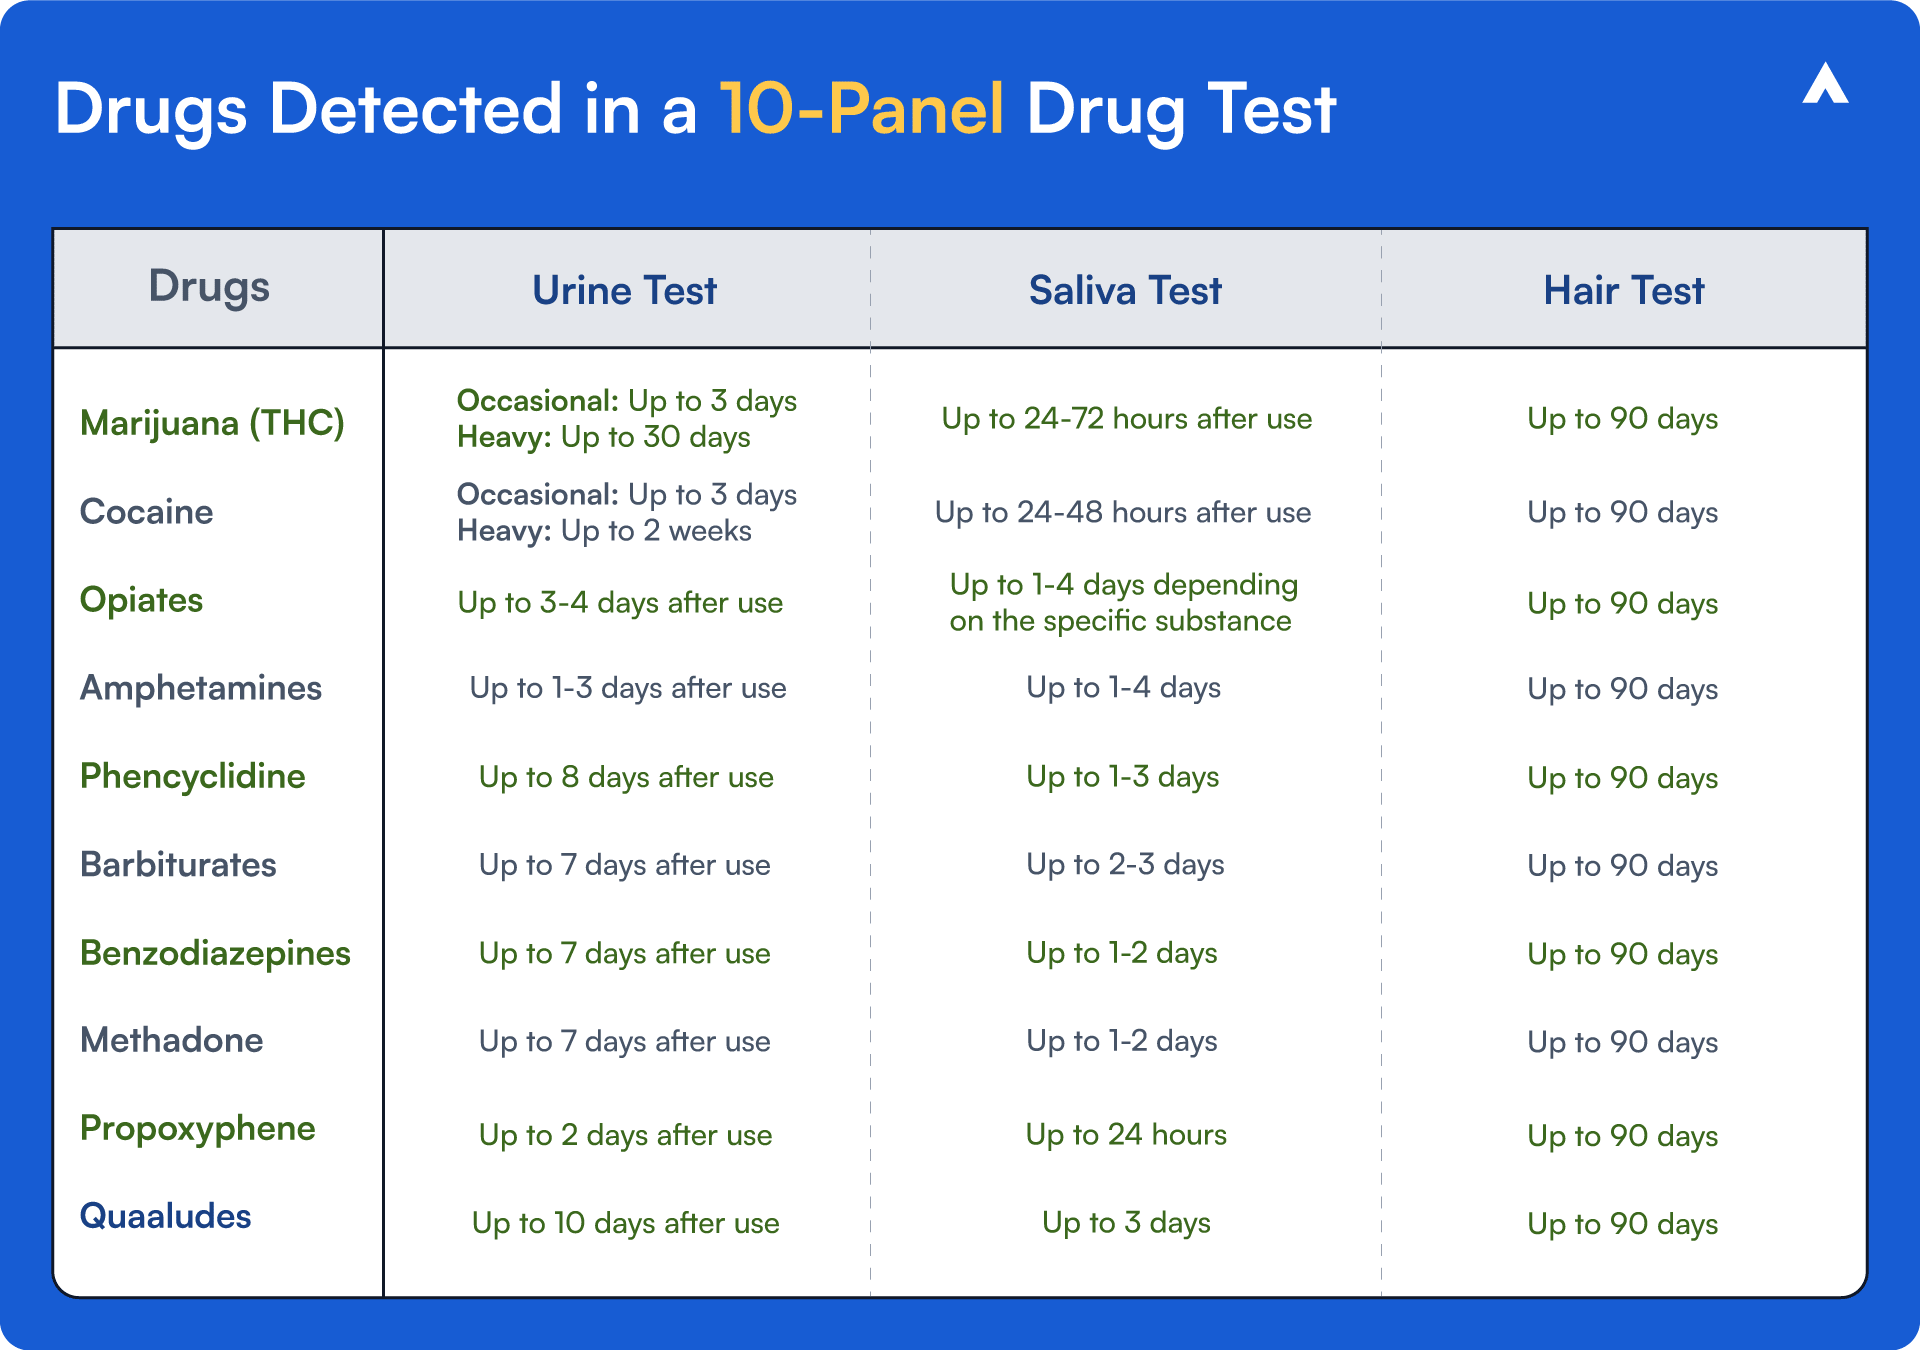
Most people approaching this topic focus entirely on the drug itself. They don't understand that the testing infrastructure has evolved significantly in the last decade. Here are a few things that aren't obvious. Detection windows vary wildly by individual. The standard advice is that THC shows up for 3 to 30 days after use. That range exists because it's accurate. A casual user who smoked once might clear in 3 days. A daily user with high body fat percentage could test positive for 45 days or more. THC metabolites are lipophilic — they bind to fat cells and release slowly. Body composition matters more than anything else. I've seen construction workers with high muscle mass and low body fat clear THC faster than office workers with higher body fat, even when both reported similar usage patterns. Hydration is a double-edged sword. Drinking excessive water before a test does dilute your urine, but it also triggers the dilute-specimen protocols I mentioned. The sweet spot that actually works is normal hydration maintained over several days, not chugging two liters right before the test. Consistent moderate fluid intake keeps metabolite concentrations naturally lower without triggering validity flags. This is the method most people overlook because it's boring and requires discipline rather than a quick fix.
Home test kits are fundamentally different from lab tests. The cheap dip cups you buy online use less specific antibodies than the lab-grade immunoassays. Cross-reactivity rates are higher. A home test might show negative while a lab confirms positive, or vice versa. If someone is relying on a home test to gauge their status before a real screening, they need to understand that the home test is not a reliable predictor of lab results. The gap between a $15 strip and a $200 lab panel is significant.
What This Approach Actually Fails At
I need to be blunt about the limitations here. No method discussed on Drugtestcheck.com or anywhere else is foolproof against a properly administered test. Observed collections eliminate the substitution method entirely. When a collection officer watches the sample go into the container, you can't swap it. Synthetic urine, clean specimens, whatever — it's not an option. The only path through an observed collection is time and abstinence. Federally regulated DOT tests have the tightest chain-of-custody protocols in the industry. The specimen is logged, tracked, barcode-scanned at every handoff, and stored at the lab. Tampering attempts are documented. Labs running DOT panels use extended validity testing that checks for creatinine, specific gravity, pH, oxidants, halides, and artificial hemoglobin. A specimen that fails any of these validity markers gets reported as adulterated, which carries the same employment consequences as a positive result in most DOT contexts.
The timeline problem is real too. If someone needs to pass a test in 48 hours, no amount of product or technique is going to reliably clear a significant THC load from their system. The body metabolizes what it metabolizes. Detox products can support the process, but they can't accelerate liver enzyme activity beyond its natural limits. Anyone selling a 48-hour guaranteed clean for heavy chronic use is selling something that doesn't exist.
Practical Takeaway
If you're preparing for a drug screen, the most effective approach combines a few things. Know what test you're taking — SAMHSA-5 panel, expanded opioid panel, individual substance test. Understand the cutoff levels. Maintain normal hydration for three to five days beforehand. Eat clean, avoid the substance entirely, and don't rely on home test strips as your final gauge. If you're a chronic user facing a test in under two weeks, the math is against you regardless of what products you buy. Drugtestcheck.com and similar resources can help you understand the landscape. They can tell you what validity parameters labs check and what products attempt to influence those parameters. But the reality is that the testing infrastructure has gotten progressively better at catching interference. The most reliable strategy isn't the most creative one — it's the one that gives your body time to do what it's already designed to do.