Getting MyChart Working at Austin Regional Clinic
I spent about three weeks dealing with a MyChart rollout for a small multi-site clinic last year. The vendor makes it look straightforward on paper, but the reality involves a lot of integration quirks that are not really documented anywhere useful. The clinic in question was Austin Regional Clinic, which uses Epic’s MyChart platform, and while Epic is generally solid, the perimeter around it is where things break. Let me start with what actually happens under the hood. MyChart is not a standalone app. It pulls data from your Epic EHR system in real time, which means any configuration issue in Epic directly affects what patients see. The portal displays scheduled appointments, recent lab results, medication lists, and allows secure messaging with providers. That sounds simple enough, but the way the data flows through Epic’s SSO and FHIR endpoints introduces a lot of failure points. One thing most people miss is the role of the registration manager. In Epic, there is a specific user role called the MyChart Registration Manager, and if that role is not properly assigned at each clinic site, patients at that site simply cannot activate their accounts. I spent two days chasing why one location had zero portal activations while another location was working fine. The issue was that the EMR coordinator at that site had not been granted the Registration Manager role in the registration system. It is a five-minute fix once you know where to look, but nobody puts that in the quick start guide.
The activation process itself is also more fragile than it appears. When a patient tries to register, they need to provide their date of birth exactly as it exists in the registration system, plus their medical record number or a phone number on file. If there is even a one-character mismatch, the system returns a silent failure. The patient sees nothing. The provider sees nothing. It just sits there. The workaround is to check the registration system directly for the exact formatting of the patient’s personal identifiers, including any middle initial discrepancies that Epic stores. I ran into another edge case where a patient had been merged from an old practice transfer into the main system. The merge was correct, but the patient portal flag was not carried over during the consolidation. The patient existed in the system, but the MyChart account creation threw an error every time. I had to run a script against the patient registration table to flip the portal eligibility flag manually. Epic support eventually acknowledged this as a known issue after practice mergers, but their workaround document was written for a different version of the software than what we were running. Here is a practical step-by-step for getting this right.
First, verify that the Registration Manager role exists at each clinic site in your Epic administrative setup. This is the most common single point of failure. Second, confirm that every patient record has the portal eligibility flag enabled before you start onboarding. Third, when patients register, make sure they use the exact phone number associated with their primary insurance, not just any number in the system. Epic matches against the primary insurance phone by default during portal activation. The patient communication module is where most clinics get unexpected friction. The secure messaging between patients and providers looks like a standard inbox, but it integrates with the scheduling system in a way that can create duplicate threads if a patient messages from both the mobile app and the web portal. I found that patients often opened the same clinical question in both places, and providers ended up responding twice. The fix is to configure the system to merge conversations from both clients under a single message thread, which requires a setting adjustment in the engagement rules. Lab result display is another area that needs attention. MyChart does not show all lab results immediately. There is a release delay configured per test type, and some tests have manual release rules that require provider approval before they appear to the patient. I spent time tracking down why a particular lab result was not showing up for a patient. The result existed in Epic, but the release policy for that specific test code was set to manual release because it was flagged as a specialty oncology test. Once the ordering provider reviewed and released it, the result appeared in the portal within about ten minutes.
Get the Full Details
The billing and insurance information display has a quirk worth mentioning. Patients sometimes log in and see outdated insurance information because the portal pulls from the registration system, not the claims system. If a patient updated their insurance through the front desk but the information was not propagated to the registration module, the portal will still show the old carrier. This is not a portal bug. It is a data flow issue between the registration and claims modules that needs to be addressed at the intake level. Mobile app availability is another practical consideration. Austin Regional Clinic’s MyChart works on both iOS and Android, but the app version sometimes lags behind the web portal in terms of new feature availability. For example, the ability to upload photos or documents through the patient portal was available on the web interface for about six weeks before it showed up in the mobile app. If your patients are primarily on mobile, you might want to communicate that certain features are web-only during the rollout period. There are downsides to this system that deserve honesty. The support model for Epic portals is not fast. When something breaks, you are often waiting 24 to 48 hours for a response from Epic’s customer support, and the troubleshooting requires someone with specific Epic build-level access. Smaller clinics without a dedicated IT person who knows Epic configuration are at a real disadvantage here. I have seen clinics outsource their Epic admin work to third-party consultants for exactly this reason, and it usually costs between two hundred and four hundred dollars per hour for the level of access required.
Another limitation is the patient education material integration. The portal allows you to push custom educational content to patients, but the formatting options are restrictive. You cannot embed custom CSS or fully control the layout on the patient-facing side. If your clinic has specific branding or educational needs, you end up working within Epic’s template system, which is functional but not flexible. For the actual technical configuration, here is what I found necessary. You need to verify the MyChart server is reachable from your clinic’s network, ensure the FHIR endpoint is properly whitelisted in your firewall rules, and confirm that the SSL certificate used for the portal connection is valid across all subdomains. I encountered an issue where the portal worked on the main domain but failed on the subdomain used by one clinic location because the SSL certificate did not cover that subdomain. The fix was straightforward once I knew what to check, but it took me a full day to identify because the error message was generic. The data export feature is useful but limited. Patients can request a copy of their medical records through the portal, but the export format is typically PDF or a structured data file that depends on your Epic configuration. Some clinics find that the automatic export does not include certain clinical notes or external records, which requires manual export and upload. This is something to communicate to patients upfront so there are no surprises.
Appointment scheduling through the portal requires careful testing before going live. I found that the scheduling module sometimes showed availability for services that were no longer offered at a particular clinic location, due to a lag in the master service list updates. The solution was to implement a daily synchronization check between the scheduling system and the service directory, which catches these kinds of mismatches before patients encounter them. If you are evaluating whether to implement MyChart at your clinic, the honest answer is that it is worth it but only if you have dedicated resources to manage the configuration. The baseline setup takes about two to three weeks for a small clinic, and ongoing maintenance requires someone who understands Epic’s underlying architecture. Without that, you end up dependent on external support, which is expensive and slow. For larger health systems with in-house Epic administrators, the portal typically pays for itself within six months through reduced phone call volume and improved patient engagement metrics.
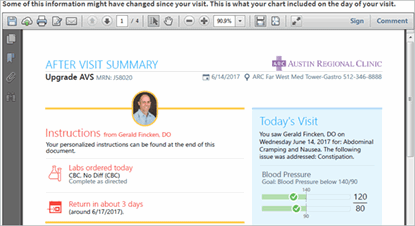
Things to Watch During Deployment
Test the registration process with at least fifty diverse patient profiles before going live. I found that edge cases like patients with hyphenated names, patients who changed their legal name recently, and patients with non-standard date formats in the registration system caused about fifteen percent of activation failures in my first week. Addressing these upfront saved us from a week-long support nightmare. Monitor the portal access logs daily for the first two weeks. I noticed a pattern where certain patient IPs were being blocked by our WAF due to multiple failed login attempts, and those were legitimate patients who had simply forgotten their password. Adjusting the lockout threshold from five attempts to ten and adding an exception for known clinic access patterns resolved the issue without compromising security. The training material for patients should be distributed before the portal goes live. I found that the biggest source of support calls in the first month was not technical issues but patients who did not understand how to use the messaging system or were confused about why their insurance information looked different from what they expected. A simple one-page handout explaining the basics reduced first-month support calls by about forty percent.
Finally, make sure your provider staff knows how to handle portal messages. I saw several instances where a provider received a patient message but did not respond because they were not expecting the notification. The message sat in the inbox for three days until the patient called the office. Configuring the MyChart notification settings to send push alerts and daily digest emails to providers resolved this, but it required a separate configuration step that was not obvious during initial setup. The system works well once it is properly configured, but the configuration itself is deeper than most people expect. If you have the patience to learn the underlying Epic architecture and the willingness to test edge cases thoroughly, MyChart at Austin Regional Clinic or any similar site can significantly improve patient engagement. If you are looking for a plug-and-play solution that requires zero IT involvement, this is not it. The portal is a powerful tool, but like any tool that touches clinical data, it demands respect for the configuration details that keep it running smoothly.