Getting an autism assessment through Clinical Partners isn't a DIY project and you shouldn't treat it like one
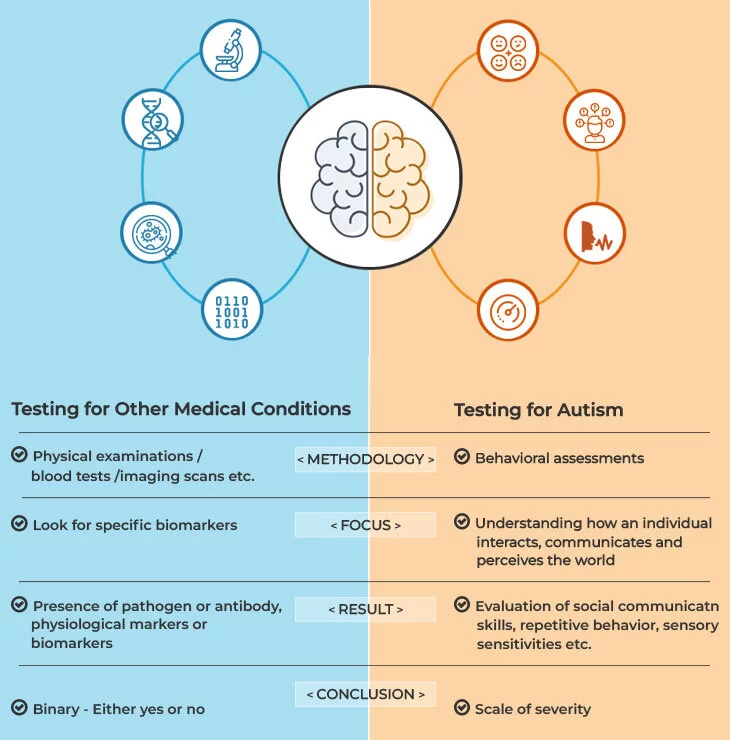
Clinical Partners runs autism assessments in the UK and a few other locations. They use standardised tools like the ADOS-2 and the ADI-R, which are the actual instruments clinicians use to make a diagnosis. The whole process usually takes two to three appointments spread over a couple of weeks, and the final report runs anywhere from fifteen to thirty pages depending on complexity. If you're looking at self-referral pathways, wait times vary wildly by region. Some NHS routes have people waiting eight to eighteen months. Private assessments through Clinical Partners typically move faster, but you're looking at costs in the region of two thousand to three thousand pounds for a full adult assessment. Here is the practical reality of how it works. You book an initial consultation where they go through your history, developmental background, and any previous assessments. Then comes the observation session, which is the ADOS-2 part. This is a structured set of tasks and conversations designed to elicit behaviours relevant to autism diagnosis. It takes roughly sixty to ninety minutes. After that, they compile everything into a diagnostic report. Some people also complete the AQ or RAADS-R questionnaires beforehand, though these are screening tools, not diagnostic instruments on their own.
Unlocking The Truth Understanding Autism Spectrum Disorder With Clinical Partners Autism Test
The phrase people see online usually refers to the broader goal of actually understanding what the results mean rather than just collecting a diagnosis. A lot of my experience has been helping people interpret their reports after the fact. The report itself tells you whether you meet criteria for autism spectrum disorder under the DSM-5 or ICD-11. What it often does not tell you clearly is what that actually means for daily life, support needs, or workplace accommodations. That gap is where people get stuck. I once worked with someone who had a clear positive diagnosis from Clinical Partners but was unable to get their employer to make reasonable adjustments because the report lacked specific functional recommendations. The clinician had done their job correctly from a diagnostic standpoint. They confirmed the diagnosis. But the document did not translate that into language the employer's HR department could act on. I wrote a separate letter breaking down the specific support needs tied to each area of the assessment, and it took about two hours. The employer then engaged properly. Without that bridge between diagnosis and functional impact, the paper diagnosis sits in a drawer. Another thing people routinely miss is that the ADOS-2 algorithm scores do not map 1:1 onto the level of support someone needs. You can score in the autism range and function quite independently in daily life. Or you can score below the threshold and still have significant support needs due to co-occurring conditions. The tool measures autistic traits, not disability. These are different things. A senior colleague of mine once put it bluntly during a case discussion: the ADOS tells you about presentation, not about personhood. That distinction matters when you're reading your own results and trying to figure out what comes next.
There are edge cases worth mentioning. Masking and camouflaging are the big one. Adults, particularly women and non-binary people, often present very differently on the day of the assessment compared to their everyday experience. I have seen people who are openly dysregulated at home perform remarkably well during the structured ADOS tasks because the environment is predictable and controlled. If you know you mask heavily, tell the assessor upfront. A good clinician will factor that into their interpretation. Clinical Partners assessors are generally aware of this, but you should still bring up your masking strategies and what they look like in your actual life. Another edge case is intellectual ability. If you have an average or above-average IQ, the ADOS can produce false negatives because your cognitive skills help you navigate the social components of the tasks. Conversely, if you have a learning disability, some elements of the ADI-R interview may not be appropriately scaled. In both situations, the assessment still happens but the interpretation requires extra clinical judgement. Make sure the report addresses these factors explicitly. If it does not, ask for clarification before you leave the process. Co-occurring conditions will show up and they complicate everything. ADHD, anxiety disorders, OCD, and trauma-related conditions can all produce symptoms that overlap with autism. I have had clients who came in convinced they were autistic only to find the assessment pointed more toward ADHD with autistic traits. Neither is wrong, but the support paths diverge significantly. One of my own assessments years ago flagged both autism and ADHD because the traits were interleaved. The clinician had to separate out which behaviours were lifelong and developmental versus which had emerged later. That separation is difficult and subjective, and no two assessors will always agree on the weighting.
Get the Full Details

Here is what the process does not do well. It does not give you ongoing support. It does not connect you with communities or services. The assessment is a snapshot in time, usually lasting a few hours across multiple sessions. Anything beyond that is up to you to navigate after you receive the report. Some people find that useful. Others find it isolating. The report is a diagnostic document, not a life manual. The cost is another real limitation. Two to three thousand pounds is not accessible to most people. If you cannot afford private assessment, the NHS route is free but slow. There is no perfect middle ground. Some people try to use online screening tools like the AQ-10 or RAADS-R as a proxy, but those are not diagnostic. They can suggest further investigation but they cannot confirm anything. I have seen too many people anchor their entire understanding of themselves to a thirty-question quiz and then feel blindsided when a proper assessment reaches a different conclusion. Practical steps if you are considering this path. Gather any old school reports, medical records, or family observations you have. Developmental history is crucial and clinicians cannot work without it. Write down specific examples of sensory sensitivities, social difficulties, and routine-based behaviours from your earliest memories. The ADI-R relies heavily on this kind of detail. Also decide what outcome you actually want from the assessment. Are you looking for a diagnosis for legal protections? For personal understanding? For access to support services? Your answer will shape how you engage with the process and what you do with the results afterward.
When you receive the report, read it slowly. The diagnostic criteria sections will reference the DSM-5 or ICD-11. Make sure the language matches your experience. If something in the report feels inaccurate or incomplete, you have the right to request a correction or to add a supplementary statement. I have helped people draft these additions before. They are short documents, usually one or two pages, that attach to the main report and address specific gaps. The broader point here is that an autism assessment is a starting point, not an endpoint. The tool itself is rigorous and well-validated when used properly. The interpretation requires clinical expertise. The aftermath requires personal effort. None of that is bad. It is just the structure of how these things actually work. If you go in with realistic expectations about what the process can and cannot do, you will get far more out of it than someone who expects the assessment to solve everything at once.




