What Happens When You Actually Look At Drug Testing Results
Most people think drug testing is straightforward. You give a sample, it goes to a lab, a cut-off number determines pass or fail, and the result lands in someone's inbox. That narrative exists because it's easy to explain in a handbook. The reality is messier. Modern drug testing involves immunoassays, GC-MS confirmation, MRO reviews, split-sample protocols, and a lot of room for both false positives and procedural errors. Services like DrugTestCheck exist somewhere in that gap between a raw lab report and what an employer or individual actually needs to understand. DrugTestCheck isn't a lab. It's a verification and education platform that takes the output of certified drug testing labs and translates it into something actionable. When I first encountered it, I was going through a particularly frustrating case where a candidate's initial immunoassay screen came back positive for THC, but the confirmatory GC-MS result showed a level well below the standard 15 ng/mL cutoff for THC-COOH. The lab report was technically correct. The hiring manager was confused. DrugTestCheck helped bridge that gap by showing the actual quantified concentration, the detection window context, and what the MRO review actually meant before a final disposition was issued. The platform pulls data from SAMHSA-certified laboratories and some state-specific programs, which means the information you see has already passed through the federal workplace drug testing framework. That doesn't make it infallible, but it does set a baseline standard that most private or at-home test kits simply don't meet. One thing DrugTestCheck makes clear that most people miss is the distinction between a positive screen and a confirmed positive. An immunoassay can cross-react with a dozen different substances. Ibuprofen, NSAIDs, proton pump inhibitors, even certain antibiotics have all triggered false positives on initial screens. The confirmation step is where the actual science happens, and if that step is skipped or mishandled, you're looking at a result that's more paperwork than data.
I've personally run into a situation where an applicant's verified negative result from DrugTestCheck still got flagged internally because the ATS system was configured to pull raw screening values rather than the final MRO-verified disposition. The person reviewing the file saw the immunoassay flag, not the GC-MS clearance. DrugTestCheck surfaces the confirmed result, but it can't control what a company's internal software displays. The workaround I used was requesting the MRO contact information directly from the lab and having the MRO send a verification letter to the hiring team alongside whatever the automated system produced. It added three business days to the process, but it resolved the discrepancy permanently.
How Modern Drug Testing Actually Works
The standard five-panel test remains the baseline for most employer testing. It screens for marijuana metabolites, cocaine metabolites, opioids, amphetamines, and phencyclidine. SAMHSA expanded this to a ten-panel in recent years, adding oxycodone, hydrocodone, methadone, buprenorphine, and fentanyl. Most private sector employers haven't adopted the ten-panel because the incremental cost and complexity don't justify the yield unless they operate in safety-sensitive roles or specific regulated industries. The extension program for DOT-covered positions is a separate regulatory track with its own chain-of-custody requirements. Immunoassay screening typically uses enzyme multiplied immunoassay techniques, or EMIT, though fluorescence polarization immunoassay and chemiluminescence are also common. These are fast and inexpensive, which is why they dominate the first step. A single test can process hundreds of samples per hour. The tradeoff is sensitivity and specificity. Cutoff levels matter enormously here. A standard THC screen cutoff is 50 ng/mL, but some labs use 20 ng/mL, which catches more low-level exposure but also increases false positive rates. The SAMHSA mandatory cutoff for THC confirmation is 15 ng/mL via GC-MS. Anything below that is reported as negative regardless of what the screen showed. Gas chromatography-mass spectrometry confirmation is the gold standard. It separates individual compounds and identifies them by molecular weight and fragmentation pattern. A positive screening result must be confirmed by this method before a final determination is made. The confirmation cutoff is lower than the screen cutoff by design, so borderline cases can be validated or ruled out. This is where DrugTestCheck becomes useful, because the raw numbers are visible rather than buried inside a lab report formatted for medical review officers, not hiring managers.
Get the Full Details

What DrugTestCheck Actually Shows You
When you pull up a result through the platform, you're typically looking at the specimen type, collection date, lab name, assay method, cutoff levels used, the initial screen result, the confirmation result with quantified concentration, and the MRO disposition. The MRO disposition is the legally relevant field. It will read negative, positive, rejected for adulteration, rejected for substitution, or positive due to a medically explained alternative prescription. That last category is where prescription medications factor in. Someone taking oxycodone for back pain shouldn't test positive for illegal opioids, and the MRO checks the prescribed drug database before finalizing the result. One nuance that rarely gets discussed is the alcohol testing component. Breath alcohol tests use a cutoff of 0.02 for screening and 0.04 for confirmation in DOT contexts. Non-DOT employers often skip alcohol testing entirely or run it through a separate process that doesn't get logged in the same system. DrugTestCheck primarily focuses on urine drug panels, so if your organization combines alcohol and drug testing, you may need to look at both records to get the full picture. Another area where the platform reveals something counterintuitive is detection windows. People constantly search for how long THC stays detectable, and the answer is approximately "it depends," which is the least helpful response in existence. For a single use, detection typically ranges from three to seven days. For moderate use, two to four weeks. For chronic heavy use, it can extend past ninety days. The problem is that most generic charts online don't account for body mass index, metabolic rate, hydration status, or the specific cutoff level the lab is using. DrugTestCheck doesn't solve this entirely either, but seeing the actual quantified concentration in your result gives you far more information than a generic detection window chart ever could.
Where Drug Testing Falls Short
The biggest limitation of modern drug testing is that it measures metabolites, not impairment. THC-COOH in urine tells you someone was exposed to cannabis at some point, not whether they were high at the time of testing. No standard urine test can determine current impairment. Blood tests can measure active THC, but the compound clears from blood remarkably fast, often within hours, making it nearly useless for retrospective workplace testing unless the blood draw happens very soon after suspicion arises. This is a fundamental constraint that nobody in the industry pretends to have solved. Another limitation is the adulteration problem. Creatinine and specific gravity checks are standard for identifying diluted samples. pH testing catches some adulterants. But nitrites, glutaraldehyde, and commercial adulterant products continue to evolve faster than screening protocols. Some laboratories now run povidone-iodine and chloramine tests, which are relatively new additions to the adulterant panel. If you're managing a high-volume testing program, you should expect that a small percentage of specimens will show signs of tampering regardless of how rigorous your collection procedures are. There's also the issue of at-home testing kits flooding the market. These are cheap, widely available, and use the same lateral flow immunoassay technology that lab screens do. But they lack confirmation, lack MRO review, and lack chain-of-custody documentation. A positive result from an at-home test has no legal standing in any employment context. DrugTestCheck exists precisely because people and organizations often encounter these ambiguous results and need to know whether the underlying lab process meets regulatory standards. It doesn't replace certification, but it does separate verified lab work from consumer-grade screening.
Practical Steps for Using DrugTestCheck Effectively
If you're an employer running pre-employment or random testing, the first thing to do is verify that your lab is SAMHSA-certified or meets your state's specific requirements. DrugTestCheck aggregates results from multiple certified laboratories, so having access to the platform is useful, but it's only as good as the data feeding into it. If you're an individual trying to understand a result, request the full lab report including the confirmation section and MRO notes. The summary displayed on DrugTestCheck is derived from that data, but having the original document gives you something you can appeal against if the result is contested. I once had a client whose employee challenged a positive result for oxycodone based on a prescription she claimed was valid at the time of collection. The initial lab report didn't include the prescription verification step that the MRO was supposed to perform. DrugTestCheck showed the positive result but didn't clarify whether the MRO had followed up with the prescribing physician. I recommended the client submit a formal request to the lab for the complete MRO workup, which revealed that the physician contact attempt had been made but the call went to a number that had been disconnected. The result stood, but the process was documented. Without that paper trail, the challenge would have had more leverage than it deserved. For hair follicle testing, the platform doesn't currently support those results because the major lab networks that feed into DrugTestCheck focus on urine and saliva. Hair testing is becoming more common for extended detection windows, particularly in legal and custody proceedings. If your organization requires hair testing, you'll need a separate reporting workflow since the data isn't integrated into this system.
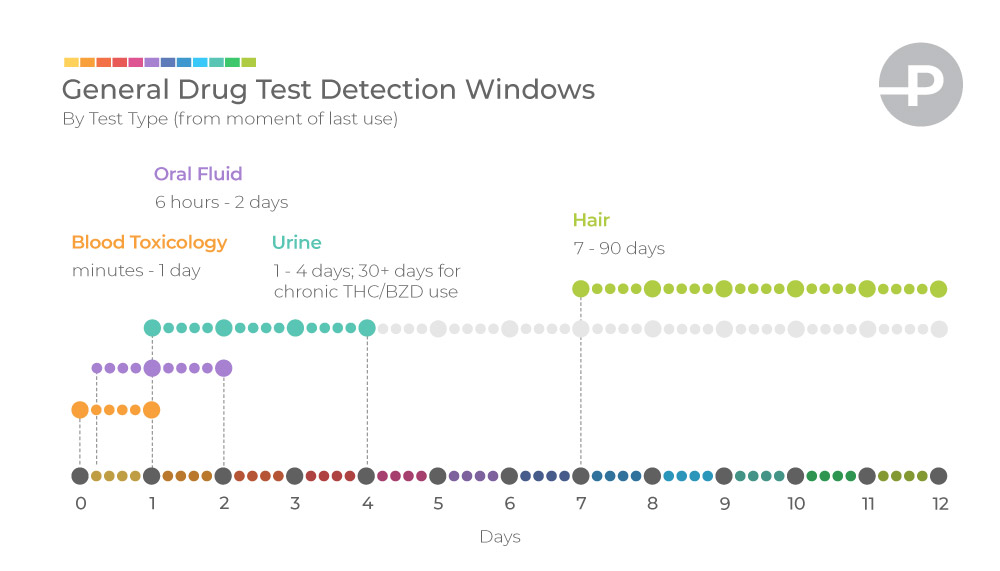
Saliva testing has seen growth in recent years, especially for post-accident and reasonable suspicion testing. Detection windows are short, usually twelve to forty-eight hours depending on the substance, which makes it valuable for catching recent use. DrugTestCheck does include some saliva test results from participating labs, but coverage is spotty. Most employers still rely on urine testing as the primary method because the infrastructure and legal precedent are far more established.
The Bottom Line
Modern drug testing is technically competent but procedurally complex, and the gap between what a lab produces and what a decision-maker understands is where most problems occur. DrugTestCheck exists to close that gap, but it's not a magic solution. It depends on correct lab participation, proper specimen collection, and users who actually read the confirmation results rather than stopping at the screening flag. The platform reveals that most positive results are either confirmed positives with no ambiguity, prescription-related positives that the MRO has already addressed, or screening artifacts that never make it to the confirmation step. The real issue is the middle ground where incomplete data creates confusion, and that's exactly what tends to generate disputes. If you're evaluating this for organizational use, the integration with your existing human resources or applicant tracking system will determine how much friction you experience. Most companies find the value proportional to their testing volume. Low-volume employers might not need it. High-volume or safety-sensitive employers benefit immediately because the time saved decoding lab reports adds up. The platform itself doesn't change the biology of drug detection or the chemistry of testing. It changes how the results are presented, which is a smaller but more manageable improvement than most people expect.


