Mapping Nerve Territories: What Every Lower Leg Dermatome Map Actually Tells You
Dermatomes are areas of skin supplied by single spinal nerves. When you press a cotton wisp against someone's shin and they can't tell you where you touched, that's a clinical test rooted in dermatome mapping. The lower leg is one of the more complicated regions to map because the nerves here overlap aggressively and individual variation is the rule, not the exception.Unlocking The Secrets Of Your Lower Leg A Comprehensive Guide To Dermatomes
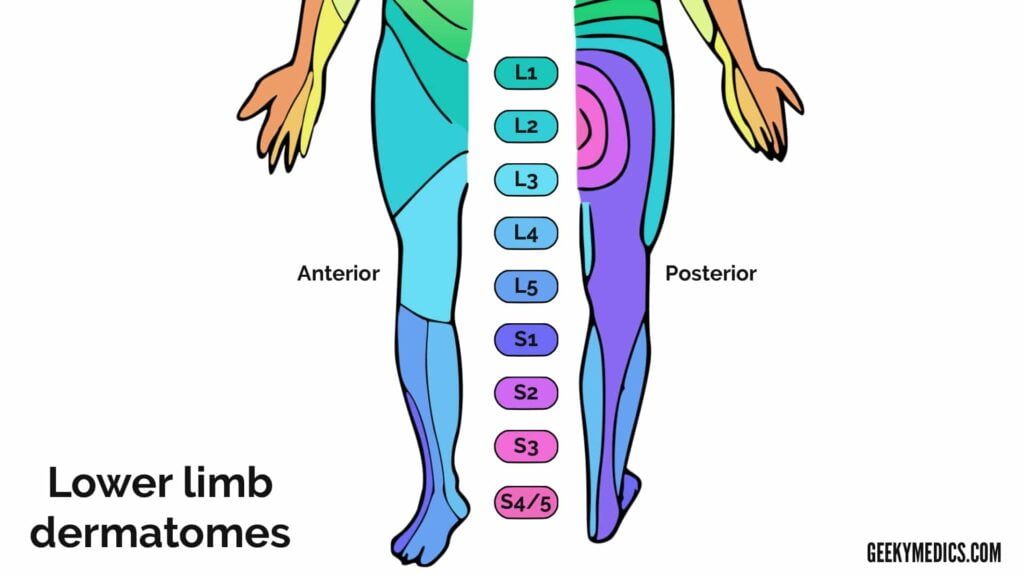
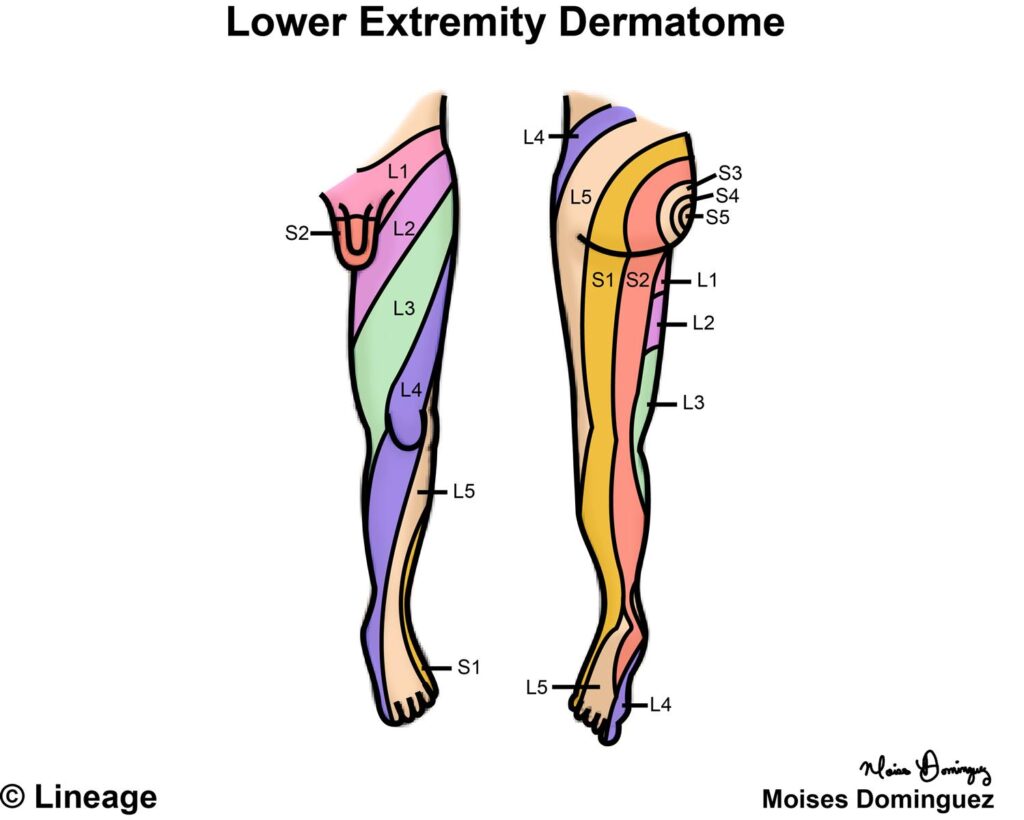
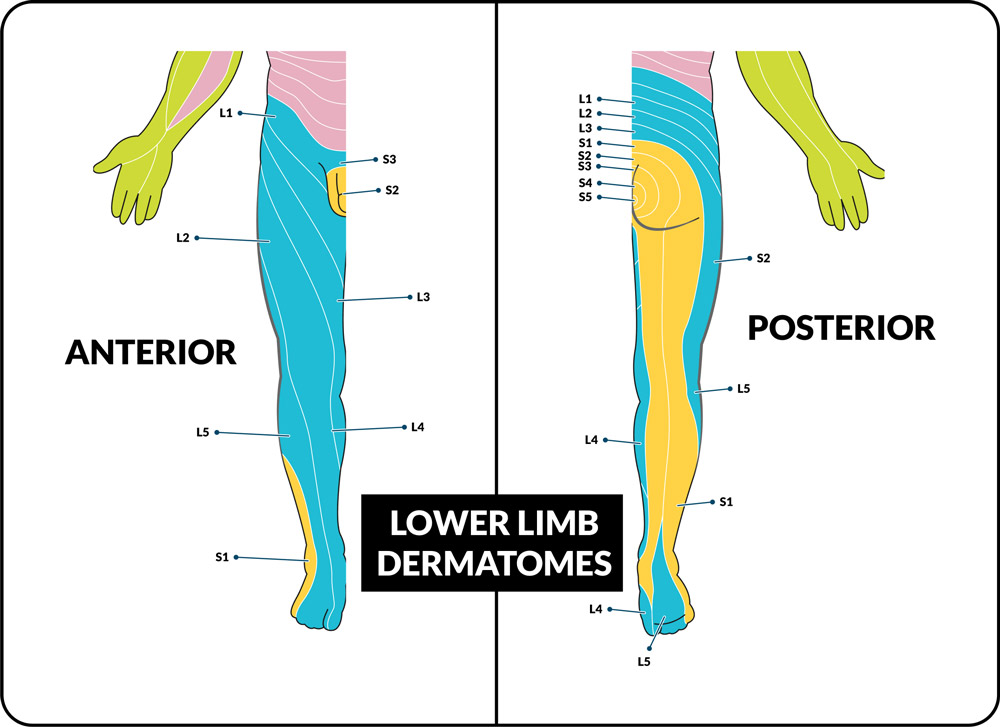
Let me be straightforward about what the maps get wrong before we get into the useful details. Standard textbook diagrams show clean, horizontal bands wrapping around the leg from L1 down to S3. They look neat. They're also essentially decorative. In reality, there is significant overlap between adjacent dermatomes, often 20 to 40 percent of any given skin area receives input from two or three nerve roots. A single nerve root lesion rarely produces a clean sensory deficit matching the textbook band. That's the first thing I wish people understood before they start relying on dermatome charts for clinical decisions. The primary nerves involved in the lower leg come from the lumbar and sacral plexuses. L4 covers the medial aspect of the leg down to the medial malleolus and the medial border of the foot. L5 runs down the lateral leg, crosses the anterior ankle, and supplies the dorsum of the foot including the big toe. S1 encompasses the lateral malleolus, the lateral border of the foot, and the sole. S2 and S3 take care of the posterior calf and the perineal region. The superior cluneal nerves at the top of the gluteal fold and the ilioinguinal and genitofemoral contributions near the upper thigh are often glossed over but matter when you're tracking a radiculopathy upward. I ran into a problem a while back with a patient presenting with what looked like a textbook L5 radiculopathy based on sensory loss along the lateral leg and dorsum of the foot. Standard dermatome mapping would have pointed straight at L5. But the deficit didn't quite match. The sensory change extended into the first web space between the toes, which is actually a mixed L5 and S1 territory. More importantly, the weakness pattern included foot inversion, which is not purely L5. I ended up ordering an MRI that showed an L5-S1 disc herniation compressing the S1 root as well, with some concurrent peroneal nerve irritation at the fibular head from altered gait. The takeaway was that dermatome maps alone got me close but not accurate. A combined nerve conduction study and careful motor examination sorted it out.
How Dermatome Testing Actually Works in Practice
The standard approach uses light touch and pinprick. You start at a known area and move systematically. The McGill and Bromberg maps remain the most cited references, though both have been questioned for inter-rater reliability. Light touch is mediated by the spinothalamic tract and dorsal columns, while pinprick sensation is primarily spinothalamic. Testing both gives you information about which pathways are affected, not just which root. That distinction matters when you're trying to differentiate a radiculopathy from a peripheral neuropathy. Proprioception testing at the great toe is S1/S2 and worth including. Vibration sense using a 128 Hz tuning fork at the medial malleolus checks large fiber function. These aren't dermatome tests per se, but they complement the map and help you distinguish root pathology from peripheral nerve damage. One counter-intuitive point that beginners miss: a negative dermatome exam does not rule out nerve root pathology. Studies show that up to 30 percent of patients with confirmed radiculopathy have normal sensory exams when tested in the acute phase. The reason is that the dorsal root ganglion can absorb enough insult before symptoms manifest in the skin territory. Motor findings and reflex changes often appear first. If you're waiting for a clean sensory map to confirm L5 radiculopathy, you might miss the window where conservative treatment works best.
Another nuance worth noting is the difference between myotomes and dermatomes. Patients and even some clinicians conflate them. Myotomes are muscle groups controlled by specific nerve roots. L4 includes ankle dorsiflexion and inversion. L5 includes toe extension and hip abduction. S1 includes plantar flexion and hip extension. When you see weakness without sensory change, think myotome and look for a motor pathway issue rather than a sensory dermatome problem. They overlap anatomically but they are not the same thing clinically.
Get the Full Details
Common Pitfalls When Using Dermatome Maps
The first pitfall is assuming symmetry. Textbook maps don't account for the fact that many people have dominant side variations. I've seen patients where the right L5 dermatome extended slightly further anteriorly than the left, and the difference was consistent across repeated exams. It's normal anatomical variation, not pathology, but it can confuse interpretation if you're comparing one leg against the map rather than against the patient's own baseline. The second pitfall is overlapping peripheral nerve territories. The superficial peroneal nerve supplies the dorsum of the foot, which overlaps with L5. The saphenous nerve supplies the medial leg, overlapping with L4. If a patient has both L4 radiculopathy and saphenous nerve entrapment, the sensory loss will look like a broader L4 territory than the map predicts. The workaround is to test proximal sites where peripheral nerves haven't yet branched. For example, testing the medial thigh rather than just the medial ankle helps distinguish L4 root pathology from saphenous nerve compression. The third pitfall is diabetic peripheral neuropathy masquerading as dermatomal loss. Length-dependent neuropathies produce a stocking distribution that can look like sacral sparing with lower lumbar involvement. But unlike a radiculopathy, the pattern is symmetric and progresses proximally over time. Reflexes are typically reduced across the board. Blood glucose and HbA1c results usually sort this out quickly enough.
When Dermatome Maps Fail Completely
There are scenarios where dermatome mapping provides almost no diagnostic value. Severe peripheral neuropathy makes sensory testing unreliable because the distal extremities are non-responsive regardless of root integrity. Critical illness polyneuropathy and myopathy produce diffuse findings that obscure any dermatomal pattern. Spinal stenosis with multi-level involvement creates overlapping deficits that no single chart can resolve. In these cases, imaging and electrodiagnostic studies are the only reliable path forward. Another situation where maps fail is congenital anomalies. Some people have unusual nerve branching patterns from birth. A patient I evaluated had an accessory L5 branch that innervated a strip of skin on the anterior thigh well above the expected territory. Standard testing would have missed this entirely unless you mapped carefully and noted the anomaly. There's no shortcut for thorough examination in these cases.
A Practical Examination Sequence
Here's how I structure a lower leg dermatome exam now after years of doing this. Start with light touch using a wisp of cotton. Test L2 on the anterior thigh just below the inguinal ligament. Move to L3 on the medial knee. L4 at the medial malleolus. L5 on the dorsum of the foot between the first and second metatarsals. S1 on the lateral malleolus and posterior calf. S2 in the popliteal fossa. S3 on the sacrum and perineum. Test pinprick in the same sequence. Compare left and right at each level. Document any asymmetry relative to the patient's own baseline, not the textbook. For confirmation, add motor testing of ankle dorsiflexion for L4-L5, big toe extension for L5, and plantar flexion for S1. Check the patellar reflex for L4 and the Achilles reflex for S1. The combination of sensory mapping with motor and reflex findings gives you a much clearer picture than any single modality. I've found that this combined approach reduces mislocalization errors significantly compared to sensory mapping alone.

What the Literature Actually Says
Multiple studies over the past few decades have questioned the precision of dermatome maps. Kim and Chung demonstrated significant variability in dermatomal boundaries across individuals using electromagnetic stimulation. Landi and colleagues found that pinprick and light touch territories did not align perfectly, suggesting that different sensory modalities may have slightly different root representations. More recent work using high-resolution MRI has shown that nerve root compression does not always correlate with expected dermatomal symptoms, reinforcing the point that clinical correlation is essential. The bottom line is that dermatome maps are useful starting points, not definitive diagnostic tools. They guide your examination and help you localize when something is wrong, but they should never replace a thorough clinical assessment. The lower leg is particularly tricky because of the dense overlap between lumbar and sacral contributions, the frequent coexistence of peripheral nerve entrapments, and the high prevalence of diabetes-related neuropathy in the population that needs this testing most. If you want to get better at this, practice on healthy subjects first. Map their legs thoroughly and note the variations you find. Then compare those findings against the standard charts. The differences you see are normal. Understanding that range of normal is what separates a competent examiner from one who misreads routine cases.