Understanding the Ventral Cavity: What Actually Matters
Unlocking The Secrets Of The Ventral Definition A Comprehensive Guide To The Abdominal Cavity
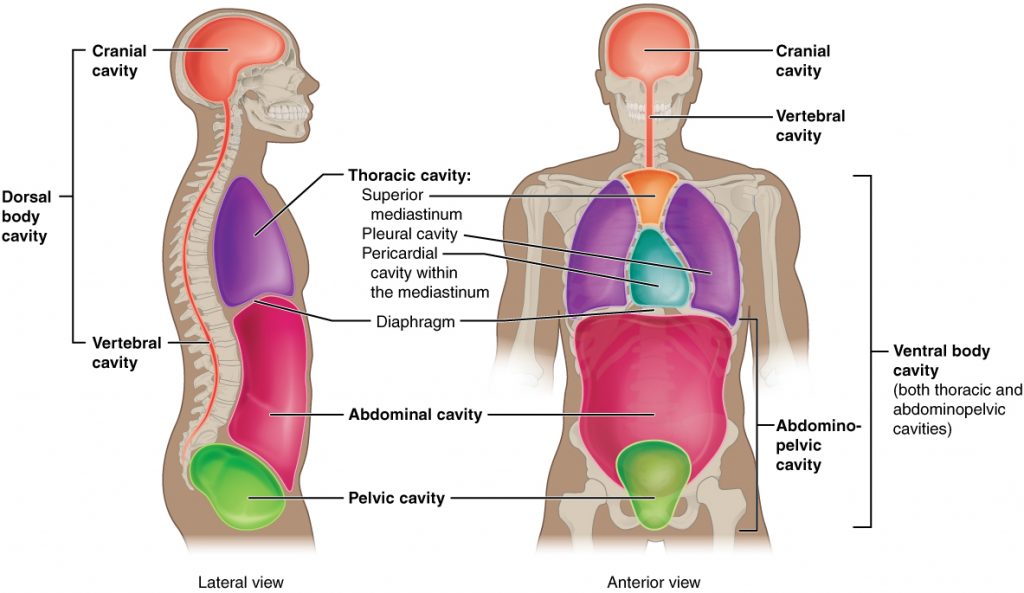
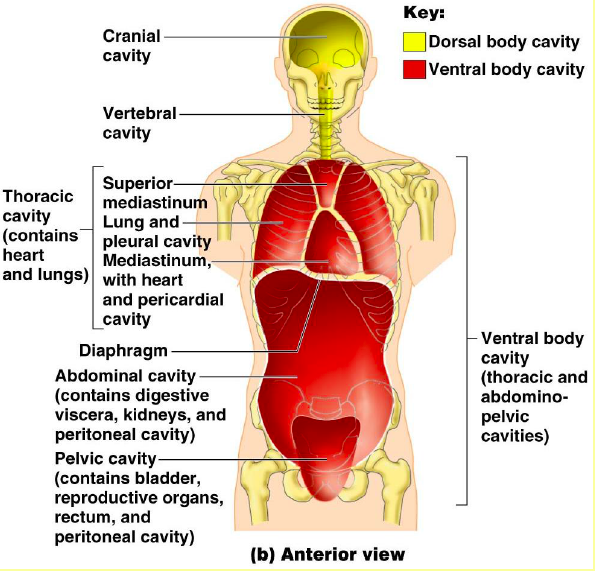
The ventral cavity is simply the front-facing body cavity. It runs from the base of the skull down to the pelvic floor. Most people encounter this term in introductory anatomy, and most people leave with a vague idea of it. The problem isn't the definition. The problem is what gets glossed over, and that gap causes confusion later when you're looking at imaging, performing dissections, or trying to understand pathology. There are two subdivisions. The thoracic cavity sits above the diaphragm. The abdominopelvic cavity sits below it. The thoracic cavity has its own internal partition called the mediastinum, which holds the heart, trachea, esophagus, and major vessels. The rest of the thoracic space houses the lungs. Below the diaphragm, the abdominal cavity contains the liver, stomach, small intestine, colon, spleen, and kidneys. The pelvic cavity contains the bladder, reproductive organs, and rectum. These are standard definitions. They're also not where the difficulty actually lies. The real complexity comes from the peritoneum. This is a single continuous membrane that lines the cavity and folds around the organs. It has two layers. The parietal peritoneum lines the abdominal wall. The visceral peritoneum covers the organs themselves. Between them is the peritoneal cavity, a potential space with a thin film of serous fluid. That fluid reduces friction as organs shift during movement and digestion. When that system gets irritated, you don't get a vague discomfort. You get localized, sharp pain that can point directly to the affected organ. This is why peritoneal signs matter in clinical evaluation.
I spent years watching students confuse intraperitoneal with retroperitoneal structures, and it's never accidental. It happens because the textbooks present the organs as isolated items on a list. They don't show you the connective tissue relationships. Let me clarify the distinction because it affects everything from surgical access to CT interpretation. Intraperitoneal organs are suspended within the peritoneal cavity by mesenteries. The stomach, liver, spleen, jejunum, ileum, cecum, ascending colon, transverse colon, and descending colon all fall into this category to varying degrees. They have mobility. They can shift. Retroperitoneal organs sit behind the peritoneum, pressed against the posterior abdominal wall. The kidneys, pancreas, duodenum (most of it), ascending and descending colon, and the aorta and inferior vena cava are retroperitoneal. They don't move much. A kidney stone causes pain in a completely different pattern than a small bowel obstruction precisely because of this anatomical difference. Here's something most guides don't emphasize: the omenta. The greater omentum hangs from the stomach like an apron. It's made of folded peritoneum and contains fat, immune cells, and lymphatic tissue. It's not decorative. It migrates to areas of inflammation and can wall off infections. I had a case once where a perforated duodenal ulcer was partially contained by the greater omentum, and the patient's presentation was atypical precisely because of that. The classic board-exam picture of rigid abdomen didn't fully apply. The omentum had created a localized abscess. If you're relying on a static diagram to understand abdominal pathology, you'll miss these variations. The anatomy is dynamic. Another practical point that gets skipped: the four quadrants versus the nine regions system. Quadrants are useful in emergency settings. Quick verbal communication matters when you're triaging. Right upper quadrant pain points to the liver, gallbladder, or duodenum. Left upper quadrant suggests spleen or stomach issues. Right lower quadrant is appendicitis until proven otherwise. Left lower quadrant involves the sigmoid colon and reproductive structures. But quadrants are crude. The nine-region system provides more precision. Epigastric, umbilical, hypogastric, right and left lumbar, right and left iliac, right and left hypochondriac. Surgeons use the nine-region system. Radiologists use both. Knowing when to switch between them is a skill that takes actual exposure to develop.
There are limitations to how much you can learn about the ventral cavity from any single source. Diagrams flatten three-dimensional relationships. Cross-sectional images require training to read accurately. Cadaver labs are the closest you'll get to real spatial understanding, but they're expensive and not universally accessible. Self-study works for memorizing organ names. It breaks down when you need to understand why a patient presents with referred pain from the gallbladder to the right scapula, or why a splenic rupture can cause shoulder tip pain through phrenic nerve irritation. Those connections come from studying the innervation and vascular supply, not from labeling diagrams. If you're working through this material, focus on the peritoneal relationships first. Get clear on what's intraperitoneal, what's retroperitoneal, and which structures carry mesenteries. Then layer in the regional anatomy. The rest follows. I still pull up cross-sectional atlases when I need to visualize relationships between the pancreas and the splenic vein, or confirm the exact position of the cecum relative to the psoas muscle. No amount of rote memorization replaces knowing how to look at the actual anatomy.
Get the Full Details