Understanding Lumbar Dermatomes In Practice
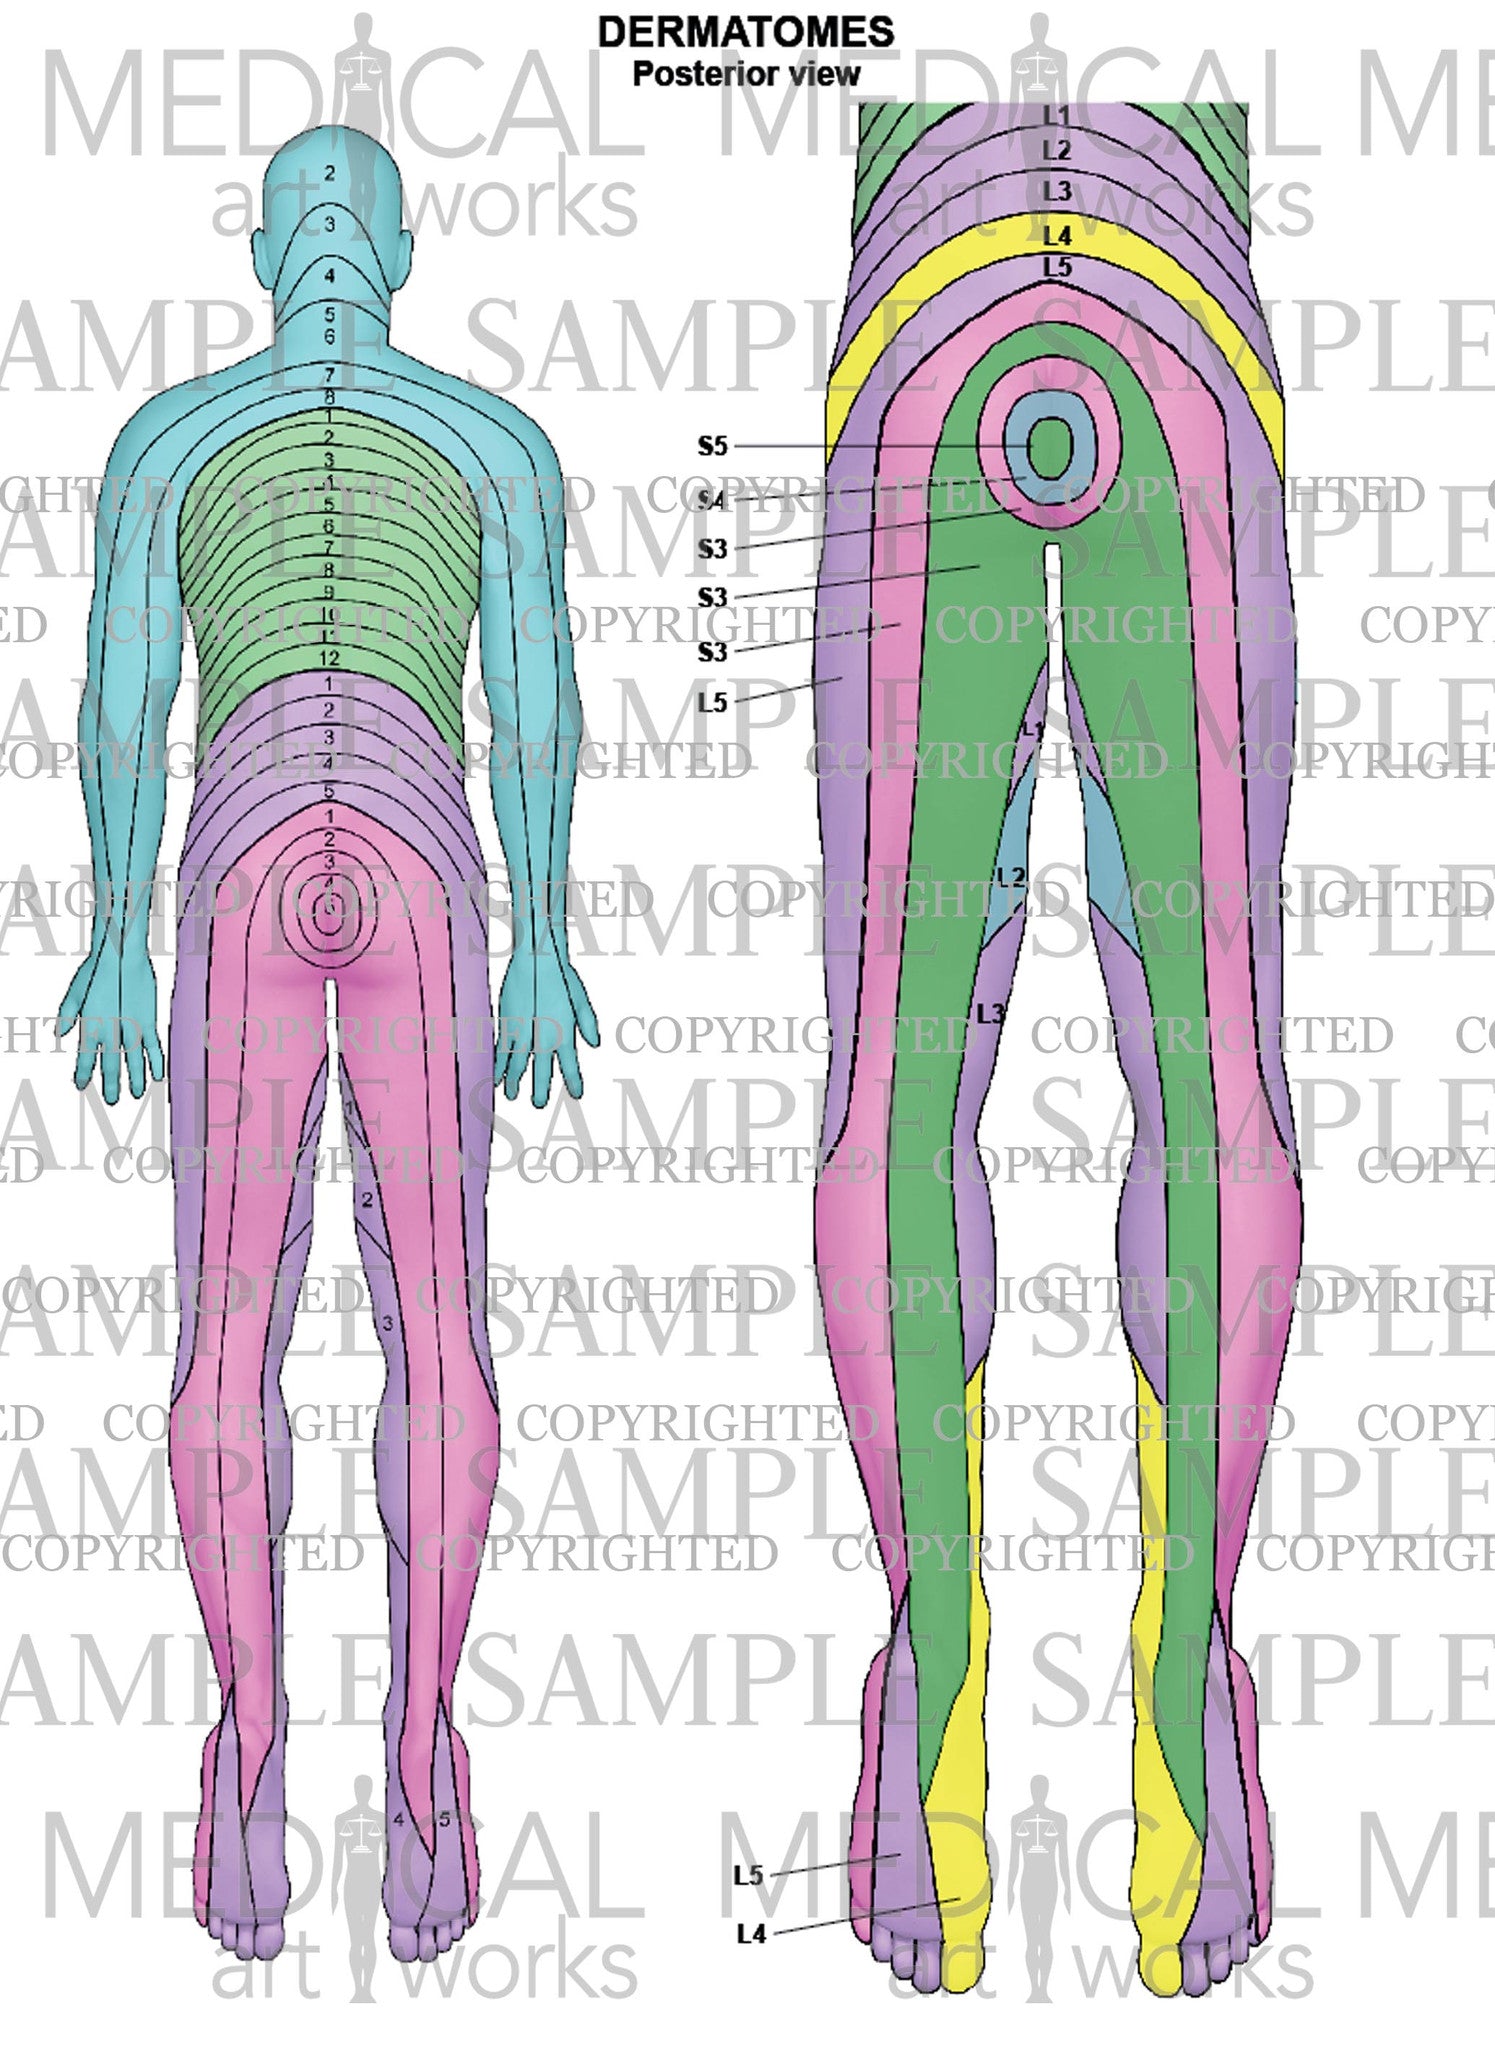
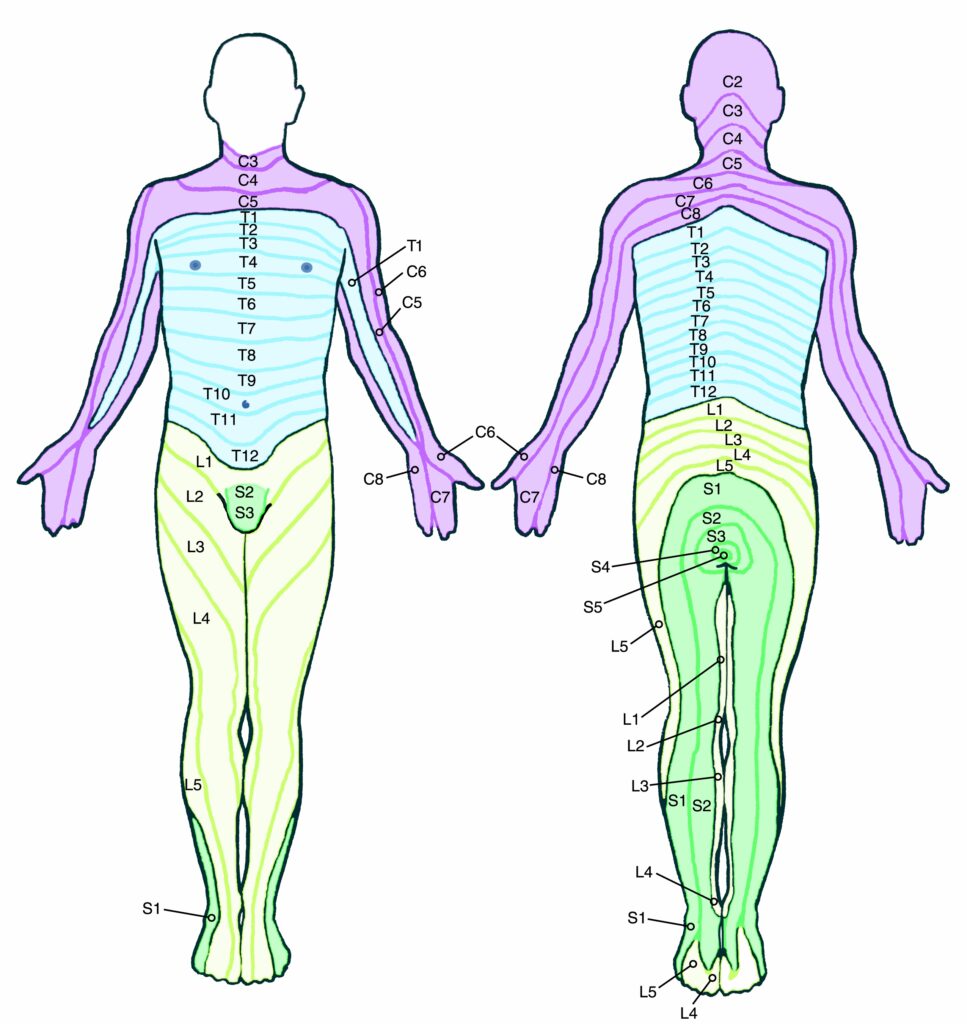
The lumbar dermatome chart is one of those things that looks simple on paper and completely falls apart when you actually try to use it on a real patient. I spent years mapping sensory loss to nerve roots before I stopped treating the textbook as gospel. The chart shows L1 through S1 as clean, distinct zones, but human anatomy does not respect boundaries drawn by early 20th-century researchers like Joseph Bonnet and Henry Head. Overlap between adjacent dermatomes is the rule, not the exception. If you are relying on crisp lines to localize a disc herniation, you are going to miss things. I had a patient with what looked like a textbook L5 radiculopathy on the chart, but the sensory changes extended into S1 territory and the reflexes told a different story. The MRI confirmed a massive central disc extrusion at L4-L5 that was compressing both the L5 root and the traversing S1 root. A strict dermatome map would have led me straight to the wrong level. Let me walk through how this actually works and where the traps are. The lumbar dermatomes govern sensation from the lower abdomen down through the anterior thigh, medial leg, and into parts of the foot. L1 covers the inguinal region and upper anterior thigh. L2 runs down the anterior thigh. L3 extends to the medial knee. L4 continues along the medial lower leg and reaches the medial malleolus. L5 sweeps across the lateral leg and dorsum of the foot, including the big toe. S1 takes the lateral foot and little toe. That is the standard model. It is useful as a starting framework, not as a diagnostic end point. Here is the part most guides skip: dermatomal maps are probabilistic, not deterministic. Studies using quantitative sensory testing show that individual dermatome borders shift by two to four centimeters between people, and the degree of overlap increases with age. A 65-year-old will show much broader and less distinct zones than a 30-year-old because peripheral nerve regeneration and collateral sprouting blur the lines over time. I learned this the hard way when tracking a patient whose L5 sensory symptoms were inconsistently mapped across three separate visits. The zone kept migrating medially and laterally by about three centimeters each time. The underlying pathology had not changed. The variation was normal anatomical drift, not disease progression. Once I understood that, I stopped using the chart as a ruler and started using it as a directional compass.
The practical application matters more than memorizing which toe belongs to which root. When you are assessing lumbar radiculopathy, combine dermatomal sensation testing with myotome strength testing and reflex evaluation. L4 involves the patellar reflex. L5 has no reliable reflex. S1 uses the Achilles reflex. A patient can have altered sensation in the L5 dermatome but normal L5 myotomes and preserved ankle dorsiflexion strength, which points away from a true L5 radiculopathy and toward a peripheral nerve issue or even a superficial cutaneous nerve entrapment like meralgia paresthetica if the symptoms sit more laterally in the L2-L3 distribution. I saw this mismatch frequently enough that I stopped ordering lumbar MRIs for isolated sensory complaints without correlating motor or reflex findings. About a third of those scans come back with age-appropriate degenerative changes that are incidental and do not explain the symptoms. If you need a reference chart for clinical work or study purposes, several reputable sources offer downloadable versions. The Clinically Oriented Anatomy atlas by Keith Moore provides a clean lumbar and sacral dermatome illustration. The NIH and NHS publish patient-friendly versions that sacrifice some anatomical precision for readability. For clinical detail, the dermatome maps from the Association of Anatomical Medicine are widely used in physical therapy and neurology residencies. Search for "lumbar dermatome chart PDF" and look for sources published by medical schools or professional associations rather than random health blogs, which often contain errors from careless recopying of older diagrams. One counter-intuitive point that catches people off guard: a positive dermatome finding does not always mean a nerve root problem. Lateral femoral cutaneous nerve entrapment mimics L2-L3 dermatomal sensory changes in the anterior thigh but spares motor function entirely and follows a completely different anatomical course. Piriformis syndrome can produce symptoms that overlay the L5-S1 distribution without any actual nerve root compression. Syringomyelia or a spinal cord tumor higher up the axis can produce sensory changes that appear to follow lumbar dermatomes because of how the spinothalamic tract is organized. I once spent two weeks chasing an L5 radiculopathy in a patient who turned out to have a small conus medullaris lesion. The sensory deficit matched the chart perfectly until I checked the bilateral pattern and realized the symmetry was wrong for a single root compression.
The main limitation of the lumbar dermatome chart is that it was built on cadaver studies and early clinical observations, not modern imaging-correlated data. The original maps assumed clean separation between nerve roots that simply does not exist in living tissue. Each root shares significant cutaneous innervation with its neighbors through plexus networking. Single-root lesions often produce minimal or no sensory loss because the overlap compensation kicks in. You can have a clinically significant L5 radiculopathy with near-normal sensation in the L5 dermatome on careful testing. That is why combining dermatomal assessment with straight leg raise tests, tension signs like the slump test, and objective neurological examination findings gives you far more diagnostic accuracy than dermatome mapping alone. Adding electrodiagnostic studies when the picture is unclear reduces mislocalization rates substantially, though they have their own limitations with partial or proximal lesions. The chart is worth studying because it gives you a structured way to think about sensory anatomy. It is not worth treating as authoritative. Use it to narrow your differential, not to confirm one. Map the area thoroughly, compare bilaterally, document the exact borders on paper or a digital tablet, and track changes over serial exams rather than making decisions from a single session. That approach catches more real pathology and sends fewer patients down unnecessary treatment paths.
Get the Full Details