
Why Everyone Messes Up This Tissue
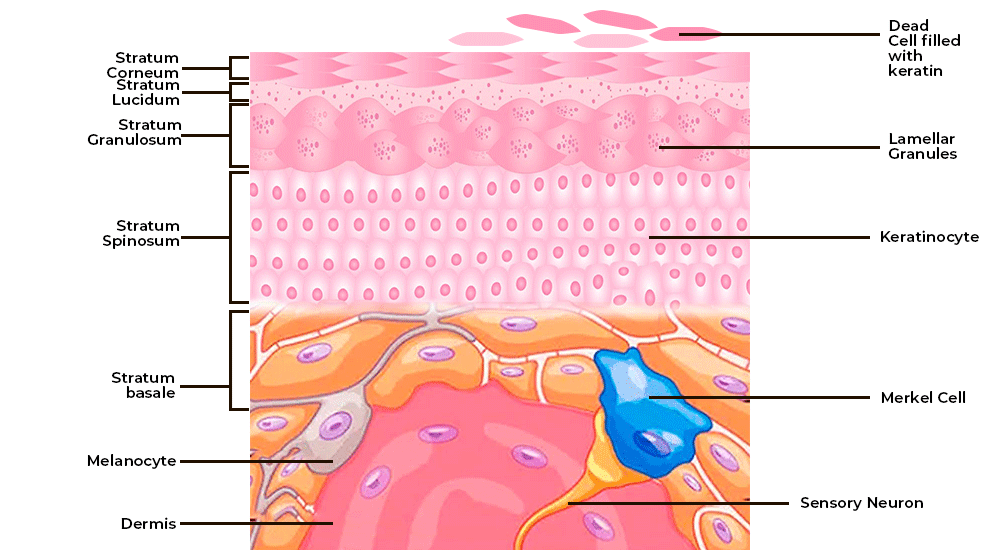
You look at a slide of nonkeratinized stratified squamous epithelium and most people think they know what they're seeing. They don't. The confusion starts at the basics and compounds fast, especially when you actually need to interpret what's going wrong in a clinical sample. The difference between nonkeratinized and keratinized tissue isn't just academic — it shows up constantly in biopsy reports, pathology workups, and honestly in lab workflows where samples get misclassified and the whole downstream analysis derails. Stratified squamous nonkeratinized epithelium is a multilayered tissue where the cells flatten out as they migrate toward the surface, but they never deposit that hard, dead protein layer that keratinized skin develops. The surface cells are still alive, still nucleated, and they stay moist. This happens in places like the oral mucosa, esophagus, vagina, and cornea — areas that need protection from abrasion but also need to stay flexible and wet, not dry and scaly like your outer skin. The basal layer sits on the basement membrane and contains the stem cells doing all the division work. Above that you have several layers of cuboidal to polygonal cells called stratum spinosum, then progressively flatter cells moving up, and finally the surface where you see intact nuclei in every cell. That's the main difference from keratinized epithelium, where the top layers are completely anucleate — just packed keratin protein with no living cell structure left.
When you're working with this tissue practically, here's what most people miss: the intermediate layers aren't just a transition zone. They're metabolically active and they maintain ion and water balance differently than you'd expect from simple "protective lining" descriptions. The tight junctions in the upper spinous layer create a paracellular barrier that's surprisingly robust, and when that barrier breaks down — which happens in conditions like pemphigus vulgaris or erosive lichen planus — you get clinical symptoms that look unrelated but are actually a direct failure of this epithelial architecture.
How to Actually Identify It Under the Microscope
Start with an H&E stain. That's standard, and you already knew that. The thing that actually helps is knowing what to look for beyond "layers of flat cells." Check the nuclear-to-cytoplasmic ratio across the layers. In nonkeratinized epithelium, the nuclei in the superficial layers remain visible and relatively uniform — they don't shrink and disappear like they do in keratinized tissue. If you're seeing superficial cells with pyknotic nuclei or complete loss of nuclei at the surface, you're probably looking at keratinized epithelium or an artifact from poor fixation. The cytoplasm in nonkeratinized cells tends to be paler and more basophilic compared to the dense eosinophilic staining of keratinocytes. This is because nonkeratinized cells retain more organelles and water. Don't confuse this with edema or artifact — check the overall architecture first. If the basement membrane is intact and the layers are orderly, the pale staining is real. I ran into a specific problem last year with a set of esophageal biopsies where the superficial layers were washing out during processing. The pathologists on the other end were calling it "parakeratosis" because they could still see nuclei at the surface, which they interpreted as abnormal keratinization. It wasn't. We had over-extended the xylene clearance steps by about forty seconds per batch, which leached out the lipid-rich intercellular material and made the superficial cytoplasm look artificially pale and disorganized. The fix was simple — cut the xylene time back to three minutes per change instead of four, and the morphology came right back. That's the kind of detail that doesn't show up in textbooks but costs you actual diagnostic confidence when it goes wrong.
Get the Full Details
Common Pitfalls That Wreck Your Analysis
Autofluorescence is a real issue if you're doing immunofluorescence work on this tissue. The connective tissue beneath the epithelium, particularly collagen in the lamina propria, lights up in the green and red channels and can easily be mistaken for specific staining on the epithelial surface. I've seen people waste half a day chasing false-positive signals before realizing the secondary antibody wasn't the problem — it was the autofluorescent stroma underneath. The workaround that actually works is quenching. A ten-minute soak in 0.1 M glycine pH 8.0 after your primary antibody incubation, followed by a thorough PBS wash, cuts most of the background autofluorescence down to acceptable levels without affecting your antigen signal. Test it on a control slide first because some antigens are sensitive to the pH shift, but for most standard markers like cytokeratin 14 or 19, it's clean. Another pitfall that people overlook: tangential sectioning. When you cut through stratified epithelium at an angle instead of perpendicular, the cells look artificially stratified or disorganized. You can mistake this for dysplasia if you're not careful. The telltale sign is that the nuclear sizes vary dramatically across what should be a uniform layer, and the basement membrane appears wavy or duplicated when it's actually just being cut obliquely. Rotate your block and recut if you see this — it costs about twenty minutes and saves you from misdiagnosing a perfectly normal sample.
Functional Significance Beyond the Textbook Definition
The barrier function of nonkeratinized epithelium operates differently than keratinized skin, and this matters if you're studying permeability or drug delivery. Nonkeratinized epithelium is more permeable to water and small molecules, which is why buccal drug administration works. The intercellular lipid matrix exists but it's less densely packed than in the stratum corneum of keratinized skin. Research from 2019 showed that transepidermal water loss across oral mucosa is roughly three times higher than across forearm skin, which seems obvious but the actual numbers matter when you're modeling diffusion rates. The immune function is also underrated. Langerhans cells and intraepithelial lymphocytes are present in nonkeratinized epithelium, but they're distributed differently than in keratinized skin. In nonkeratinized tissue, immune surveillance cells tend to cluster in the suprabasal layers rather than the basal layer, which makes sense evolutionarily — the surface is where pathogens first contact the tissue, so that's where the immune sentries need to be. This has implications for how infections and autoimmune conditions present in these tissues. There's also the matter of regeneration capacity. Nonkeratinized stratified squamous epithelium regenerates faster than keratinized epithelium after injury because the stem cell niche in the basal layer is more accessible and the turnover rate is higher. Wound healing in oral mucosa takes about three to five days for complete re-epithelialization, compared to two to three weeks for equivalent wounds in keratinized skin. The reason isn't just cell proliferation speed — it's also the anti-fibrinolytic environment of the oral cavity, which promotes clot stability and reduces inflammation during the early healing phase.
Practical Takeaways for Working With This Tissue
If you're processing samples, keep fixation time between six and twelve hours in neutral buffered formalin. Overfixation hardens the tissue and makes clean sectioning nearly impossible, especially at the epithelial-stromal interface where you need clear demarcation. Underfixation causes autolysis in the superficial layers first, which is exactly where you need the best morphology. For staining protocols, a standard H&E with a nine-minute hematoxylin stain and differentiated in 1 percent acid alcohol gives the clearest nuclear detail for this tissue type. Going longer than that muddies the cytoplasm and makes layer distinction harder. The eosin stain should be no more than two minutes — longer and the pale cytoplasm of nonkeratinized cells blends into the background. If you need higher resolution of the intercellular junctions, scanning electron microscopy shows the tight junctional complexes clearly, but preparation artifacts are common. The critical step is rapid fixation at 4 degrees Celsius before any chemical processing, and using glutaraldehyde at 2.5 percent for at least two hours. Room temperature fixation causes the cell membranes to retract and the junctional complexes to collapse, giving you a completely misleading picture of the barrier structure.

For anyone doing molecular work on this tissue, the RNA quality is generally excellent because the cells are metabolically active throughout the layers, not just in the basal zone. That's unlike keratinized epithelium where the upper layers are transcriptionally silent. If you're pulling RNA from oral or vaginal swabs for gene expression analysis, nonkeratinized epithelial cells will give you higher yield and better integrity scores than you'd get from skin swabs processed the same way. Just account for the bacterial load in those sites — it can skew your rRNA depletion efficiency if you're not using a eukaryotic-specific protocol.


