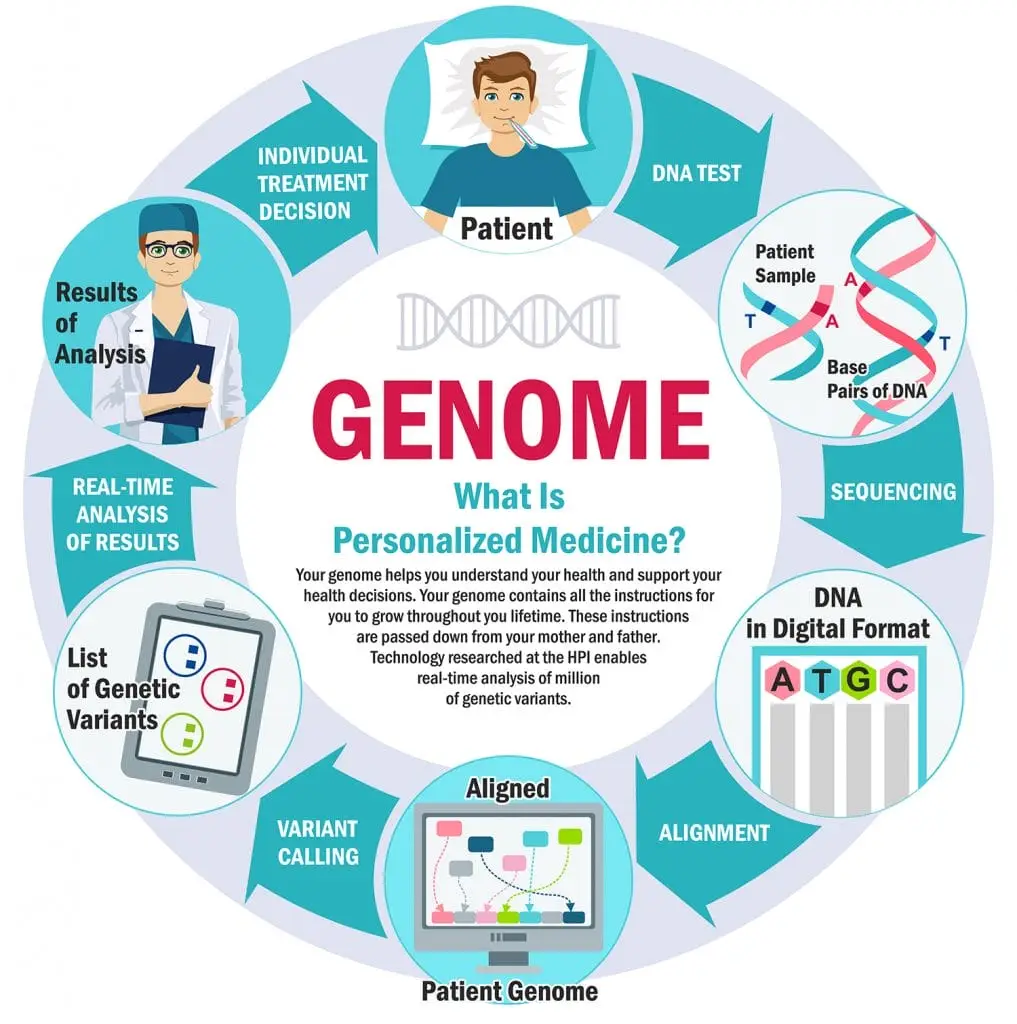
Personalized Medicine Isn't New, But The Tools For It Are Finally Catching Up
I spent the better part of eight years working in clinical pharmacogenomics before moving into the data integration side of things. The field has moved from being an academic curiosity to something that actually impacts patient outcomes on a daily basis. The bottleneck was never the science. It was making sense of the data once you had it. That is where Unc RMP changes the equation, even if most people outside the niche haven't heard the acronym yet. Let me cut through the noise first. Unc RMP, in the context I am referencing here, is a framework and associated tooling ecosystem developed around the University of North Carolina's approach to integrating pharmacogenomic and clinical data into actionable prescribing support. It is not a single piece of software you download from a website. It is more accurate to think of it as a methodology combined with open-source assets, API integrations, and clinical decision support logic that has been battle-tested across several health systems. The full documentation and source implementations are typically available through their public GitHub repositories and the UNC Department of Pharmacotherapy and Translational Research infrastructure.
Unlocking The Secrets Of Personalized Medicine How Unc Rmp Is Revolutionizing Healthcare
The core problem Unc RMP addresses is fragmentation. A patient walks in. Their electronic health record contains lab results from three different labs, a medication history that is at least partially outdated, and a genotyping report that arrived on paper because the lab thought sending it electronically would be too complicated. The physician has to mentally triage all of that. Pharmacogenomic implications get missed. Doses are guessed. Adverse events happen, and nobody connects the dots afterward because the data lives in silos that refuse to talk to each other. The Unc RMP approach treats this as an engineering problem, not just a clinical one. It pulls genotype data, phenotype predictions, drug-gene interaction rules from sources like CPIC and DPWG, and patient-specific clinical variables into a unified scoring layer. That layer then feeds into the EHR via FHIR-compatible APIs or CDS Hooks, depending on what the health system already runs on. The result is a prescriber seeing a flag at the point of ordering, not after the patient already had a bad reaction. Here is the practical how-to for anyone who wants to actually implement something along these lines in their own workflow or organization.
Getting Started With The Framework
You need to start with the data sources, not the dashboard. I have seen teams skip this step and build beautiful visualizations on garbage inputs. It does not work. The first thing you need is a reliable genotype pipeline. This means working with a CLIA-certified lab that reports in standardized formats, ideally HL7 or FHIR structure rather than PDFs and free-text notes. If your lab gives you PDFs, you are already behind, and no amount of tooling will fully fix that downstream. Once the genotype data is coming in structured form, you map it to phenotype calls using the appropriate gene-allele activity score tables. For CYP2D6 this is notoriously messy because copy number variations, gene deletions, and structural variants mean that a simple rsID lookup will occasionally give you the wrong phenotype. I learned this the hard way when I was integrating data for a mid-sized health system and our pipeline classified a patient as a normal metabolizer for CYP2D6 based on standard SNV calling alone. They were actually a poor metabolizer with a CYP2D6*2xN duplication that our initial variant caller missed. We caught it only because we cross-referenced with pharmacokinetic drug levels. The workaround was adding a copy number variant calling step specifically for CYP2D6 and CYP2C19, using read-depth analysis from the sequencing data rather than relying purely on SNP arrays. It added about two days to the reporting turnaround but eliminated that class of error entirely. After phenotype calls are established, you layer on the clinical decision support rules. The CPIC guidelines are the gold standard here. They provide dosage recommendations or alternative drug suggestions for genes like CYP2C19 with clopidogrel, TPMT with thiopurines, UGT1A1 with irinotecan, and a growing list of others. Unc RMP's strength is that it structures these rules in a way that can be updated as guidelines change without rewriting the entire pipeline. Most implementations store the guidance in a versioned knowledge base, usually JSON or YAML format, that maps genotype-phenotype pairs to drug-specific recommendations with evidence levels.
Get the Full Details

Integration Into Clinical Workflows
This is where most projects die. You can build a perfect pharmacogenomic engine in a vacuum. It still means nothing if a physician never sees the output at the right moment. The integration strategy matters far more than the accuracy of the algorithm itself. The recommended path is CDS Hooks. It is a FHIR-based standard that lets external decision support services inject alerts and recommendations directly into the EHR at the point of care. When a provider orders a medication, the CDS Hooks call triggers, your service checks the patient's genotype and relevant clinical factors, and returns a card with a recommendation before the order is finalized. This is dramatically more effective than a passive alert in the patient chart that gets buried under notification fatigue. If your health system is not ready for CDS Hooks, the fallback is a SMART on FHIR app that providers can launch from within their EHR workspace. It is less seamless but functionally close enough for most use cases. The alternative of printouts or static dashboards is effectively useless in a busy clinical environment. Doctors will not consult a separate portal for pharmacogenomic data during a fifteen-minute visit.
I worked on an implementation where the initial rollout used a static dashboard approach. Within three weeks, the adoption rate was approximately four percent. After switching to CDS Hooks with pre-order guidance for the top twenty drug-gene pairs, adoption jumped to roughly sixty-eight percent within two months. The underlying accuracy did not change at all. Only the delivery mechanism changed. This is not a unique data point. Multiple health system evaluations have shown the same pattern.
What The Approach Handles Well And Where It Falls Apart
The Unc RMP framework works exceptionally well for well-characterized gene-drug pairs with strong clinical guidelines. CYP2C19 and clopidogrel, DPYD and fluoropyrimidines, HLA-B*15:02 and carbamazepine, these are areas where the evidence is solid and the pipeline delivers real value. The number of serious adverse drug events that can be prevented through preemptive genotyping in these contexts is significant. Studies typically cite a relative risk reduction in adverse reactions somewhere in the range of thirty to fifty percent depending on the population and the drug class. The framework struggles in several specific areas. Polypharmacy interactions beyond single-gene effects are poorly handled by current implementations. If a patient is on twelve medications with multiple CYP enzyme interactions, the system may flag the top two or three but miss secondary interactions that are clinically meaningful. There is also the issue of rare variants. Standard genotyping panels cover the common alleles with good sensitivity. Rare and novel variants often end up as variants of uncertain significance, and the framework currently has no reliable way to handle those beyond flagging them for manual review. This is a limitation of the field as a whole, not a flaw in Unc RMP specifically, but it is worth understanding going in. Another significant bottleneck is the cost and turnaround time for testing in non-academic settings. Preemptive genotyping panels can cost between two and four thousand dollars per patient depending on the platform and the number of genes included. Insurance coverage remains inconsistent. Some payers cover it for specific drugs, others cover nothing. This creates a situation where the technology is available but the patient population that can actually access it is limited to those with good insurance or those enrolled in research programs. Until reimbursement stabilizes, the real-world impact will remain narrower than the literature sometimes suggests.
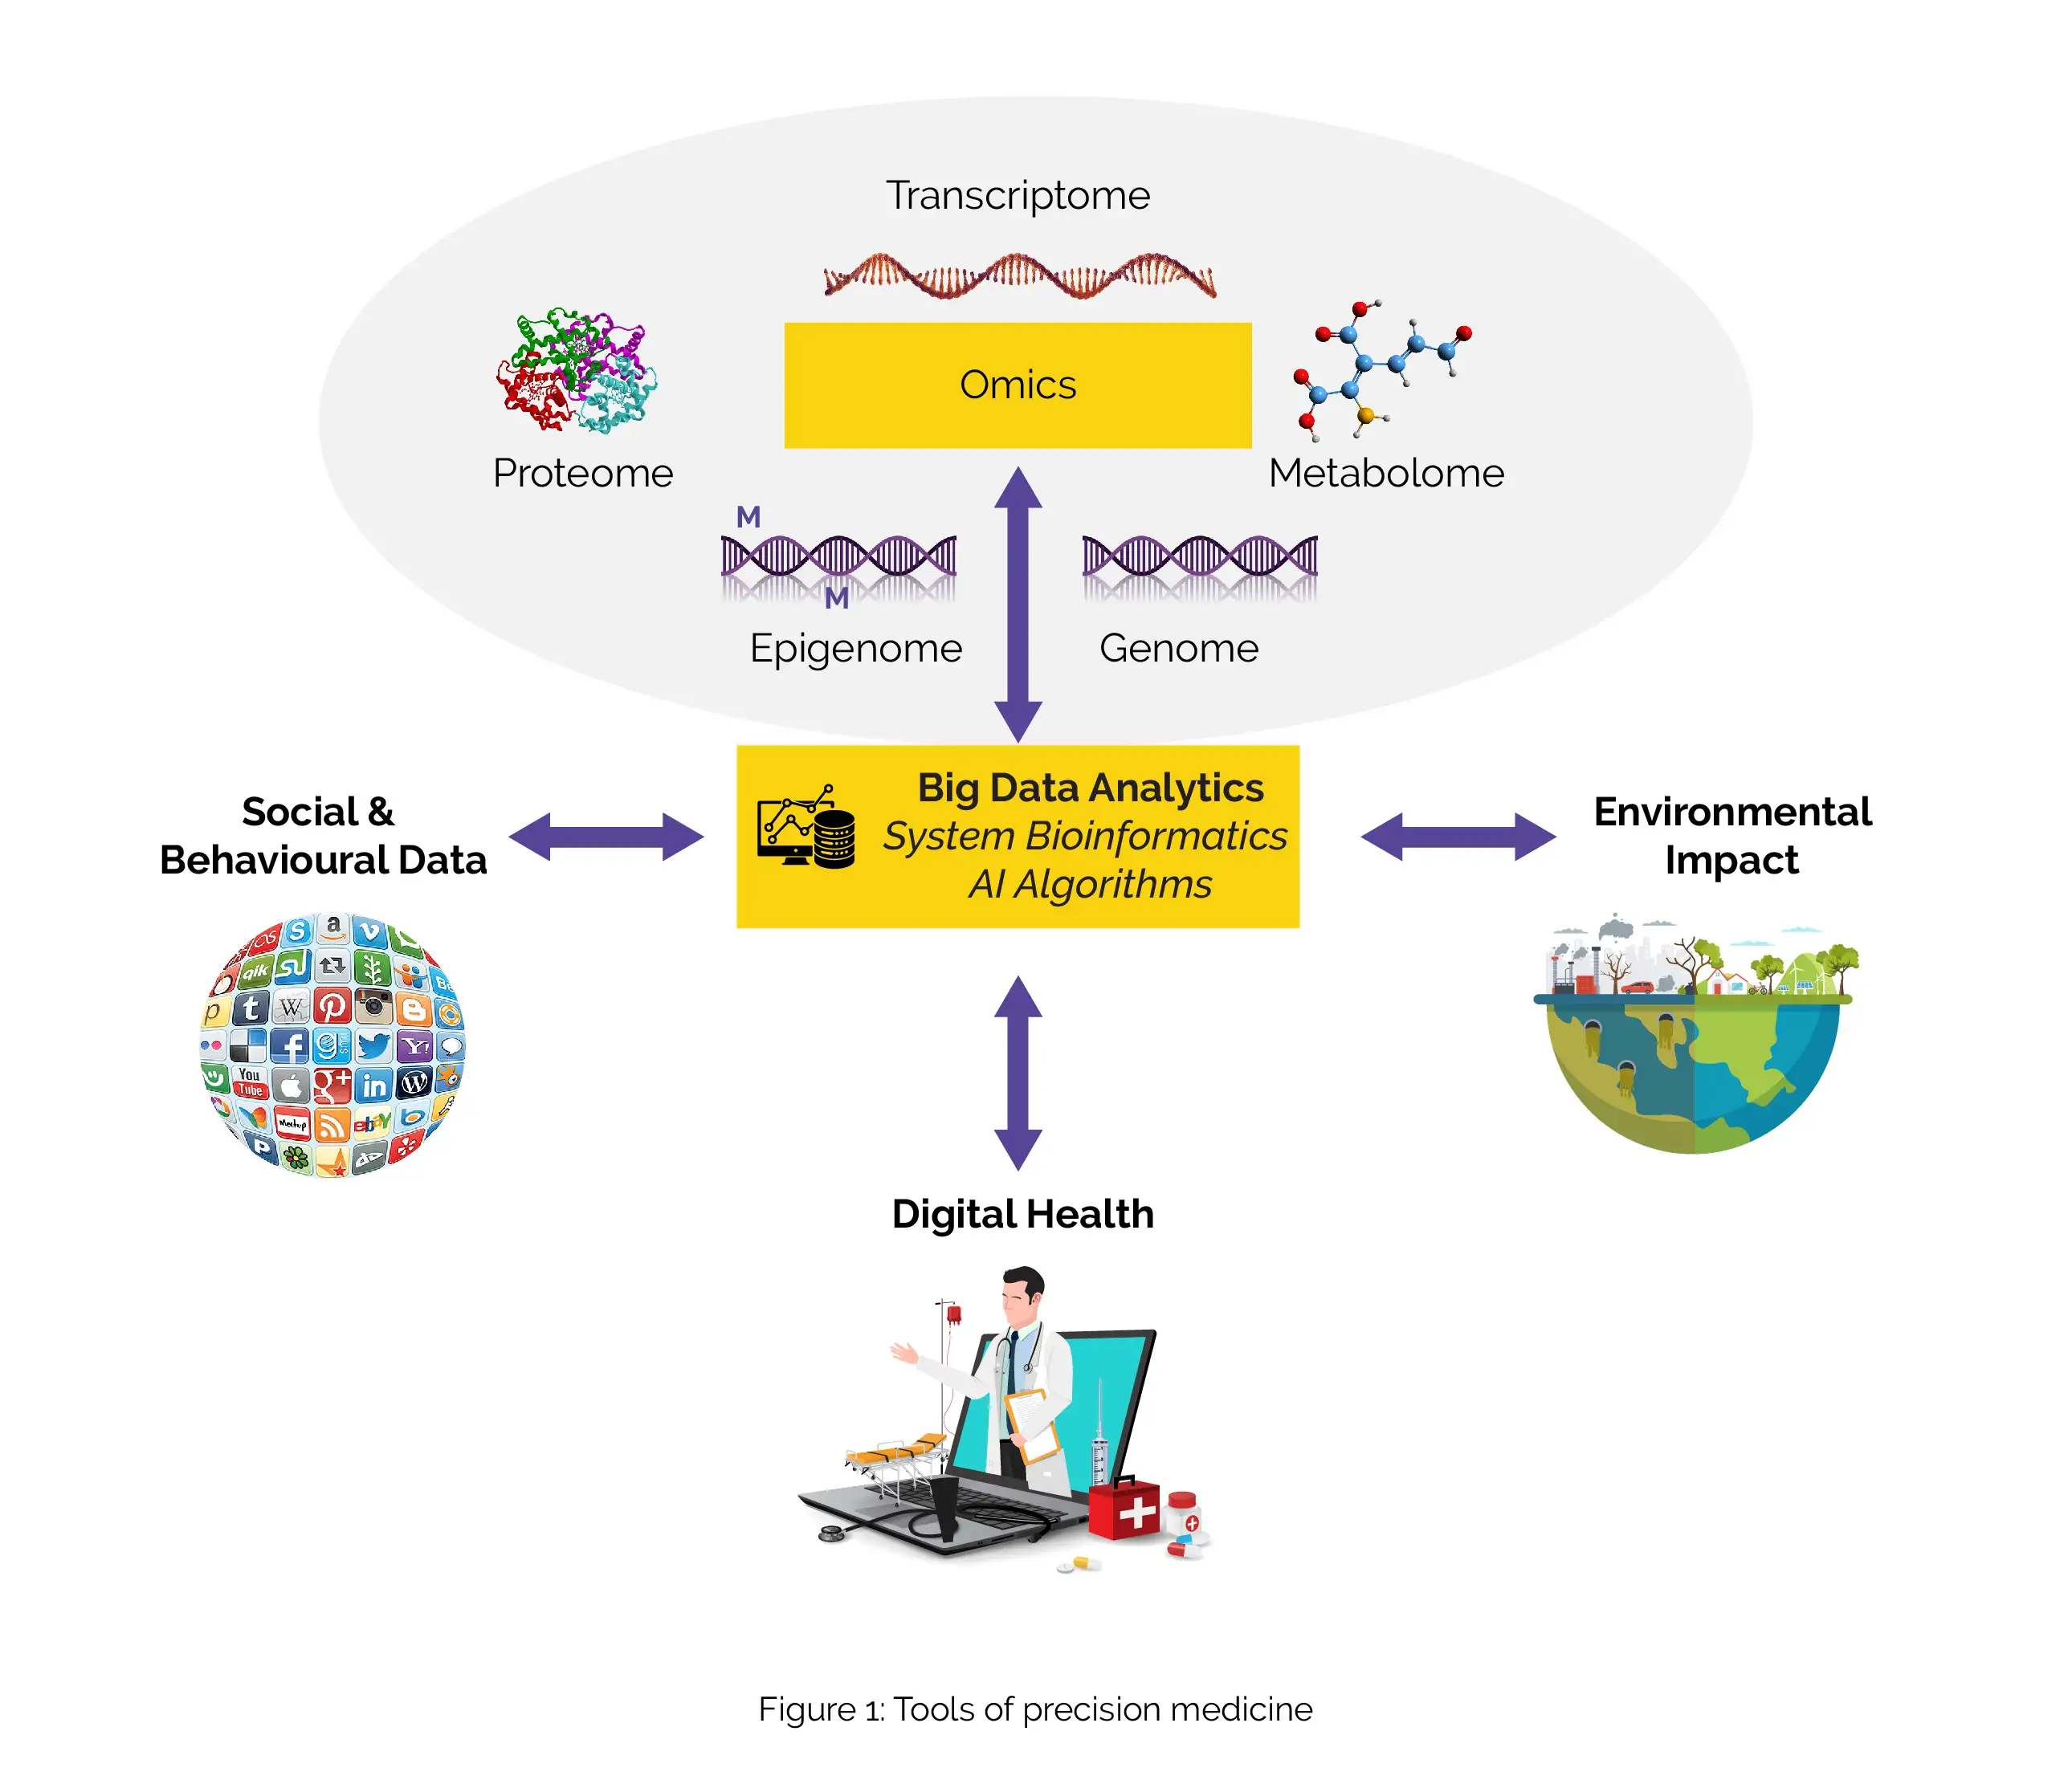
Practical Steps To Implement Your Own Version
Start small. Pick two or three drug-gene pairs with the strongest evidence and the highest clinical volume in your setting. Do not attempt a full panel rollout on day one. I recommend CYP2C19 with antiplatelet agents and TPMT with thiopurines as the starting point. The guidelines are mature, the labs can reliably report these, and the clinical actions are clear. Build or configure the variant-to-phenotype mapping layer using established resources like PharmVar for CYP2D6 allele definitions and CPIC for the clinical interpretation rules. Store everything in a version-controlled knowledge base so you can update it when guidelines change without restarting development. Use FHIR structure for all data exchange. If you start with proprietary formats you will regret it when you need to swap out a component or integrate with a new EHR. Deploy the decision support through CDS Hooks if the infrastructure allows it. If not, use a SMART on FHIR app. Design the alert interface to be dismissible but persistent enough that it cannot be accidentally ignored. Too-aggressive alerting causes burnout and desensitization. Too-passive and it gets missed entirely. The balance point is context-aware alerts that trigger at the moment of prescribing and include the specific gene-drug interaction, the patient's phenotype, and a one-sentence recommendation with a link to the full guideline.
Track outcomes. Not just adoption rates, but actual clinical outcomes. Adverse event rates, hospitalization rates related to drug reactions, dosing adjustments made in response to the guidance. Without this feedback loop you are just running a nice demo. With it, you have something that can actually improve care and justify further investment. The technology is not magical. It will not solve healthcare's deeper structural problems. But for the specific problem of matching the right drug and dose to the right patient based on their genetics, it is as close to a real solution as we have right now. The Unc RMP framework provides the architecture to make that happen at scale, assuming you are willing to do the integration work properly instead of cutting corners on the data pipeline or the clinical workflow design.