Understanding Genetic Mutations In Practice
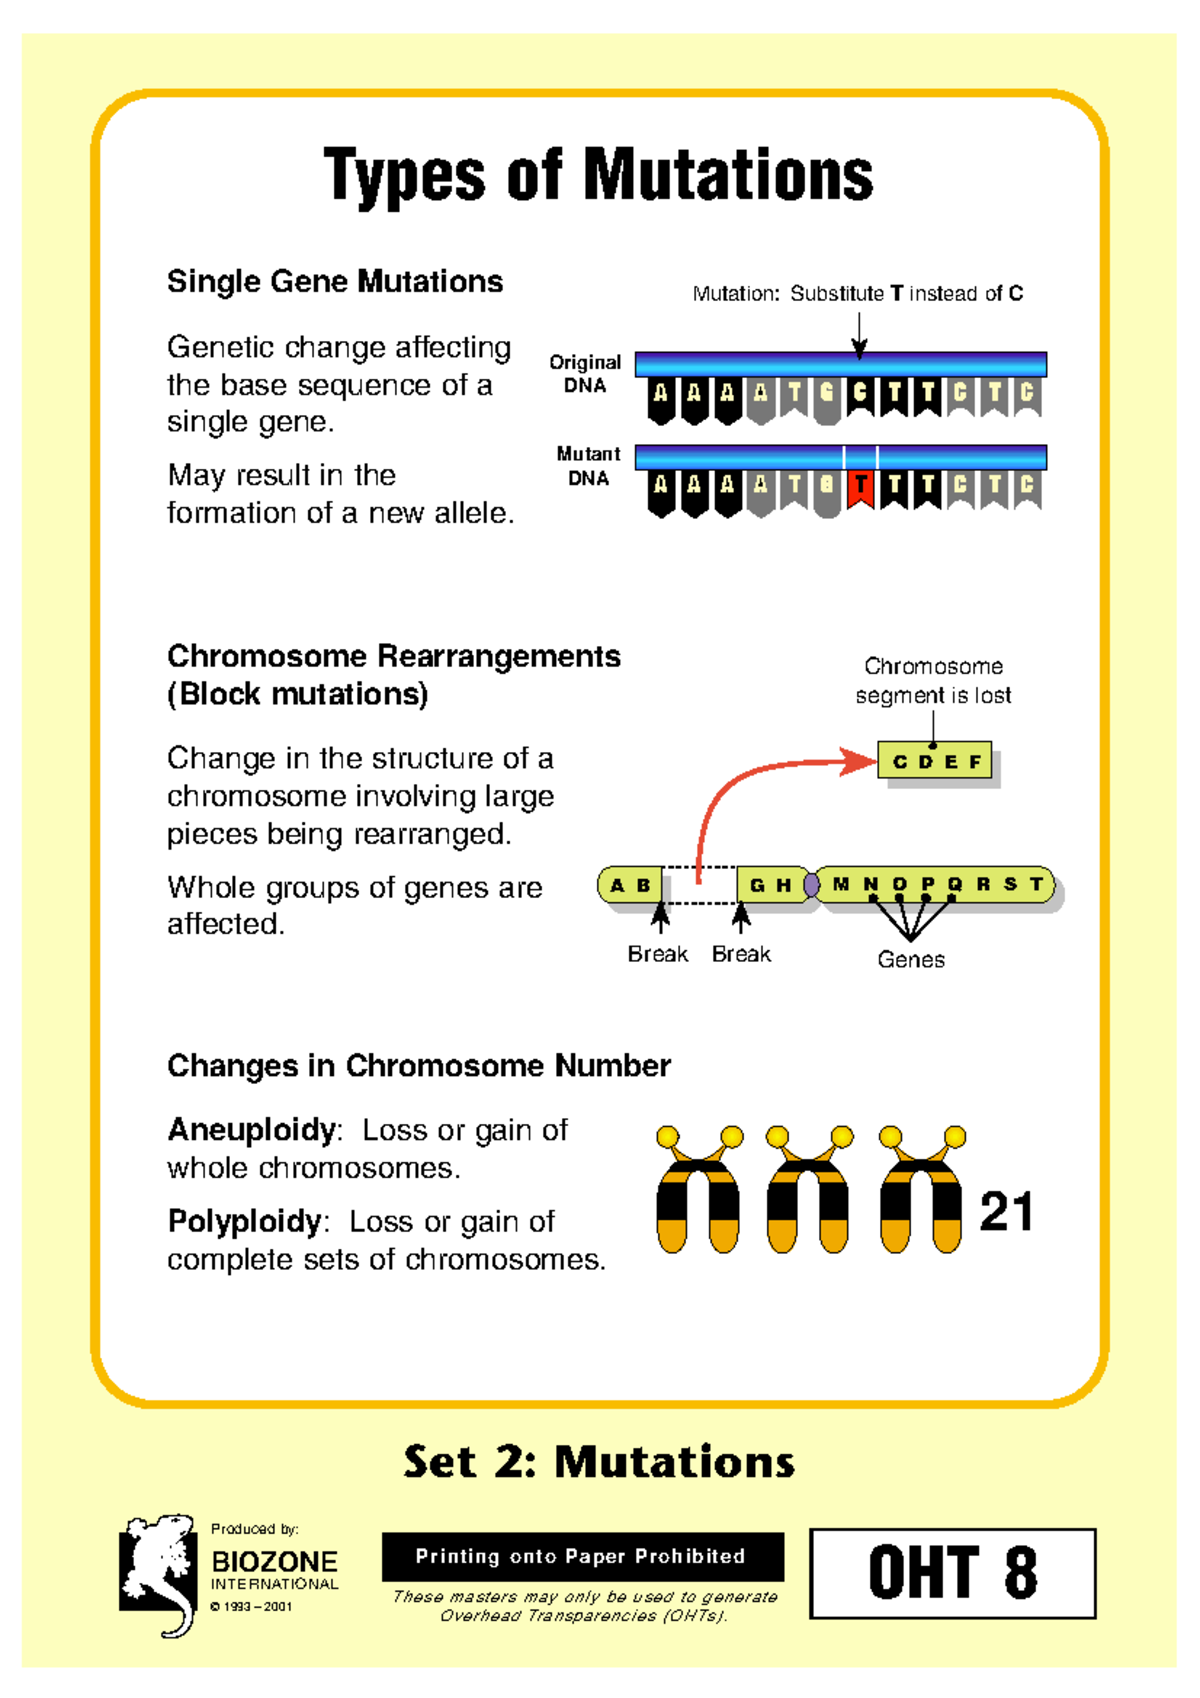
Most people think of mutations as dramatic transformations, but the reality is far more granular and mechanistic. When I first started working with sequence data, I assumed the textbooks had the whole story. They don't. The categories are useful as a starting framework, but they break down fast when you actually look at real biological systems. This is what I've learned after spending years cataloging and interpreting genetic variation across populations. Mutations fall into several broad categories, but the boundaries between them are fuzzy. Let me walk through the main types and what actually happens when you encounter them in a real dataset. Point mutations are single nucleotide changes. That sounds simple. They come in three flavors: transitions, where a purine swaps for another purine (A to G or C to T) or a pyrimidine swaps for another pyrimidine, and transversions, where a purine becomes a pyrimidine or vice versa. In practice, transitions happen about ten times more often than transversions in most organisms. This isn't arbitrary. It's because the chemical structure of transitions preserves the double helix shape better, so DNA polymerase makes fewer errors during replication, but when it does slip, transitions are the result. Transversions distort the helix more and are usually caught by proofreading mechanisms, which is why they're rarer.
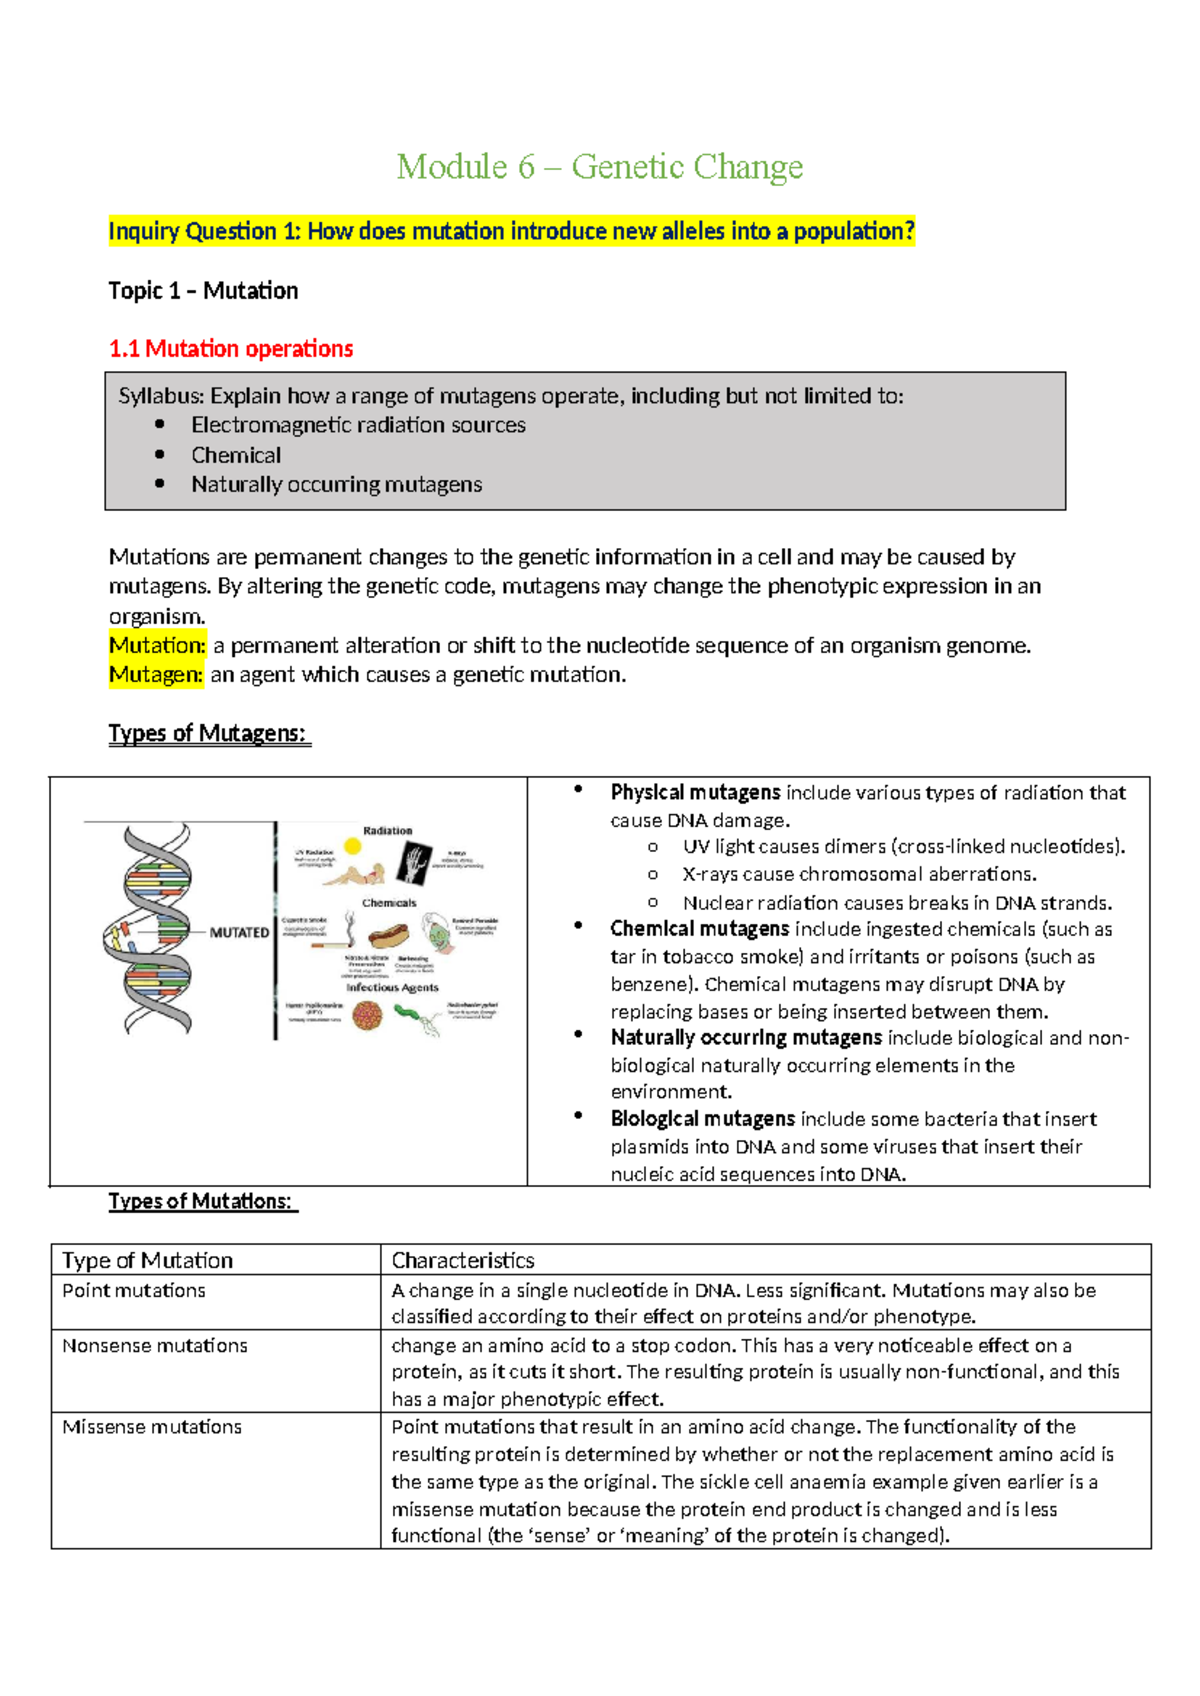
Within point mutations, you need to track whether the change is silent, missense, or nonsense. A silent mutation changes the DNA sequence without changing the amino acid, thanks to codon degeneracy. A missense mutation swaps one amino acid for another. A nonsense mutation creates a premature stop codon. Here's where it gets interesting: silent mutations are not always neutral. I spent weeks tracking what appeared to be a harmless synonymous variant in a mitochondrial gene, only to discover it was disrupting a splicing enhancer sequence. The protein came out fine, but the mRNA processing was off, and expression levels dropped by about forty percent. That variant was showing up in patient samples and nobody had flagged it because the classification said "silent." Insertions and deletions, collectively called indels, are next. A single base insertion or deletion causes a frameshift when it occurs within a coding region. The reading frame shifts entirely downstream of the mutation, which usually produces a completely nonfunctional protein. Two base indels also cause frameshifts. Three base indels preserve the frame but add or remove a single amino acid. The practical consequence depends heavily on where in the gene the indel sits. An in-frame deletion of three bases in a non-critical region might have no observable effect. The same deletion in an active site region can destroy protein function completely. I've seen indels misclassified as benign simply because the variant was classified by position without considering structural context. Duplication mutations copy a segment of DNA, sometimes duplicating entire genes. This is different from a simple indel because the copied material is inserted adjacent to or near the original. Duplication is a major driver of evolutionary innovation. Gene families like the globin genes exist because of duplication events followed by divergence. But duplication can also cause disease. A 1.5 megabase duplication on chromosome 17 that includes the PMP22 gene causes Charcot-Marie-Tooth disease type 1A. The extra copy leads to overexpression of the protein, which disrupts myelin sheath formation. In clinical sequencing, duplications are notoriously hard to detect with standard short-read methods. I found a case where a patient's symptoms pointed directly to PMP22 duplication, but the whole exome sequencing data came back clean. We ended up using multiplex ligation-dependent probe amplification to confirm it. Short-read NGS just doesn't resolve copy number changes well in repetitive regions.
Inversion mutations flip a segment of DNA end-to-end. The genetic material is still there, but the orientation is reversed. If an inversion falls within a single gene and doesn't break any critical sequences, it might have no phenotypic effect. If it spans a breakpoint within a gene, it can disrupt coding sequence or regulatory elements. Large inversions are difficult to detect with standard sequencing approaches. You need split-read mapping or paired-end analysis to catch them reliably. I once worked with a dataset where an inversion was suspected based on missing heterozygosity patterns, but confirming it required long-read sequencing. By that point, the sample had been through multiple extraction rounds and the DNA was too fragmented for accurate long-read assembly. Chromosomal mutations involve large-scale changes to chromosome structure. These include translocations, where segments swap between nonhomologous chromosomes, and aneuploidy, where entire chromosomes are gained or lost. The Philadelphia chromosome, a translocation between chromosomes 9 and 22 that creates the BCR-ABL fusion gene, is the classic example. It drives chronic myeloid leukemia. Aneuploidy mutations are usually lethal in mammals unless they involve sex chromosomes or very small chromosomes. Down syndrome results from trisomy 21, one of the few whole-chromosome gains that allows survival to term. There's another category that doesn't fit neatly into the standard framework: dynamic mutations. These involve expansion of tandem repeat sequences, like trinucleotide repeat disorders. Huntington's disease comes from CAG repeat expansion in the HTT gene. The repeats are stable through most generations but can expand significantly during gametogenesis, a phenomenon called anticipation, where each generation shows earlier onset and more severe symptoms. I encountered a family where the father had been classified as pre-symptomatic with a moderate repeat count, but his children showed full disease manifestation with much longer expansions. The parents had been told the variant was stable. It wasn't. Repeat expansion genotyping requires specialized PCR protocols, not standard Sanger sequencing, and even then, very long repeats can be difficult to amplify accurately.
Get the Full Details
How To Categorize Mutations When You're Looking At Real Data
Classification starts with identifying the variant type, then determining its location relative to functional elements, and finally assessing its likely impact. Tools like ANNOVAR, VEP, and SnpEff can automate much of this, but they make assumptions that aren't always valid. I've seen variants annotated as intronic when they actually overlap deep intronic regulatory elements. I've seen intergenic variants dismissed when they sit in conserved non-coding sequences with demonstrated enhancer activity. The ACMG/AMP guidelines provide a framework for pathogenicity classification, combining multiple evidence types. But the system has gaps. Variants of uncertain significance make up a substantial portion of clinical reports, sometimes over thirty percent in some genes. The guidelines weigh population frequency heavily, which works well for common variants but underweights rare functional evidence for unusual mutations. I recommend supplementing computational predictions with experimental data whenever possible. Functional assays, even simple ones like minigene splicing assays, can resolve uncertainty that bioinformatics alone cannot. When you're building a mutation catalog or interpreting clinical reports, pay attention to the reference genome version and the annotation database versions. GRCh37 and GRCh38 coordinate systems differ in ways that matter for variant positioning. Annotations from Ensembl release 100 versus release 110 can assign different functional consequences to the same variant. I've seen the same variant reported as pathogenic in one database and benign in another, purely because the annotation pipelines used different transcript models. Always check which versions were used and whether alternative transcripts might change the interpretation.
One thing that catches people off guard: mutation rate varies dramatically across the genome. CpG sites mutate at roughly ten times the background rate because cytosine methylation followed by spontaneous deamination produces thymine. This creates hotspots that show up repeatedly across unrelated individuals. If you see the same mutation in multiple patients, check whether it falls on a CpG dinucleotide before concluding homoplasy or shared ancestry. Most of the time, it's just the mutation rate doing what it does. Here's another practical point that matters more than people realize. Germline and somatic mutations require different analytical approaches. Germline variants are present in all cells and inherited. Somatic variants occur in specific tissues and accumulate over a lifetime, especially in rapidly dividing cells. Cancer sequencing pipelines filter out germline variants to focus on somatic changes, but if you're studying a tumor with high microsatellite instability, the germline background can be noisy enough to obscure true somatic calls. I've recommended orthogonal validation with deep normal tissue sequencing in cases where the tumor purity was below sixty percent. Below that threshold, somatic variant calling becomes unreliable without a matched normal sample. Mutation categories are a useful organizing principle, but they don't capture the full complexity of what happens in actual genomes. The functional consequences of a genetic change depend on context, dosage, redundancy, and cellular environment. Classification tells you what changed. Understanding what it means requires looking beyond the category.