So You Want To Understand MRI
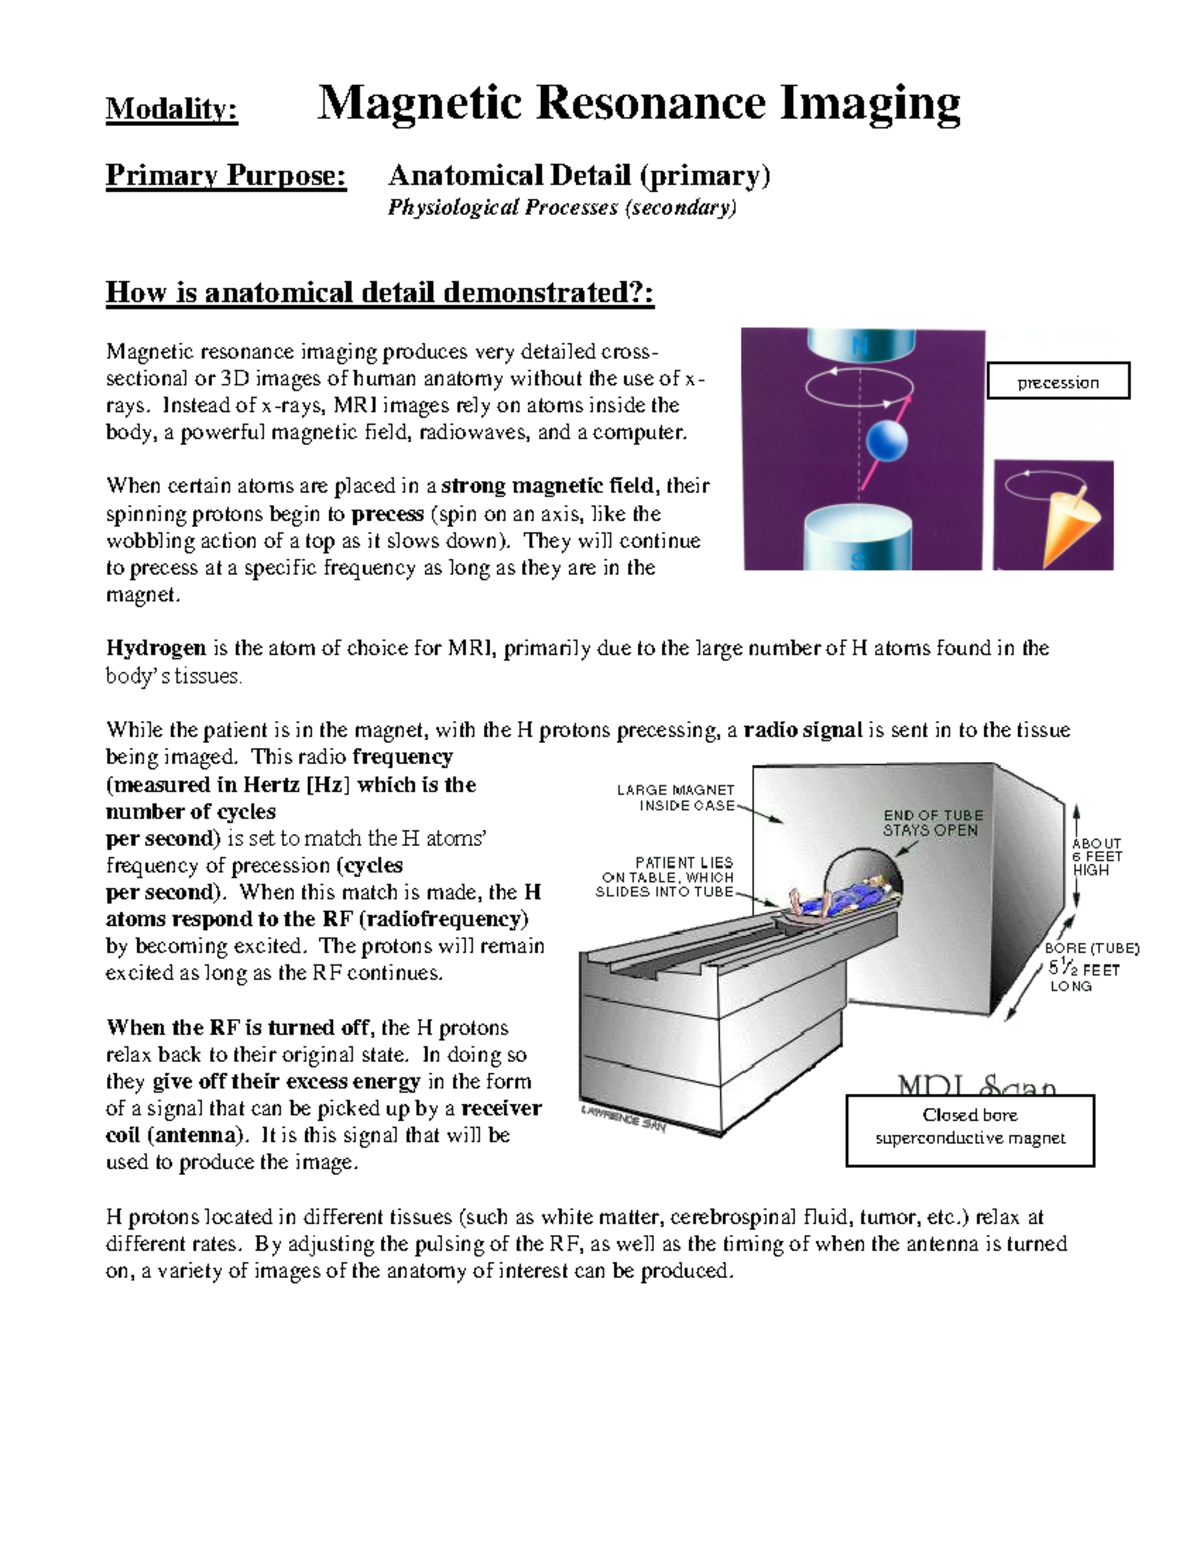
Magnetic resonance imaging is basically a big superconductor wrapped around a table. You lie down, a magnet does its thing, radio waves hit water molecules in your body, and a computer turns the echo into a picture. That is the tl;dr version. The reality is messier than that cartoon explanation. I spent most of my twenties reading gradient coils and troubleshooting artifacts at 2am because the night tech called and said the Siemens Skyra was throwing a phantom image error again. You learn more about MRI in those moments than you do from any textbook diagram.
Unlocking The Secrets Of MRI Understanding Magnetic Resonance Imaging
The core physics is straightforward enough. Hydrogen nuclei in your body act like tiny spinning magnets. A strong static field, usually 1.5T or 3T, aligns them. A radiofrequency pulse tips them off axis. When they relax back, they emit a signal. Gradient coils spatially encode that signal so you can reconstruct where it came from. K-space is the raw data space. You fill it with phase-encoding and frequency-encoding steps, then Fourier transform it into the image you actually look at. What nobody tells you up front is that k-space is not just some abstract math concept. The center of k-space holds the contrast information. The edges hold the fine detail. If you undersample the center, your image looks blobby. If you undersample the edges, it loses sharpness. That distinction matters when you are running accelerated sequences. I ran into a real problem once where a patient with a known cochlear implant was scheduled for a brain MRI. The manufacturer brochure said it was "MRI conditional," which turned out to mean the device would survive the scan but the image quality around the temporal bone was completely unusable. The workaround was to switch to a 1.5T system instead of the 3T, use a low-SAR spin-echo sequence rather than a gradient echo, and apply z-shimming to reduce the susceptibility artifact. The implant still created a massive blowout, but we could see the rest of the brain. You do not get a perfect exam with that hardware in place, but you can salvage something useful.
Sequence design is where most people get lost. Spin echo versus gradient echo is the first fork in the road. Spin echo refocuses static field inhomogeneities, which makes it more robust against susceptibility artifacts. Gradient echo does not, which is why it is sensitive to hemorrhage and calcification on GRE or SWI sequences. You pick one based on what you are looking for, not because one is inherently better. TR and TE are the two knobs that control contrast. Long TR and long TE give you T2 weighting. Short TR and short TE give you T1 weighting. Proton density sits somewhere in between. FLAIR is just a T2-weighted sequence with an inversion time set to null the CSF signal. That inversion time is usually around 2000ms at 1.5T and a bit shorter at 3T. Get it wrong and the CSF either stays bright and ruins your periventricular lesion detection, or it gets partially nulled and the image looks strangely flat. Parallel imaging is standard now. SENSE and GRAPPA both accelerate acquisition by using the spatial information from multiple coil elements. You can typically get a factor of 2 without major issues. Factor of 3 is possible but starts introducing reconstruction artifacts if your coil geometry is not clean. SNR drops roughly with the square root of the acceleration factor, so a race of 2 costs you about 30 percent signal. That is why modern head coils with 32 channels make such a difference. More channels means more spatial encoding information, which means you can push higher acceleration factors while maintaining diagnostic quality.
Get the Full Details

Here is something most beginners miss: shimming is not optional. A poorly shimmed scan at 3T looks worse than a well shimmed scan at 1.5T. Automatic shimming does most of the work, but for certain anatomical regions, especially the brain base and temporal lobes, you often need manual third-order shim adjustments. I have seen studies where the diagnosis was borderline because the local shims were left at the factory default and the susceptibility artifacts made a small cavernoma invisible. Running a localized shim routine before your diagnostic sequence takes about ninety seconds and can change the entire diagnostic confidence. Motion is the enemy. You can buy advanced motion correction software, and it helps, but it is not a magic bullet. The most practical solution is still keeping the patient still. For pediatric or anxious patients, sedation is often the right call. For adults who can hold still but have chronic pain, splitting the exam into shorter blocks with breaks usually produces better results than pushing through a 45-minute scan where the patient is gradually getting worse. Motion artifacts tend to appear as ghosting along the phase-encoding direction, so knowing which direction your sequence uses lets you distinguish motion from real anatomy. SAR, or specific absorption rate, is the limitation you will run into most at 3T. RF energy deposition is proportional to the square of the Larmor frequency, so going from 1.5T to 3T roughly quadruples the SAR for the same sequence parameters. This means you cannot simply copy your 1.5T protocols to 3T and expect them to work. You have to adjust flip angles, increase TR, or use lower-power pulse designs. The scanner will warn you and often refuse to proceed. The workaround is usually switching from a turbo spin echo to a reduced flip-angle variant or using a controlled heating protocol if you are running long sequences near the limit.
Contrast agents are gadolinium-based, and they shorten T1 relaxation time, making vascular and inflamed tissues appear bright on T1-weighted images. The old linear agents carry a higher risk of nephrogenic systemic fibrosis in patients with severe renal impairment. The macrocyclic agents are safer but more expensive. If a patient has an eGFR below 30, you generally avoid gadolinium unless the diagnostic benefit clearly outweighs the risk, and you use a macrocyclic agent at the lowest possible dose if you proceed. Artifacts will test your patience. Metal implants cause signal voids and geometric distortion. Dental fillings create streak artifacts in head scans. Cardiac and respiratory motion create ghosting. The trick is recognizing the pattern quickly so you know whether to change the sequence, adjust the orientation, or accept that a particular view will never be clean. You cannot fix everything. Some exams just have limitations, and telling the referring physician that clearly is part of the job. The field is moving toward AI-assisted reconstruction and compressed sensing, which can further accelerate acquisitions. The promise is real, but the current implementations still struggle with certain edge cases, especially when the training data does not match the patient population. I have seen AI reconstructions that smoothed out small enhancing lesions because the algorithm interpreted them as noise. You still need a radiologist or physicist validating the output, not just trusting the machine.
If you are getting started, I would suggest running through the basic physics once, then spending real time at the console watching how each parameter change affects the image in real time. Read the protocol documentation for the scanner you use daily. There is a huge gap between knowing what MRI is and knowing how to actually acquire a diagnostic image consistently. The gap closes with practice, not with reading summaries.