
Working With Lateral Subluxation Without Breaking Your Patients
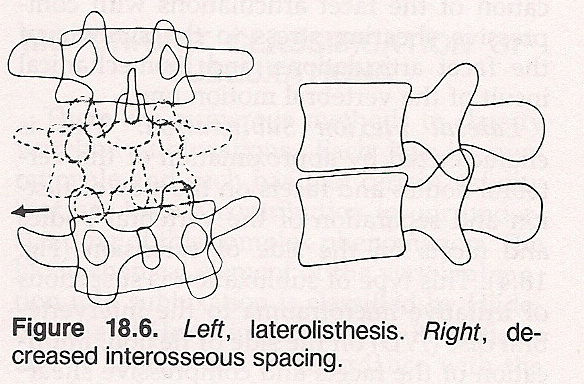
Lateral subluxation usually comes up when you're dealing with a joint where the articular surfaces have shifted sideways relative to each other, but they haven't fully dislocated. Most people who run into this are working in manual therapy, sports rehab, or chiropractic settings. The kind of people who spend too much time looking at X-rays trying to figure out why a patient still has pain three months after treatment. I've spent years trying to map these properly and they are harder to find than the literature makes them look. The problem starts early because imaging doesn't always tell you where things actually are. A standing PA weight-bearing radiograph will show you alignment, but if the patient is slightly rotated or tilted, what looks like a lateral shift might just be positioning artifact. I learned this the hard way with a patient who had a right L4 lateral subluxation on paper. We spent four sessions mobilizing the wrong side before I noticed the pelvis was rotated. The vertebra wasn't the issue, the pelvis was. took it another year to stop making that mistake consistently.
Unlocking The Secrets Of Lateral Subluxation
Here is the practical part. When you have a true lateral subluxation, the joint capsule on the convex side gets stretched and the concave side gets compressed. That compression side is where the restriction lives. You need to decompress that space before any mobilization will stick. If you just start thrusting or grinding from the outside in, you push the joint harder into the restriction and nothing changes. The patient leaves feeling the same. What actually works for me is a three-step approach. First, you locate the concave side by palpating the spinous processes and paraspinal muscles. The tender, tight side is usually the concave compressed side. Second, you use a gentle lateral glide on that side, moving the vertebra away from the compression, not into it. I use about 5 to 10 newtons of force, just enough to create space in the joint. Third, you follow up with oscillatory Grade III movements while maintaining that distraction. The whole process takes maybe twenty minutes per level and works best when the patient is prone with a small pillow under their abdomen to reduce lumbar lordosis. For cervical lateral subluxation, the approach is similar but more sensitive. I find the restricted facet by side-bending the neck and noting where movement stops. Then I apply a lateral glide using a thumb contact on the transverse process of the superior vertebra, pushing it toward the open side. Grade II to III oscillations for about thirty seconds per segment, two or three passes. I usually see improvement in range of motion within the first session for acute cases. Chronic cases take longer and don't always resolve completely, which is worth noting upfront.
There is a specific edge case that trips everyone up including me. When a lateral subluxation is associated with a rotational component, pure lateral glides won't fix it. You have to address the rotation first. I encountered this with a thoracic patient who had a persistent right T8 lateral shift. Every glide I tried produced maybe five degrees of improvement and then it snapped back. After about ten minutes of gentle rotatory mobilization to the left, the lateral shift became much more accessible. The rotation was the primary restriction and the lateral component was secondary. It took me seeing it happen to two other patients before I started checking for rotational partners routinely. One thing beginners consistently get wrong is treating the subluxation in isolation. The adjacent segments usually compensate, which means they become restricted too. I see this constantly in the lumbar spine where L5 compensates for an L4 lateral shift. If you fix L4 and don't address L5, the patient will relapse within days. Always assess the segment above and below the affected level and mobilize any restrictions you find there before you finish the session. Another counter-intuitive point that isn't taught much is that sometimes the side you think is restricted isn't. Palpation can mislead you when there is significant muscle guarding. The paraspinals on the apparent tight side may just be reflexively protecting the joint, not actually causing the restriction. I test this by having the patient gently actively move into the suspected restricted direction. If they can move into it voluntarily but not passively, the issue is more neural or muscular than articular. In those cases, lateral subluxation work is the wrong tool and you should be looking at nerve gliding or myofascial release instead.
Get the Full Details
The tools matter less than the technique. I used to spend money on specialized tables and vibration devices. None of it moved the needle compared to hand positioning and patient communication. A good treatment table with adequate chest and pelvic supports is enough. What matters is that the patient is relaxed and the force you apply is controlled. I use a spring gauge on myMobilization tables sometimes just to verify my feel against a number. It keeps my technique honest when I'm tired or rushing through a long clinic day. There are scenarios where this approach simply fails and you need to change tactics. Advanced degenerative joint disease with significant osteophyte formation will not respond to lateral glide mobilization. The joint surfaces are too irregular and the restrictions are bony, not capsular. In those cases, soft tissue work around the affected area and strengthening of the stabilizing musculature gives better outcomes. I also avoid aggressive mobilization when there is any sign of spondylolisthesis. A lateral subluxation on top of a slip is a recipe for making things worse. Acute trauma cases require a different mindset entirely. If the lateral subluxation resulted from a recent injury, you wait. I typically hold off on any mobilization for at least two weeks unless there is a clear indication that immediate intervention is necessary. Let the acute inflammation settle, let the patient's pain pattern clarify, and then reassess. Treating too early often increases symptoms and delays recovery. Patience here is not a virtue, it is a requirement.
The evidence base for these techniques is thinner than most practitioners would like. There are more case reports than randomized controlled trials, which means your results will vary and you shouldn't present this as guaranteed. Document your findings clearly before and after treatment. Range of motion measurements, pain scores, and functional assessments give you data to work with and protect you if outcomes are unexpected. Most importantly, know your limits and refer out when something doesn't fit the pattern you recognize.


