Understanding Side-Specific Design in Workspace and Movement Planning
Unlocking The Secrets Of Ipsilateral Vs Contralateral Understanding The Difference
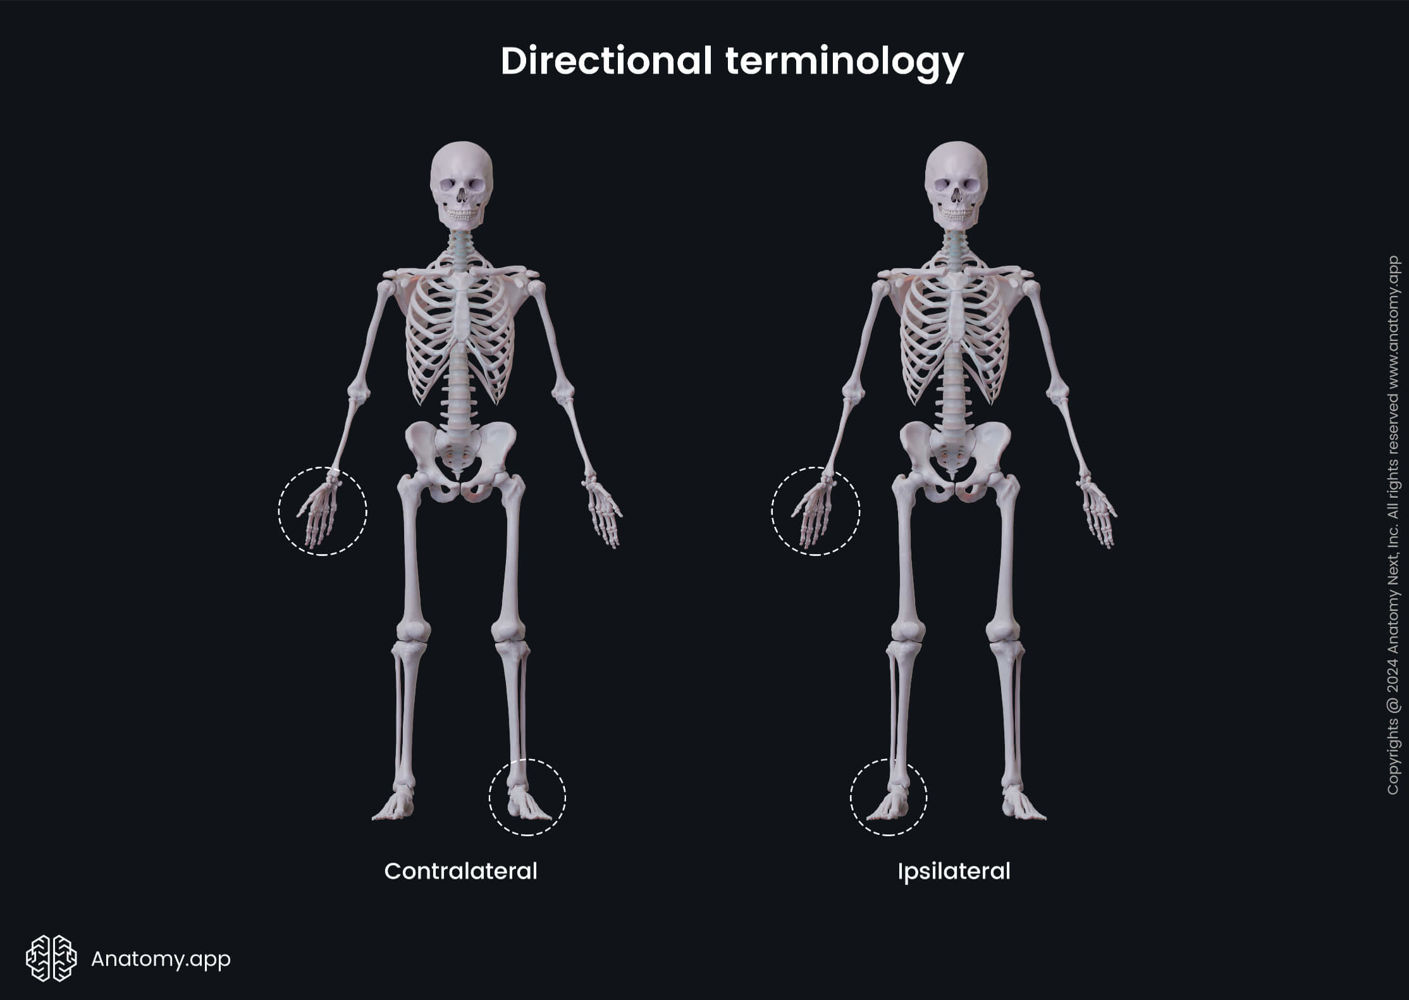
I spent three years troubleshooting why warehouse pickers on one particular line were taking 40% longer per cycle than their counterparts on another, until I realized the difference wasn't motivation or training. It was whether they were working ipsilaterally or contralaterally without knowing it. The tools, the station layout, the motion paths — all of it came down to that distinction. Ipsilateral simply means a relationship on the same side of the body. If you reach with your right hand to grab something positioned to your right, that's an ipsilateral movement. Contralateral means crossing the midline — reaching with your right hand to something on your left, or vice versa. That's it. Basic definition. But the operational implications in any kind of workflow design, clinical assessment, or even basic human factors engineering are where things get complicated fast.
Why This Shows Up In Practice
In ergonomic workstation design, ipsilateral placement is almost always faster and less fatiguing for repetitive tasks. The arm stays in its natural working envelope. The shoulder doesn't have to internally rotate across the torso. You see this in assembly lines where parts bins are staged on the same side as the dominant hand. It cuts average cycle time by roughly 12 to 18 seconds per operation compared to contralateral staging, depending on the weight of the component and the repetition rate. But contralateral work isn't always worse. It becomes necessary and sometimes preferable when you're dealing with bilateral symmetry tasks, or when the workspace geometry forces crossing the midline. Think of a mechanic working on a car engine from the driver's side door reaching across to spark plugs on the opposite bank. You can't rearrange the engine. You work contralateral. The trick is managing the increased spinal rotation and shoulder strain over repeated cycles. In clinical settings, this distinction matters for stroke recovery assessments, neurological screenings, and even basic range-of-motion testing. A therapist asking a patient to touch their nose with their right hand is an ipsilateral task. Asking them to touch their left ear with their right hand introduces contralateral coordination. The difference between a clean execution and a clumsy one can indicate cerebellar dysfunction, hemispatial neglect, or simple motor planning deficits. I've seen junior clinicians miss whole patterns of impairment because they were only testing ipsilateral movement and assuming symmetry.
The Edge Case That Wasted Me A Week
Early in my ergonomics work, I was consulted on a packaging line where operators were reporting chronic shoulder pain. The layout showed every tool and material positioned ipsilaterally. Right-handed operators had everything on the right. Left-handed ones had everything on the left. By all conventional human factors standards, the station should have been optimal. It wasn't. The problem was that the conveyor belt ran perpendicular to the operator's stance, and products were arriving from the contralateral direction. Every single package required a trunk rotation plus an arm reach across the body midline. The station was set up for ipsilateral tool access but the primary task was fundamentally contralateral. We ended up rotating the entire work cell 90 degrees so the conveyor ran parallel to the operator, bringing the incoming product into the ipsilateral zone. Pain complaints dropped by about 70% over six weeks. The fix was simple once I noticed what was actually happening instead of what the paperwork said should be happening.
Get the Full Details

How To Apply This To Your Own Setup
Start by mapping your primary tasks and noting which side of the body each one occupies. If you're doing something like a desk job, look at your keyboard, mouse, phone, and frequently used reference materials. Are they clustered on one side? That's ipsilateral bias. Are you constantly crossing your midline to reach between them? That's contralateral strain. It accumulates. For left-handed people specifically, most consumer and industrial equipment is designed for right-handed ipsilateral use. This means left-handers frequently perform tasks contralaterally by default — reaching across the body with their non-dominant right hand because the tool is positioned for right-hand access. I've seen people buy left-handed mice and never address the fact that their monitor, keyboard, and document holder still forced contralateral patterns. Fix the whole ecosystem, not just one component. In physical rehabilitation contexts, a useful progression is starting with ipsilateral exercises to build confidence and coordination, then introducing contralateral movements gradually. The contralateral pattern requires more neural cross-talk between hemispheres via the corpus callosum. If you skip that transition, you risk reinforcing compensatory movement strategies that mask underlying deficits. I recommend a simple screening: can the person perform a contralateral reach-and-place task smoothly while standing, and then again while maintaining an unstable surface like a foam pad? If balance degrades significantly, that's a red flag for proprioceptive or coordination issues worth escalating to a professional.
Where This Framework Falls Apart
Not every situation maps cleanly onto ipsilateral versus contralateral. In ambidextrous workers, the distinction blurs because both sides are functionally dominant. In tasks requiring true bilateral coordination — like playing certain musical instruments, or operating heavy machinery with dual controls — neither category fits well. You're not really choosing one side over the other; you're engaging both simultaneously with independent motor programs. Another limitation: laterality isn't purely anatomical. It's task-dependent. A right-handed person might work predominantly ipsilaterally with their right hand for fine motor tasks, but switch to contralateral patterns for gross motor activities like throwing. Assuming a person's laterality is fixed based on handedness alone will lead you astray in assessment or design. If you're working in a domain where ipsilateral/contralateral analysis feels insufficient — neurorehabilitation with complex hemiplegia, for example — there are more comprehensive frameworks like Fugl-Meyer Assessment or the Action Research Arm Test that account for graded motor impairments rather than a simple same-side versus opposite-side binary. Those tools are longer to administer but far more informative for pathological populations.
Quick Reference For Common Applications
Office ergonomics: Position your most-used items ipsilaterally. Keep the mouse on the same side as your dominant hand. Document holders and phone within that same lateral zone. Only introduce contralateral reaches for low-frequency, low-importance items. Industrial workstations: Match the primary material flow direction to the operator's dominant side. If the workflow inherently requires contralateral reaching, introduce rest cycles and mechanical assistance like articulated arm holders or gravity-fed bins that reduce the force required for each cross-midline movement. Clinical screening: Test both ipsilateral and contralateral coordination separately. Note asymmetries. A patient who can touch their nose with their right hand but cannot smoothly bring their right hand to their left shoulder may have dyscoordination on the contralateral side that warrants further neurological evaluation.

Home organization: This applies outside of work too. If you cook with your right hand, keep your primary cutting board, knife, and prep bowl on the right side of the stove. The contralateral grab for salt shaker or spices should be a brief secondary reach, not the default motion pattern. Kitchens designed around ipsilateral workflow zones tend to feel more intuitive and cause less fatigue over long cooking sessions.