Understanding Heme and Its Role in Human Biology
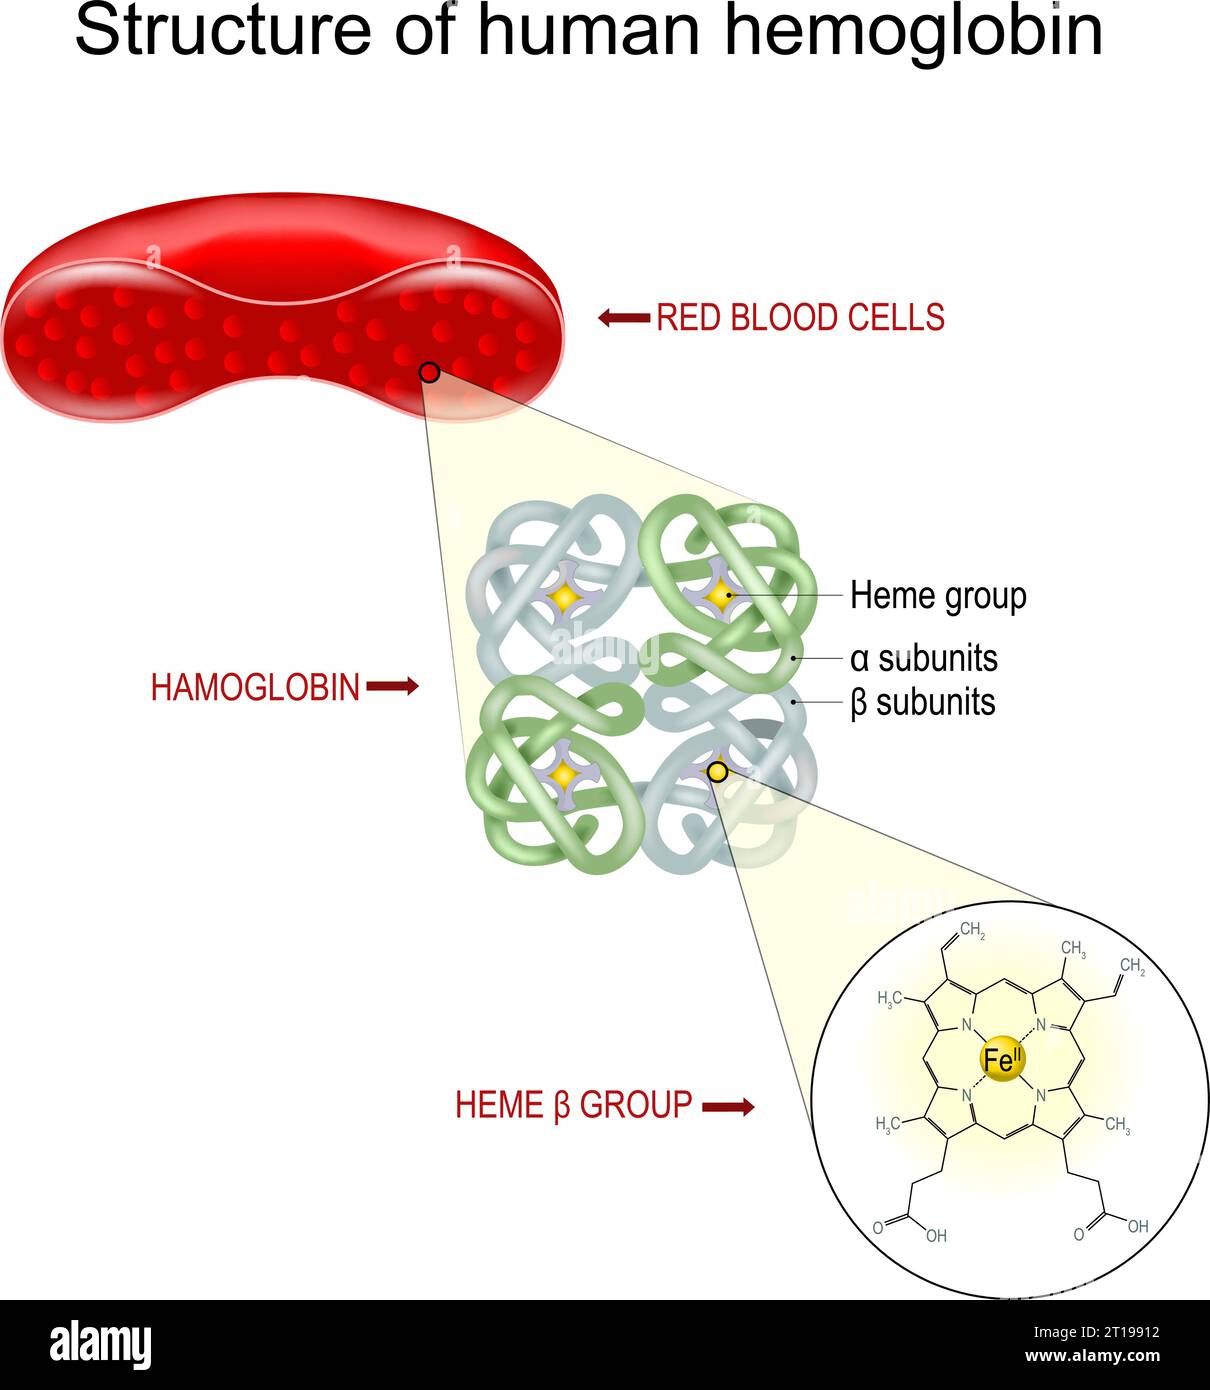
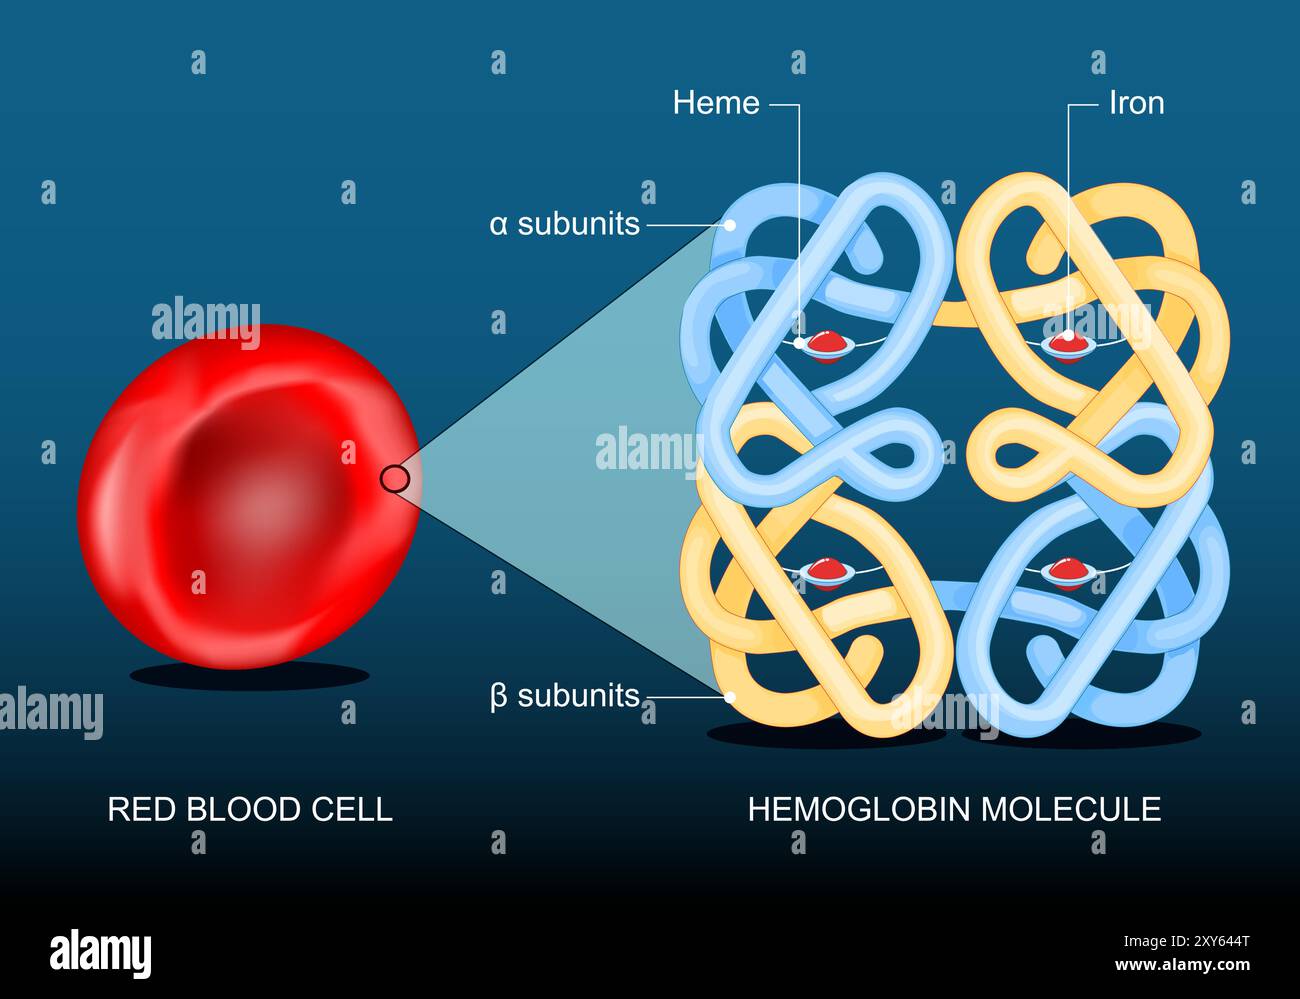
Heme is a complex organic molecule that serves as the prosthetic group for hemoglobin, the protein responsible for oxygen transport in red blood cells. Without heme, the blood's capacity to carry oxygen drops to near zero, and cellular respiration fails within minutes. The structure consists of a porphyrin ring with an iron atom at its center. That iron atom binds reversibly to oxygen molecules, allowing hemoglobin to pick up oxygen in the lungs and release it in tissues. Each hemoglobin tetramer contains four heme groups, meaning one red blood cell can theoretically carry nearly a billion oxygen molecules during its 120-day lifespan.
Unlocking The Secrets Of Hemo The Vital Component Of Human Life
The word "hemo" in everyday usage usually refers to hemoglobin or the blood system broadly, but the actual heme molecule is what makes oxygen transport possible. Iron deficiency anemia, the most common nutritional disorder worldwide, directly results from inadequate heme synthesis. The body requires sufficient iron, vitamin B6, and several other cofactors to produce functional heme groups in the bone marrow. I spent several years working in a clinical laboratory where we processed hemoglobin electrophoresis samples. One particular case involved a patient with unexpectedly low oxygen saturation despite normal lung function. The issue turned out to be a hemoglobin variant with altered heme binding affinity. We confirmed it through high-performance liquid chromatography and genetic testing for globin chain mutations.
How Heme Synthesis Actually Works in Practice
The biochemical pathway begins in the mitochondria with the condensation of glycine and succinyl-CoA to form delta-aminolevulinic acid. This reaction is catalyzed by ALA synthase, the rate-limiting enzyme that requires vitamin B6 as a cofactor. The pathway proceeds through eight enzymatic steps, ultimately producing protoporphyrin IX, which combines with ferrous iron to form heme. The regulation involves feedback inhibition at multiple points. When cellular heme levels are sufficient, the enzyme ALA synthase gets downregulated. Iron availability directly controls heme production through the iron-responsive element binding proteins. In iron deficiency, heme synthesis slows dramatically, leading to microcytic anemia where red blood cells become smaller and less efficient at oxygen transport. This process usually takes about 45 minutes to complete in isolated mitochondrial preparations, though in vivo turnover is continuous. The half-life of heme in hemoglobin matches the red blood cell lifespan, approximately 120 days under normal conditions. After degradation, the iron gets recycled through the reticuloendothelial system, primarily in the spleen and liver.
Get the Full Details
Common Pitfalls and Counter-Intuitive Insights
Beginners often assume that more dietary iron automatically increases heme production. This is incorrect beyond a certain threshold. The intestinal absorption of iron is tightly regulated through hepcidin, a peptide hormone produced by the liver. In iron overload conditions like hemochromatosis, heme synthesis continues unchecked, leading to tissue damage from iron deposition in the heart, liver, and pancreas. Another misconception involves the relationship between hemoglobin concentration and oxygen carrying capacity. Patients with polycythemia vera may have extremely high hemoglobin levels but paradoxically reduced oxygen delivery due to hyperviscosity slowing blood flow through capillaries. The actual determinant of oxygen transport is not just hemoglobin quantity but also heme group functionality and red blood cell rheology. Sickle cell disease illustrates the importance of heme environment. The point mutation in the beta-globin chain causes hemoglobin polymerization under low oxygen conditions. This transforms red blood cells from flexible discs to rigid sickle shapes, leading to vaso-occlusive crises. The heme group itself remains functional, but the altered protein structure creates severe clinical complications.
Diagnostic Approaches and Clinical Applications
Standard hematology practice involves measuring hemoglobin concentration, hematocrit, and red blood cell indices. Complete blood count with peripheral smear examination provides initial information about heme-related disorders. Iron studies including serum ferritin, transferrin saturation, and total iron binding capacity help distinguish between different types of anemia. Hemoglobin electrophoresis separates different hemoglobin variants based on their electrical charge. This technique identifies conditions like sickle cell trait, thalassemia, and other globin chain abnormalities. High-performance liquid chromatography has largely replaced gel electrophoresis in modern laboratories for hemoglobin A2 quantification and fetal hemoglobin measurement. Coenzyme Q10 supplementation has no direct effect on heme synthesis, though some alternative medicine sources claim otherwise. The actual heme biosynthesis pathway requires specific precursors that cannot be obtained through general nutritional supplements alone. Medical intervention typically addresses the underlying cause, whether iron deficiency, lead poisoning inhibiting ALA dehydratase, or genetic disorders affecting porphyrin metabolism.
Limitations and Scenarios Where Standard Approaches Fail
Acute blood loss reduces hemoglobin concentration rapidly, but heme synthesis cannot compensate quickly enough to restore oxygen carrying capacity. The bone marrow responds within days to weeks, depending on iron availability and erythropoietin stimulation. In chronic kidney disease, reduced erythropoietin production leads to anemia that responds poorly to iron supplementation alone. Certain medications inhibit heme synthesis through direct enzyme inhibition. Lead poisoning blocks both ALA dehydratase and ferrochelatase, the final enzyme that inserts iron into protoporphyrin. This creates accumulation of free erythrocyte protoporphyrin, which can be measured as an indicator of chronic lead exposure. Porphyrias represent a group of disorders where specific enzymes in the heme pathway are deficient. Acute intermittent porphyria causes neurological symptoms due to accumulation of porphyrin precursors. The heme group itself remains functional in red blood cells, but altered metabolites create severe clinical complications requiring specific medical management.

Advanced Nuances for Clinical Practice
The relationship between hemoglobin A1c and average blood glucose reflects non-enzymatic glycation of hemoglobin. This diagnostic marker has revolutionized diabetes management, though heme group functionality remains unchanged. Patients with hemoglobin variants may show falsely elevated or depressed HbA1c values depending on red blood cell turnover rates. Carbon monoxide poisoning demonstrates the importance of heme environment in oxygen transport. The affinity of heme for carbon monoxide exceeds oxygen by approximately 200-fold, creating carboxyhemoglobin that cannot carry oxygen. This transforms blood from oxygen transport medium to toxic carrier, requiring immediate hyperbaric oxygen therapy in severe cases. Methemoglobinemia illustrates altered heme functionality when iron oxidizes from ferrous to ferric state. The heme group cannot bind oxygen in this configuration, creating functional anemia despite normal hemoglobin concentration. NADH-cytochrome b5 reductase deficiency prevents methemoglobin reduction, leading to cyanosis requiring specific medical management.
The clinical significance of heme extends beyond oxygen transport to enzyme function in cytochrome P450 systems. Drug metabolism depends on heme-containing enzymes in the liver, though red blood cell heme remains separate from hepatic cytochrome pools. Genetic polymorphisms in CYP450 enzymes affect drug clearance rates significantly.