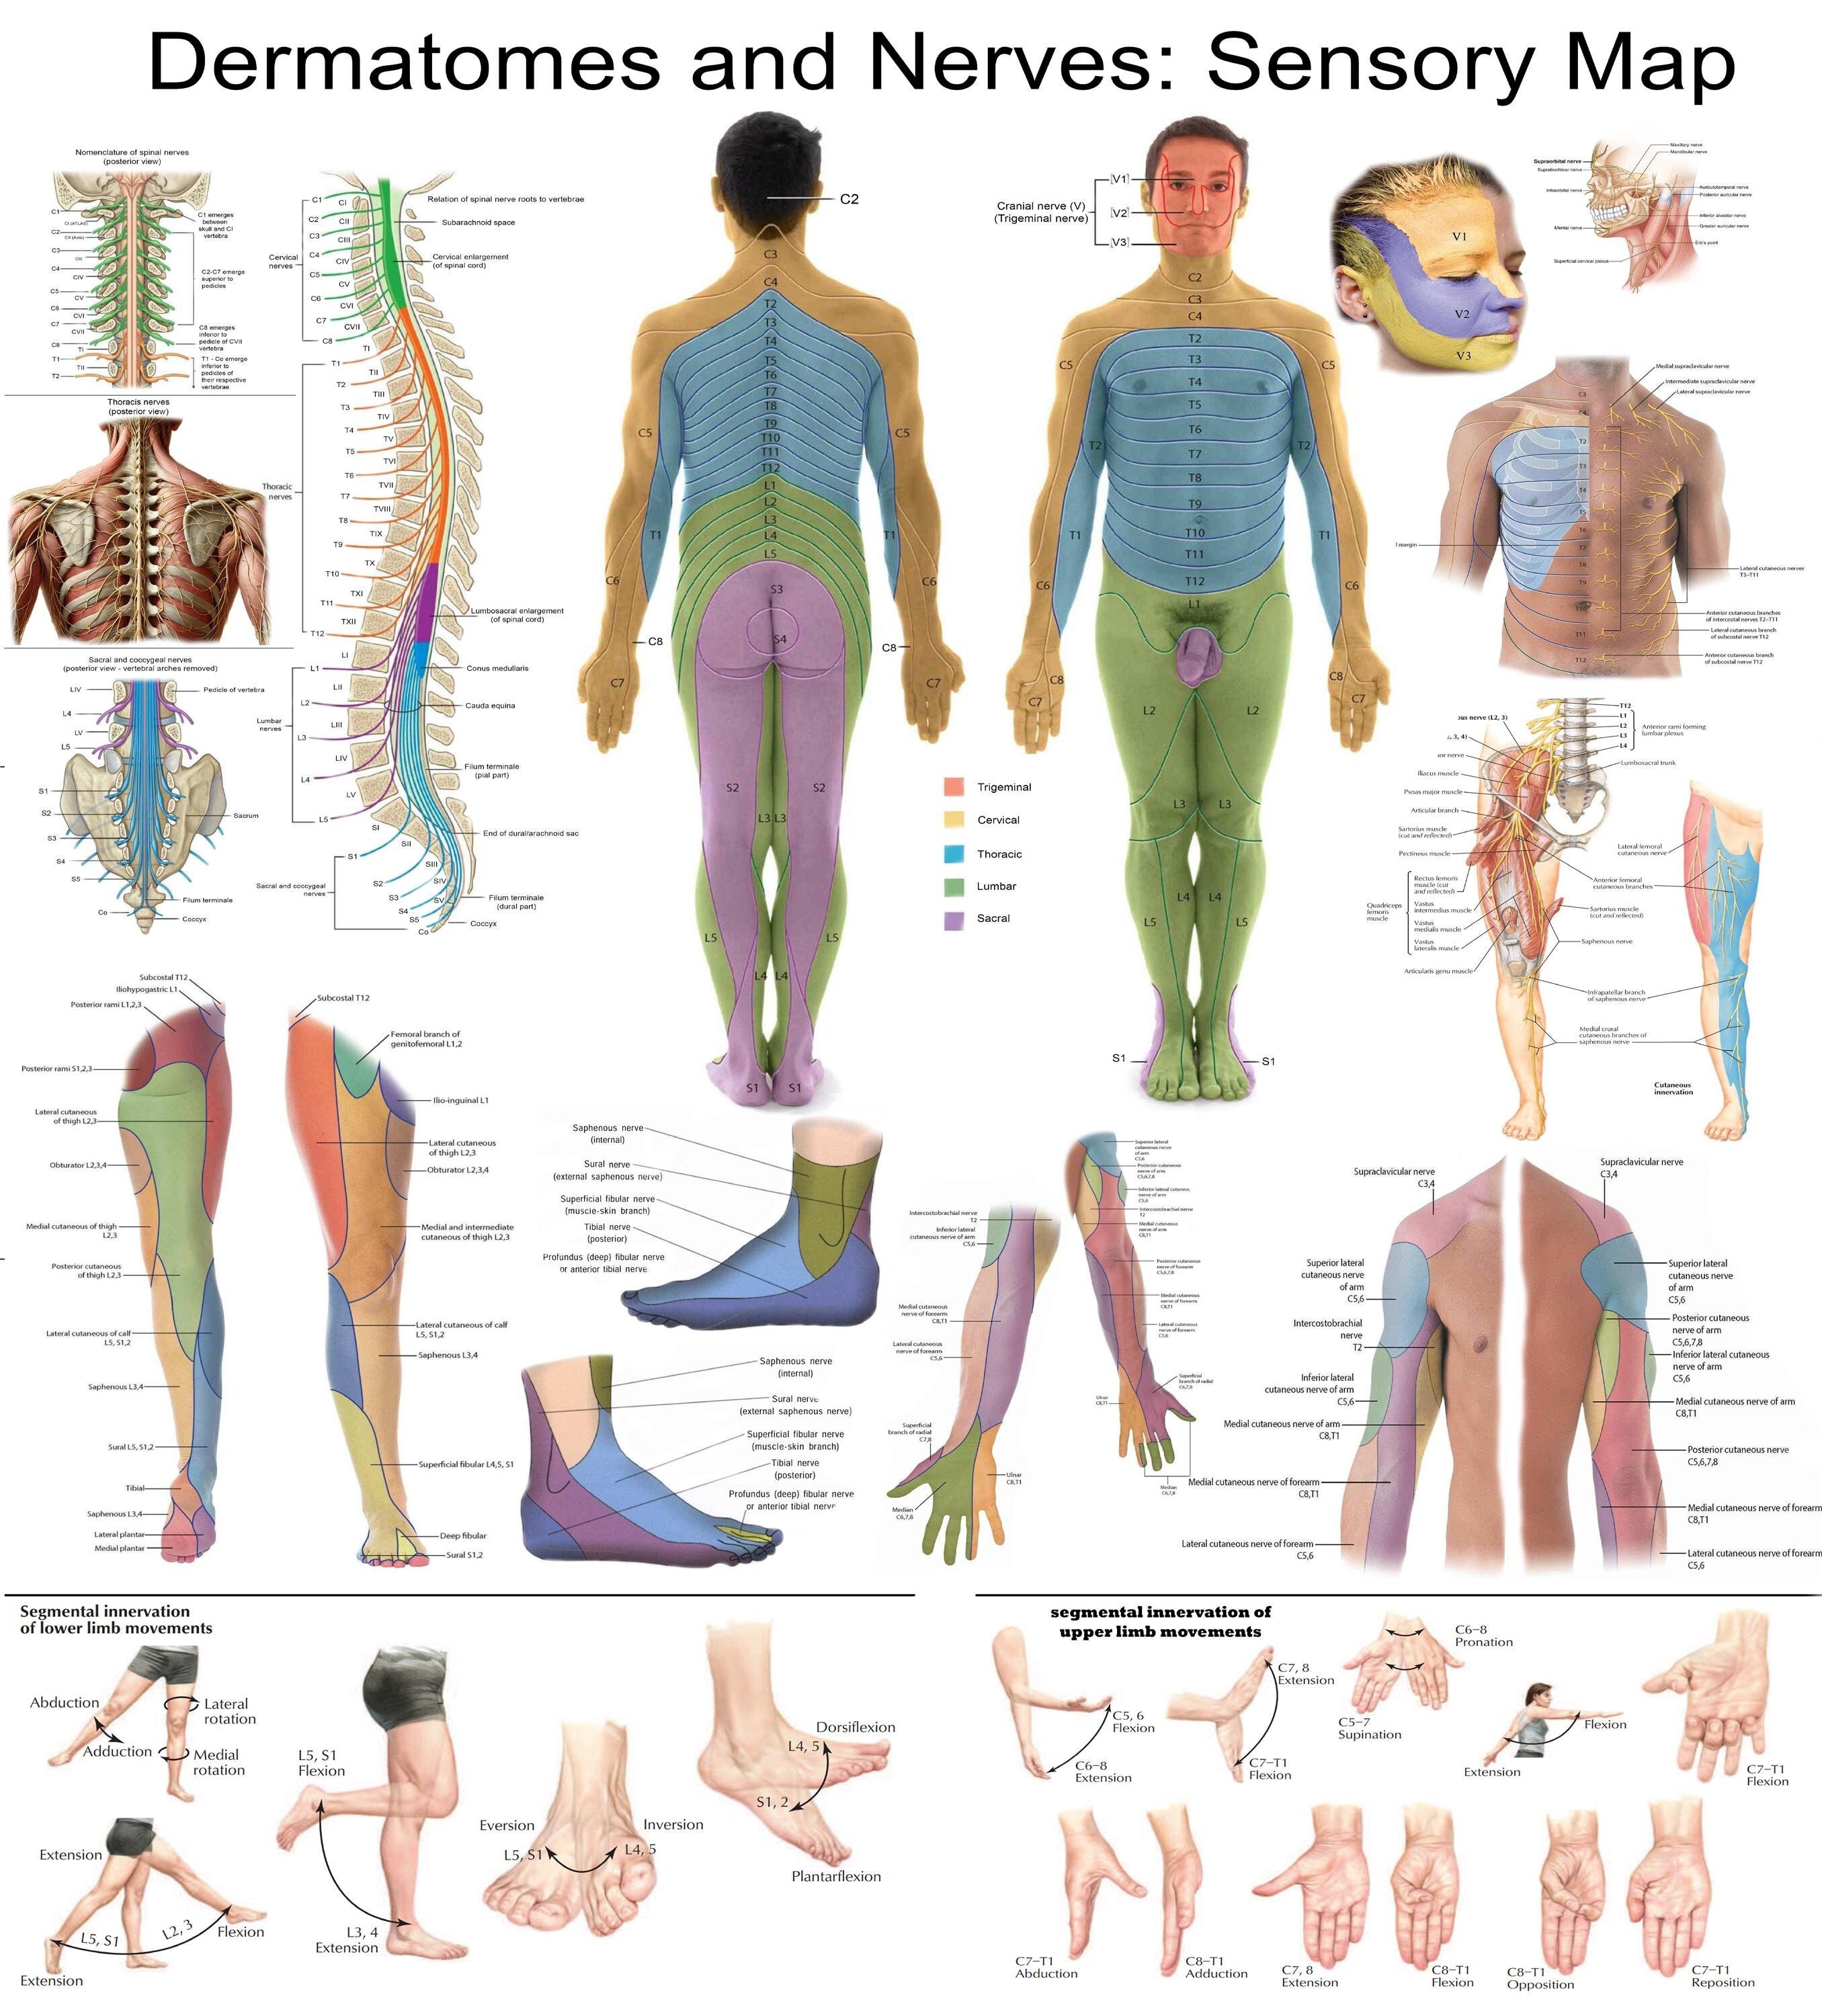
Reading Leg Sensation Through Dermatomes
If you spend enough time mapping neurological exams, you start noticing how patients describe sensory changes in ways that don't always line up with textbook diagrams. The standard charts show clean borders between L4, L5, and S1. Real people don't follow those lines. That's where the actual work begins. I've found the most practical approach is to combine dermatomal maps with myotome testing and then verify with a pinprick and light touch exam done systematically from proximal to distal. When I run this on someone with lower back complaints, I start at the anterior knee for L3 and L4, move down through the medial malleolus, test the dorsum of the foot for L5, and finish at the lateral foot and sole for S1. That sequence catches most radiculopathies in about eight minutes if the patient cooperates.
Unlocking The Secrets Of Dermatomes And Spinal Nerves Understanding Leg Sensation
Here's something most students miss: the overlap between adjacent dermatomes is massive. Up to sixty percent of the time, damaging one nerve root won't cause complete numbness because neighboring roots pick up the slack. What you actually look for is a relative reduction in sensation, not total anesthesia. I learned that the hard way during residency when I confidently told an attending that a patient's L5 root was intact because the dorsum of the foot felt normal. The attending handed me a tuning fork and asked me to recheck with vibration sense. Reduced at L5. The pinprick had been misleading because of the overlap. Another counter-intuitive detail that trips people up is that the dermatome map changes slightly depending on which part of the leg you're testing. The L5 dermatome covers the big toe and the medial dorsum when assessed on the foot, but on the anterior thigh it sits more laterally. Maps drawn on flat paper don't account for the cylinder shape of a limb. I keep a reference chart that shows the leg as if it's been unrolled, which makes the boundaries clearer than the standard posterior-anterior diagrams you find in anatomy textbooks. The S1 distribution is usually straightforward. Lateral foot, sole, and the fifth toe. But here's where it gets messy: S1 and S2 overlap significantly at the perineum and posterior calf. If a patient reports numbness on the back of the lower leg, you can't automatically assume S1. You need to check the plantar flexion strength and the Achilles reflex to distinguish S1 radiculopathy from a superficial peroneal nerve issue or even a tibial nerve entrapment. I had a patient last year with isolated posterior calf paresthesia who tested clean on every dermatomal exam. The real problem was a Baker's cyst compressing the tibial nerve behind the knee. Dermatomal testing alone would have sent that case down the wrong path.
For clinical work, the most reliable method I use is the semi-quantitative approach. Instead of just noting present or absent, I rate sensation on a scale from zero to two for each region: zero is no response, one is reduced but present, and two is normal. This catches early or partial nerve root irritation that a binary test misses. It takes about thirty seconds longer per limb and it matters more than you'd think. There are real limitations to this whole framework. Dermatomal mapping is surprisingly poor at localizing the exact level of a disc herniation. Studies show clinicians can identify the affected root from dermatome exams alone maybe fifty-five to sixty percent of the time. MRI findings and clinical correlation frequently disagree. A patient with a clear L5-S1 disc bulge on imaging might present with predominantly S1 symptoms or nothing notable at all. Don't let the dermatome chart override what the history and reflexes are telling you. If you're trying to internalize the leg dermatomes, I recommend drawing them yourself on a life-size leg outline rather than memorizing from a small textbook image. The act of drawing forces you to confront the overlap zones and the transitions between roots. After I did that a few times, the patterns stuck. Flashcards don't work well for spatial information like this. Your hand needs to remember what your eyes need to find on a patient.
Get the Full Details

The L4 root deserves special attention because it sits right between two major nerve structures. The saphenous nerve, which is purely sensory, shares territory with L4 on the medial lower leg. A saphenous nerve injury from surgery or trauma can mimic an L4 radiculopathy. The differentiator is usually the knee jerk reflex, which L4 influences but the saphenous nerve doesn't touch. Check the reflex. It saves you from mislabeling a peripheral nerve injury as a root problem.