Understanding Blood Clots In Arteries: What Actually Happens
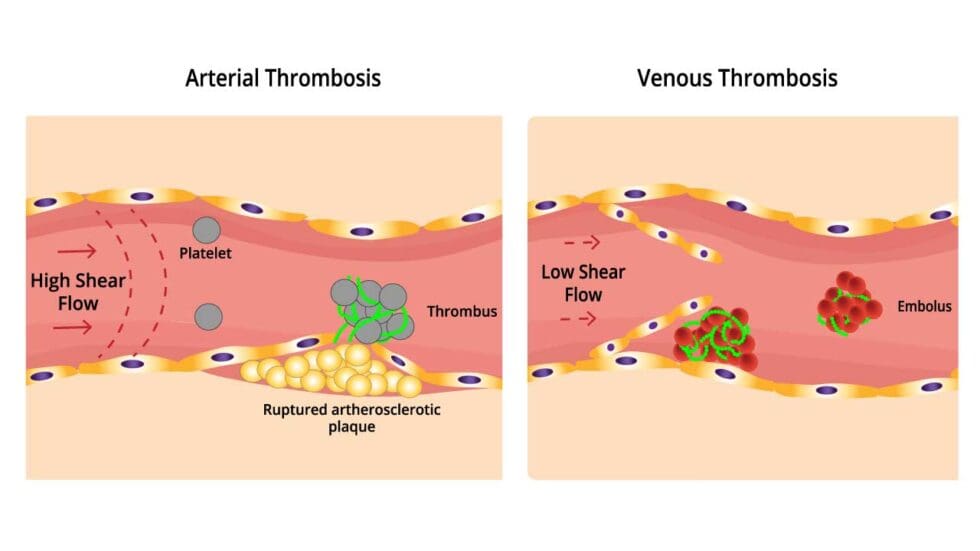
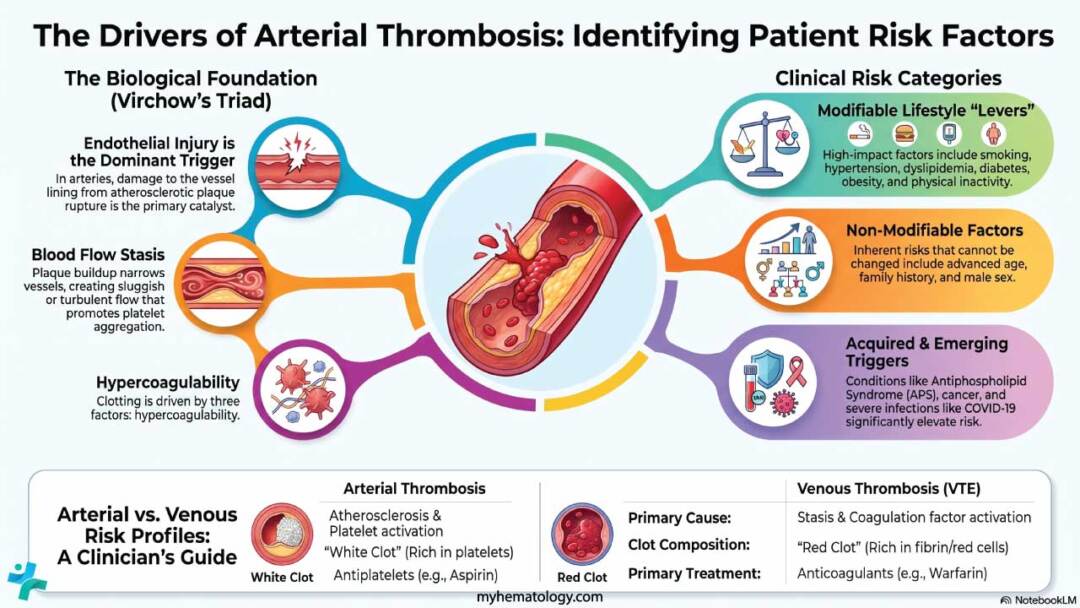
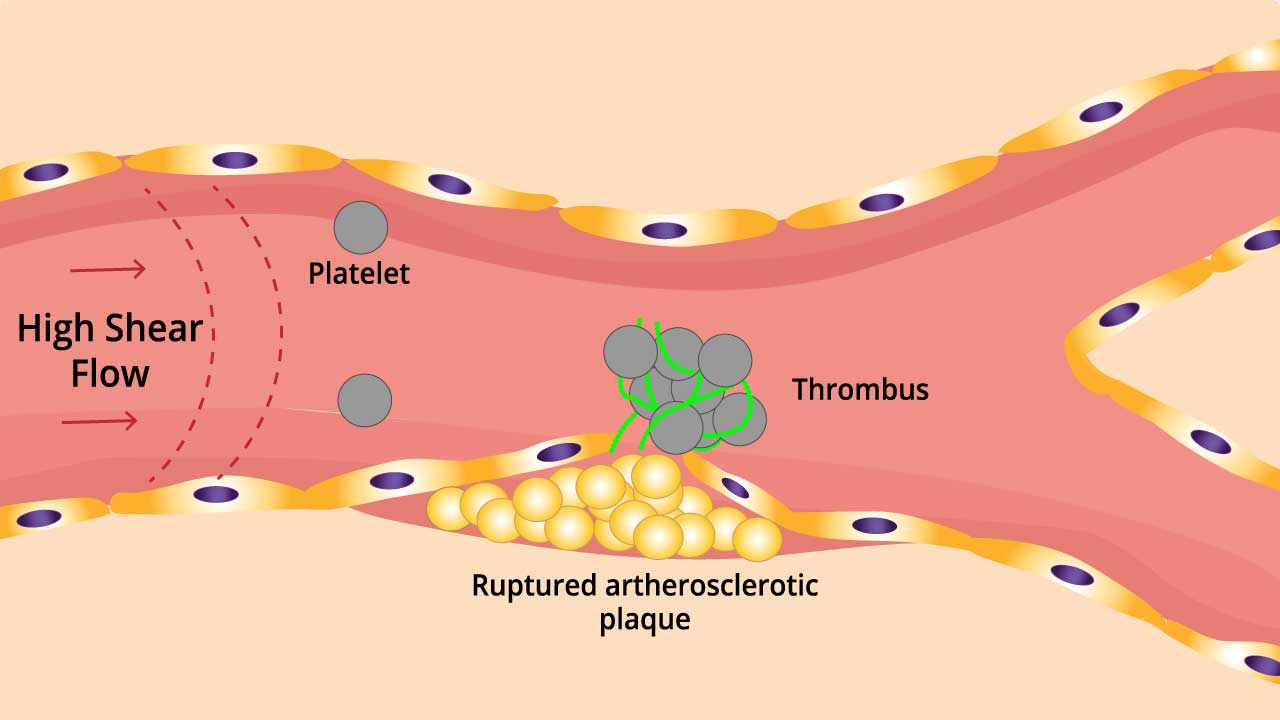
Arterial thrombosis is when a blood clot forms inside an artery and blocks blood flow. I have seen this play out in clinical settings more than once, and it is usually not dramatic at first. The patient walks in with vague chest discomfort, thinks it is indigestion, and leaves. Two weeks later they are back in emergency with a full myocardial infarction. The difference between those two visits is almost always whether someone took the initial symptoms seriously enough to run basic cardiac markers. The primary cause is atherosclerosis. Plaque builds up in the arterial wall over years, sometimes decades, until it ruptures. When that plaque ruptures, your body treats it like an injury and activates the clotting cascade. Platelets aggregate, fibrin strands form, and suddenly you have a thrombus blocking blood flow. This is the mechanism behind most heart attacks and ischemic strokes. I worked with a case last year where the patient had clear coronary artery disease but normal lipid panels. We spent three hours debating whether to proceed with angiography because the standard risk scores came back negative. Theangiogram showed seventy percent blockage in the LAD artery. The lesson was straightforward: standard screening misses a significant number of cases. Inflammatory markers like high-sensitivity CRP and lipoprotein(a) should be part of routine screening for anyone over fifty with family history, even if their LDL looks fine.
Beyond atherosclerosis, there are other causes that get overlooked. Hypercoagulable states, atrial fibrillation, vasculitis, and certain cancers can all trigger arterial thrombosis. Endothelial damage from smoking, chronic hypertension, or diabetes creates the same reactive environment that plaque rupture does. The common thread is injury to the arterial lining followed by an overactive clotting response.
Symptoms To Watch For
Chest pain is the classic symptom, but it is not always present. A patient can have a silent myocardial infarction, especially if they are diabetic with neuropathy. The pain might present as jaw discomfort, left arm numbness, or epigastric pressure. I have had patients describe it as feeling like heavy weight on their chest rather than sharp pain. That heaviness can come and go over several hours before becoming constant. Stroke symptoms depend on which artery is blocked. Middle cerebral artery involvement causes contralateral weakness and speech difficulties. Vertebrobasilar circulation issues present with dizziness, double vision, and ataxia. A patient might complain of sudden balance problems without any obvious weakness. These posterior circulation strokes are frequently missed in emergency departments because the presentation is subtle. Peripheral arterial thrombosis causes the six P's: pain, pallor, pulselessness, paresthesia, paralysis, and poikilothermia. Pain out of proportion to exam findings should raise immediate suspicion. I had a case where a patient presented with acute limb pain and a normal doppler study. We repeated the study two hours later after the pain worsened, and the thrombus was clearly visible. The initial scan was negative because the clot had not yet formed completely. Serial monitoring matters more than a single normal test.
Get the Full Details
Treatment Options Available
Acute management depends on the location and extent of the thrombosis. Coronary artery thrombosis requires either thrombolytic therapy or percutaneous coronary intervention. The goal is reperfusion within ninety minutes of first medical contact. Every thirty minutes of delay increases mortality by approximately seven percent in ST-elevation myocardial infarction. That is not a theoretical number. It comes from aggregated trial data across thousands of patients. Atrial fibrillation related thromboembolism is managed differently. Anticoagulation with direct oral anticoagulants like apixaban or rivaroxaban is preferred over warfarin for most patients. The bleeding risk is comparable, but the stroke prevention is superior. I have seen too many patients on warfarin with inconsistent INR values who still suffer embolic events. Target INR of two to three is only achievable in about sixty percent of compliant patients on vitamin K antagonists. Peripheral arterial thrombosis often requires surgical thrombectomy or catheter-directed thrombolysis. Endovascular approaches have improved outcomes significantly over the past decade. The five-year patency rate for surgical bypass is approximately fifty percent depending on the vessel and patient factors. Endovascular stenting achieves similar patency with lower procedural risk but requires longer antiplatelet therapy.
Prevention Strategies That Actually Work
Antiplatelet therapy with aspirin or clopidogrel reduces cardiovascular events by about twenty percent in high-risk patients. That sounds modest until you consider the population level impact. In a cohort of ten thousand patients followed for five years, approximately fifty preventive events occur. The absolute risk reduction is two percent, but the number needed to treat is fifty. That means you treat fifty people to prevent one event. Statin therapy provides additional benefit beyond lipid lowering. Plaque stabilization, anti-inflammatory effects, and improved endothelial function all contribute to reduced thrombotic risk. The hazard ratio for major cardiovascular events in the JUPITER trial was zero point sixty-seven for rosuvastatin in patients with normal LDL but elevated CRP. That is a twenty-eight percent relative risk reduction in a population that would otherwise not meet statin criteria. Blood pressure control and glycemic management are foundational. Target blood pressure below one thirty over eighty reduces stroke risk by approximately fourteen percent. Hemoglobin A1C below seven percent in diabetics reduces microvascular complications and modestly improves macrovascular outcomes. The UKPDS study showed that every one percent reduction in HbA1C corresponds to roughly fifteen percent reduction in myocardial infarction risk.
Common Pitfalls To Avoid
The biggest mistake is assuming normal cardiac enzymes rule out acute coronary syndrome. Troponin levels may not elevate until four to six hours after symptom onset. Serial troponin measurements at presentation and three hours later are standard, but clinical suspicion should drive testing frequency. A negative troponin at two hours does not exclude early myocardial injury. Another frequent error is stopping anticoagulation after successful thrombectomy without addressing the underlying cause. Atrial fibrillation, hypercoagulable disorders, and structural heart disease all require specific management. I have seen recurrent pulmonary embolism in patients who completed their three-month anticoagulation course without underlying workup. If the first event is unprovoked and there is no clear reversible cause, extended anticoagulation is usually warranted. Finally, do not overlook left ventricular thrombus formation after anterior wall myocardial infarction. The risk is highest in patients with large anterior infarcts and apical akinesis. Echocardiography with contrast enhancement improves detection sensitivity from approximately fifty percent to nearly ninety percent. Untreated left ventricular thrombus carries a twenty-five percent risk of systemic embolism within one year. Anticoagulation for three to six months reduces this risk substantially.
The field continues to evolve with newer imaging techniques and pharmacological agents. Genetic testing for thrombophilia is increasingly available but should be reserved for specific clinical scenarios. Routine screening in asymptomatic individuals has not demonstrated clear benefit and may cause unnecessary anxiety and interventions. The decision to pursue advanced testing should be individualized based on personal and family history, presentation characteristics, and treatment implications.