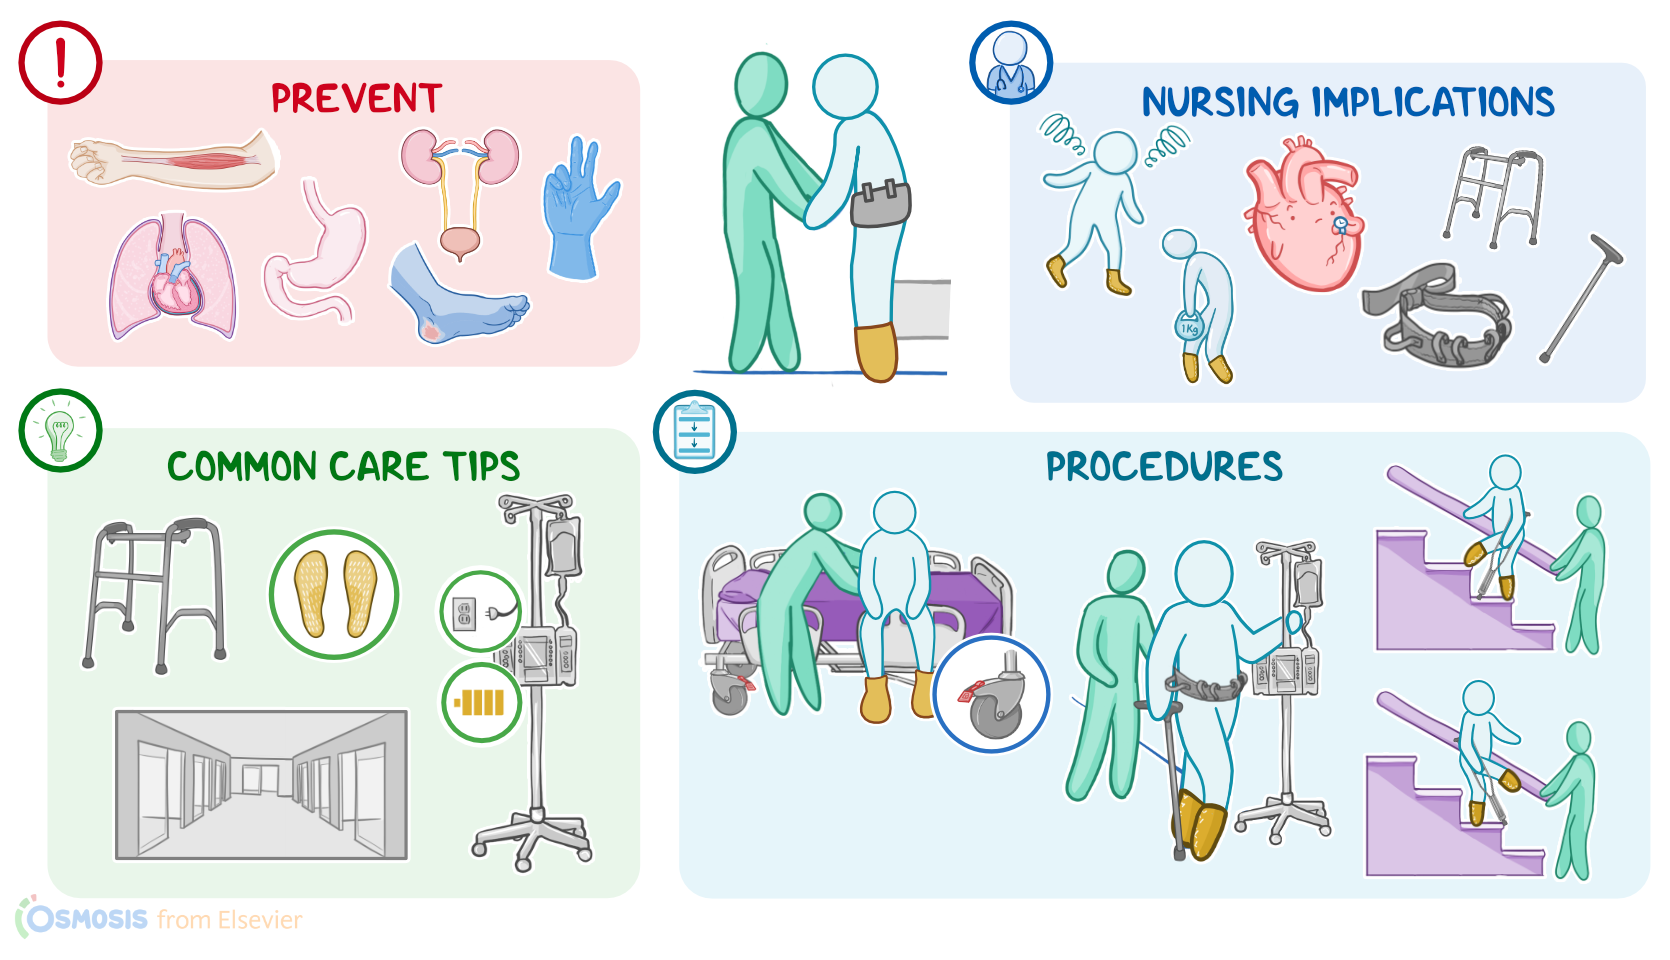
What Ambulation Actually Is and Why You Should Care
Ambulation is the medical and clinical term for walking or mobility. It sounds fancy, but it's just a word for moving from one place to another on your feet. The reason this topic keeps coming up is that in healthcare settings, how well a patient ambulates predicts almost everything else about their recovery trajectory. I've seen entire treatment plans pivot based solely on whether someone could stand and take a few steps without assistance. The concept encompasses far more than simple walking speed. It involves balance, endurance, coordination, weight-bearing capacity, and the cognitive ability to navigate obstacles. When clinicians talk about ambulation assessments, they're measuring a composite of physical and mental functions working together.
Unlocking The Secrets Of Ambulation What Does It Mean And Why It Matters
To truly understand ambulation assessment, you need to know that most beginners focus exclusively on distance walked. That's missing the bigger picture. The real measure lies in how the person moves, not just how far they go. A patient might shamble twenty meters without stopping but with dangerous instability. Another might walk ten meters carefully with proper gait mechanics and better overall prognosis. Distance alone doesn't tell you which patient will recover faster or need more support. The tools most people reach for first are the six-minute walk test and the Timed Up and Go test. These are reliable but limited. They give you numbers, and numbers feel objective, but they miss subtle factors that matter in real-world recovery. I learned this the hard way about three years ago when a patient scored well on both tests but couldn't safely navigate a crowded pharmacy aisle. She tripped over a floor mat that wasn't there during her assessment. The tests showed independent ambulation. Reality told a different story. After that incident, I started incorporating environmental simulation into my ambulation evaluations. Rather than testing only in clear hallways, I introduced controlled obstacles: a slight elevation change, a narrow passage, turning while walking, and carrying an object. This added about ten minutes to each assessment but caught issues that standard tests completely missed. One specific adjustment that made the biggest difference was having patients navigate while briefly distracted by a conversation. It sounds minor, but it revealed which patients were relying entirely on conscious focus to walk and which had developed genuine automaticity in their gait.
Another counter-intuitive point that most guides skip: ambulation ability doesn't always correlate with leg strength. I've worked with patients who had strong quadriceps but poor proprioception, meaning they couldn't sense where their feet were in space without looking. Their walking pattern was awkward and unsafe despite decent muscle power. The workaround here involves testing balance on different surfaces, not just flat ground. A firm mattress or foam pad during assessment exposes proprioceptive deficits that vanish on hospital flooring. If you're looking to improve ambulation either for yourself or a patient, the most effective approach combines progressive weight-bearing exercise with balance training. Starting with parallel bars or a walker and gradually reducing support as confidence and strength build is the standard pathway. The timeline varies enormously. Some patients see measurable improvement in two weeks. Others need six to eight weeks before noticeable changes occur. Age, underlying condition, and consistency of practice all factor in heavily. There are bottlenecks you should know about. Compression garments that are too tight around the thighs can restrict movement and make ambulation exercises feel harder than they actually are. This happens more often than you'd think, especially post-surgery when patients wear compression stockings for circulation. Loosening or adjusting these garments during walking exercises often immediately improves gait quality. Also, footwear matters enormously. Hospital socks are notorious for causing slips on hardwood or linoleum floors. Simple non-slip shoes or even sturdy sneakers make a measurable difference in stability and confidence during ambulation practice.
Get the Full Details

Some methods simply don't work well. Treadmill-based ambulation training without harness support has a high fall risk for elderly patients or those with recent joint surgery. The safety line approach works better, though it can create psychological dependency where patients refuse to walk without it. Gradual tapering of the harness is necessary to build genuine independent mobility. For caregivers and family members wanting to support ambulation improvement at home, the most practical tool is a simple stopwatch and a marked distance in the house. Measuring regular walks over time provides data without needing clinical equipment. Recording the time, noting any fatigue or pain, and tracking progress week to week gives you objective feedback. This method alone costs nothing and reveals trends that intuition misses. The bottom line is that ambulation assessment and improvement requires looking beyond surface-level metrics. Speed and distance are useful, but they're incomplete. Real understanding comes from observing how a person moves through actual environments with real challenges. That approach takes more time upfront but prevents setbacks later and leads to safer, more sustainable mobility outcomes.