Unlocking The Secret Of The Bifid Spinous Process How This Vertebral Structure Supports The Spines Vital Function
Samantha
2026-05-06
Palpating The Bifid Spinous Process: A Practical Guide
Most anatomy students learn that bifid spinous processes exist and move on. The problem is they never actually practice finding them. On a cadaver they feel obvious. On a living person they disappear under layers of trapezius and erector spinae. You are not going to feel much with your thumb pressed flat against someone's neck.
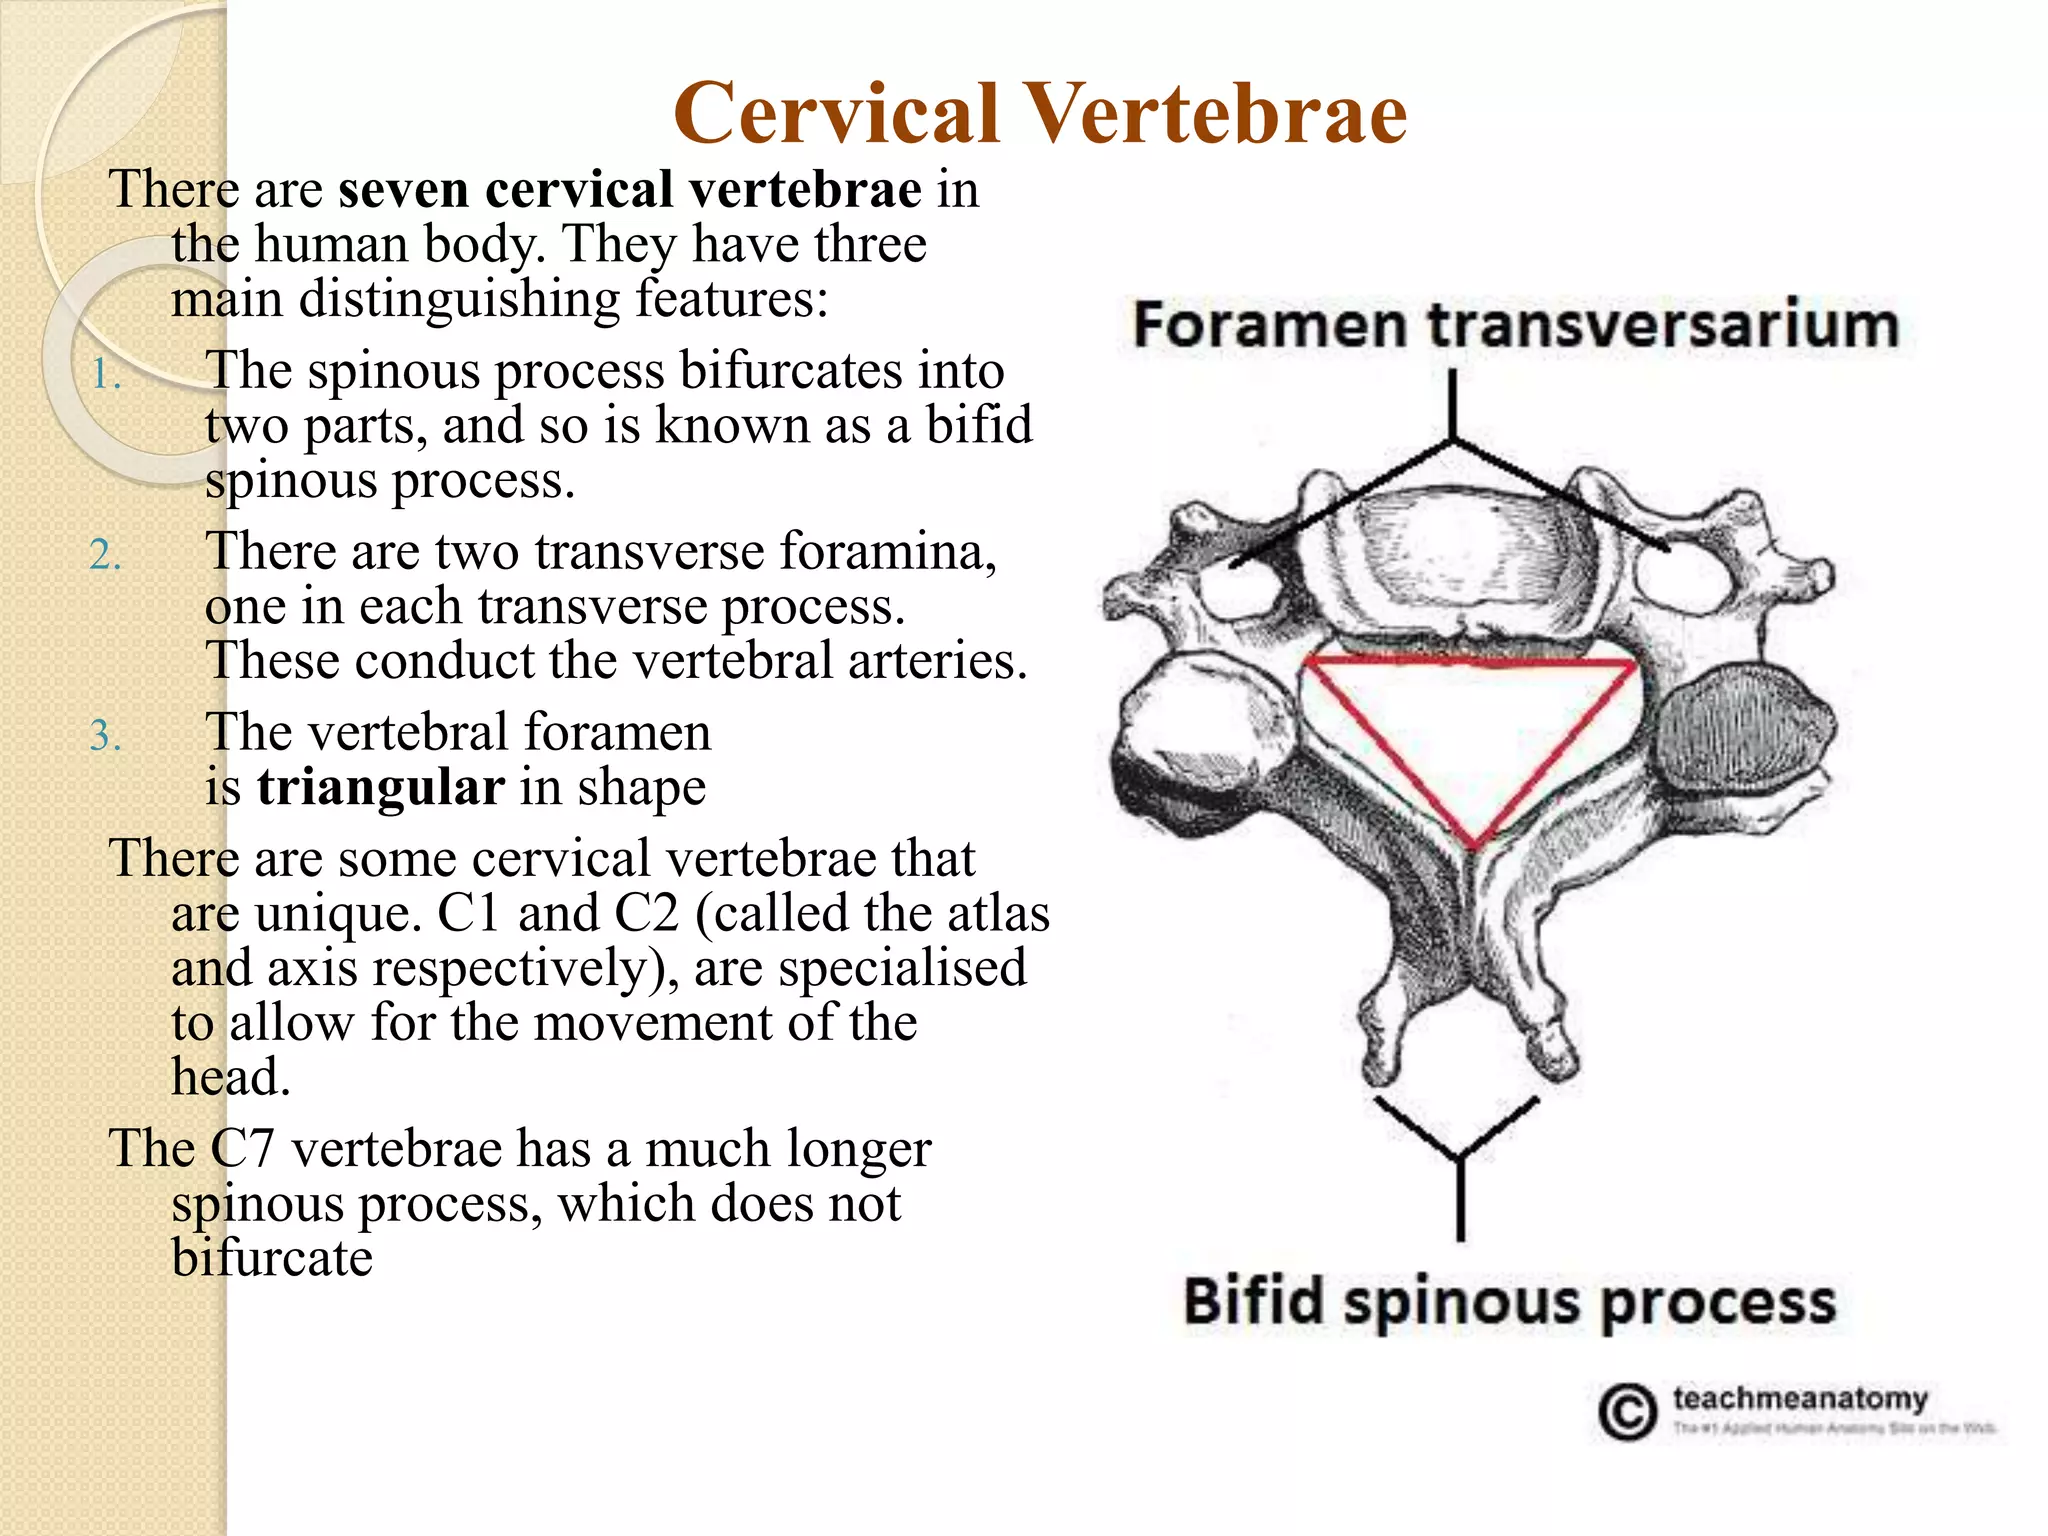
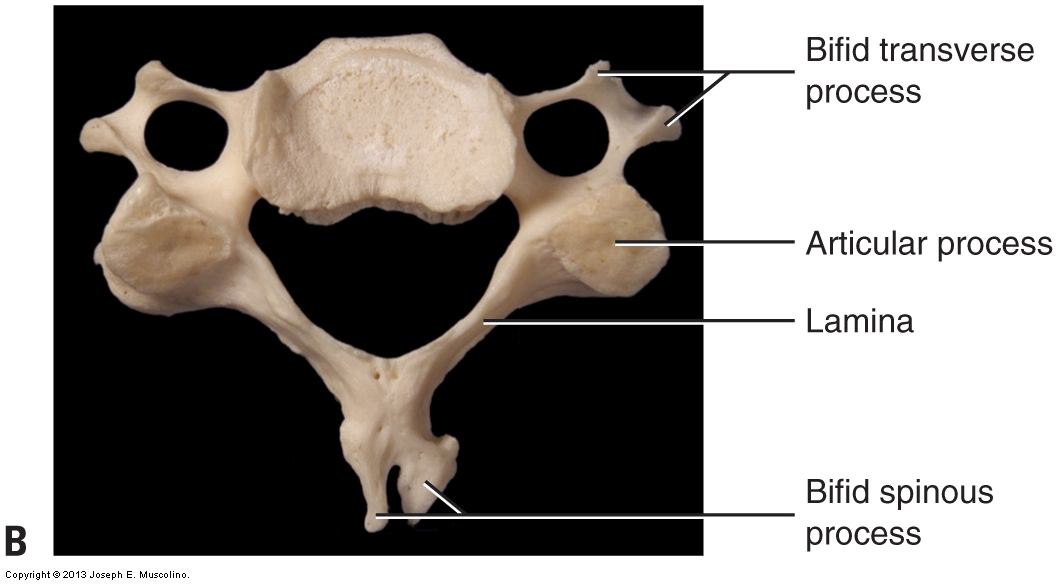
The bifid morphology means the tip splits into two small tubercles separated by a shallow notch. This creates a double bump you can roll your finger over instead of a single sharp point. That extra bulk is what makes them easier to distinguish when you know what to look for.
Unlocking The Secret Of The Bifid Spinous Process How This Vertebral Structure Supports The Spines Vital Function
Bifid spinous processes occur most consistently in the mid-cervical vertebrae, typically from C2 through C6. Some lower cervical vertebrae show partial bifidity, and you will occasionally find bifid processes in the upper thoracic region, usually T1 through T3. The splitting of the tip increases the surface area available for attachment of the nuchal ligament and several deep posterior neck muscles, including the semispinalis cervicis and the multifidus.
The structural consequence is worth understanding before you try to work clinically around these landmarks. A bifid process does not simply provide more room for soft tissue. The notch between the two terminal tubercles creates a mechanical groove that guides the direction of tensile forces running through the nuchal ligament. When the head flexes forward, the force vector runs longitudinally along the ligament toward those two terminal points. When the head extends, the force shifts and the bifid architecture distributes that load across a broader contact zone on the posterior arch. This reduces localized stress on any single insertion site compared to a non-bifid, single-point process of the same overall length.
The spine's vital function here is not abstract. It is about maintaining neutral alignment while allowing the cervical region its normal range of motion without placing excessive strain on the posterior ligamentous complex. The bifid design contributes to that load distribution. That is the mechanism most textbooks skip over.
How To Locate Them In Practice
Start at the external occipital protuberance and move your fingers downward along the midline. The first prominent process you encounter is C2, and it is usually bifid. The second major landmark is C7, the vertebra prominens. C7 is almost never bifid, so finding it gives you a fixed reference point. Count upward from C7 and you should land on the mid-cervical bifid processes.
The problem with counting is that people misidentify C7 as C6. The spinous process of C6 is often short and may be partially obscured by the scalenus anterior tendon. C7 has a large, non-bifid process that becomes very prominent when the neck is flexed. If you are unsure, have the person gently nod their head forward. C7 will stand out. The processes above it, especially C3 through C5, will feel softer and slightly wider at the tip with a palpable central groove.
I used to press too hard when trying to confirm bifidity. The deeper you press, the more you compress the underlying muscle and lose the distinct double-tubercle feeling entirely. Light pressure, about 2 to 3 kilograms of force, is sufficient. Use the pad of your index finger, not the tip, and roll horizontally across the expected level rather than pushing straight down. You should feel two small rounded edges with a subtle depression between them.
A specific edge case that wasted me considerable time involves patients with significant trapezius hypertrophy or chronic muscle guarding. In these cases the bifid notch becomes virtually unpalpable because the muscle fibers override the bony contour. The workaround I settled on is to position the patient prone with the head neutral, then ask them to perform gentle isometric neck extension against light resistance from your other hand while you maintain the light rolling contact over the expected level. The isometric contraction briefly tenses the underlying fascia and shifts the overlying trapezius fibers enough to reveal the bony landmark underneath. It is not perfect. Sometimes you simply cannot feel it, and you move to the next level.
Why This Matters Clinically
The bifid spinous process is a critical landmark for several procedures. Cervical epidural injections and facet joint blocks rely on accurate midline identification. A process that is mistakenly assumed to be C6 when it is actually C7 will shift your entire procedural plane upward by one level. That is an easy mistake to make and a dangerous one to miss.
Palpation of these landmarks is also essential for manual therapy assessment. The supraspinous and interspinous ligaments attach directly to these processes. Hypertonicity in the semispinalis and multifidus often produces tender nodules near the bifid tips rather than along the midline between them. Treating the space between two bifid processes without recognizing the actual anatomical attachment points means you are working on tissue that is not the primary source of the restriction.
Common Pitfalls
The first mistake is assuming all mid-cervical processes are equally bifid. C2 is reliably bifid. C6 shows partial bifidity in roughly 40 percent of the population and can appear nearly non-bifid in others. C7 is the standard reference point and is almost always non-bifid. If your assessment does not account for this variation, your level identification will drift.
The second mistake is conflating bifidity with pathology. A palpable notch is normal anatomy. A sudden loss of the normal bilateral symmetry at a single level, particularly when accompanied by focal tenderness, warrants imaging before any invasive procedure. Bifid processes can also fracture, though this is uncommon. I once encountered a patient with acute mid-cervical pain after a minor whiplash event. The bifid tip of C5 was tender and visibly swollen compared to the contralateral side. Imaging confirmed a non-displaced fracture through the bifid tip. Standard palpation alone would not have caught this.
Limitations Of Palpation
Palpating bifid spinous processes works reasonably well in lean individuals with average muscle mass. It becomes significantly less reliable in patients with higher body fat, large trapezius development, or significant postural kyphosis that changes the angulation of the cervical spine. In those cases, fluoroscopic guidance or ultrasound becomes necessary for any procedure requiring precise midline localization. No amount of practice will overcome thick soft tissue barriers.
Ultrasound visualization of the bifid tip is possible with a high-frequency linear probe placed in a transverse orientation over the mid-cervical region. The two echogenic tubercles create a characteristic bifid appearance that can be difficult to distinguish from surrounding soft tissue interfaces without practice. I found that scanning the contralateral side first and comparing the two sides simultaneously made recognition much more reliable than relying on a single-side view.
Functional Takeaway
The bifid spinous process is a straightforward anatomical adaptation that serves a specific mechanical purpose. It increases the attachment surface for posterior cervical stabilizers and distributes tensile load across two terminal points rather than concentrating it at a single insertion. Understanding this helps you interpret palpation findings accurately and avoid procedural errors rooted in misidentified levels. It also explains why certain palpation techniques fail in specific body types and why imaging guidance remains necessary in those situations.
Gallery Unlocking The Secret Of The Bifid Spinous Process How This Vertebral Structure Supports The Spines Vital Function
Lecture 2 - Spinal Structure & Function Flashcards | Quizlet
Surgery & anatomy of vertebral column and spinal nerves | PPTX
Introduction to (overview of) the cervical spine of the neck
Introduction to (overview of) the cervical spine of the neck
Joints of the Cervical Spine Flashcards | Quizlet