What MyChart Actually Is And What It Won't Do For You
MyChart is Epic's patient portal, the same platform running behind hundreds of hospital systems across the country. If you are tied to a MyChart-enabled provider, you already have access to lab results, prescription refill requests, appointment scheduling, and a message system that connects you directly to your care team. That part is straightforward. The part people never tell you about is how inconsistent the experience is from one health system to the next. I spent roughly six years working health IT integration before moving over to the provider side, and even now I deal with MyChart on a regular basis. The platform itself is solid, but the way each hospital configures it creates a lot of friction that most patients just absorb without understanding why. There are configuration choices made at the institutional level that have nothing to do with Epic's software and everything to do with whether your administrator thinks patients should see certain results immediately or after a provider review window.
Unlocking The Power Of Your Health A Comprehensive Guide To Utmb Mychart
UTMB MyChart is the University of Texas Medical Branch portal, and it follows the same Epic backbone as every other MyChart instance. The core functions are identical: view results, send messages, request refills, manage appointments, share data through MyChart Family Access. What differs is the UTMB-specific configuration. Some result categories here have longer default review hold periods than you might see at a private hospital system. Lab results that would post within twenty-four minutes at one facility can sit for up to seventy-two hours at UTMB depending on the test type and how the pathology department flags them. The first thing I learned the hard way was about the result release policy. Early on I was confused why a basic metabolic panel showed up in MyChart almost instantly while a comprehensive infectious disease panel took three days to appear. The answer is not a technical glitch. UTMB applies an institutional review window to certain result categories as a standard practice. This is not unique to UTMB. Many academic medical centers do the same thing because they want a clinician present to interpret complex or unexpected findings before the patient sees them raw.
Setting Up Your Account And Getting Past The First Friction
Account activation is where most people hit their first wall. You will receive an invitation code either printed on a visit summary sheet or sent to your registered email. The code expires. I do not know the exact expiration window because it varies by system generation date, but I have watched it be anywhere from fourteen to thirty days. Do not wait. When you register, you will be asked to verify your identity. This typically means providing your date of birth, phone number, and sometimes the last four digits of your Social Security number or a Medicare number. The verification step trips people up when the name on the account does not perfectly match the name on file at the hospital. If you go by a nickname or have a recent name change, call the health information management office before you waste twenty minutes getting rejected by the automated system. They can update the name match on the back end in about five minutes. There is also a mobile app and a web interface, and they are not always in sync. I discovered this when I requested a medication refill from my phone and then checked the web portal two days later to confirm it went through. The refill request appeared on the web version as pending but the app showed nothing. The data was there but the app cache had not pulled the updated status. Clearing the app cache and doing a hard refresh on the web both fixed it. It is a known synchronization delay that usually resolves within four to six hours but can drag to twenty-four if their background job queue is backed up.
Get the Full Details

Reading Results Without Getting Yourself Into Trouble
MyChart posts results in a structured format. Each lab value has a reference range and a flag indicating whether it falls outside that range. The flags are standard: H for high, L for low, and sometimes AA or N for abnormal. The problem is that patients routinely interpret any flagged result as a crisis, and then they flood the messaging system with panicked questions that get triaged to the bottom of the queue. Here is the counter-intuitive part that nobody explains well. A flagged value does not always mean something is wrong. Reference ranges are built on population statistics, usually the middle ninety-five percent of healthy people. That means roughly five percent of completely healthy individuals will naturally fall outside the reference range on any given test. A single slightly elevated value with no clinical context attached is almost never actionable on its own. Repeat testing and trend analysis matter far more than any single number. I had a patient once who saw a borderline high potassium result in MyChart at ten at night and convinced themselves they were having a cardiac event. They came to the emergency department. Their actual potassium was normal on repeat drawing and the initial result was a hemolyzed sample, which is a pre-analytical artifact where red blood cells rupture during the draw and release intracellular potassium into the serum. The lab flags this, but the flag is buried in the details section that most people never scroll past. I wish more portals highlighted hemolysis warnings right on the main results view instead of hiding them three clicks deep.
Message System Reality Check
The patient messaging feature is the most misunderstood tool in MyChart. People assume it works like email. It does not. It works like a secure ticketing system routed through a clinical workflow engine. Messages go to a nursing or administrative inbox first, not directly to the physician. Triage happens based on keywords, urgency indicators, and the message category you select. If you write a message saying "I feel terrible and my chest hurts" without selecting the urgent triage category, it will sit in the general queue. I have watched routine refill requests get answered faster than urgent clinical complaints simply because the refill was routed correctly through the pharmacy coordination path while the symptom message got stuck in an inbox that processes fifty messages before the on-call provider even clocks in. The workaround is straightforward. Use the symptom checker tool if your system has one, and when messaging directly, put the most clinically relevant information in the first line. Subject lines like "urgent concern" mean nothing to the routing algorithm. "Chest pain onset 3 hours ago" triggers different triage logic.
Prescription Refills And The Hidden Bottleneck
Refill requests appear to go through instantly but they do not. Behind the scenes, the request travels to the pharmacy, the pharmacy verifies insurance and formulary status, then sends it to the prescriber's office for electronic authorization. The prescriber or their PA or NP reviews it, and then it gets signed. From my experience, a straightforward maintenance medication refill through MyChart takes anywhere from four business hours to three business days. Non-controlled substances move faster. Controlled substances require additional verification steps that add one to two days minimum and some providers will not authorize them through the portal at all, requiring a phone call or visit instead. The biggest frustration I see is when patients request refills through MyChart while also calling the office directly. This creates duplicate requests and often results in confusion about which one gets processed. Pick one channel and stick with it. If you need something sooner, call. MyChart is not built for speed. It is built for documentation and audit trails.

Sharing Access And Family Management
MyChart Family Access lets you manage health information for dependents. This is useful but it comes with its own complications. Children under thirteen typically need a parent or guardian to manage their portal access. Once they turn thirteen, some systems automatically transition ownership to the patient and the parent loses access unless the teen agrees to continue sharing. This transition happened to me when my daughter turned thirteen and I suddenly could not see her immunization records anymore. I had to have her log in and grant me permission again, which sounds simple but requires her to have active device access and know her credentials. Adult children managing elderly parent accounts is another common scenario. If you are helping an aging parent navigate MyChart, make sure you understand the authentication requirements. Many systems now require multi-factor authentication for any account change, which means you cannot simply update their phone number or email from your own device without going through their verified contact method first. This is a security feature but it creates a catch twenty-two when the parent's phone number is outdated and they cannot receive the verification code.
What MyChart Cannot Do And When You Should Look Elsewhere
MyChart will not replace a phone call when you need something immediate. It will not provide same-day appointment availability in most cases because scheduling through the portal usually routes to a staff member who has to confirm with the provider's actual schedule. It will not resolve billing disputes efficiently because the billing department often operates on a completely different workflow and their response times through MyChart are notoriously slow compared to calling the patient finance line directly. For urgent clinical questions that arise outside business hours, MyChart is essentially useless. Messages sent overnight sit in the queue until the next business day. If you are dealing with a time-sensitive issue, call. The portal is designed for asynchronous communication, which means convenience traded against speed. Most people do not realize they made that trade until they need something quickly. The portal also does not integrate across health systems. If you see a specialist at a different hospital network, their results will not appear in your UTMB MyChart. You will need separate accounts for each system, and some regional networks have begun sharing data through health information exchanges but adoption is inconsistent and you should not count on cross-system visibility without confirming it explicitly with both providers.
Practical Workflow Tips That Actually Matter
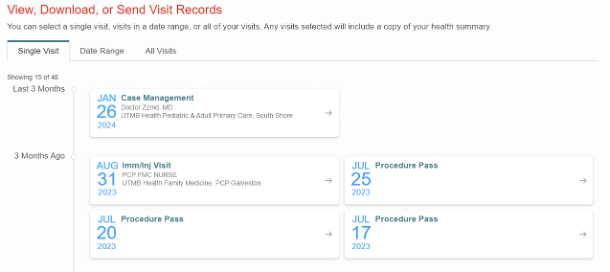
Download your results when they arrive instead of just viewing them in the browser. MyChart allows PDF export for most documents, and having a local copy is valuable when you need to share information with another provider or when the portal temporarily goes down for maintenance, which happens more often than patients realize. Academic medical centers run maintenance windows regularly and MyChart can be unavailable for two to four hours on weekend mornings without much advance notice. Keep a running list of your medications and allergies outside the portal, preferably in a simple document on your phone. MyChart tracks this information but the display is inconsistent across different encounter dates, and old medications sometimes remain listed as active while new ones get added without clearing the obsolete entries. I have seen medication lists with seven discontinued drugs still showing as current because nobody clicked the discontinue button in the system after the prescription was stopped. Use the secure messaging thread feature when following up on a previous conversation. Start a new message instead of replying to an existing thread and your follow-up question can get detached from the original context, forcing the clinician to scroll through unrelated conversation history to understand what you are asking about. Thread discipline is a small habit that makes a measurable difference in response quality.
The Edge Case That Nobody Warns About
Here is something I ran into that I still find frustrating. If you change your phone number or email address in MyChart, existing two-factor authentication tokens and backup codes do not always update cleanly. I went through a period where I could log in but could not receive the verification code because the old number was still the primary MFA method and the new number had not fully propagated through the authentication service. It took a phone call to the IT help desk during business hours to resolve, and the resolution involved a manual token reset that took about forty-five minutes of hold time. The workaround is to update your contact information while you still have access to the old verification method. Do not wait until you are locked out. Also, print or save your backup codes the first time you set up two-factor authentication. Most people skip that step and then regret it. I still see patients coming in with compromised accounts because they lost their backup codes and could not verify their identity through any alternate method. Another edge case involves laboratory names that appear differently across systems. Your primary care office might order a test labeled "Lipid Panel" but the reference lab that processes it could report the result as "Lipid Profile" or "Cholesterol Panel" in MyChart. This is not a discrepancy, just inconsistent nomenclature between the ordering system and the reporting system. Patients sometimes message worried that they are being tested for a different condition than what their doctor ordered. The test is the same. The label is not.
The portal has improved significantly over the last few years and the UTMB implementation is reasonably functional for routine tasks. It is not perfect and it will not handle every situation you throw at it, but knowing how it actually works behind the scenes, what delays are normal versus what indicates a problem, and where the real bottlenecks live will save you a lot of unnecessary stress. The system rewards people who understand its limitations and punishes people who treat it like a consumer app that should respond instantly to everything.