What The Medulla Actually Does
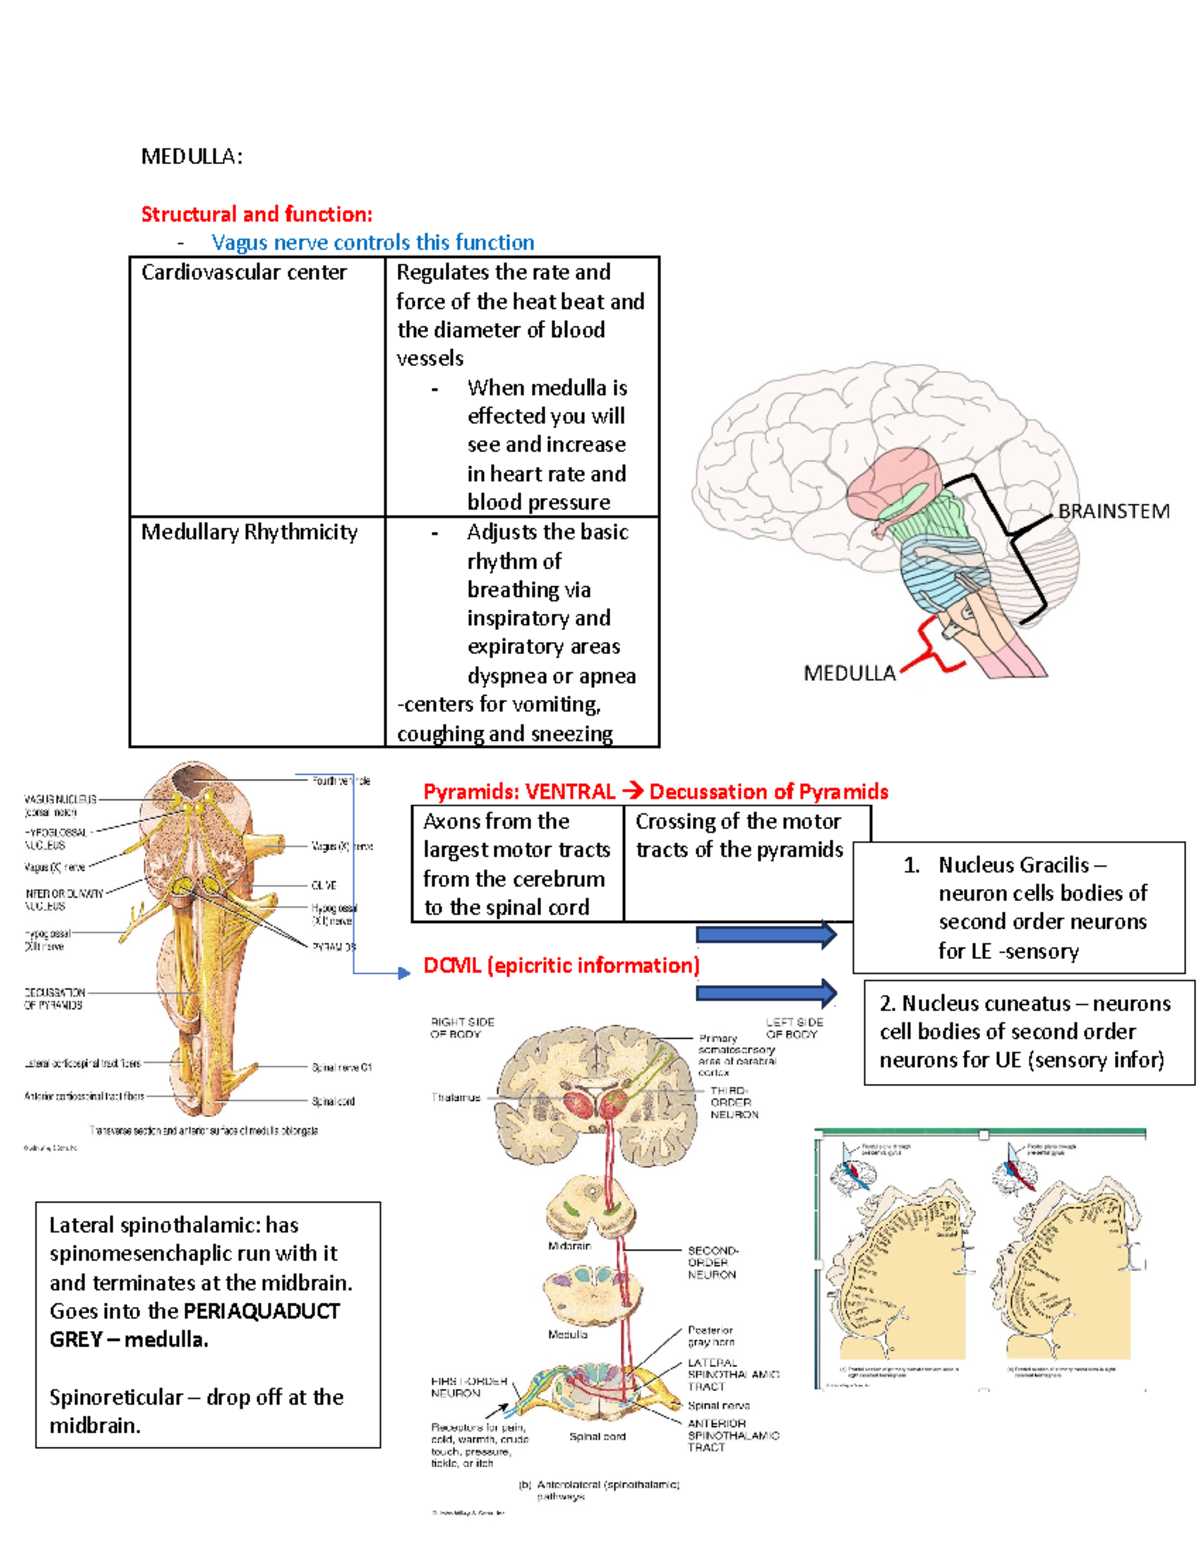
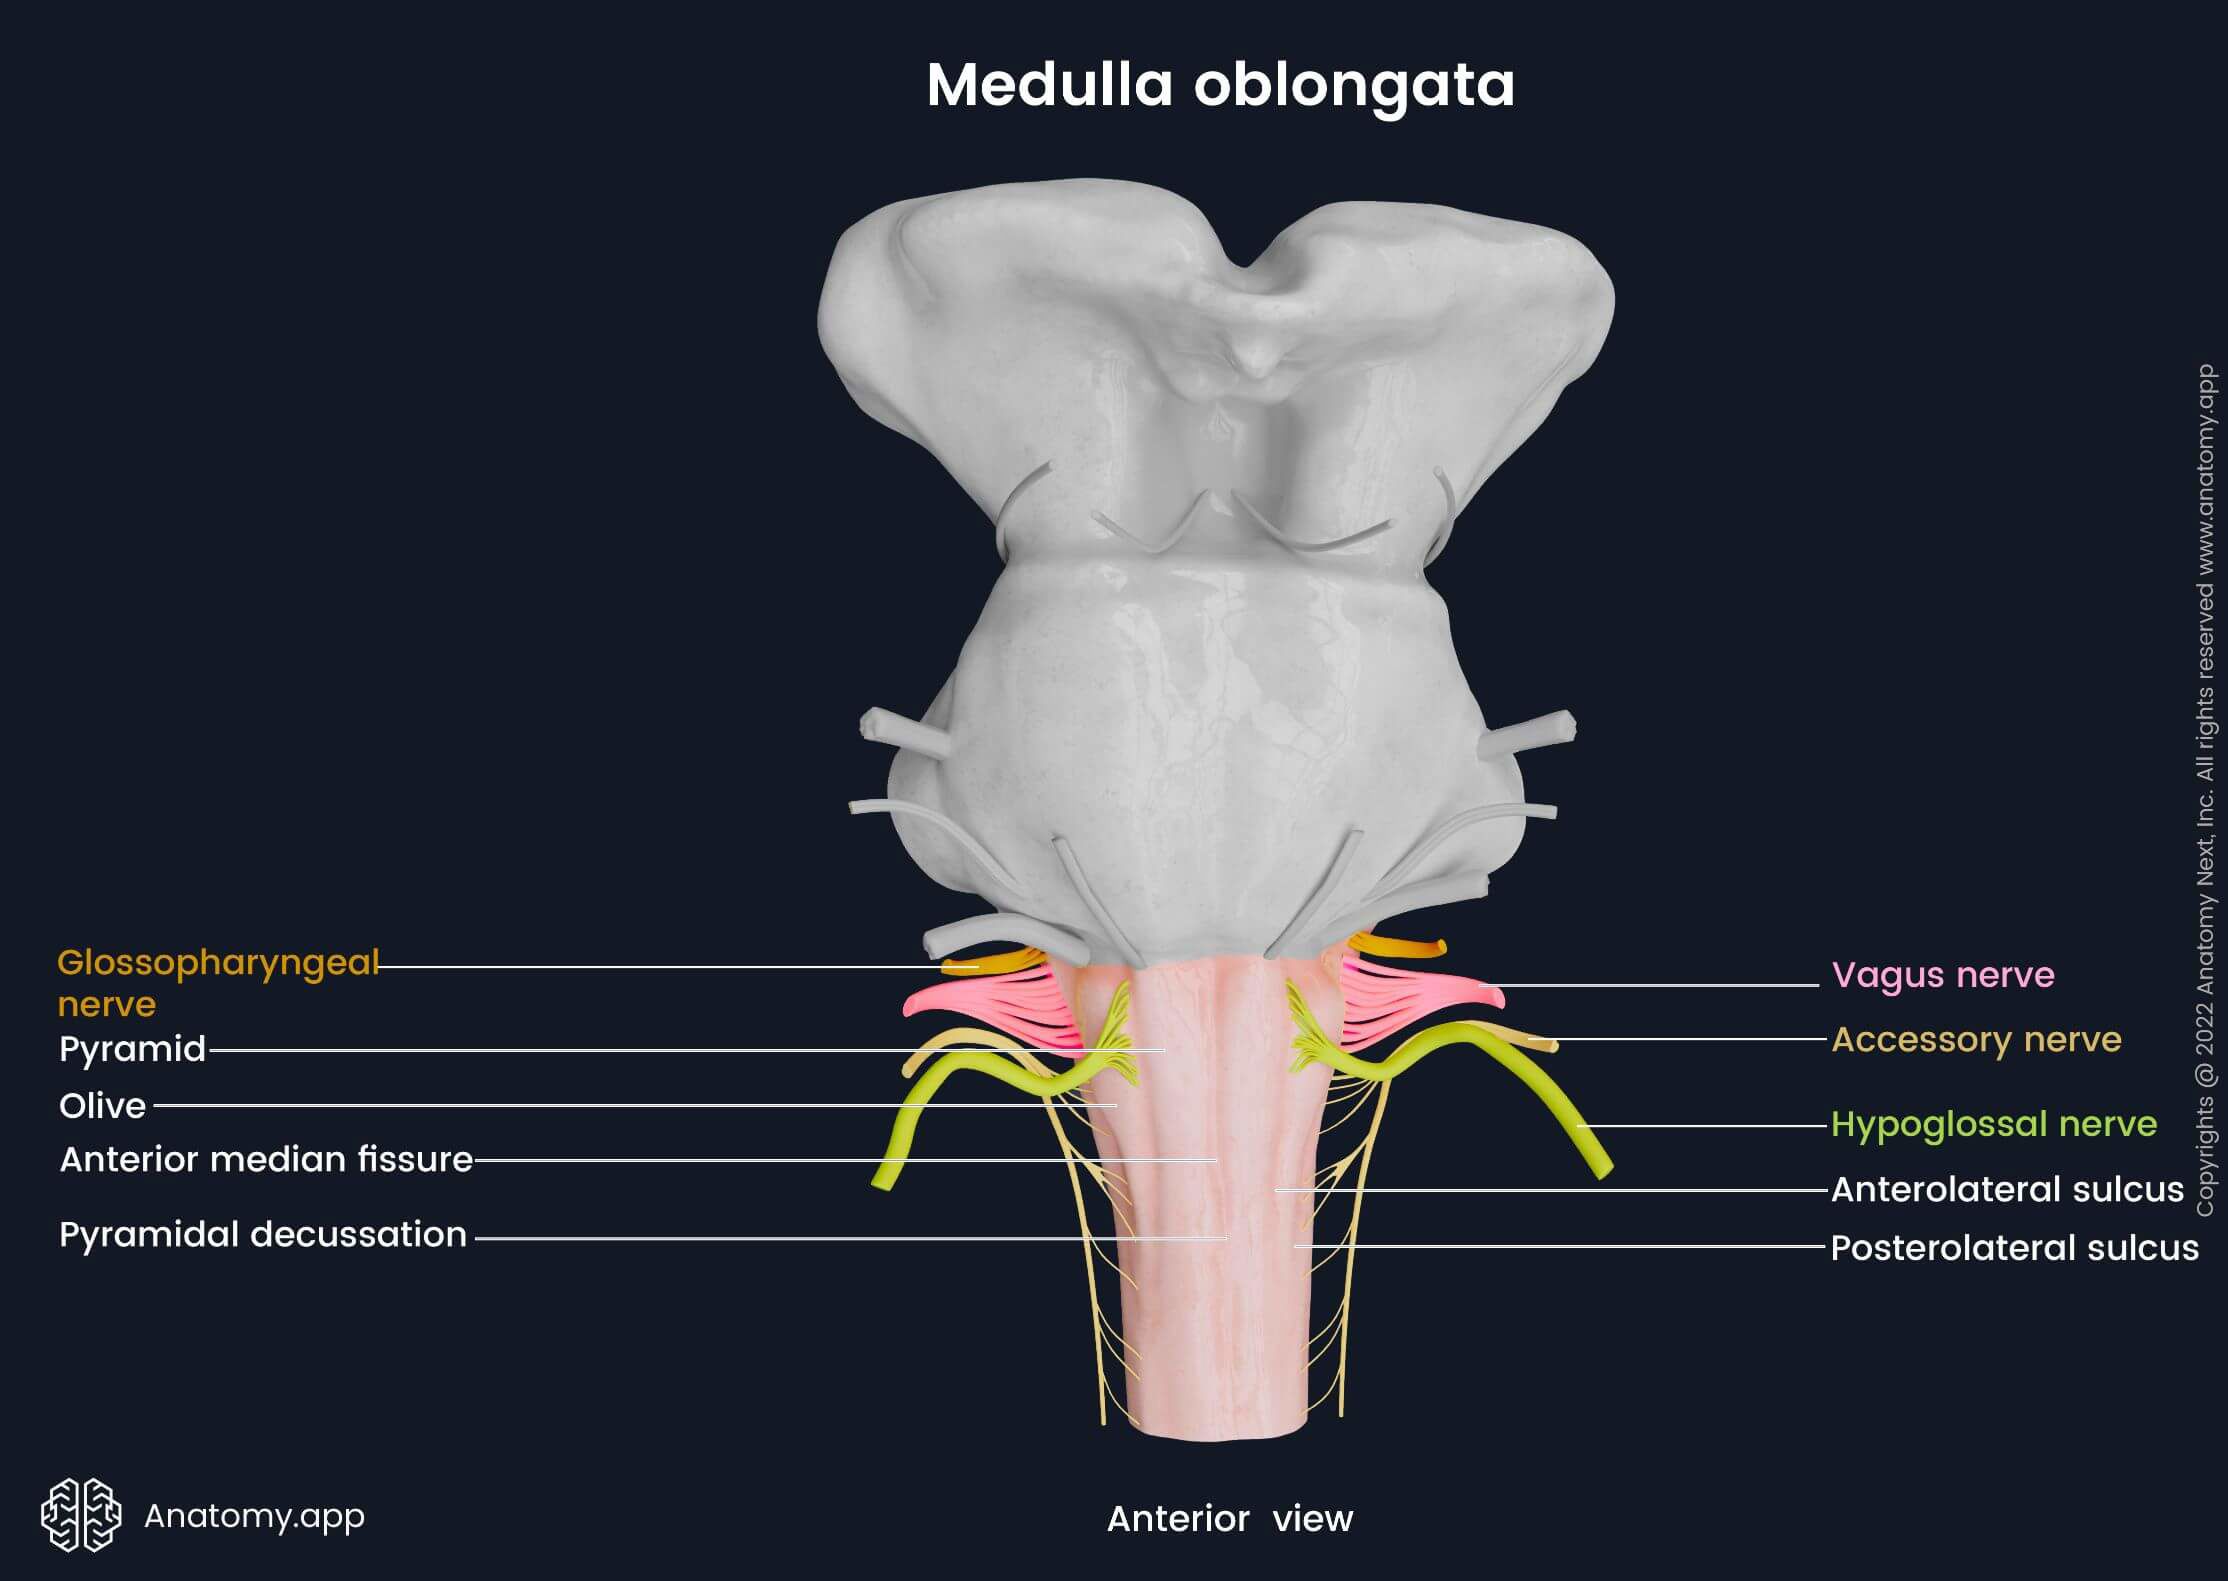
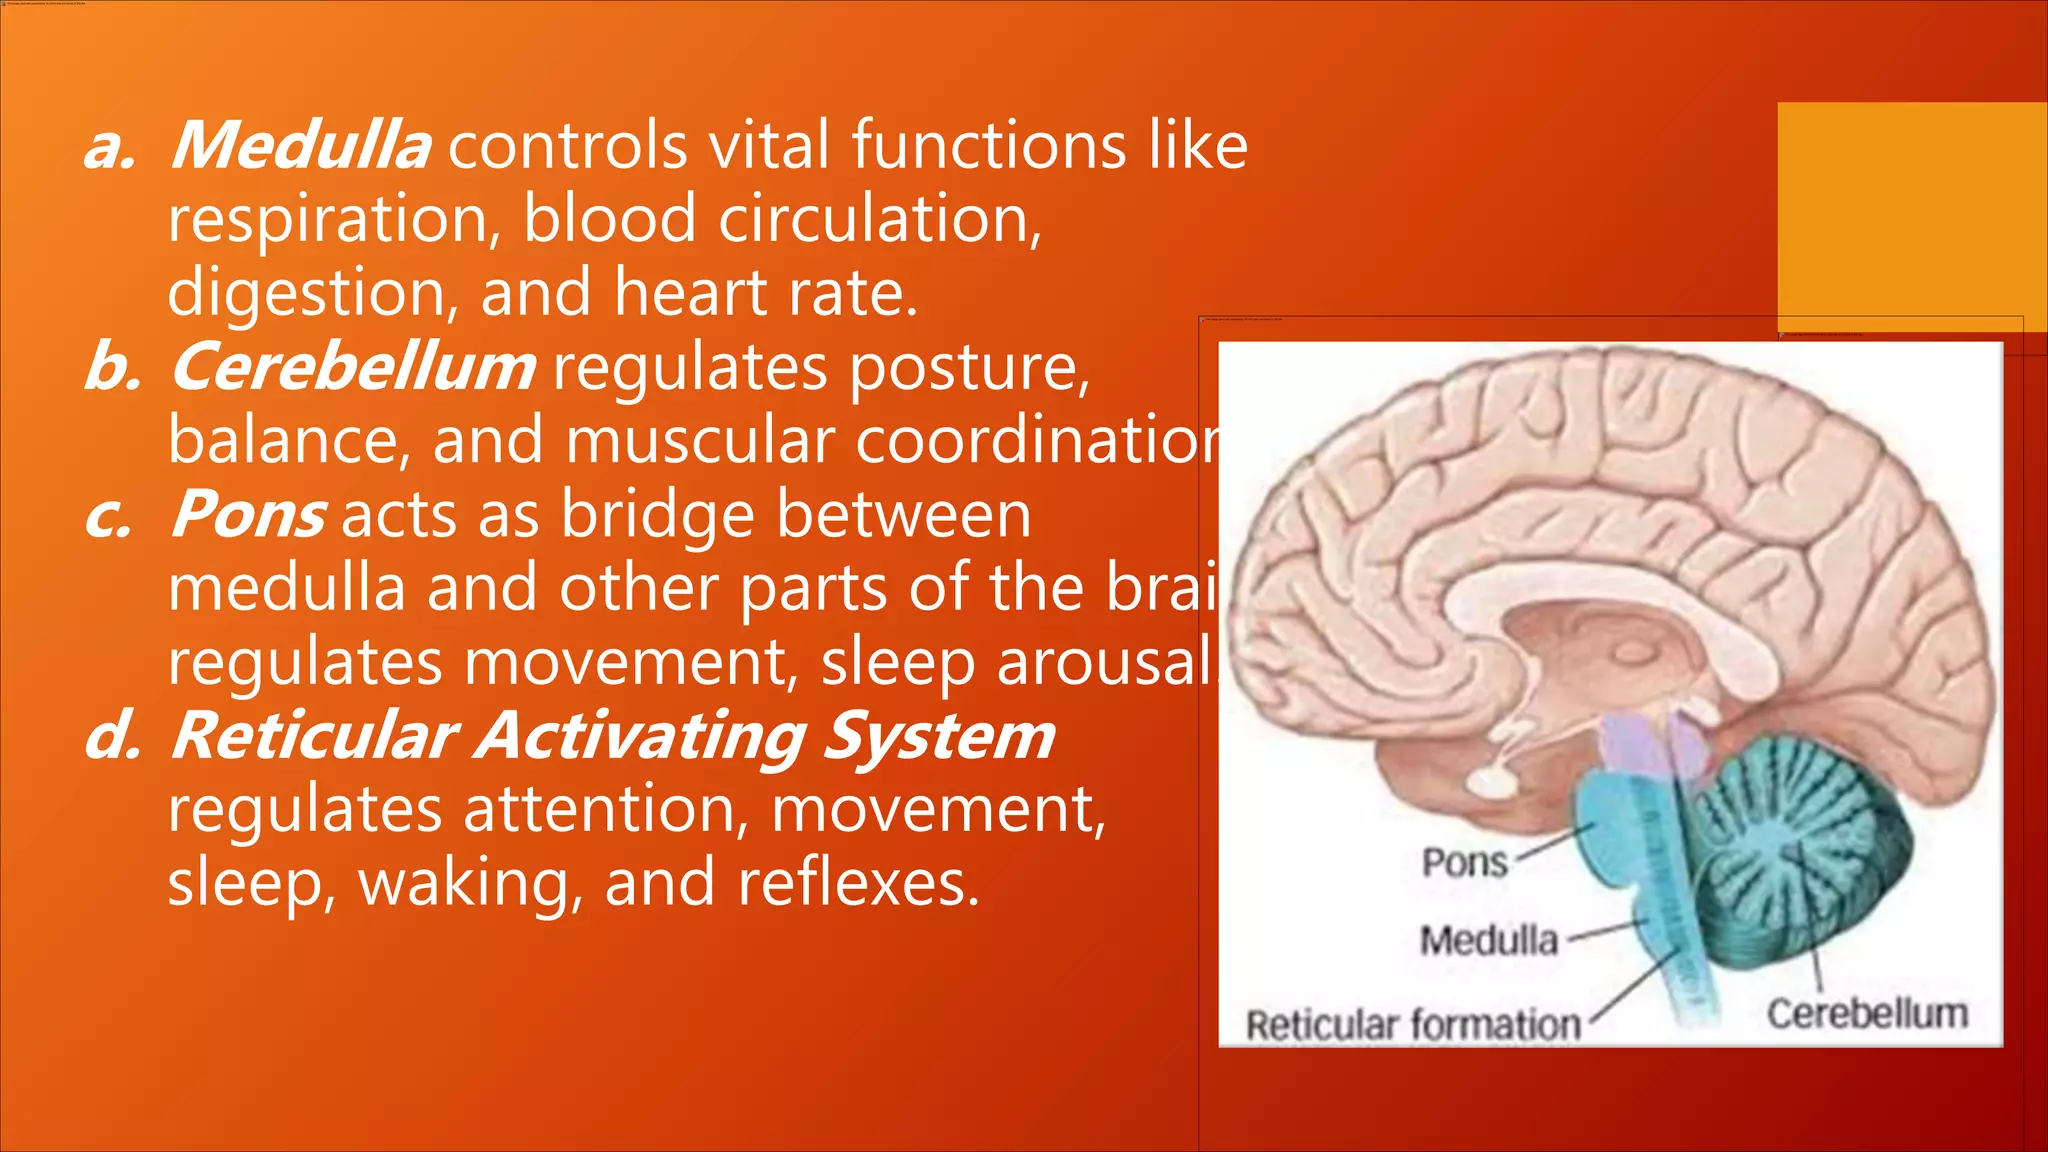
The medulla oblongata sits at the base of your brainstem where it connects to the spinal cord. It handles breathing rhythm, heart rate regulation, blood pressure control, and a handful of reflex arcs like swallowing and vomiting. That is the textbook version. The reality is messier and more interesting. It is not a simple relay station. The medulla contains nucleus tracts that cross pathways, integrate sensory input from the vagus nerve, and modulate autonomic output without any conscious involvement. When it works properly, you do not think about breathing. You breathe. When it does not, things go wrong very quickly.
Unlocking The Power Of The Medulla What Does The Medulla Do And Why Does It Matter
Understanding the medulla matters because so many clinical assessments trace back to it. Pupillary response, respiratory pattern, baroreceptor reflexes, gag reflex — these are all medullary functions. A neurologist checking brainstem integrity is largely checking the medulla. If a patient loses coordinated breathing after a stroke in the posterior fossa, that is the medulla failing to maintain rhythm generation. I spent years working in neurocritical care, and the medulla was always the first structure I worried about with brainstem lesions. There is a particular kind of urgency when you see Cheyne-Stokes breathing develop overnight. It tells you something is shifting near the ventral pons or the medullary respiratory centers, and you do not have much time to figure out what.
How The Medulla Regulates Vital Functions
Respiration starts in the medulla with the dorsal respiratory group and ventral respiratory group. These nuclei generate the basic rhythm. The pre-Bötzinger complex within the ventral group is widely considered the pacemaker for breathing. It fires bursts of action potentials that drive the diaphragm and intercostal muscles in a cycle you cannot consciously override for very long. Blood pressure regulation happens through the cardiovascular center in the medulla. Baroreceptors in the carotid sinus and aortic arch send signals via the glossopharyngeal and vagus nerves into the nucleus tractus solitarius. That nucleus processes the input and adjusts sympathetic and parasympathetic outflow to the heart and blood vessels. A drop in blood pressure triggers increased sympathetic firing. The heart beats faster, vessels constrict, and pressure rises back toward normal. This loop runs constantly. Swallowing and vomiting are also coordinated here. The solitary nucleus receives taste and visceral sensory input. The swallowing center integrates signals from cranial nerves IX and X to sequence the complex muscular contraction required to move food from mouth to stomach. The vomiting center, located near the area postrema, can trigger emesis when it detects toxins in the blood or receives signals from the chemoreceptor trigger zone.
Get the Full Details
A Real Problem I Faced With Medullary Assessment
Not long ago, I was managing a patient with a large cerebellar hemorrhage causing brainstem compression. The classic signs were there — decreased consciousness, irregular breathing, hypertensive bradycardic response. But the pupils were still reactive, which made me second-guess how far down the compression had progressed. The medulla can maintain pupillary function while losing respiratory coordination if the compressive force is asymmetric. The workaround was serial brainstem reflex testing combined with close observation of respiratory patterns over time. I was checking for subtle changes every two hours: the presence of a gag reflex, eye deviation with cold water irrigation, and the shape of the respiratory waveform on the ventilator. The trend mattered more than any single finding. Within six hours, the gag reflex disappeared and the respirations became ataxic. That told me the medulla was being crushed. We went to surgery the next morning. Delaying would have been fatal.
Counter-Intuitive Things About The Medulla
Most people think the medulla is just an automatic pilot for basic functions. It is not. It receives massive cortical input and can be modulated by higher brain centers. Stress, anxiety, and cognitive load all influence medullary output. This is why someone having a panic attack can hyperventilate until they pass out. The cortex is driving the medulla into overdrive. Another thing beginners miss: the medulla does not work in isolation. It is deeply connected to the pons and midbrain. Lesions that appear pontine often have medullary consequences because the pathways run through both. A stroke in the vertebral artery can produce lateral medullary syndrome — Wallenberg syndrome — with vertigo, loss of pain and temperature sensation on one side of the face and the opposite side of the body, hoarseness, difficulty swallowing, and Horner's syndrome. All from a single vascular territory. This is not some rare edge case. It is one of the most common brainstem stroke syndromes. There is also the issue of medullary autoregulation. The medulla maintains its own blood flow across a range of systemic pressures, but that range narrows significantly in chronic hypertension. A patient with long-standing high blood pressure can suffer medullary ischemia at blood pressures that would be perfectly fine for someone else. This is why aggressive blood pressure management in acute stroke needs careful balancing. Drop it too fast and you compromise the very structures you are trying to save.
Why This All Matters Clinically
The medulla is small, roughly the size of your thumb, and it controls everything that keeps you alive without you having to think about it. Damage here is rarely trivial. Even small infarcts can produce devastating deficits because the nuclei are densely packed. There is very little room for error. For anyone studying neuroanatomy or entering clinical practice, the medulla should not be treated as a footnote. It deserves focused attention because it sits at the intersection of consciousness, respiration, circulation, and reflex. When any of those systems fail, the medulla is usually involved. Recognizing that early saves lives.
What You Can Do With This Knowledge
If you are a student, draw the cross-sections. Trace the pathways. Learn where the decussation of the pyramids sits relative to the solitary tract. Memorize the vascular territories. Vertebral artery gives rise to the posterior inferior cerebellar artery, which supplies the lateral medulla. Basilar artery branches supply the medial structures. Know which syndrome goes with which vessel. If you are a clinician, use bedside assessment as your primary diagnostic tool before ordering imaging. Respiratory pattern tells you more than you might expect. A patient with Kussmaul breathing has a metabolic problem driving the medulla. A patient with apneustic breathing has a pontine lesion affecting medullary input. These patterns are free and they are immediate. CT scans take time. Your eyes do not. For patients and families, the medulla is the reason you do not have to consciously remember to breathe. It is also the reason that certain drugs, especially opioids and sedatives, can stop breathing altogether. They depress the medullary respiratory centers. This is not abstract pharmacology. It is the direct effect of a molecule binding to receptors in a structure that controls whether you take your next breath. That is why overdose deaths happen so quickly and why naloxone works by reversing that depression.
The medulla does not get enough credit. It runs the show from underneath everything else. Learn what it does. Pay attention when it fails. That is about all there is to it.