Point-of-care testing is everywhere now but most people still don't know what they're actually looking at when they order one
I spent about eight years working in clinical labs before moving into POCT quality oversight, and the thing that always surprised me was how many clinicians ordering these tests had never actually thought about the difference between a lab instrument and a handheld one. They just see "faster result" and move on. The reality is messier than that. POCT covers a huge range of devices. You've got blood gas analyzers in the ER, glucometers in diabetes clinics, rapid strep tests at the front desk, IL-6 and procalcitonin immunoassays on whole blood analyzers that bolted onto ICU carts, and even some basic hematology with portable counters. The common thread is just that the testing happens near the patient rather than in a central lab. Everything else varies wildly.
Unlocking The Power Of Pointofcare Testing Revolutionizing Healthcare One Patient At A Time
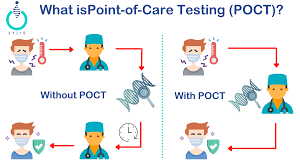
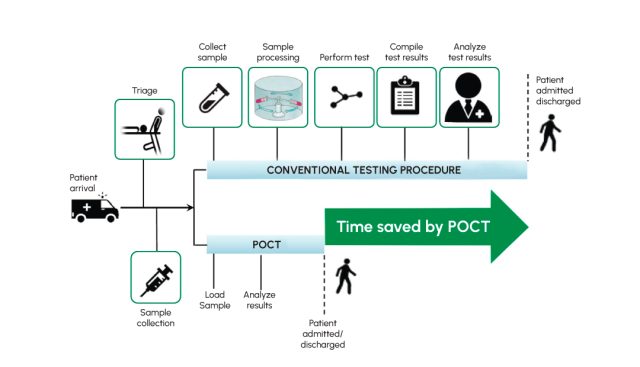
The actual workflow difference is where things get interesting. In a central lab you have phlebotomy, tube labeling, courier transport, centrifugation, instrument run time, QC, and reporting. With POCT you collapse most of that into one room. A nurse can draw blood and get a troponin back in 12 minutes instead of waiting 45 to 90 minutes for a stat lab turn-around. That matters when you're making time-sensitive decisions about cardiac pathways or sepsis protocols. But collapsing the workflow also collapses the quality infrastructure that normally protects you. That's the part nobody talks about enough. Central labs have IQC, EQA, SOPs, competency assessments, and instrument maintenance schedules enforced by lab directors. POCT devices live in clinics and wards where someone has to own that same structure without the centralized support system. I've seen sites run glucose POCT for two years without anyone verifying that the control materials were stored at the correct temperature. The results looked fine until a patient's A1c didn't match their glucose readings and someone actually traced it back. Here's how I approach setting up a POCT program practically. First, you inventory every device on site, note the manufacturer, model, firmware version, and the intended use for each one. Then you map which tests are CLIA-waived versus moderate complexity. That distinction matters because the regulatory requirements around QC, personnel training, and proficiency testing change entirely based on that classification. A CLIA-waived glucometer needs different oversight than a moderate-complexity cardiac marker analyzer, even if both are technically "point-of-care."
Next you establish who owns each device. Not the department, a specific person. I've seen devices where nobody knew who was responsible for collecting QC records because three different nurses each used it and assumed someone else tracked it. You need a single point of accountability per instrument. It sounds obvious but it's the failure mode I encounter most often in real audits. For the actual operation side, you set up a schedule that includes daily or per-run QC, monthly instrument checks, quarterly competency validation, and annual proficiency testing enrollment. CLIA requires PT at least twice a year for moderate-complexity tests, but many states and accrediting bodies want more. Check your local requirements before you assume the federal minimum is sufficient. The edge case I remember clearly involved a site running point-of-care INR testing for anticoagulation management. The device was a small whole-blood analyzer, moderate complexity, used in a dialysis unit. Everything looked normal on paper. Then I noticed the correlation between the POCT INR values and the central lab INRs was drifting. The POCT values ran consistently 0.3 to 0.5 points lower than the lab reference method over a three-month period. The techs didn't flag it because each day's QC was passing within range.
Get the Full Details

The problem turned out to be hematocrit dependency. The device's algorithm had a built-in correction for hematocrit variations, but the correction factor was calibrated for a range that didn't cover the dialysis population. These patients run chronically anemic with hematocrits in the 20s and 30s, which pushed the correction outside its validated range. The fix wasn't replacing the device or stopping the program. We submitted a variance to the state lab surveyor, documented the limitation, added a footnote to every POCT INR result flagging the potential bias, and instituted a policy where any POCT INR above 2.0 in a patient with hematocrit below 30% gets automatically reflexed to the central lab for confirmation. It's not elegant but it's practical and it prevents a real clinical error. That example illustrates the bigger issue with POCT that beginners miss. These devices are not interchangeable with their lab counterparts even when they measure the same analyte. Different methodology, different calibration, different reference ranges. A troponin result from a point-of-care immunoassay analyzer does not have the same clinical decision thresholds as the high-sensitivity troponin from the central lab. If your protocol says "troponin above X means activate the cath lab," you need to know which instrument's result triggers that pathway. Mixing them up has caused real admission errors. Another counter-intuitive thing is that POCT doesn't always produce faster results. I've seen sites spend more time on documentation, QC logging, and instrument maintenance than they save by testing on-site. It's easy to underestimate the administrative overhead. Each device needs its own logbook or electronic tracking system, each operator needs documented training and annual competency, each lot change of reagents needs verification, and every error needs investigation. On a busy ward that overhead adds up quickly.
The devices themselves have limitations that matter in practice. Strip-based tests like glucose monitors are affected by altitude, temperature, humidity, and competing substances in the blood. Immunoassay analyzers suffer from hook effect at very high analyte concentrations, which means an extremely positive result can read as borderline negative if the instrument doesn't have automatic dilution built in. Hematocrit affects nearly all whole-blood POCT devices. And sample volume requirements mean that sometimes the fingerstick just doesn't give you enough blood and you have to redraw, which defeats the speed advantage entirely. If you're building a program, start with a needs assessment that is brutally specific. Don't say "we want faster results." Say "we need cardiac markers back in under 20 minutes for chest pain patients in the ED and our current lab turn-around is 75 minutes." Then calculate whether the cost per test, the staffing requirements, the QC burden, and the quality oversight capacity justify the device. Many sites adopt POCT because it feels modern and responsive without actually doing that math. For training, keep it simple but rigorous. Initial competency should include a direct observation of at least ten patient tests compared against a reference method where possible. Annual competency should repeat that process. Document everything. The surveyors don't care how good your techs are, they care that you proved it on paper.
Data management is where most programs quietly fail. Some instruments print results that get hand-entered into the chart, which introduces transcription errors. Some link to the EHR but only send partial data. Some sit on standalone networks with no audit trail at all. Push for electronic result integration from day one. If the device can't push results to your EHR, figure out whether a middleware solution exists before you approve the purchase. The manual entry workaround always becomes permanent and always causes problems later. The biggest mistake I see is treating POCT as a collection of individual devices rather than a unified testing network. Each instrument shouldn't operate as its own island with its own QC schedule, its own training records, and its own quality metrics. You need a program-level view that tracks device utilization, error rates, QC failure patterns, and result correlation with the central lab across all instruments simultaneously. That's how you catch the slow drift before it becomes a patient safety event. I've also learned to be skeptical of vendor claims about reduced turn-around time and improved patient outcomes. The data exists but it's uneven. Some studies show meaningful improvements in sepsis bundles when POC procalcitonin is available. Others show no difference in length of stay or mortality for various point-of-care assays. The device is a tool, not an intervention. What matters is whether the result gets acted on appropriately and quickly enough to change the pathway.

If your site already has POCT and you're looking at expanding it, evaluate the existing program's performance data first. Look at your QC failure rates, your proficiency testing scores, your incident reports, and your EHR integration coverage. If those metrics are solid, adding another device category is manageable. If they're messy, you're going to make the mess bigger, not better. The regulatory landscape keeps shifting too. CLIA requirements are the floor, not the ceiling. CAP has published POCT accreditation guidelines that go beyond CLIA. Some states have additional requirements. Your hospital's own medical staff bylaws may impose further restrictions on who can perform and who can order POCT. Check all of those before you write your policy manual. One last practical note about inventory. Track your reagent lots meticulously. When a manufacturer issues a recall or field safety notice, you need to know exactly which devices were affected, which patients were tested with that lot, and whether any results need to be flagged or repeated. I've seen sites waste days tracking down lot numbers because nobody updated the inventory log when a new box of strips was opened.
POCT works well when you respect the infrastructure it replaces rather than pretending you don't need it anymore. The speed advantage is real. The clinical value depends entirely on whether you manage the quality side with the same seriousness you would if those instruments were sitting in a central lab where someone actually checked.