Labcorp Link Is Just A Portal — But The Data Behind It Is The Actual Product
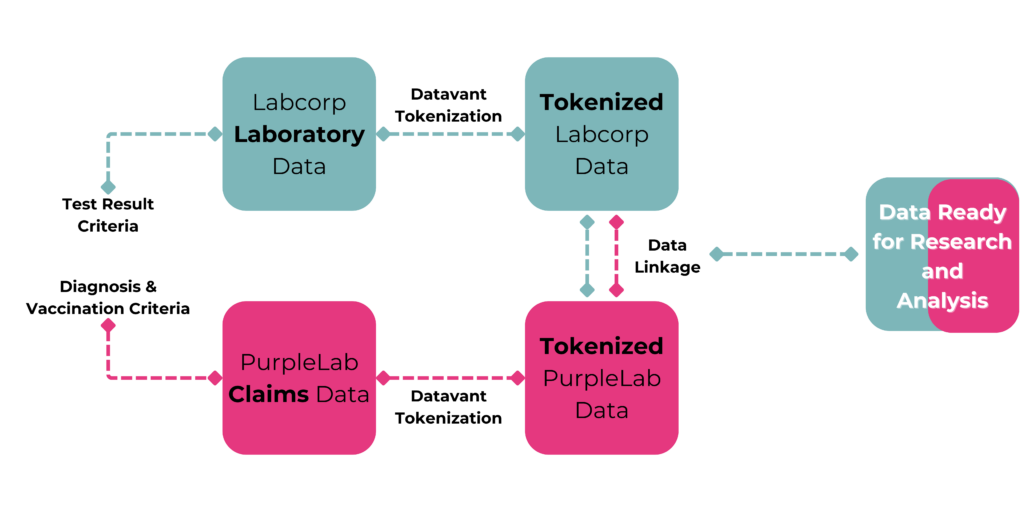
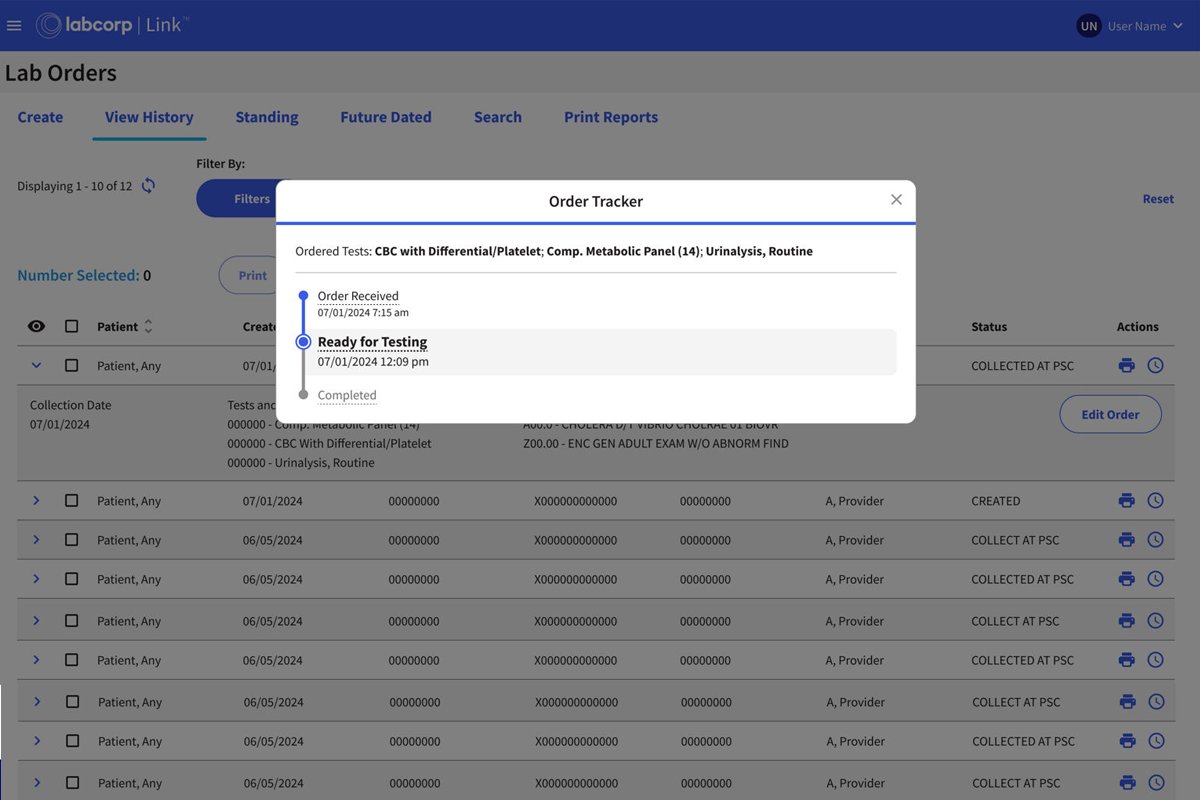
Labcorp Link is the primary web and API-driven communication platform Labcorp uses to deliver test results, messages, and order management tools to healthcare providers, labs, and patients. Most people treat it like a standard login page where you check results. That is an incomplete picture. The platform functions as a data aggregation and distribution hub that connects the lab's internal LIS (Laboratory Information System) with provider EHRs, practice management software, and patient-facing tools. The revolution is not the interface. It is the downstream data flow. The core mechanism is straightforward once you understand what is happening under the hood. When a clinician orders a test through an EHR that has an HL7 or FHIR interface with Labcorp, the order travels digitally. The lab receives it, logs the specimen, runs the test on analyzers, and sends the result back through the same channel. Labcorp Link sits in the middle as the delivery layer. Providers see results populate in their own workflow. Patients get access through a separate patient portal instance. That routing, validation, and normalization of data is where the actual value lives. I spent several years working on integration projects between regional health systems and major reference labs, and one thing everyone gets wrong about Link is the assumption that result delivery is instantaneous. It is not. There is a delay between when the analyzer signs off on a result and when it appears in the provider's Link dashboard. In my experience, this typically runs 4 to 12 hours for routine chemistry and hematology panels, and up to 48 hours for specialty and microbiology tests that require manual review. The delay is not a bug. It is a quality control gate. Results that trigger critical value alerts or flag anomalies go to a pathologist or senior technologist for verification before they are released into the system. If you are pulling results via API and expecting real-time data, you will write buggy code. Build in polling intervals and asynchronous callbacks instead.
Here is a specific edge case I ran into that took me two weeks to resolve. A mid-sized clinic network was using the Link Patient Access API to pull results for about 3,000 patients and display them in their own patient app. Everything worked fine until we tried to fetch results where the patient had multiple test orders on the same day with different panel combinations. The API returned overlapping result sets. A complete metabolic panel and a lipid panel ordered together would generate separate result objects that both appeared in the feed, making it impossible for the app to correctly group them into a single visit summary. The workaround was not in the API documentation anywhere. I ended up using the accession number as the grouping key rather than the test order number. Each physical tube of blood gets its own accession number, and all tests drawn from that draw are linked under it. By grouping results by accession number first, then by test code, we got clean, chronological result sets. Labcorp support eventually confirmed this was the intended behavior but admitted their developer documentation did not explicitly state it. The data-driven diagnostic piece comes from how Labcorp has structured the return payload. Modern Link integrations return results in LOINC-coded formats with reference ranges, historical trend data, and flag annotations all embedded in the response. A provider pulling results through a well-built interface does not just see "Glucose: 98 mg/dL." They see the LOINC code, the reference interval, a rolling trend graph across previous draws, and any flagged status from the lab's interpretation engine. That is the shift from reactive testing to proactive monitoring. Some practices I consulted with were able to identify trending renal function decline in dialysis patients three months earlier than before because the trend visualization in Link made subtle changes visible that individual result reviews had missed. There are two common pitfalls that catch people off guard. The first is credential management. Labcorp Link uses a dual-authentication model for clinical users. The provider account requires multi-factor authentication, but the API client ID and secret are separate credentials that many organizations store in the same vault as their EHR integration keys. When you rotate those credentials, do not forget the API client rotation happens on a different schedule and through a different process than the SSO credential reset. I watched a clinic's entire result feed go dark for five days because someone rotated the MFA tokens and assumed the API keys would follow the same rotation path. They did not.
The second pitfall is more subtle. The results you receive through Link are the finalized, signed-off results. They are not preliminary. If you are building a system that needs to alert providers about critical values while a test is still in progress, Link is not the right tool. You need to look at Labcorp's critical value notification service, which is a separate API endpoint that pushes alerts before the full result is posted to the main dashboard. These two services are not advertised together and the documentation treats them as entirely separate products. Most integration guides I have seen focus only on the result retrieval endpoint and skip the critical value path entirely. If your use case involves time-sensitive notifications, you need both. Let me be blunt about the limitations. Labcorp Link is not a universal solution for every lab testing workflow. It works well for high-volume routine testing and standard specialty panels. It struggles with research-grade testing, investigational assays, and certain molecular diagnostics where the result interpretation requires clinical context that a standardized data field cannot capture. The platform also has rigid turn-around-time expectations baked into its reporting metrics. If a lab is processing a low-volume test that takes variable time based on specimen quality, the Link reporting dashboard will flag those delays as performance issues even when the delay is clinically justified. I have seen labs artificially inflate their throughput numbers by splitting complex tests into sub-components just to meet the SLA thresholds that Link tracks. It is a gaming problem, not a technology problem, but it is real. For organizations that want to build on top of this, the practical first step is not downloading software. It is requesting API access through Labcorp's developer portal, which requires a valid CLIA-certified organization number and a signed data use agreement. The onboarding process typically takes 10 to 14 business days. Once you have access, the sandbox environment is functional but uses synthetic patient data that does not always mirror the edge cases you will hit in production. I recommend running a parallel integration test with a small real patient cohort before you commit to a full rollout. The data will not be identical, but the error patterns will be representative.
Get the Full Details

The platform is free for providers who already have a Labcorp testing relationship. There is no licensing fee for the basic result access tier. The premium tiers that include advanced analytics dashboards and custom report builder tools start at a per-provider monthly rate that varies by organization size. Patient access is free. The cost comes in implementation and integration maintenance, which is where most budgets get surprised. A straightforward EHR-to-Link integration for a single specialty practice usually runs between 40 and 80 engineering hours. Multi-site health systems with legacy systems that require middleware translation can exceed 200 hours before the first result successfully flows end to end. What makes this different from the old fax-and-phone model is not speed alone. It is the ability to write queries against accumulated result data. A lab director can pull every hemoglobin A1c result for a specific patient across a five-year span in under a minute. An integrated care team can generate a cohort report of all diabetic patients whose last three A1c readings show a downward trend without opening a single chart. That is the actual revolution. The portal is just the window. The data is the infrastructure. If you are evaluating whether to integrate Labcorp Link into your practice workflow, the decision should not be based on convenience. It should be based on whether your organization has the engineering capacity to maintain the integration. These systems decay. API versions change. Authentication methods update. Result fields get deprecated. The organizations that treat this as a set-it-and-forget-it tool are the ones that end up with broken dashboards and confused staff six months later. Build for maintenance from day one. Document your accession number grouping logic. Set up credential rotation alerts that are separate from your general IT password policies. Test the critical value notification path alongside the standard result retrieval path. And do not assume the documentation you read today will be accurate a year from now. It never is.
.jpg "Enhance lab workflow with integrated data & analytics | Labcorp")

