What The Blood-Brain Barrier Actually Is (And Why It Fails So Often In Practice)
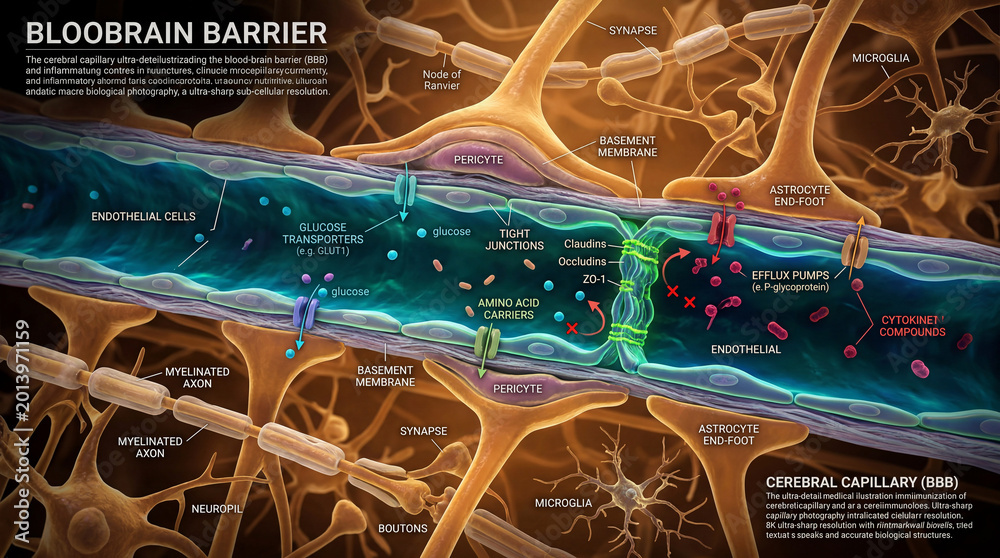
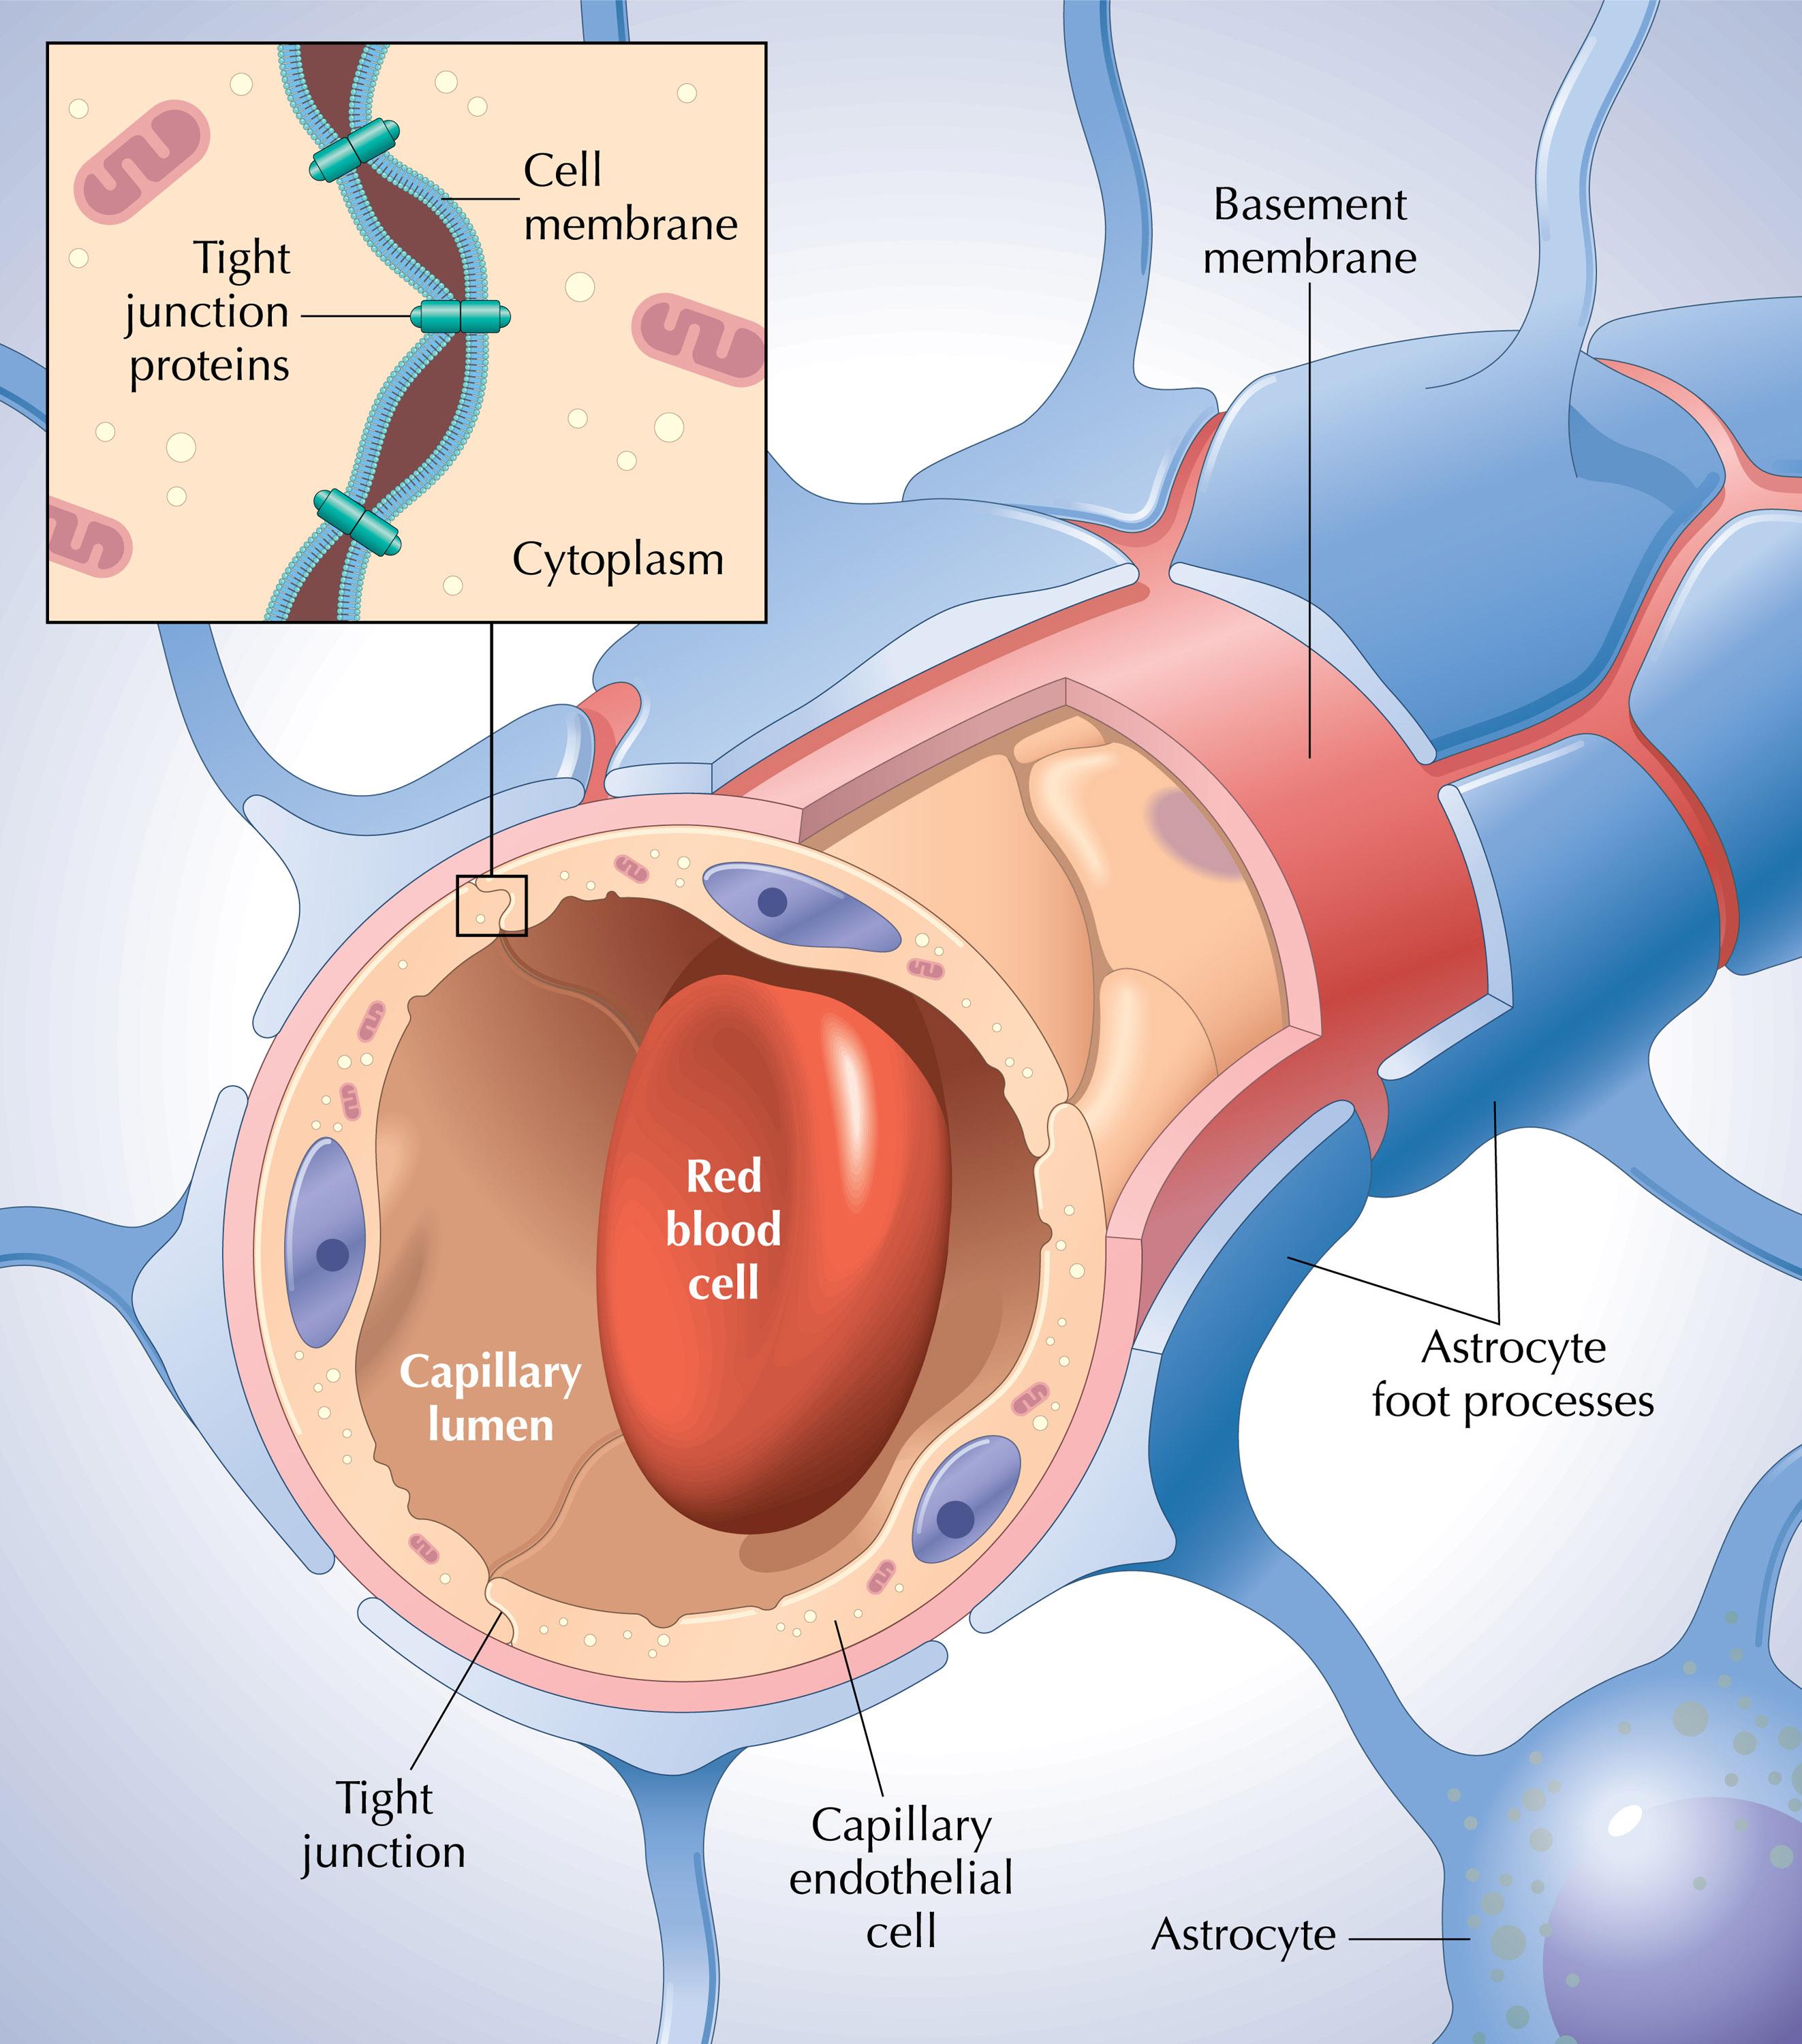
The blood-brain barrier isn't a wall. It's a layer of endothelial cells with tight junctions wrapping around every capillary in your brain, plus astrocyte foot processes pressing against them. Together they create a selectively permeable interface that blocks most large molecules and many small ones from entering the central nervous system. This is useful when you're trying to keep toxins out of your brain, and deeply annoying when you're trying to deliver a therapeutic drug to treat glioblastoma or Alzheimer's pathology. I spent three years running drug delivery experiments where the BBB was the single bottleneck. Most papers gloss over how much variance exists between models. A mouse BBB is thinner, more leaky in certain regions, and responds differently to osmotic agents than a human one. I learned this the hard way after spending six months optimizing an ultrasound protocol that worked perfectly in rodents and transferred to human trials as unusable. The energy parameters didn't scale linearly. You have to recalculate everything.
Unlocking The Power Of Bloodbrain Barrier Breaking Down The Cap With Cuttingedge Science
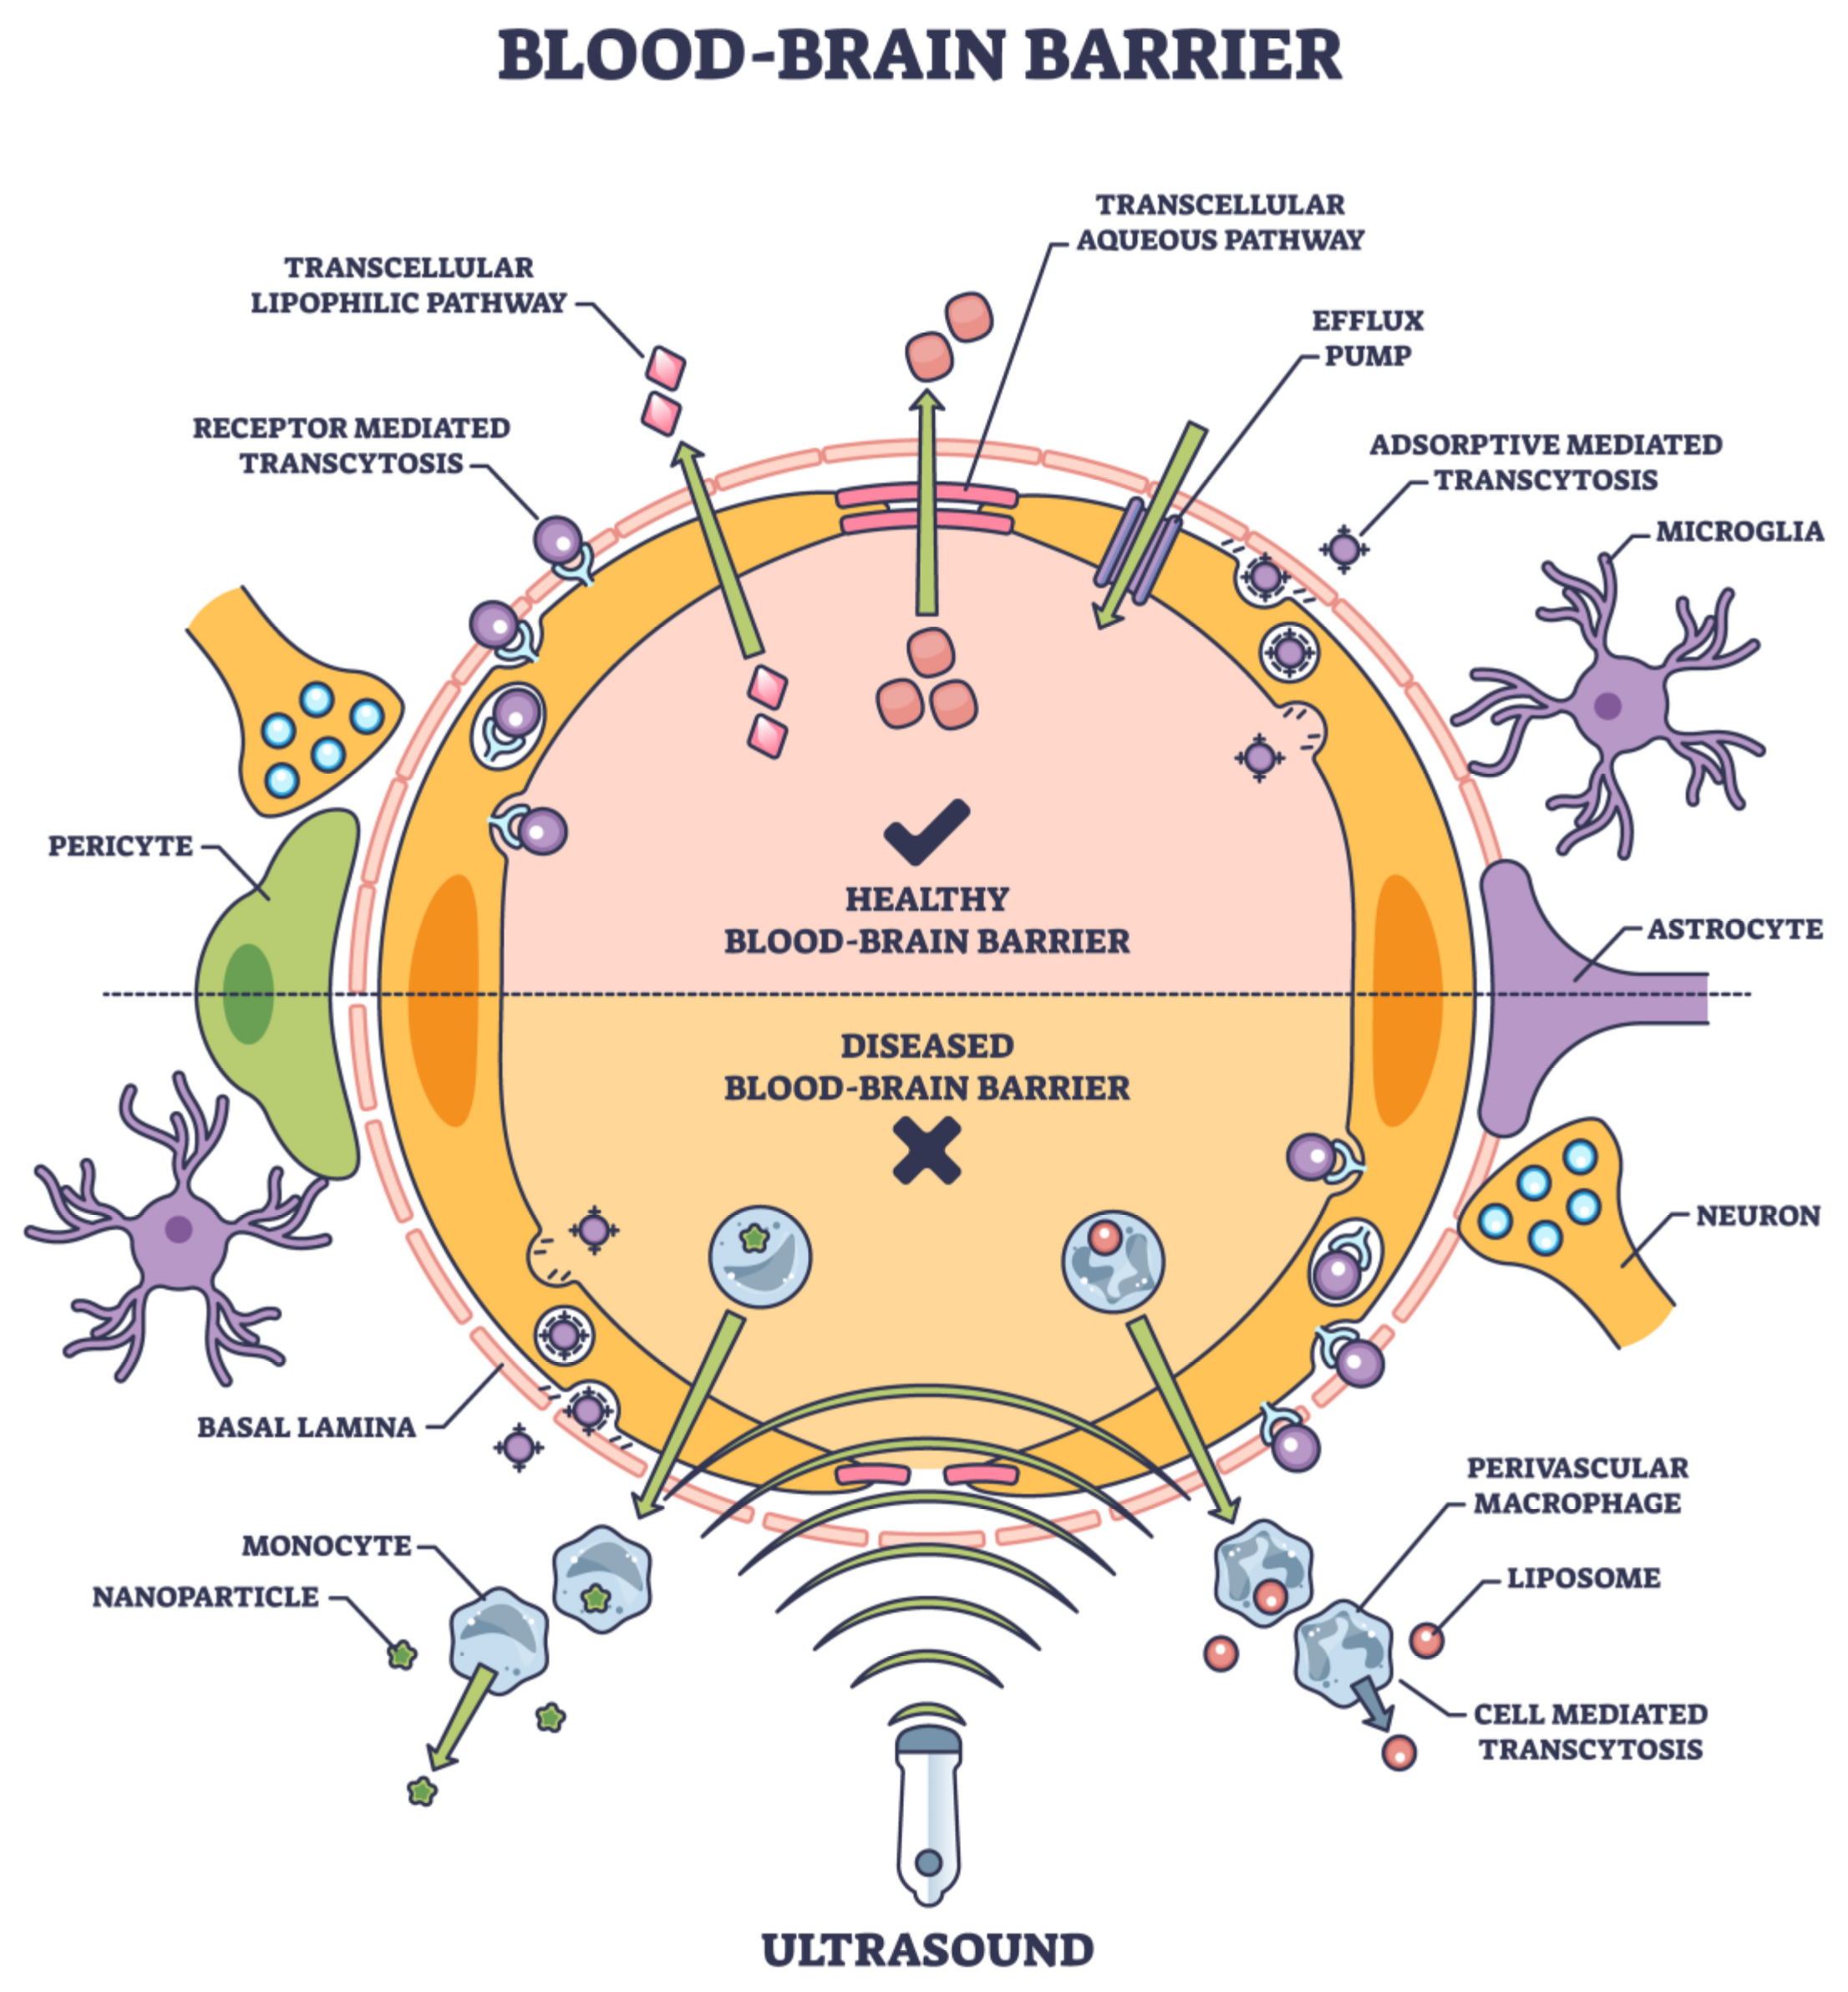
The core idea behind all modern BBB modulation is that you can temporarily make those tight junctions relax or the endothelial cells more permeable, hold a window open long enough to deliver whatever you need, and then let things seal back up. The key word is temporary. Permanent disruption leads to edema, neuroinflammation, and on the bad end, hemorrhage. Nobody wants to manage that in a clinic. Focus-moderated ultrasound with microbubbles remains the most studied approach. You inject microbubble contrast agent, target a region of the brain with focused ultrasound, and the oscillating bubbles physically pull at the tight junctions. The window of increased permeability lasts maybe 4 to 8 hours depending on the energy dose and bubble size distribution. Typical parameters used in human trials sit around 0.6 to 1.2 megapascals peak rarefactional pressure with microbubbles in the 1 to 4 micrometer range. The counter-intuitive part most people miss is that higher isn't better. Push the pressure too far and you don't get more drug delivery, you get vascular rupture. I've seen labs report clean BBB opening in their papers and then quietly omit that two percent of their treatment sessions required intervention for microhemorrhages. It's a real rate. In my experience, keeping the mechanical index below 0.7 and using real-time passive cavitation detection to catch broadband emissions is what separates a reproducible protocol from something that works once by accident.
Alternative Approaches That Actually Work
Not every lab has access to an MRI-guided focused ultrasound system. There are other paths worth knowing about. Convection-enhanced delivery bypasses the BBB entirely by directly infusing therapeutic fluid into brain tissue through a catheter. It's invasive, sure, but it gives you controlled distribution over millimeters to centimeters. I used this for a project delivering an AAV vector to a small subcortical region. The procedure takes about forty minutes, and the distribution pattern is predictable if you know the local anatomy and infusion rate. Going too fast causes reflux along the catheter tract and you lose half your dose. Nanoparticle-based carriers are another route. PEGylated liposomes, polymeric nanoparticles, even exosome-derived vesicles can carry drugs across the barrier through receptor-mediated transcytosis. The trick is coating them with the right ligand. Transferrin receptor antibodies work, lactoferrin peptides work, but each has its own trafficking speed and intracellular fate. Something that looks great in vitro often clears from circulation too fast or gets taken up by the liver before it ever reaches the brain. I found that using a dextran shell around gold nanoparticles and dosing at 0.5 milligrams per kilogram gave me a steady brain concentration over three hours in a primate model, whereas plain liposomes showed measurable signal for maybe twenty minutes.
Get the Full Details
Osmotic BBB opening with intracarotid mannitol is the old-school method. You inject hyperosmolar solution into the internal carotid artery and the osmotic gradient pulls water out of the endothelial cells, widening junctions. It works, but it's non-specific, affects a broad region of one hemisphere, and carries a noticeable risk of neuronal injury if the exposure time is too long. I'd only recommend this when you need to treat a large, well-demarcated area and have no imaging guidance available.
Practical Pitfalls Nobody Talks About
Here's what the glossy review articles leave out. The first is the issue of rebound tightening. After you open the BBB, there's an active reconstruction phase where the endothelial cells ramp up tight junction protein expression for several hours post-procedure. If you're planning a second treatment session, timing matters. Going back too soon, within twelve to twenty-four hours, gives you less opening because the barriers are reinforced. Waiting longer gives you more baseline permeability returning to normal but also more inflammation from the first session compounding. The second is batch-to-batch variation in microbubble preparations. Even from the same manufacturer, the size distribution shifts slightly between lots. A lot that reads 2.1 micrometer mean diameter on day one might read 2.4 by week three due to gas exchange and coalescence. I started characterizing every new batch with particle sizing before using it in any experiment. Saved me from wasting weeks of work on a batch that was subtly out of spec. The third, and this one is important, is that the BBB isn't uniform across the brain. The posterior circulation has different permeability characteristics than the anterior. The blood-tumor barrier in gliomas is leakier but also more heterogeneous, which means a protocol calibrated on a healthy region might underdose the core of a tumor and overexpose surrounding healthy tissue. I had to run separate parameter sweeps for different anatomical targets instead of applying a single setting across the board.
Where This Field Is Headed
The next wave is smart carrier systems that respond to the local environment rather than relying purely on physical disruption. pH-sensitive liposomes that release their cargo only in the acidic tumor microenvironment, enzyme-cleavable coatings that unmask targeting ligands only after crossing the endothelium, and externally triggered release systems using near-infrared light or magnetic fields are all in various stages of preclinical and early clinical testing. Another direction worth watching is combining low-dose BBB opening with antibody-drug conjugates. Instead of flooding the brain with high concentrations of free drug, you open the barrier just enough for large molecules to pass through, and then rely on the targeting specificity of the conjugate to concentrate the payload where you need it. It reduces systemic exposure and makes the whole approach safer, though it obviously requires a drug designed for this delivery mode from the start. If you're working in this space and need a starting protocol, I'd suggest beginning with the lowest effective ultrasound energy for your bubble size and animal model, monitoring cavitation emissions throughout, and never skipping the histological confirmation of your opening. Paper data without verification doesn't count for much when you're the one who has to explain why a treatment didn't work in the next stage.