Why Your Shoulder Blades Look Wrong and What Actually Fixes It
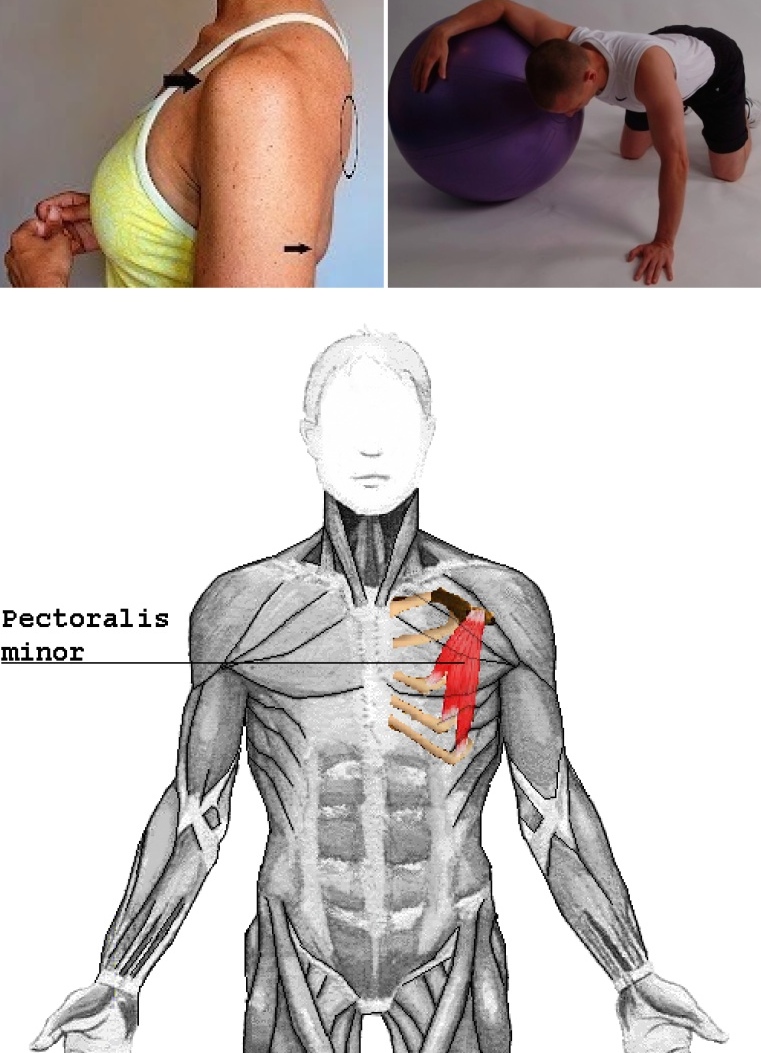
The pec minor sits underneath the pectoralis major, attaching from ribs three through five up to the coracoid process of the scapula. When it is chronically shortened, it pulls the shoulder blade forward and downward. This creates internal rotation of the humerus, rounded shoulders, and a visible loss of scapular control during pressing movements. Most people treat the symptom and ignore the root cause. They stretch their upper traps, foam roll their lats, and wonder why their posture looks exactly the same the next week. I spent about six months dealing with my own version of this problem before I actually understood what was happening. I had chronic front delt and shoulder impingement pain during overhead presses. My shoulder would catch at about sixty degrees of elevation, and I could not figure out why my rotator cuff "worked fine" on isolation movements. I had a client, a competitive baseball pitcher, who had nearly identical symptoms, except his issue was arm acceleration deceleration related. He could not extend his shoulder fully after the throwing motion without sharp pain between the shoulder blade and the rib cage. The breakthrough came when I started palpating the pec minor at the coracoid process instead of just rolling over the pec major. The difference was immediate. The pec minor tissue felt like dense, fibrous rope rather than normal muscle. After roughly forty seconds of sustained pressure at that point, my client reported a significant reduction in that posterior shoulder ache, and his overhead reach improved by about twenty degrees. This is not a minor detail. A twenty degree change in scapular position is the difference between a clean press and a painful impingement.
The mechanism is straightforward. A shortened pec minor tilts the scapula into anterior tilt and protraction. It also internally rotates the humerus passively because of the way the glenohumeral joint aligns with a malpositioned scapula. During any pushing movement, the humeral head then jams into the front of the glenoid, creating the pinching sensation. This is what causes the common misdiagnosis of rotator cuff tendonitis. The tendon is irritated because the joint mechanics are wrong, not because the tendon itself is the primary problem.
How To Release The Pec Minor Properly
You need a firm ball, a lacrosse ball or a specialized myofascial release ball. Do not use a softball unless you enjoy bruising your sternum. Sit or lie down with the ball positioned between your upper chest and a wall. Locate the pec minor by finding the coracoid process, which is the bony bump about two inches below the collarbone near the shoulder joint. The pec minor fibers run from that area down toward the third, fourth, and fifth ribs. Place the ball on the muscle belly, not directly on the coracoid process itself. Press in at about a forty five degree angle toward the shoulder blade. You are looking for a tender spot that feels deep, not superficial. Hold sustained pressure for thirty to sixty seconds. Breathe normally. Do not bounce. When the tension begins to decrease, which usually takes about forty five seconds, slowly move to the next spot. Repeat this for the entire muscle belly, which typically takes about three minutes per side. I ran into a specific edge case that most guides skip over. Some people have a very pronounced pec minor trigger point that refers pain into the wrist and hand, mimicking a nerve compression issue. I had a client who complained of numbness in his ring and little fingers. We spent weeks working on cervical spine issues and thoracic outlet syndrome with no improvement. The breakthrough happened when we pressed on that specific pec minor trigger point near the coracoid, and the hand numbness decreased noticeably within two minutes. I recommend anyone with unexplained arm or hand symptoms try pec minor release before spending money on diagnostic imaging or specialist referrals. The referral pattern from the pec minor can absolutely mimic ulnar nerve issues. If you get relief from the release, you have your answer.
Get the Full Details

The Stretch That Actually Works
Most people do the doorway stretch incorrectly. They lean forward with their arm at ninety degrees of abduction and wait for a pull. This primarily stretches the pec major, not the pec minor. The pec minor requires a different positional approach. You need to combine shoulder extension with abduction and external rotation simultaneously. Here is the proper sequence. Stand in a doorway or use a sturdy post. Place your forearm against the frame with your elbow slightly below shoulder height. Your hand should be higher than your elbow, roughly at about a one o'clock position if you imagine your shoulder as the center of a clock. This places the arm in extension, abduction, and slight external rotation. Step forward with the opposite leg, not the same side leg. Keep your core braced and do not arch your lower back excessively. You should feel the stretch deep in the front of the shoulder, near the armpit area, not across the broad chest. Hold for sixty to ninety seconds. Repeat twice per side. I usually see people hold this stretch for only thirty seconds, which is insufficient for myofascial adaptation. The connective tissue needs sustained loaded length to remodel. Going beyond ninety seconds does not provide additional benefit and can sometimes increase joint irritation. Sixty to ninety seconds is the sweet spot for most people.
Strengthening The Antagonists
Releasing the pec minor is only half the equation. If you do not strengthen the muscles that counteract its pull, the pec minor will just shorten again within days. The primary antagonists are the lower trapezius, the serratus anterior, and the rear deltoid. Without adequate strength in these areas, the pec minor wins the tension battle every time because it is a smaller, tighter muscle designed for postural stability, not movement. The most effective exercise for this is the prone Y raise, not the prone T raise. Lie face down on an incline bench at about thirty degrees, or on the floor with a pillow under your stomach. Extend your arms overhead at about a thirty degree angle from your torso, forming a Y shape. Lift your arms off the surface by squeezing your lower traps. Do not shrug your shoulders toward your ears. The movement should come from the muscle between your shoulder blade and your spine. Three sets of eight to twelve reps per side is sufficient. Most people can only manage five clean reps initially because their lower traps are functionally inhibited. For the serratus anterior, the scapular push up is non-negotiable. Get into a plank position, keep your arms straight, and protract your shoulder blades by pushing the floor away. Your ribs should stay down. Do not let your lower back sag. This trains the scapula to move correctly against resistance. Three sets of ten to fifteen reps. I also recommend adding wall slides with a focus on maintaining contact between the forearms and the wall throughout the entire range of motion. This provides real-time feedback on whether your scapula is tracking properly.
Common Mistakes That Undermine Progress
The first mistake is releasing the pec minor once and expecting permanent results. Fascia and muscle tissue adapt to the positions you hold repeatedly throughout the day. If you spend eight hours at a desk with your shoulders rolled forward, one release session will not retrain that pattern. You need consistent daily or every other day work for at least three to four weeks before seeing lasting postural changes. The second mistake is ignoring thoracic spine mobility. A stiff thoracic spine prevents the scapula from moving through its full range, which means the pec minor remains under constant tension even after release. A simple self-assessment is the overhead squat. If your arms cannot reach straight overhead while maintaining a neutral spine and your lower back arches excessively, your thoracic extension is limited. Address this with thoracic extensions over a foam roller before or after pec minor work. Five sets of ten extensions per day is usually enough to see improvement within two weeks. The third mistake is overstretching the pec minor to the point of joint instability. The pec minor provides important anterior stability to the glenohumeral joint. If you aggressively stretch it for extended periods without strengthening the posterior musculature, you can create anterior shoulder laxity. This is particularly relevant for individuals who already have hypermobile shoulders. In those cases, focus on strengthening first and use gentle release rather than aggressive stretching. I worked with a client who had mild Ehlers Danlos syndrome, and aggressive pec minor stretching made her shoulder instability worse. We switched to a strengthening dominant approach and her symptoms improved significantly.

Practical Integration Into Training
The most efficient way to incorporate pec minor work into an existing routine is to do it as part of your warm up, before any upper body pushing movements. Spend three minutes releasing the pec minor, two minutes on the proper stretch, and three minutes on scapular control exercises. This takes about eight minutes total and addresses the issue before it becomes a problem during training. For athletes in overhead sports like volleyball, swimming, and baseball, this protocol should be done daily, not just on training days. The repetitive overhead motion places extreme demand on the pec minor, and cumulative shortening happens quickly. I had a swimmer who trained six days a week, and his pec minor would tighten so severely that his shoulder external rotation decreased by fifteen degrees by the end of each training cycle. Daily maintenance work reduced that loss to about three degrees. For general population clients, two to three times per week is adequate. The pec minor does not require the same frequency of intervention as larger muscle groups because its primary role is postural, not movement based. A consistent but moderate approach yields better long term results than aggressive sporadic treatment.
When Pec Minor Release Is Not The Solution
This approach does not work for everyone, and it is important to recognize when it is not the right intervention. If you have a structural issue such as a congenital scapular anomaly or a previous surgical intervention on the shoulder, pec minor release may provide minimal benefit. If you have a herniated disc in the cervical spine that is referring pain to the shoulder region, working on the pec minor will not address the actual source of the problem. Sometimes the tightness in the pec minor area is actually compensatory tension from a weak rotator cuff. In these cases, the muscle is not the primary problem, and releasing it provides only temporary relief. The correct approach is to strengthen the rotator cuff and improve glenohumeral joint stability first. If you try pec minor release for three weeks and see no improvement in shoulder mechanics, reassess whether the issue is actually originating from the scapulohumeral rhythm or the cervical spine. There is also a scenario where the pec minor is short but not the limiting factor. Some people have adequate pec minor length but still present with poor shoulder posture because of thoracic kyphosis from prolonged sitting. In these cases, addressing the spinal curvature and strengthening the entire posterior chain is more effective than focusing solely on the pec minor. The pec minor may be relatively tight, but it is not the root cause of the postural deviation.
Progress Tracking And Realistic Expectations
Monitor your progress using objective measures rather than subjective feelings of tightness. Track your shoulder external rotation range of motion using a goniometer or a simple smartphone app. Measure your overhead squat depth and arm position. Record your push up form quality and any pain during pressing movements. These metrics provide clearer feedback than whether your shoulder feels less stiff in the morning. Expect to see measurable changes in scapular position within two to three weeks of consistent work. Full remodeling of the tissue and neuromuscular adaptation typically takes eight to twelve weeks. This timeline is consistent with the general principles of myofascial and postural adaptation. Anyone promising permanent results in less than two weeks is not being accurate. The pec minor is an often overlooked muscle that has a disproportionate effect on shoulder health, posture, and athletic performance. It connects the rib cage to the scapula, and when it is tight, it disrupts the entire kinetic chain from the spine to the hand. Understanding its anatomy, learning to release it correctly, and integrating appropriate strengthening and stretching work into your routine is a practical solution to a common problem. The key is consistency, proper technique, and recognizing when the issue extends beyond what soft tissue work can address.