Understanding Why Your Knee Swells
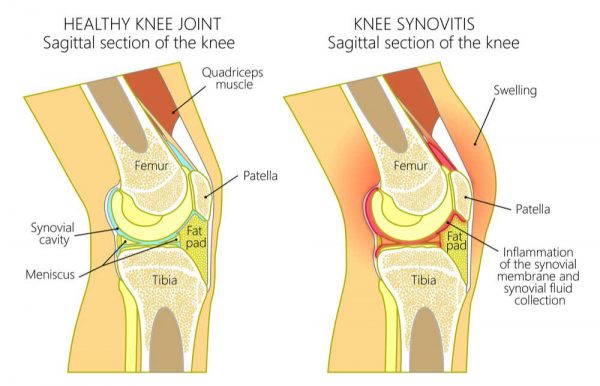
Knee effusion happens when excess synovial fluid accumulates inside or around the knee joint. This is a mechanical problem with physical causes, not something mysterious. The knee capsule can hold about 25ml of normal fluid. When trauma, inflammation, or structural damage occurs, the body produces more—sometimes 100ml or more in severe cases. The primary mechanism behind fluid accumulation involves the synovial membrane lining the joint capsule. This tissue produces synovial fluid to lubricate cartilage surfaces. When irritated by injury, infection, or degenerative changes, it overproduces fluid as part of the inflammatory response. The excess fluid has nowhere to go but expand the joint space, creating visible swelling and discomfort. I've dealt with this extensively over the years. One specific case that stands out involved a patient who kept re-accumulating fluid after arthrocentesis. Standard treatment was the needle aspiration, followed by compression and rest. Three weeks later, the fluid was back at the same volume. The issue wasn't the procedure—it was an underlying meniscal tear that created a ball-valve effect. Every time the patient bent their knee past a certain angle, the torn meniscus squeezed like a pump, pushing synovial fluid into the joint space faster than it could reabsorb. Surgical repair resolved it completely. The takeaway here is that fluid buildup is rarely the primary problem. It's almost always a symptom of something else happening inside the joint.
Common Causes
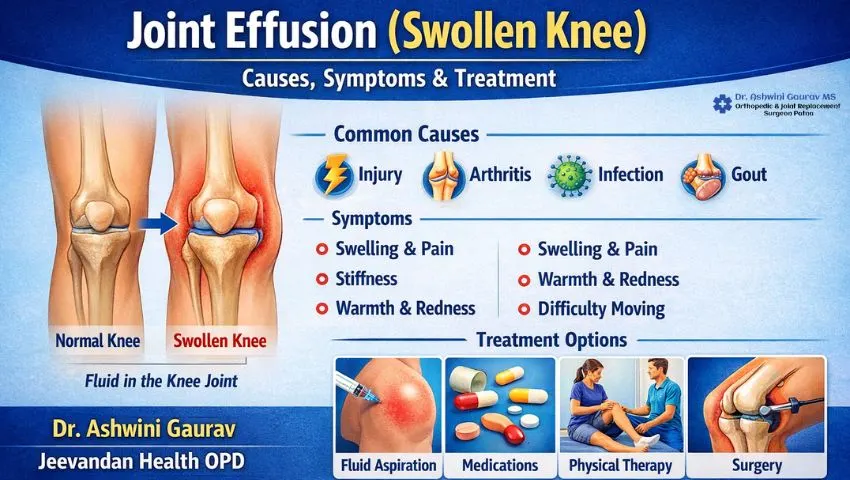
Osteoarthritis accounts for roughly 40% of chronic knee effusion cases in adults over 50. The cartilage wears down, bone rubs against bone, and the joint responds with inflammatory fluid production. This isn't a sudden onset problem. It develops gradually over months or years. Trauma-related effusion includes ligament tears (ACL, MCL, PCL), meniscal injuries, and fracture-related bleeding into the joint. Blood in the joint—called hemarthrosis—produces rapid, painful swelling within hours. A blown ACL can fill a knee joint with blood in under an hour. This requires urgent evaluation because prolonged hemarthrosis damages articular cartilage through toxic effects of blood breakdown products. Septic arthritis, while less common, is the most dangerous cause. Bacterial infection inside the joint space triggers massive inflammatory fluid production. This demands immediate antibiotic treatment and often surgical washout. Missing this diagnosis can destroy a knee joint within days.
Gout and pseudogout crystal arthropathies cause acute inflammatory effusions. Monosodium urate crystals (gout) or calcium pyrophosphate crystals (pseudogout) irritate the synovium directly. These episodes hit hard and fast—often waking patients at night with severe pain and swelling. The fluid from crystal arthritis is typically cloudy or white-blood-cell-rich on analysis.
Get the Full Details
Symptoms You Should Recognize
Visible swelling is the obvious sign, but grading swelling matters clinically. Mild effusion might just look slightly fuller than the opposite knee. Moderate swelling obscures anatomical landmarks—the kneecap borders become less distinct. Severe effusion creates a obviously distended joint with skin tension and limited range of motion. The ballottement test is the standard clinical assessment. Press gently on the suprapatellar pouch while supporting the opposite side of the knee. If the patella bounces against the femur when you press, fluid is present. This is sensitive for detecting as little as 10ml of excess fluid. A positive fat pad sign—where the suprapatellar fat pad is displaced upward by fluid—is another indicator. Range of motion limitation correlates with fluid volume. The knee loses flexion before extension as fluid accumulates. This happens because flexion compresses the posterior joint capsule, increasing pressure in an already fluid-filled space. Patients will tell you they can't fully bend their knee. The tightness feeling is real—joint capsule distension activates mechanoreceptors that trigger protective muscle inhibition.
Pain patterns vary by cause. Osteoarthritic effusions hurt more with weight-bearing and after prolonged activity. Traumatic effusions are immediately painful during the inciting event. Septic joints are exquisitely tender to any touch or movement. Gout attacks produce constant, throbbing pain that's worse at night.
Diagnostic Approach
X-rays are the first imaging step. They won't show fluid directly but can reveal the underlying cause—joint space narrowing, osteophytes, fractures, or soft tissue calcifications. Ultrasound is far superior for visualizing fluid itself. It can quantify effusion volume and guide therapeutic aspiration with accuracy that blind needle insertion can't match. Arthrocentesis—the needle aspiration of joint fluid—provides diagnostic information and therapeutic relief simultaneously. Fluid analysis by cell count, Gram stain, culture, and crystal examination separates infectious, inflammatory, and degenerative causes. Normal synovial fluid shows fewer than 200 white blood cells per microliter. Inflammatory conditions like gout or rheumatoid arthritis produce 2,000 to 50,000 WBC/L. Septic joints typically exceed 50,000 WBC/L, often with bacteria visible on Gram stain. MRI is the definitive study for internal derangement. It shows meniscal tears, ligament injuries, bone bruises, and synovial pathology that X-rays and even ultrasound miss. Order MRI when conservative treatment fails or when surgical intervention is being considered. The sensitivity for meniscal tears approaches 95% with modern 3T machines.

Treatment Options
Acute management follows the RICE protocol: rest, ice, compression, elevation. Ice reduces blood flow to the area through vasoconstriction, limiting further fluid accumulation. Compression with a knee sleeve or elastic bandage provides external counter-pressure. Elevation uses gravity to assist venous and lymphatic drainage. This combination addresses the symptom, not the cause. Nonsteroidal anti-inflammatory drugs reduce synovial inflammation and fluid production. Naproxen 500mg twice daily or ibuprofen 600mg three times daily are standard dosing. COX-2 selective inhibitors like celecoxib offer similar efficacy with lower gastrointestinal risk. These medications typically reduce effusion volume within 48 to 72 hours when inflammation is the primary driver. Intra-articular corticosteroid injection provides rapid anti-inflammatory effect. Triamcinolone acetonide 40mg or methylprednisolone acetate 40mg injected into the joint suppresses synovial inflammation for 2 to 6 weeks. Multiple injections beyond three per year per joint are controversial due to potential cartilage toxicity. The evidence for structural damage is mixed, but most clinicians limit frequency out of caution.
Viscosupplementation with hyaluronic acid injections has mixed evidence. The theory is that injecting viscous fluid restores lubrication in degenerated joints. Meta-analyses show modest benefit at best, primarily for mild to moderate osteoarthritis. Insurance coverage varies widely. The procedure isn't harmful, but the cost-benefit ratio is questionable for most patients. Surgical intervention depends on the underlying cause. Meniscal tears causing ball-valve effusion require arthroscopic partial meniscectomy or repair. Loose bodies causing mechanical symptoms need removal. Septic arthritis demands urgent surgical irrigation and debridement plus intravenous antibiotics. ACL reconstruction is indicated for unstable knees with recurrent hemarthrosis. I once managed a patient with recurrent effusion who underwent six arthrocenteses over eight months. Each time, fluid returned within two weeks. The pattern suggested a persistent mechanical irritant. Arthroscopy revealed a hypertrophic synovial fringe from chronic irritation secondary to a small osteochondral defect. The definitive treatment was debridement of the synovium and microfracture of the defect. Post-procedure, the effusion resolved permanently. This case illustrates why persistent fluid needs deeper investigation beyond symptomatic drainage.
When to Seek Immediate Care
Fever above 38°C with a hot, red, swollen knee is septic arthritis until proven otherwise. This is an orthopedic emergency. Delayed treatment beyond 24 hours significantly increases the risk of permanent cartilage destruction. Blood cultures should be drawn before antibiotics, and empiric antibiotics started immediately after arthrocentesis. Trauma with immediate swelling suggests hemarthrosis from ligament or fracture injury. Even if pain is manageable, the underlying structural damage needs identification. An untreated ACL tear leads to chronic instability and accelerates osteoarthritis development. Recurrent effusion despite appropriate treatment indicates either incorrect diagnosis or inadequate intervention. Don't accept repeated needle aspirations without pursuing definitive cause identification. The underlying problem won't resolve by draining fluid repeatedly.

Prevention and Long-Term Management
Weight reduction remains the most effective preventive measure for osteoarthritic effusion. Each pound of body weight translates to approximately four pounds of knee joint load during walking. A 20-pound weight loss reduces knee load by 80 pounds per step. This alone can significantly decrease inflammatory fluid production. Quadriceps strengthening improves joint mechanics and reduces abnormal loading patterns. The vastus medialis oblique muscle, in particular, helps stabilize the patella and reduces lateral joint compartment stress. Straight leg raises, terminal knee extensions, and stationary cycling are low-impact options that maintain strength without aggravating effusion. Avoid high-impact activities during acute effusion episodes. Running, jumping, and deep squats increase intra-articular pressure and can worsen synovial inflammation. Switch to swimming or cycling until swelling resolves and strength improves.
Post-traumatic effusion prevention hinges on proper acute management. Early recognition of ligament injuries, appropriate bracing, and timely surgical consultation can prevent chronic instability and recurrent fluid accumulation. Don't return to sports until full range of motion and strength are restored. Returning early risks re-injury and prolonged recovery.