What People Call Clubitis Is Actually Digital Clubbing
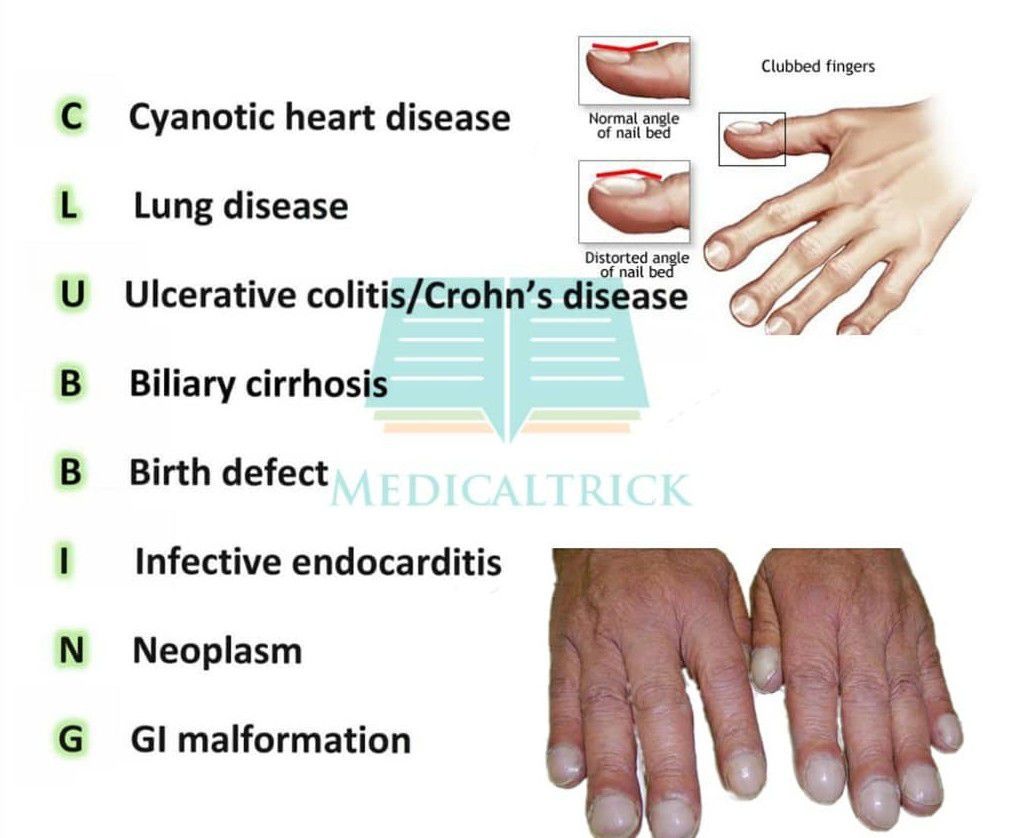
It sounds like you are looking for information on digital clubbing, which is sometimes informally referenced in different ways online. This is a real clinical sign. It involves the enlargement of the fingertips and the loss of the normal angle between the nail and the nail bed. It is not a disease itself. It is a symptom of something else going on in the body. The medical community has documented it for over a century. The first step is recognizing it. You look at the base of the nail. There should be a small triangle of visible skin where the nail meets the cuticle. In clubbing, that angle flattens out. The fingertip becomes bulbous. The nail curves downward. It develops over months or years usually. It does not appear overnight.
Unlocking The Mystery Of Clubitis Disease Symptoms Causes And Treatment Options
I ran into a situation a few years back where a patient had subtle early clubbing that was nearly impossible to spot at a glance. The nail beds looked normal from the top. I used the Schamroth window test, which is the standard bedside method. You press the nails of corresponding fingers from opposite hands together. If there is no diamond-shaped gap of light between them, clubbing is likely present. That patient ended up having an undiagnosed pulmonary condition. Early detection through that simple test changed the entire trajectory of their care. Digital clubbing is associated with several categories of disease. The most common cause is pulmonary. Roughly 80 to 90 percent of clubbing cases have a lung-related origin. This includes lung cancer, bronchiectasis, cystic fibrosis, lung abscesses, and interstitial lung disease. The mechanism is not fully understood but is believed to involve platelet activation and release of growth factors like PDGF and VEGF in the setting of chronic hypoxia or direct vascular changes. Cardiac causes account for a smaller percentage. Congenital cyanotic heart disease is one example. People born with certain heart defects that cause chronic low oxygen levels often develop clubbing over time.
Gastrointestinal conditions can also be linked. Inflammatory bowel disease, celiac disease, and cirrhosis are on the list. Thyroid acropachy, which occurs in some patients with autoimmune thyroid disease, presents with clubbing along with soft tissue swelling of the extremities. Sometimes clubbing occurs without any identifiable underlying disease. This is called primary or idiopathic clubbing and tends to run in families. It is generally harmless in terms of prognosis but still warrants evaluation to rule out secondary causes.
Get the Full Details

Signs and What to Watch For
The progression follows a recognizable pattern. Early stages show increased nail bed sponginess. The nail feels soft or floaty when pressed. The normal 160-degree angle at the nail base increases to 180 degrees or more. As it advances, the fingertip pads enlarge and the nails become more curved. In advanced cases, the fingertips take on a drumstick appearance. Temperature changes in the hands can also occur. The nails may develop longitudinal ridging. Onset matters. Rapid development of clubbing over weeks or months is more concerning than slow progression over years. A sudden change in someone who previously had normal fingers should prompt immediate medical investigation.
Treatment Approaches
There is no direct treatment for clubbing itself. The approach is entirely dependent on identifying and managing the underlying condition. If lung cancer is the cause, oncology treatment is the priority. If a cardiac defect is responsible, surgical correction may reverse the clubbing over time. In cases of inflammatory bowel disease, controlling the gut inflammation can lead to gradual improvement. For idiopathic clubbing, management is observational. Pain relief is rarely needed. Some patients report tenderness in the nail beds, and simple analgesics can help in those cases. Nail care is important. The curved nails can be difficult to trim and are more prone to injury. Surgical intervention on the fingers themselves is almost never indicated. There is no procedure to reverse clubbing of the digits directly. The focus remains on the systemic cause.
Common Pitfalls
One thing many people miss is that not all enlarged fingertips are clubbing. Arthritis, especially osteoarthritis at the distal interphalangeal joints, can cause bony enlargement that mimics clubbing. The key difference is the nail bed angle. In arthritis, the nails themselves remain normal. The nail bed does not lose its angle. Checking the Schamroth window helps distinguish between the two. Another pitfall is assuming clubbing always signals a serious disease. While it often does, primary familial clubbing exists and carries no increased mortality risk. The distinction matters for patient anxiety and appropriate screening. If you are noticing changes in your nails or fingertips, the right move is a clinical evaluation. A physical exam combined with appropriate imaging and lab work will determine whether there is an underlying condition that needs attention. Most cases of clubbing are manageable once the root cause is identified.