Understanding Arrhythmia: What Actually Happens Inside the Heart
The heart has an electrical system. It fires signals in a specific sequence that tells the chambers when to contract. When that sequence gets disrupted, you get an arrhythmia. That is the entire definition. The clinical spectrum is much broader than most people realize, though, and the way these conditions behave in practice is often quite different from textbook descriptions. I have spent years working with ECG interpretation and cardiology diagnostics, and the cases that trip up both patients and clinicians are usually the ones that do not look dramatic on paper. A sinus tachycardia at 110 bpm because someone is anxious about their health. Premature ventricular contractions that feel like flip-flops in the chest but are completely benign in a structurally normal heart. The scary ones tend to be silent until they are not.
Unlocking The Mystery Of Abnormal Heart Rhythms Understanding Arritmia Cardiaca
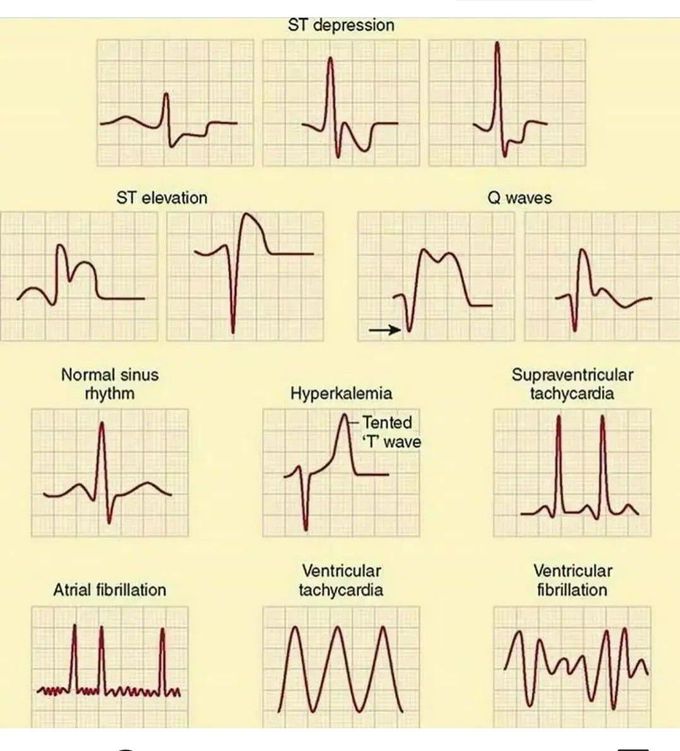
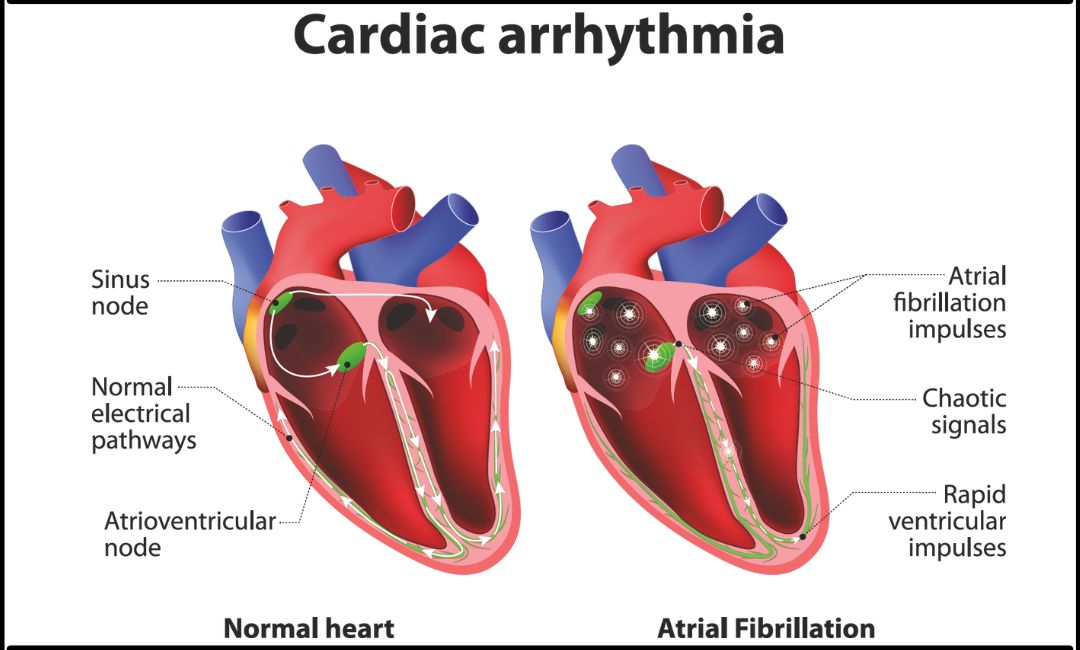
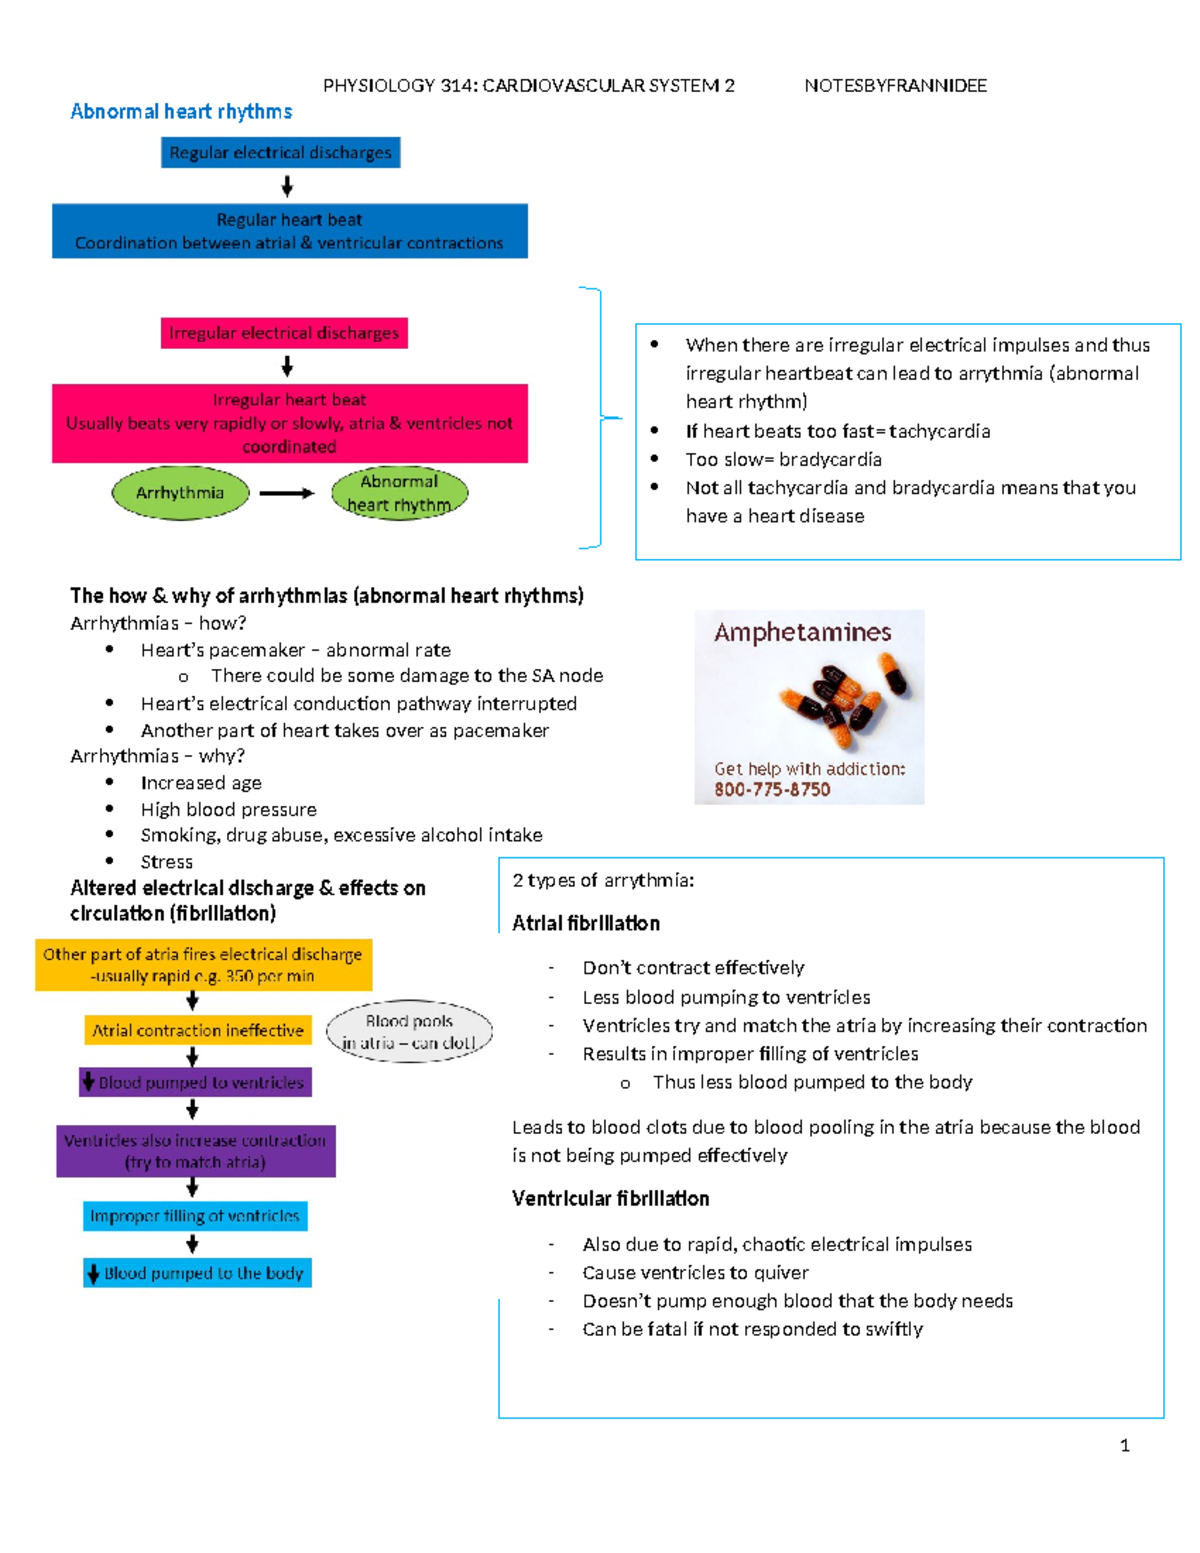
Arritmia cardiaca, or cardiac arrhythmia, covers any condition where the heart beats too fast, too slow, or irregularly. The major categories are atrial fibrillation, atrial flutter, ventricular tachycardia, bradyarrhythmias, and various forms of premature beats. Each has distinct mechanisms, risk profiles, and management pathways that diverge significantly from one another. Atrial fibrillation affects roughly 2% to 3% of the adult population in developed countries. That number climbs to around 10% in people over 80. The mechanism involves chaotic electrical activity in the atria, typically originating from the pulmonary veins. The ventricles respond irregularly because the AV node acts as a filter, conducting some impulses and blocking others at random intervals. This produces the classic irregularly irregular pulse that clinicians look for during a physical exam. Ventricular tachycardia is where things become genuinely dangerous. This originates in the ventricles themselves, usually from scar tissue or diseased myocardium creating re-entry circuits. The heart rate can exceed 150 bpm, and the ventricles do not fill properly because the activation sequence is abnormal. Blood pressure drops. Patients lose consciousness. Sustained VT requires immediate intervention, typically electrical cardioversion or antiarrhythmic medication depending on stability.
Bradyarrhythmias present the opposite problem. The heart rate falls below 60 bpm, and in symptomatic cases the patient experiences fatigue, dizziness, syncope, or exercise intolerance. Complete heart block is a classic example where no electrical signals pass from the atria to the ventricles. The ventricles maintain themselves with an escape rhythm at 30 to 40 bpm, which is barely enough to sustain organ perfusion during activity. One counter-intuitive thing about atrial fibrillation that most people miss is that rate control alone is often as effective as rhythm control for many patients. The AFFIRM trial and subsequent studies showed that maintaining normal sinus rhythm does not necessarily reduce mortality compared to simply controlling the ventricular response. This changed practice significantly. Many patients who would have been put on antiarrhythmic drugs like amiodarone or flecainide are now managed with beta-blockers or calcium channel blockers for rate control, plus anticoagulation based on their CHA2DS2-VASc score. Another nuance that gets overlooked is the concept of tachycardia-induced cardiomyopathy. Prolonged uncontrolled tachycardia, whether from AF with rapid ventricular response or persistent SVT, can weaken the heart muscle over weeks to months. The ejection fraction drops. The heart enlarges. The good news is that this is often reversible once the rhythm is controlled, sometimes within a few months. I have seen patients with an EF of 30% who were put on a defibrillator for primary prevention, only to have their EF recover to 55% after successful ablation. They never needed the device.
Get the Full Details
Diagnosis starts with a 12-lead ECG, but that snapshot only captures a few seconds of cardiac activity. For intermittent arrhythmias, which is the majority of cases outside of permanent AF, you need prolonged monitoring. Holter monitors track 24 to 48 hours. Event monitors can extend to 30 days. Implantable loop recorders last up to three years and are useful when the arrhythmia is infrequent but clinically significant. I ran into a specific edge case recently that illustrates why surface-level diagnosis can be misleading. A patient presented with palpitations and a normal resting ECG. Their Holter was also unremarkable. We eventually diagnosed the issue using an implantable loop recorder over six months, and it turned out to be episodic atrial flutter with 2:1 AV conduction that only occurred during sleep. The flutter waves were buried in the T waves on surface ECG, making it nearly indistinguishable from sinus rhythm during wakeful hours. The workaround was keeping the device implanted long enough to capture an event, then proceeding with catheter ablation, which was curative. The most common pitfall in arrhythmia management is underestimating stroke risk in atrial fibrillation. Anticoagulation decisions should be based on validated scoring systems, not on whether the AF appears paroxysmal or permanent. Paroxysmal AF carries the same thromboembolic risk as persistent AF. I have encountered too many patients who were told they did not need blood thinners because their AF only came and went. That is incorrect guidance.
Treatment options range from lifestyle modification to catheter ablation to surgical Maze procedures. Lifestyle changes matter more than people expect. Alcohol binge drinking can trigger acute AF in susceptible individuals, sometimes called holiday heart syndrome. Obstructive sleep apnea is strongly associated with AF recurrence after ablation. Weight loss of 10% or more has been shown to significantly reduce AF burden. These are not minor recommendations. Catheter ablation has evolved considerably. Pulmonary vein isolation is now the standard for atrial fibrillation, with success rates around 70 to 80% after a single procedure for paroxysmal AF. For persistent AF, the success rate drops to roughly 50 to 60%, and multiple procedures are sometimes needed. Complication rates are low but real, including cardiac tamponade, stroke, pulmonary vein stenosis, and atrioesophageal fistula, which is rare but almost universally fatal. Antiarrhythmic drug therapy carries its own trade-offs. Class IC agents like flecainide and propafenone are effective for structurally normal hearts but are contraindicated in coronary artery disease due to proarrhythmic risk. Amiodarone is highly effective but has substantial extracardiac toxicity, including pulmonary fibrosis, thyroid dysfunction, hepatic toxicity, and corneal deposits. It is usually reserved for patients who have failed other treatments or who have significant structural heart disease.
Sick sinus syndrome represents another category that deserves attention, particularly in older adults. The sinus node fails to fire appropriately, causing alternating bradycardia and tachycardia, sometimes referred to as tachy-brady syndrome. These patients often cannot tolerate beta-blockers or calcium channel blockers because their baseline rate is already too low. The definitive treatment is a permanent pacemaker, often combined with medication for rate or rhythm control once the underlying bradycardia is addressed. Long QT syndrome and other inherited channelopathies require a different approach entirely. These are genetic conditions that predispose patients to malignant ventricular arrhythmias. Diagnosis involves genetic testing and specialized ECG analysis. Treatment includes beta-blockers, implantable cardioverter-defibrillators, and in some cases left cardiac sympathetic denervation. The prognosis has improved dramatically with modern ICD technology, but these patients need lifelong specialist follow-up. The bottom line is that arrhythmias are not a single condition. They span a wide spectrum from benign and self-limiting to immediately life-threatening. Proper evaluation requires careful clinical assessment, appropriate diagnostic testing, and recognition that guidelines have evolved significantly in recent years. The old instinct to restore sinus rhythm at all costs in atrial fibrillation is no longer supported by evidence for most patients. Rate control plus stroke prevention is often the safer and equally effective strategy.