Getting Actual Precision Out of Cardiac Feature Labeling
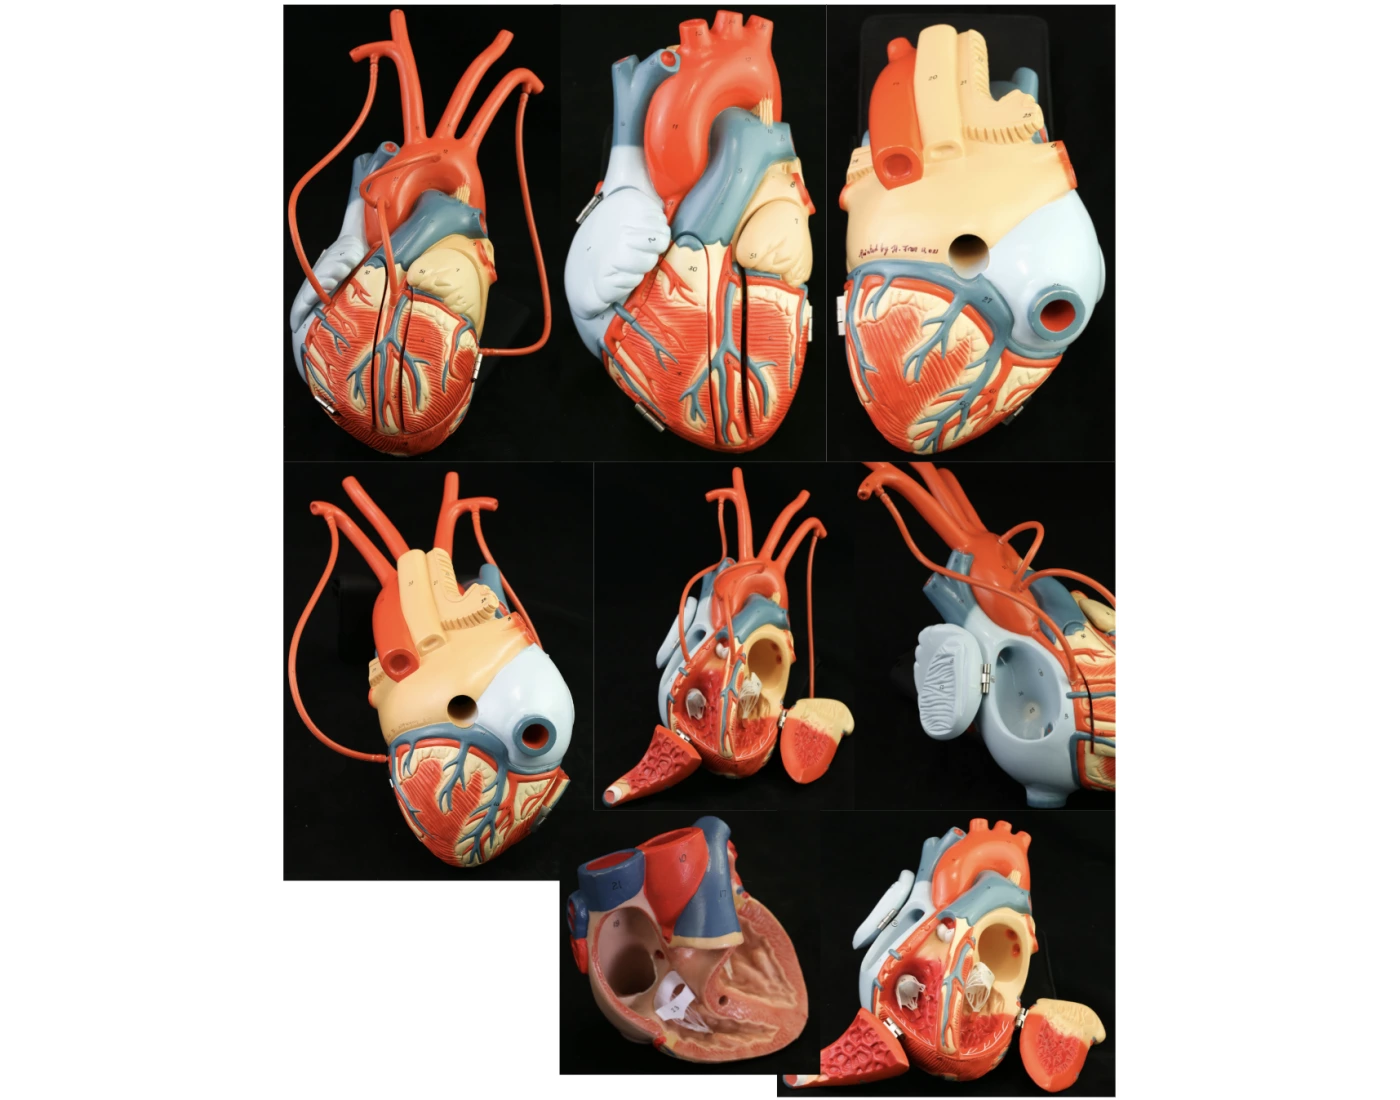
Cardiac image annotation is not a simple task. You take a stack of 2D slices from an MRI or echo study and you need to draw contours around chambers, valves, and vessels that shift position from frame to frame. The images themselves are noisy. The contrast is poor. Different scanners produce different signal characteristics. Doing this right requires patience and a structured approach. Here is how the actual workflow goes when you are building a labeled dataset for model training or clinical analysis. You have a few options depending on your budget and time constraints.
ITK-SNAP is free, runs on Windows and Linux, and handles NIfTI and DICOM files well. It has semi-automated region-growing that saves time but requires manual correction anyway. 3D Slicer gives you more control over multi-planar reconstruction and annotation tools. LabelMe is lightweight and good for quick polygon-based labeling if you are working with individual frames rather than full volumes. For clinical-grade work where you need pixel-level accuracy, CVAT or Segment Anything Model fine-tuned on cardiac data can give you a starting point, but human verification is still mandatory.
The Workflow
Start by organizing your data. DICOM studies should be converted to NIfTI format using tools like dcm2niix before you begin labeling. This gives you a single volumetric file that most annotation platforms can read. Keep the original DICOM archives backed up somewhere separate. You will need them for audit trails. Define your label schema first. You need to decide exactly which structures you are labeling before you open any image. Common classes include the left ventricle blood pool, left ventricular myocardium, right ventricle, left atrium, right atrium, aorta, and pulmonary artery. Be specific. Do not create a catch-all class called "heart tissue." Your models will thank you later, or your clinical colleagues will. Label in short sessions. Two hours of concentrated contour drawing is the practical maximum before fatigue introduces errors. I used to push through four-hour blocks and missed things. A trabeculation detail here, a papillary muscle misclassified as wall there. After about hour two, your eye stops catching these mistakes.
Get the Full Details

A Real Problem I Ran Into
Last year I was annotating a dataset of cardiac MRI scans from a population with significant arrhythmia. The R-R intervals varied too much between beats, which meant end-diastolic and end-systolic frames were not consistent across patients. The standard protocol says label at end-diastole and end-systole, but when the patient has atrial fibrillation, those phases drift. I spent three days trying to force the labels into a rigid timing framework and kept getting misaligned contours. The workaround was to abandon fixed-frame labeling and instead annotate based on the actual volume measurement at each phase. I pulled the time-series data from the PACS system, identified the frames with minimum and maximum LV volumes visually, and labeled those regardless of whether they matched the textbook phase definitions. It added about twenty minutes per case but the resulting annotations were clinically accurate. If you are building a training set for any downstream model, accuracy at the frame level matters more than following a rigid protocol blindly.
Quality Control
You cannot skip this step. Every labeled study needs at least one independent review. Ideally a second annotator who did not see the first pass. Compare the contours and measure the Dice similarity coefficient between them. If it drops below 0.85 for any major structure, resample that case and re-label together. For inter-observer agreement studies, you calculate the Dice score and intraclass correlation coefficient separately for each structure. Left ventricle endocardial contours typically achieve Dice scores around 0.90 to 0.95 between experienced annotators. Myocardial contours are harder, usually landing around 0.82 to 0.88 because the epicardial boundary is less distinct, especially in older patients with pericardial fat. Right ventricular labels are the worst, often 0.75 to 0.82, because the RV has a more irregular shape and the papillary muscles make the boundary ambiguous.
Common Pitfalls
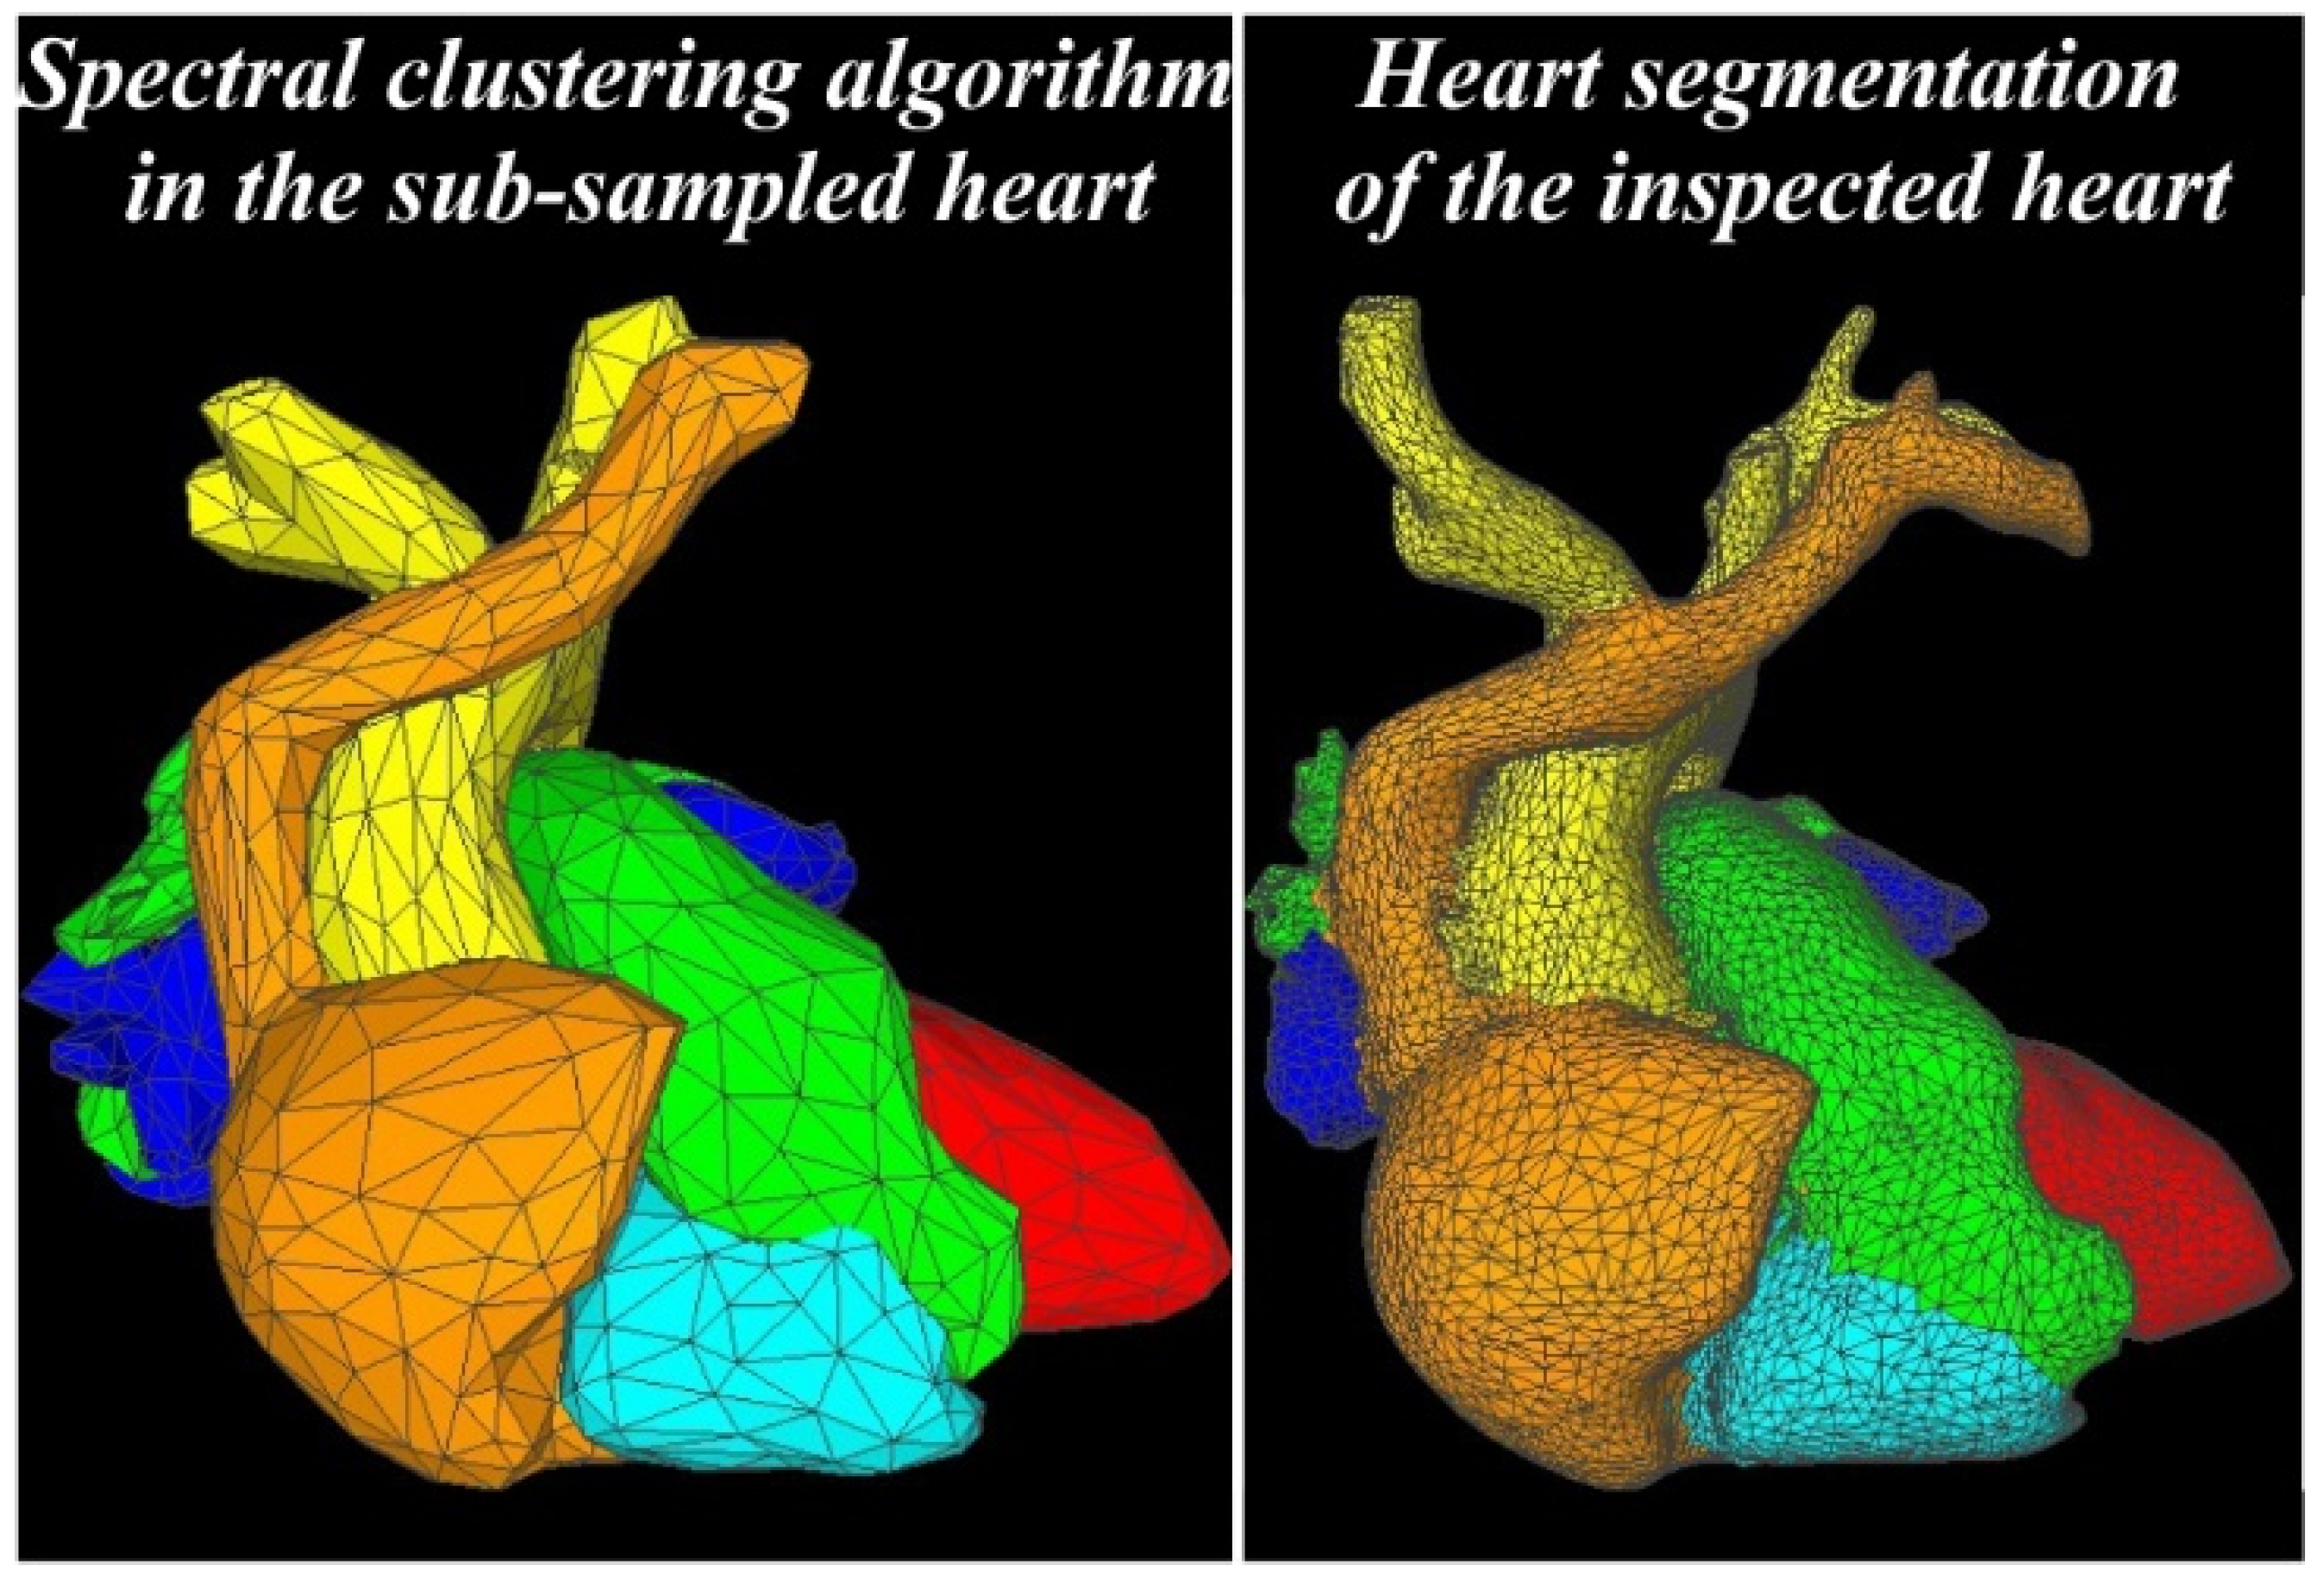
The most frequent mistake is inconsistent inclusion of the papillary muscles. Some annotators include them in the blood pool, some in the myocardium, and some exclude them entirely. This variation propagates directly into your model outputs. Pick one convention and document it explicitly in your methods section. If you are using the data for clinical decision support, include the papillary muscles in the blood pool. That matches how radiologists measure LV volumes in practice. Another pitfall is slicing direction confusion. Short-axis views are standard for LV quantification, but longitudinal and three-chamber views contain different anatomical information. Mixing slice orientations without clear labeling in your dataset metadata causes models to learn orientation-dependent features that fail on real data. Tag every annotation with the view type and slice orientation. Boundary ambiguity at the base of the heart is a persistent issue. The mitral valve plane is not always visible. Different annotators draw it in different places, which shifts the entire LV volume calculation. The American Society of Echocardiography has guidelines on this, but they are not always followed in dataset documentation. State clearly where you placed the mitral annulus plane.
Downsides and Where This Breaks Down
Manual cardiac annotation is slow. A single trained annotator can produce roughly 8 to 12 fully labeled cardiac MRI studies per day, including quality checks. That is about 150 to 200 slices per study, so you are looking at approximately 15 to 25 seconds per slice of actual contour drawing time, plus overhead for navigation and review. For a dataset of 1,000 studies, you are looking at two to three months of full-time work from one person. The quality of your labels is only as good as the annotator's expertise. A cardiology fellow or a cardiac sonographer will produce significantly better myocardial contours than a general radiology resident. Domain-specific training matters more than generic annotation tool experience. I have seen datasets produced by annotators with no cardiac imaging background where the RV outflow tract was consistently mislabeled as the aorta. The model trained on that data failed in production immediately. If you need large-scale labeling quickly, consider using a foundation model like SAM 2 or a fine-tuned U-Net as a pre-labeling step. These can generate initial contours in seconds rather than minutes per slice. The trade-off is that you still need expert review to catch systematic errors, and the automated outputs tend to smooth over small anatomical details that matter for certain applications. For a segmentation model that needs to detect subtle wall motion abnormalities, the pre-labeled contours from an automated tool may miss thinning regions that a human would catch.
Documentation
Write down everything. Annotation guidelines, software versions, DICOM conversion parameters, inter-observer agreement statistics, and exclusion criteria. If you are publishing or sharing the dataset, this documentation is what separates a useful resource from something nobody trusts. The MIM-C dataset papers and the ACDC challenge materials are reasonable examples of how thorough documentation should look. Pick a naming convention for your label files and stick to it. JSON, TIFF masks, or NIfTI label volumes all work. Just make sure every mask matches its source image spatially. I have lost count of the times I found a 1-pixel shift between the label and the source because the coordinate system was not properly aligned during conversion. The model learns that shift as a feature and then fails on any data that does not have the same offset. This is the practical reality of cardiac feature labeling. It is tedious, it requires domain knowledge, and it does not scale well without automation assistance. But the output is foundational for anything that depends on it, whether that is a diagnostic algorithm, a surgical planning tool, or a research study. Getting it right matters.