What The Coronoid Process Actually Is
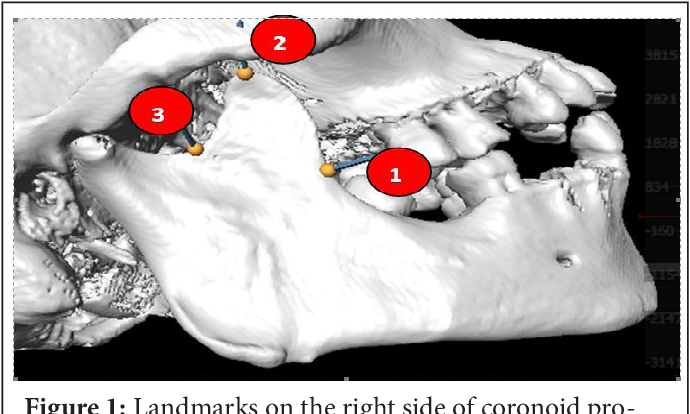
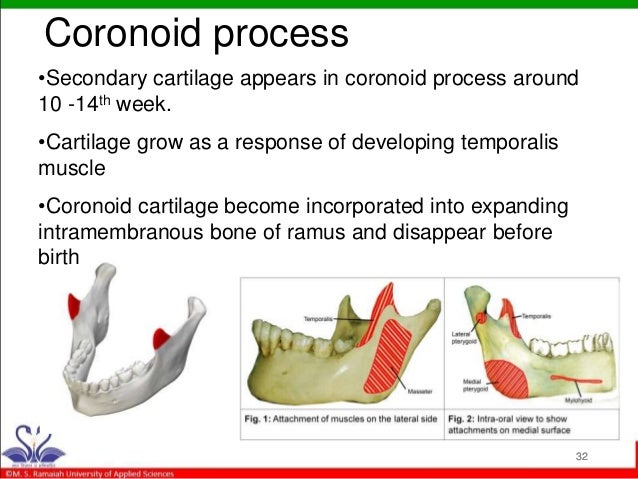
The coronoid process is a triangular projection on the anterior border of the mandibular ramus. It serves as the attachment point for the temporalis muscle, which is the primary elevator of the jaw. Most dental students learn this in anatomy class and move on. But if you're dealing with it clinically—especially during procedures involving the posterior maxilla or TMJ work—you'll find that this structure shows up in ways that aren't covered in textbooks. I first really noticed the coronoid process when I started doing more sinus augmentation cases. During a routine CT scan review, I saw that one patient had an unusually elongated coronoid process jutting toward the zygomatic arch. It wasn't causing symptoms at the time, but it changed my approach to implant placement in the posterior maxilla. The proximity altered the angle I needed for drilling. Ignoring it would have been careless. Here's what most sources don't emphasize: the coronoid process varies dramatically in shape and size between individuals. Some people have a short, blunt projection. Others have a long, slender one that can nearly articulate with the zygomatic arch. This variation is largely genetic and doesn't correlate with age, sex, or occlusion in any predictable way. You can't estimate it from extraoral landmarks either. The only reliable way to assess it is through CBCT imaging.
In practice, an elongated coronoid process can limit mouth opening. I've seen patients with trismus where the culprit turned out to be coronoid impingement against the zygomatic arch. These patients might open to 20 or 25 millimeters and then hit a hard stop. It's not muscular. It's mechanical. The coronoid literally bumps into the arch and blocks further opening. Treating this requires a coronoidectomy, which is a straightforward procedure but one that general dentists rarely perform. Usually, you'd refer to an oral surgeon for that. Another thing that catches people off guard is the relationship between the coronoid process and the pterygomandibular raphe. The deep temporal fascia blends with the lateral pterygoid plate, and the temporalis tendon inserts broadly across the medial surface of the coronoid process. When you're administering an inferior alveolar nerve block, your needle path passes near this area. If the coronoid process is hypertrophied, it can alter the anatomical landmarks you're using. I've had cases where the standardIANB technique missed the target because the coronoid was sitting higher and more anterior than expected, effectively shielding the mandibular foramen from the usual needle trajectory. The workaround was simple: I dropped the injection point slightly and redirected the needle more posteriorly and medially. Sometimes you need to rely less on surface anatomy and more on depth and angulation adjustments. Coronoid hyperplasia is rare but worth knowing about. It presents as progressive, painless limitation of mouth opening, usually bilaterally. It's more common in Asian populations according to the literature, though I've seen it in patients of all backgrounds. The diagnosis is confirmed on CBCT, and the treatment is bilateral coronoidectomy with good outcomes in the majority of cases. Post-surgical mouth opening typically improves to normal range within a few weeks.
If you're a dental student or early-career clinician, don't skip the CBCT when you're planning complex cases in the posterior jaws. The coronoid process might be the difference between a smooth surgery and an unexpected complication. It's a small structure that demands attention.
Get the Full Details