How Ambulatory Referrals Actually Work in Practice
An ambulatory referral is when your primary care doctor sends you to see a specialist for non-emergency care. That part is straightforward. The reality of how these function inside insurance networks, prior authorization systems, and hospital workflows is much messier. I spent years working on the administrative side of healthcare transitions, and the number one complaint I hear from patients is not that they don't understand the concept. It is that the system seems designed to lose your referral somewhere between the moment it is written and the moment the specialist's office confirms receipt.
Unlocking The Meaning Of Ambulatory Referral Your Guide To Navigating The Healthcare System
Here is the basic structure. You have a health issue that requires more expertise than your primary provider can offer. They write a referral or order for specialty consultation. That document travels to the specialist's office, often through a claims clearance house or an EHR portal like Epic's FollowMyHealth or Cerner's HealtheLife. The specialist's staff checks whether the referral meets their requirements before scheduling. Those requirements vary wildly by practice. Some offices want a full clinical summary. Some want recent imaging reports already on file. Some will not accept a referral without documentation that you attempted conservative treatment first. This last point catches people off guard frequently. For physical therapy cases, many orthopedic specialists require at least six weeks of documented PT before they will see you for surgical consultation. If your referring doctor skips that step, your referral bounces. You lose two to four weeks resetting the process.
The Prior Authorization Layer
This is where most referrals stall out. A referral and a prior authorization are not the same thing. The referral is the clinical handoff. The prior authorization is the insurance company's permission slip. Many plans require both before a specialist visit gets covered. I once watched a referral for a dermatology oncology consult get stuck in prior auth limbo for eleven days because the specialist's office submitted the wrong CPT code on the authorization form. They used a consultation code instead of the evaluation and management code the plan required. The plan rejected it on first pass. The office resubmitted with corrected documentation on day seven. By day eleven, the patient had given up and gone to an out-of-network provider. The workaround here is simple but most people skip it. Call the insurance company directly after the referral is sent and ask for the authorization number. Do not ask the specialist's office to do this. Their staff is juggling thirty calls an hour. If you get the authorization number yourself, you can track the status and follow up directly with the insurer if it stalls.
Get the Full Details
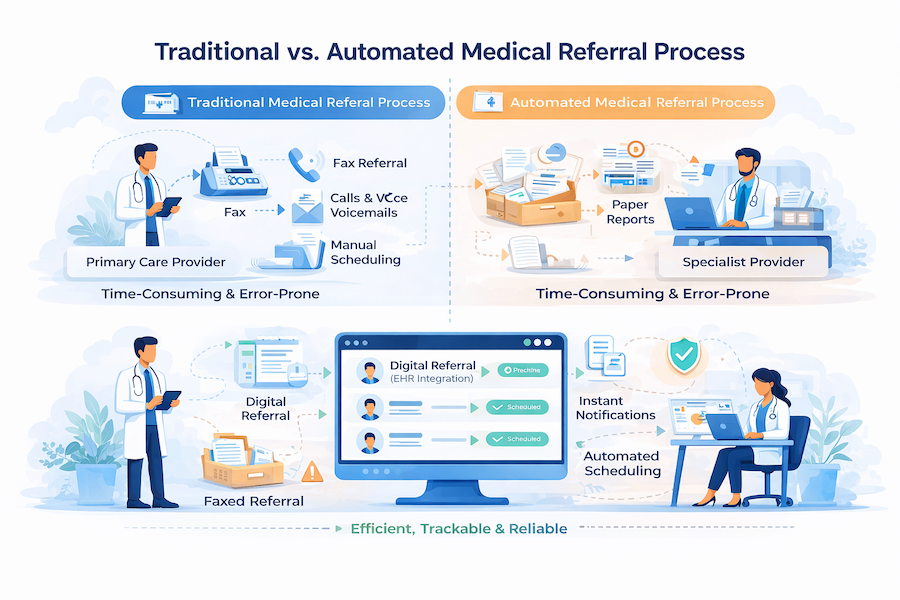
What Actually Happens After You Submit the Referral
Step one is confirming the specialist accepts new patients with your insurance plan. This sounds obvious. Most people skip it. They get referred to a cardiologist who does not take their specific PPO tier. The referral goes to a scheduler who discovers the problem two weeks later. You have wasted two weeks. You start over with a different specialist and your referring doctor has to rewrite the referral. Step two is making sure your primary doctor's office transmits supporting documentation. A referral alone is often insufficient. The specialist needs your medication list, your relevant lab results from the last twelve months, and any imaging reports. Without these, the specialist either requests them directly or declines to schedule you until they arrive. This adds three to five business days to the timeline. Step three is calling the specialist's office yourself once you receive a confirmation number. Their intake systems are automated and understaffed. Automated confirmations sometimes go out for referrals that were never actually reviewed by a human. I found this out the hard way when a patient showed up for an appointment that was never on the doctor's calendar. The system had auto-generated a confirmation email based on the referral intake form. When I checked the actual scheduling system, the patient had no appointment. We lost twenty minutes scrambling to reschedule.
Common Pitfalls That Nobody Warns You About
Insurance plans often require referrals to be renewed annually or within a specific timeframe. A referral written in January may expire by September depending on the plan terms. If you are seeing the specialist months after the original referral, call your primary care office to confirm it is still active. Some plans auto-renew. Some do not. The only way to know is to check. Another issue involves narrow network plans. Your insurance might technically cover the specialist, but the specialist may be out of network for your specific plan variant. Blue Cross Blue Shield PPO is different from BCBS HMO. Aetna Choice is different from Aetna POS. People assume their insurance works everywhere within the network. It does not. Always verify the exact plan type matches the specialist's contracted network before showing up.
When Referrals Fall Apart and What to Do
Sometimes the specialist declines the referral. This happens for several reasons. The specialist may not treat the condition you have. The referral may lack required documentation. The specialist's practice may not be accepting new patients. The insurance authorization may have been denied. When this happens, ask your referring doctor's office for the specific reason. Do not accept a vague answer. If the specialty clinic declined because of missing documentation, ask your primary doctor to send it again. If the clinic does not treat your condition, ask for a referral to a different specialist who does. If the insurance authorization was denied, request a peer-to-peer review. This is where your doctor speaks directly with the insurance company's medical director to justify the need for specialty care. Peer-to-peer reviews succeed about forty percent of the time based on the data I saw working in utilization management. If all else fails and you need care urgently, ask your primary doctor for a case management referral through your insurance company's member services line. This bypasses the standard referral process and routes your case to a dedicated nurse case manager who can expedite specialty access. It works best for time-sensitive conditions like suspected cardiac issues, neurological symptoms, or progressive joint damage.
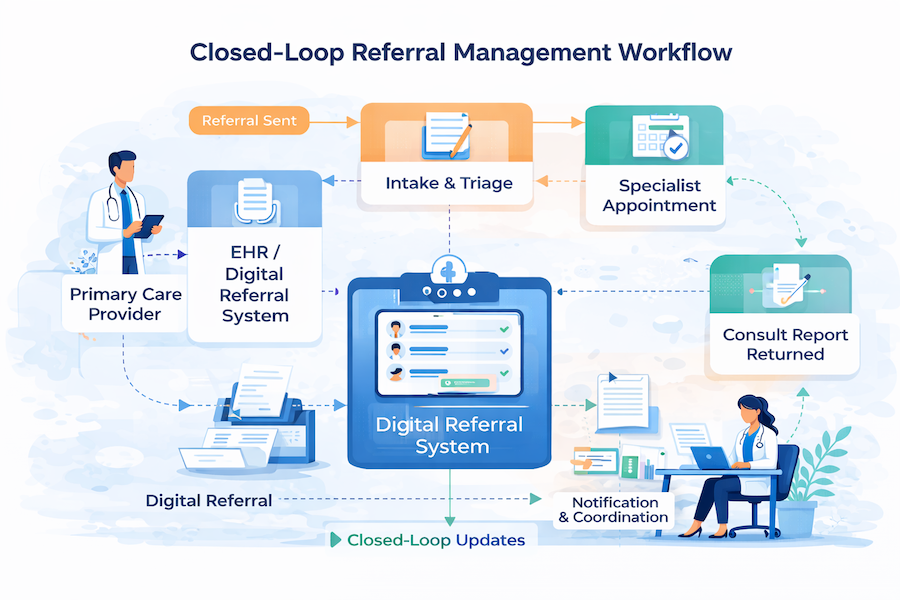
The Bottom Line on Navigating This Process
Ambulatory referrals are functional but fragile. They depend on multiple parties coordinating correctly: your primary doctor, the specialist's office, the insurance company, and you. When any single link fails, the whole chain breaks. The system assumes you will catch errors. It does not have staff available to catch them for you. Keep records of every call. Note the date, the representative's name, the reference number, and what was said. Save copies of your referral documents. Follow up proactively rather than reactively. Most delays are recoverable if you catch them within the first week. Most delays become catastrophic if you ignore them for three weeks or more. The process usually takes between two and six weeks from referral written to first specialist appointment if everything goes smoothly. If something goes wrong, it can stretch to three to four months. The difference is almost always how early and how consistently you track the status yourself.