Understanding What Actually Happens Inside Your Kidneys
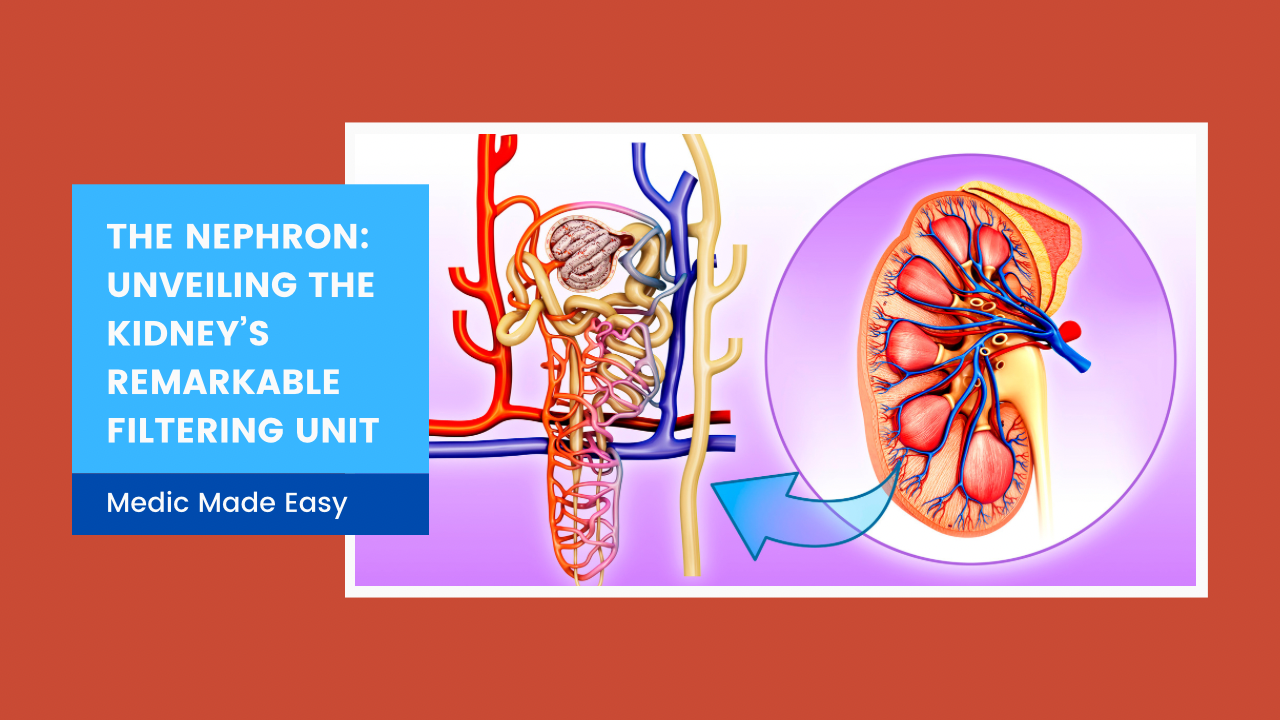
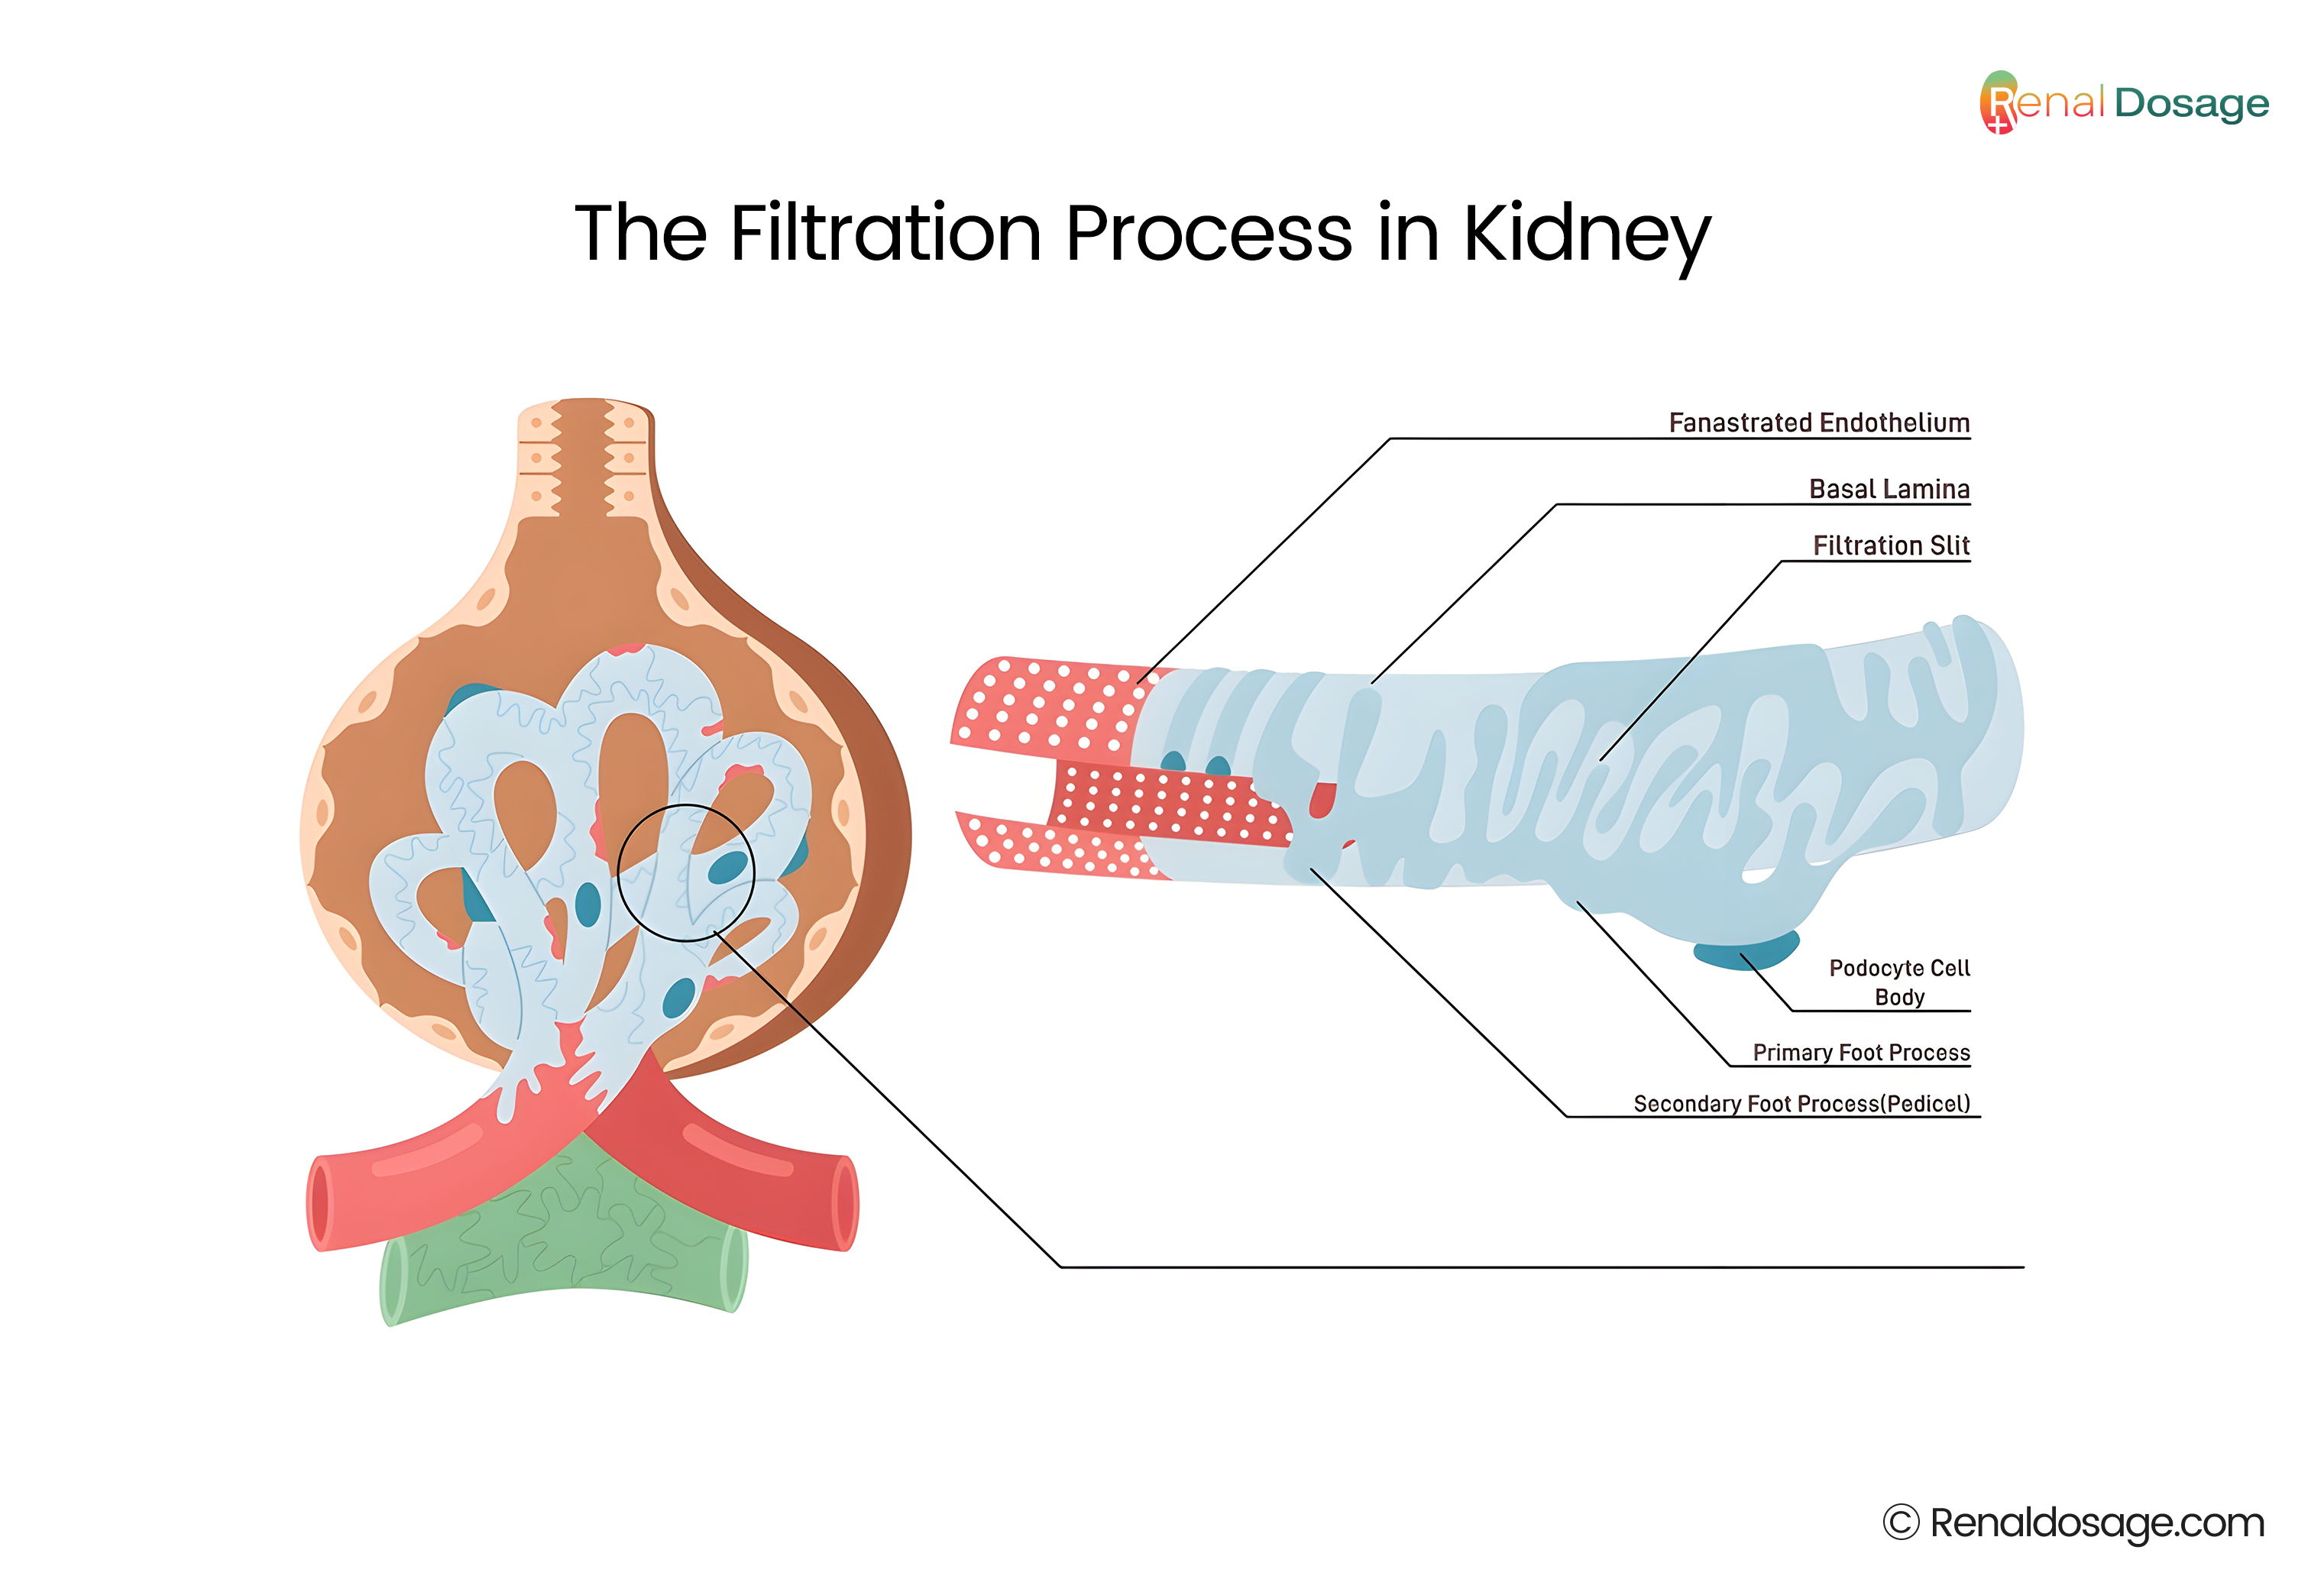
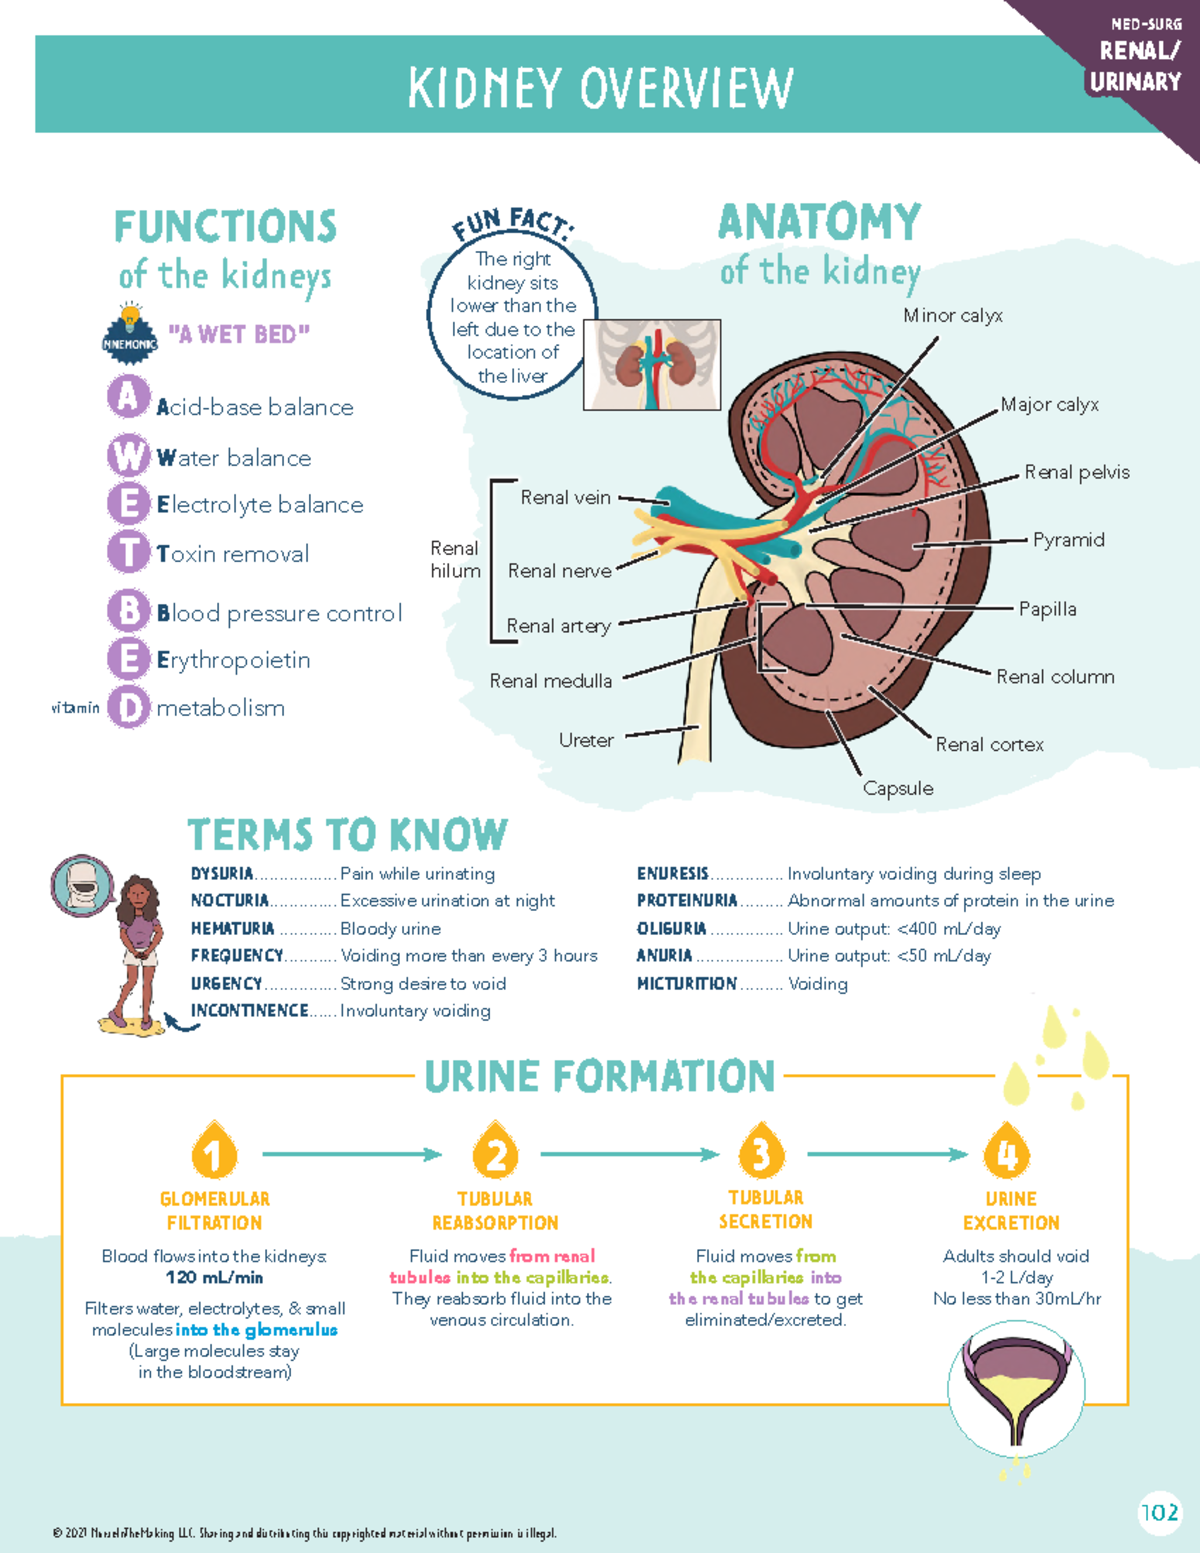
The kidney's basic working unit is the nephron. Each one contains a glomerulus, which acts as the initial filter, and a tubule system that reclaims what your body needs while letting waste continue toward the bladder. You have roughly one million of these per kidney. They run continuously, filtering about 180 liters of blood plasma every single day under normal conditions. Most of that water and useful solutes get reabsorbed. The rest becomes urine. When people talk about "unlocking" or optimizing this, they're usually referring to supporting the nephron's filtration efficiency and the tubular reabsorption machinery. The medical reality is less exciting than the phrasing suggests, but there are concrete, evidence-based ways to keep the system running well. Hydration status matters most for glomerular filtration rate, or GFR. When you're chronically low on water, your body releases antidiuretic hormone and constricts the afferent arterioles feeding the glomerulus. That drops the filtration pressure. You don't need to chug gallons. Consistent, moderate fluid intake throughout the day keeps things moving. I've seen patients who thought they were drinking enough because they had one large glass in the morning, then nothing until dinner. Their urine was concentrated all afternoon. That's not hydration, that's a daily cycle of mild stress on the filters.
Blood pressure control is non-negotiable for long-term nephron health. High intraglomerular pressure over years causes sclerosis, which is basically scarring of the filtering unit. Once a nephron scars, it doesn't come back. ACE inhibitors and ARBs are often prescribed not just for blood pressure but because they specifically reduce that internal filtering pressure. That's why kidney specialists prioritize them in proteinuric patients.
What Actually Damages Nephrons Over Time
Uncontrolled diabetes is the leading cause of chronic kidney disease. High blood glucose damages the tiny blood vessels in the glomeruli. It also causes the mesangium, the supportive tissue inside the filter, to thicken abnormally. This reduces the surface area available for filtration. Over a decade or two, that process is cumulative and generally irreversible at the individual nephron level. NSAIDs are another common quiet damage source. Ibuprofen, naproxen, and similar drugs block prostaglandins that keep the afferent arteriole dilated. In healthy people drinking normally, occasional use is fine. In someone who is volume-depleted or already has reduced kidney function, regular NSAID use can cause acute injury or accelerate chronic decline. I had a patient in his sixties who took naproxen daily for knee pain and came in with elevated creatinine. He assumed his kidneys were fine because he felt normal. They weren't. Stopping the NSAID and adjusting his other medications brought his labs back toward baseline within weeks.
Get the Full Details
Practical Steps That Actually Move the Needle
Keep sodium intake reasonable. Excess salt raises blood pressure and forces the kidneys to work harder to excrete it. Aim for under 2,300 milligrams daily unless your doctor has given you a different target. Manage blood sugar if you have prediabetes or diabetes. Even modest improvements in HbA1c significantly slow kidney damage progression. This is one of the few interventions where early action really changes the trajectory. Avoid high-dose supplements marketed as kidney cleanses. There's no credible evidence that any herbal protocol improves nephron function. Some can actually be harmful. Creatinine-based pre-workout blends and certain weight-loss supplements have been linked to acute kidney injury in case reports. Stick to what you actually need.
Get periodic screening if you're at risk. A simple serum creatinine test gives you an eGFR number. Urine albumin-to-creatinine ratio catches early protein leakage before symptoms appear. These are cheap, routine tests that catch problems when they're still reversible or at least manageable.
When the System Fails
Nephron loss is permanent. The remaining nephrons hypertrophy and compensate, which works for a while but eventually leads to further scarring. This is called glomerulosclerosis, and it's a self-perpetuating cycle. Once eGFR drops below 30, the compensation mechanism starts failing faster than it can maintain function. Dialysis or transplant becomes the only option at that stage. That's why catching issues early matters so much. Sometimes the problem isn't the nephron itself but the downstream plumbing. Kidney stones, an enlarged prostate, or ureteral strictures can cause obstruction that backs up pressure into the filtering units. This type of damage is often reversible if treated promptly, but it's easily missed because blood work can look normal until obstruction is significant. Flank pain, changes in urine stream, and unexplained nausea are clues worth taking seriously.

The Bottom Line Without the Fluff
Your nephrons filter blood continuously. They don't need supplements, teas, or special devices. They need stable blood pressure, controlled blood sugar, adequate hydration, and avoidance of known toxins like chronic high-dose NSAIDs. The best thing you can do is keep your annual physical, get your labs checked, and treat the conditions that slowly wear them down. Everything else is noise.