Nephron Labeled Mapping: What It Actually Is and Why Most People Skip It
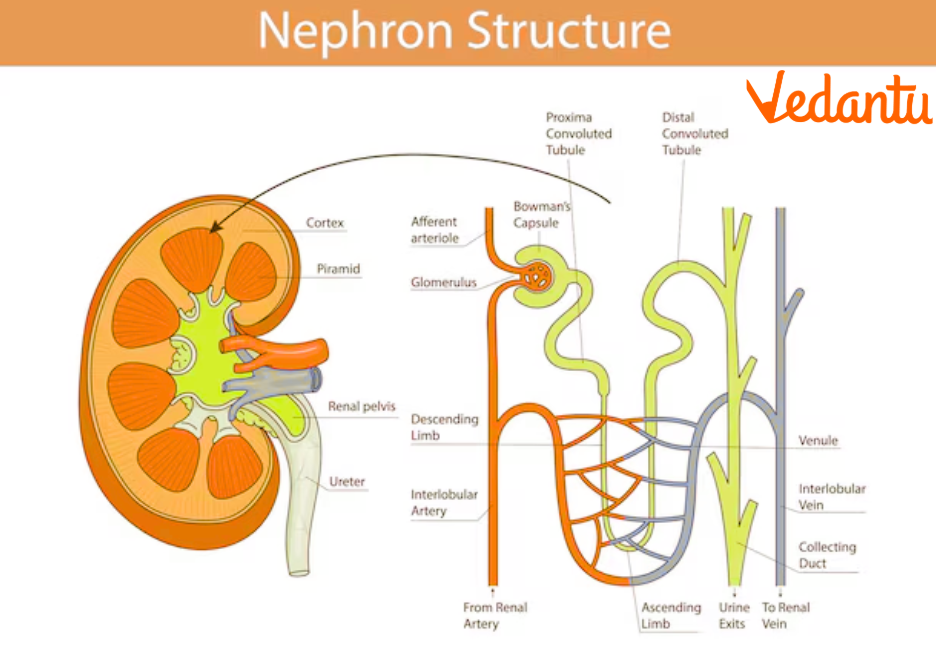
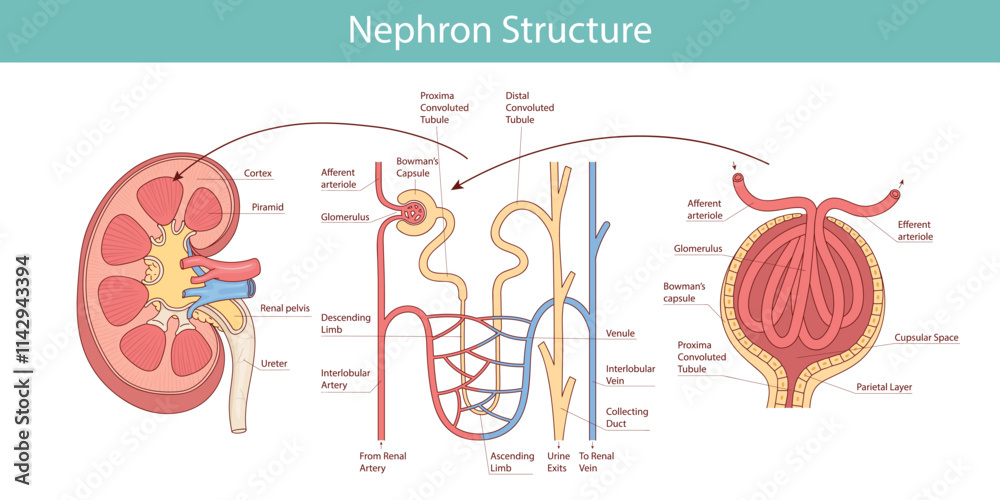
I started working with kidney tissue labeling about six years ago in a renal pathology lab. We were trying to map out how different segments of the nephron respond to ischemic injury at single-cell resolution. What we found changed how we approach disease modeling entirely. The method isn't fancy. It's labor-intensive, yes, but it reveals structural patterns that standard histology completely misses. Nephron labeled mapping is the process of tagging specific nephron segments—proximal convoluted tubule, loop of Henle, distal convoluted tubule, collecting duct—with molecular markers or fluorescent dyes, then reconstructing their spatial relationships across whole-kidney or segmented tissue samples. The result is a structured map that shows exactly which segments are damaged, which are compensating, and which show early signs of recovery. Without this level of segmentation, you're just looking at a blob of pink and purple under H&E stain. Useful for broad patterns, but you can't track individual nephron behavior. The basic workflow runs like this: fix the tissue, run a panel of segment-specific markers, image with confocal or slide-scanning microscopy, register the images to a reference atlas, and then annotate each labeled segment manually or through automated segmentation tools. The annotation step is where most people stall out.
Unlocking The Kidneys Blueprint How Nephron Labeled Mapping Illuminates Disease And Recovery
I want to get into the actual mechanics because there's a gap between reading a paper on this and doing it in a real lab. The first thing you need to nail down is your marker panel. You can't label everything at once. Antibody cross-reactivity in kidney tissue is a real problem, especially when you're working with paraffin-embedded samples that have been through multiple antigen retrieval steps. For proximal tubules, lotus tetragonolobus lectin (LTL) or Kim-1 works well. Distal tubules respond to calbindin-D28k and Na-K-ATPase staining. Collecting ducts are best identified with CD44 or aquaporin-2. The loop of Henle is the stubborn one—thin limbs don't pick up many standard markers cleanly. I've seen people use Rhce transporter antibodies, but the signal-to-noise ratio is poor unless you're starting with fresh frozen tissue. Here's the practical part most protocol papers leave out: tissue thickness matters enormously. If you're cutting sections thicker than 6 microns, your z-axis overlap between adjacent tubules will trash your segmentation algorithm. Six microns is the ceiling. Four is better. You lose some structural context but your registration accuracy improves dramatically.
I ran into a specific problem last year that I still think about. We were mapping nephron recovery after acute kidney injury in a murine model, and the labeled segments kept showing up fragmented during the registration step. The software was splitting single tubules into multiple disconnected regions because the autofluorescence from red blood cells in peritubular capillaries was creating false edges. The standard solution would have been to add a more aggressive bleaching step, but that degraded our fluorescent markers too much. What actually worked was switching from a confocal setup to a spinning-disk confocal with a lower laser power and longer exposure times. The reduced photobleaching meant we could keep the fluorophores intact while still getting optical sections thin enough to register properly. It added about twenty minutes per sample, but the data quality difference was night and day. We went from roughly 40 percent of segments misaligned to about 8 percent. That's not a small gap when you're quantifying recovery rates. Another thing nobody warns you about is the reference atlas problem. Most published nephron atlases are built from mouse C57BL/6 kidneys. If you're working with a different strain, or worse, human tissue, the anatomical variance can throw off your entire registration. Human kidneys vary significantly in cortical thickness and medullary ray organization between individuals. I've seen registration pipelines fail completely on specimens from older donors simply because the atlas didn't account for age-related medullary fibrosis altering the spatial layout.
Get the Full Details

The workaround I use now is to build a local reference from at least three healthy control samples in each batch rather than relying solely on a published atlas. You spend an extra day or two on manual landmark identification, but once you have that baseline, subsequent samples register in minutes instead of hours. When it comes to actually interpreting the maps for disease and recovery, the key metric most people overlook is segmental compensatory hypertrophy. After injury, surviving nephron segments often enlarge to take on additional reabsorptive load. If you only count damaged segments, you'll miss the adaptive response that's actually driving functional recovery. I always calculate a compensation index by comparing the average cross-sectional area of labeled segments in injured tissue against a healthy baseline from the same staining batch. There are honest limitations to this approach. The biggest one is throughput. Even with automation, generating a complete nephron map for a single whole-kidney sample takes roughly 40 to 60 hours of instrument time plus another 20 to 30 hours of annotation and registration work. If you need population-level data with hundreds of samples, this method won't scale. In those cases, targeted immunofluorescence on serial sections paired with stereological sampling gives you enough statistical power at a fraction of the time.
Another limitation is that labeled mapping shows you structure, not function. You can see that the proximal tubule has regrown, but you can't tell from the map alone whether it's actually reabsorbing solutes properly. I always pair my mapping data with inductively coupled plasma mass spectrometry for electrolyte clearance measurements or, if the model allows it, micro-puncture studies. The structural map tells you where the damage is. The functional data tells you whether the tissue is actually working again. For anyone setting this up for the first time, start small. Don't try to map a whole kidney. Pick a single cortical region, label three or four markers, and learn the registration pipeline until it runs without constant manual correction. Once that's stable, expand outward. The technique works. It's just not as elegant as the figures in the papers make it look.