The GLP-1 and Insulinoma Connection
Most endocrinologists know the basics of insulinoma management: 72-hour fasting, C-peptide suppression, diazoxide for refractory cases. But over the last few years, a pattern has been showing up in case reports and clinical conversations that most people aren't building into their diagnostic algorithms. A patient on a GLP-1 receptor agonist presents with recurrent hypoglycemia. Standard workup comes back inconclusive or borderline. Something about the medication is obscuring the picture. I ran into this a couple years ago. A type 2 diabetic on exenatide was coming back to us with fasting glucose readings in the 50s and 60s. Their sulfonylurea screen was negative. C-peptide was detectable but not screamingly high. We had been treating this as a stubborn medication side effect when the actual issue was a 1.5-centimeter lesion in the pancreatic head that turned out to be a well-differentiated neuroendocrine tumor. The GLP-1 agonist wasn't causing the hypoglycemia directly, but it was amplifying the insulin secretory response from a tumor that had been there the whole time. Stopping exenatide didn't eliminate the episodes, which was the clue we needed.
How the Mechanism Actually Works
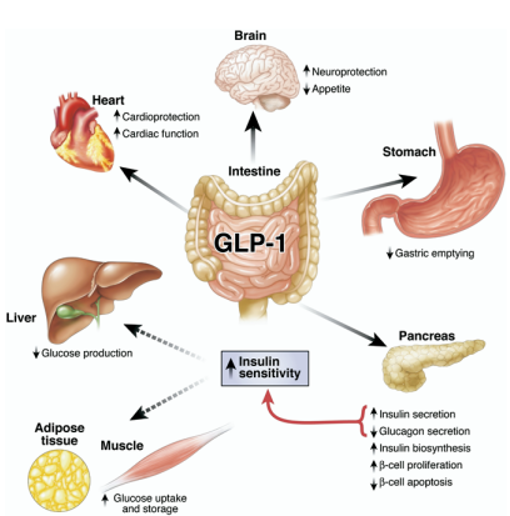
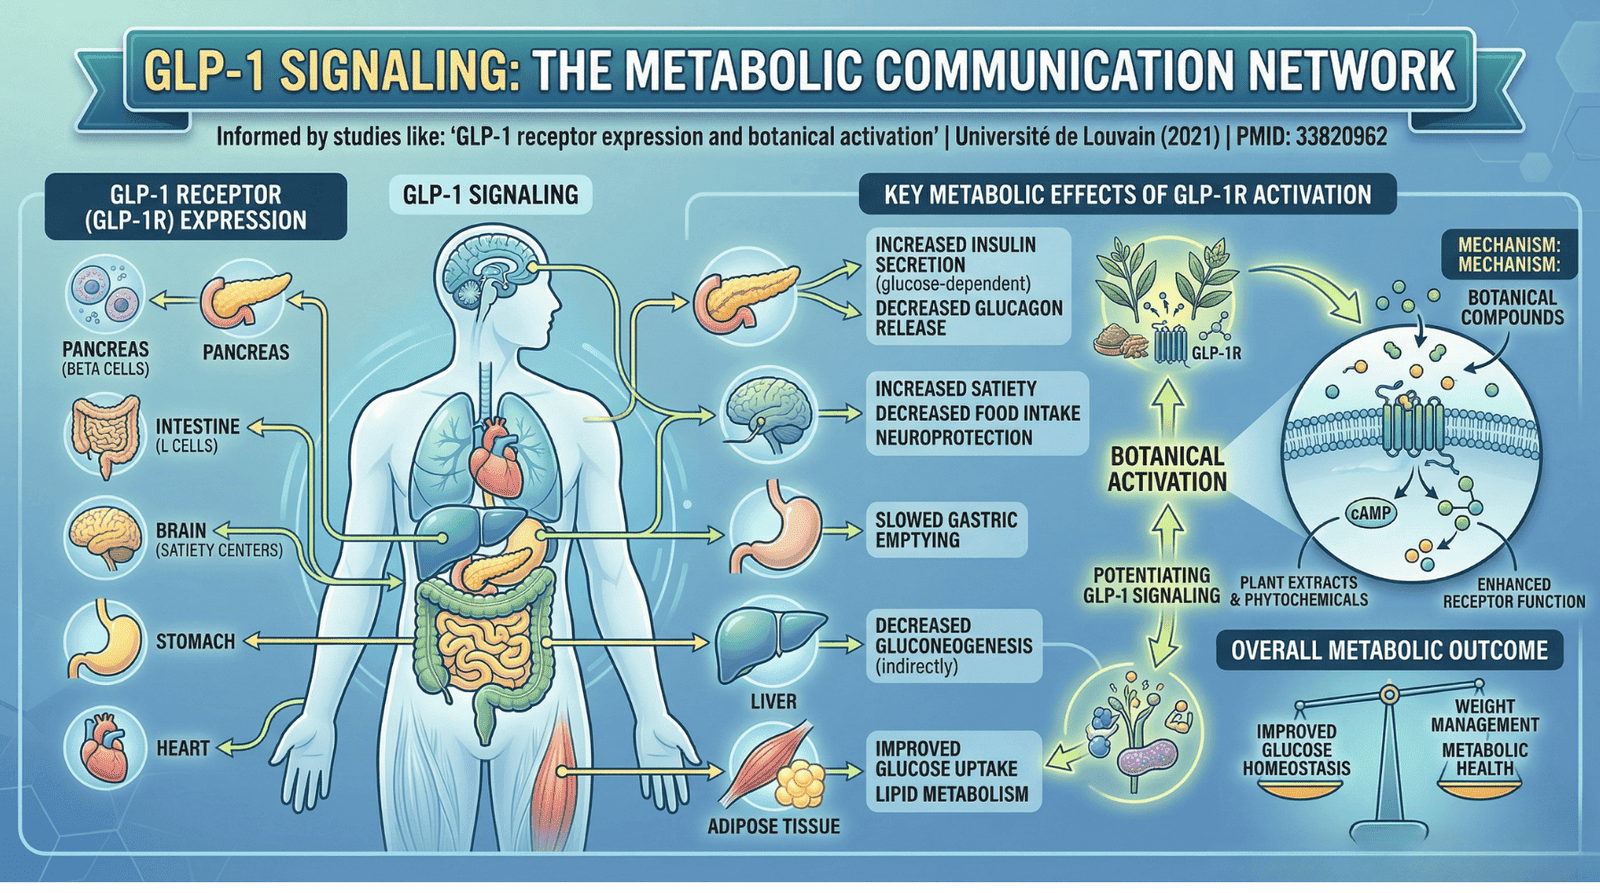
GLP-1 receptors are expressed on pancreatic beta cells under normal circumstances. That's how GLP-1 agonists work in diabetes treatment—glucose-dependent stimulation of insulin release. The receptor is a G-protein coupled receptor, primarily coupling through Gs to increase intracellular cAMP. This triggers exocytosis of insulin granules. Insulinomas are clonal proliferations of beta cells. They retain GLP-1 receptor expression in the vast majority of cases. The counterintuitive part is that insulinoma cells can be hypersensitive to GLP-1 stimulation compared to normal beta cells. Their glucose thresholds for insulin secretion are shifted downward, and the GLP-1 pathway adds additional amplification on top of that. This means even physiological concentrations of GLP-1—levels you'd see after a meal—can drive significant insulin release from tumor tissue. The clinical consequence matters most in two scenarios. First, undiagnosed insulinoma in a patient started on a GLP-1 agonist. The drug can unmask or accelerate the presentation of a previously quiet tumor. Second, patients with known insulinoma being considered for GLP-1 therapy. Some of these patients have had paradoxical responses where postprandial hypoglycemia actually worsened on the medication despite better fasting glucose control.
Unlocking The Hidden Connection Between Glp1 And Insulinoma What You Need To Know
The diagnostic workup needs to account for the confounding effect of exogenous GLP-1 receptor agonists. Here's the practical approach I use and recommend: Stop the GLP-1 agonist for at least five half-lives before testing. Exenatide twice daily has a half-life of about 2.4 hours, so roughly half a day. Liraglutide and semaglutide have longer half-lives and active metabolites; I wait a full two weeks before drawing baseline samples. This is important because circulating GLP-1 receptor agonist will persist in the system and actively stimulate the tumor during your sampling window, giving you artificially elevated insulin and C-peptide values that look like spontaneous hyperinsulinism rather than tumor-driven secretion. When you do the 72-hour fast, draw samples at baseline and then at hypoglycemic thresholds. The key measurements are glucose, insulin, C-peptide, proinsulin, beta-hydroxybutyrate, and sulfonylurea/meglitinide screen. With an insulinoma, you should see inappropriately elevated insulin (usually above 3 microU/mL) when glucose drops below 55 mg/dL, suppressed C-peptide ratio, and detectable proinsulin. But if the patient was still on GLP-1 therapy when you drew these, the insulin level may be elevated from drug stimulation rather than autonomous tumor secretion, making interpretation nearly impossible.
Get the Full Details
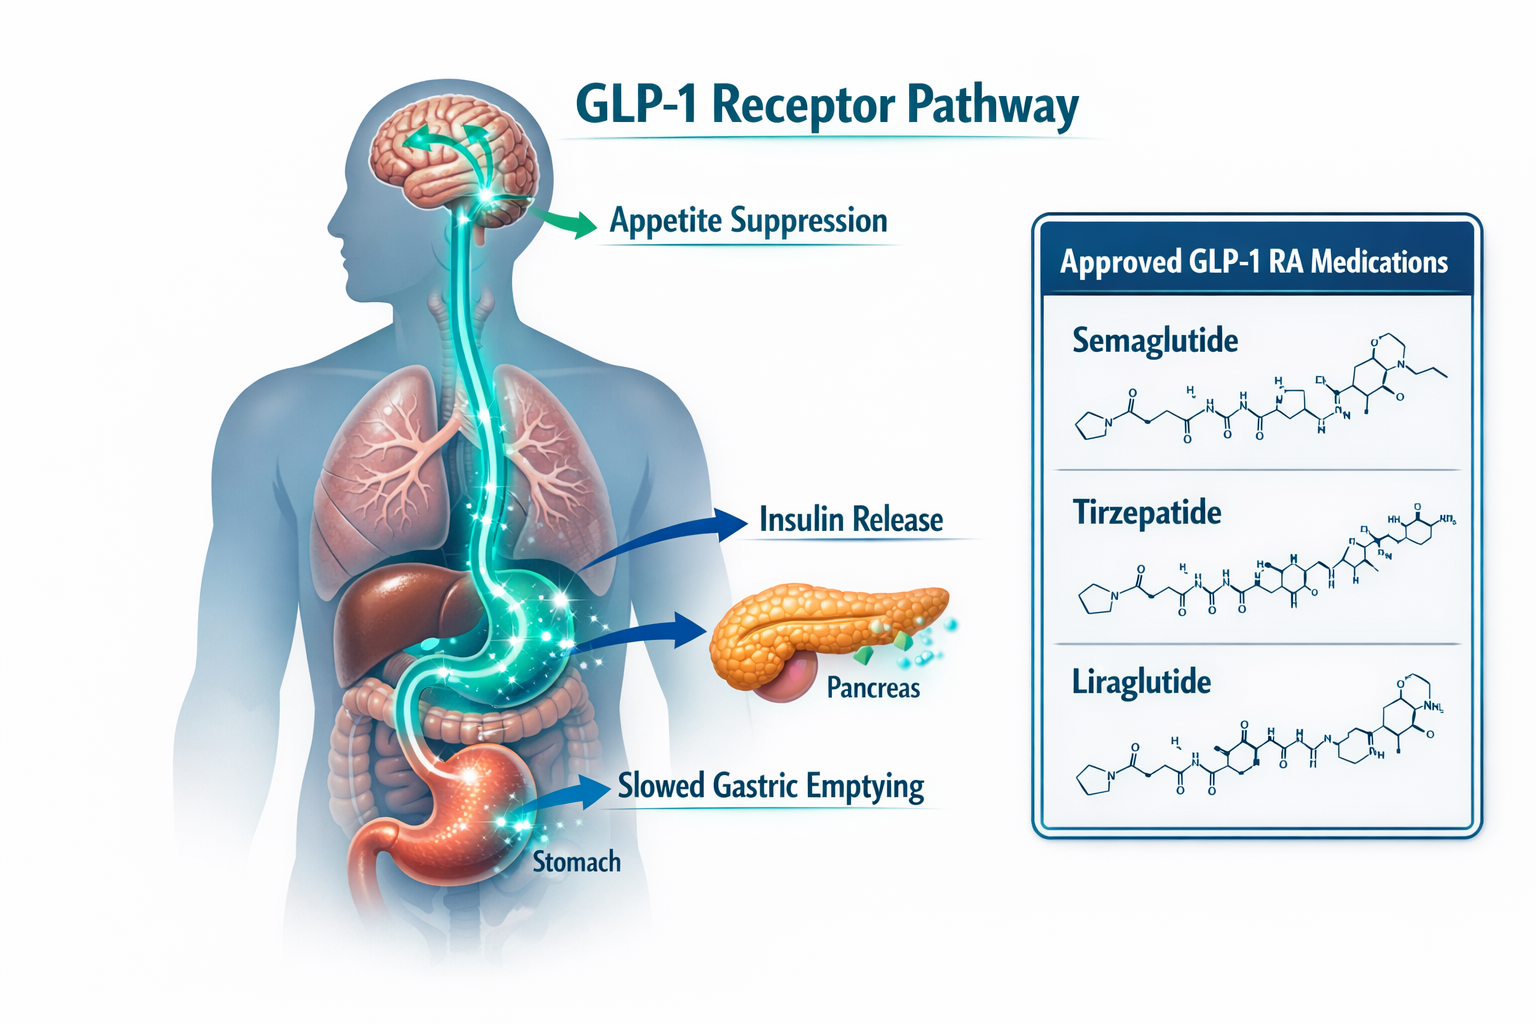
One thing that catches people off guard: GLP-1 itself, the endogenous incretin, gets cleared extremely quickly by DPP-4 enzymatic degradation with a half-life measured in minutes. Synthetic GLP-1 agonists resist this degradation, which is why they last long enough to be therapeutic. When you're measuring endogenous GLP-1 levels in a patient with insulinoma, draw the sample in a chilled EDTA tube, spin it immediately, and freeze it. If you don't process it within 30 minutes at room temperature, the reading is essentially worthless. I've seen labs report undetectable GLP-1 levels in insulinoma patients that were actually just degraded from poor sample handling.
Advanced Nuances Most Guidelines Don't Cover
There's a subset of insulinomas that show unusually robust GLP-1 receptor expression. In our experience, these tumors tend to be more sensitive to somatostatin analogs for symptom control but also more reactive to GLP-1 stimuli. The clinical implication is that octreotide or lanreotide might provide better preoperative glucose stabilization in these cases, but you have to monitor carefully because the response isn't uniform. Another thing that doesn't get enough attention: GLP-1 can affect gastric emptying. Delayed emptying in a patient with an insulinoma changes the timing of hypoglycemic episodes dramatically. Postprandial hypoglycemia becomes less predictable because nutrient absorption is slowed, and the tumor's insulin secretion doesn't align with glucose appearance anymore. Patients describe this as random episodes rather than the typical one-to-three-hour post-meal pattern you see in non-GLP-1 insulinoma patients. This temporal distortion often leads to misdiagnosis as factitious hypoglycemia or reactive hypoglycemia of non-neoplastic origin. Imaging is where the GLP-1 connection gets most practically relevant. Endoscopic ultrasound remains the most sensitive modality for small pancreatic neuroendocrine tumors, picking up lesions as small as 3-4 millimeters that cross-sectional imaging misses. Glucagon-like peptide-1 receptor imaging using Ga-68 labeled GLP-1 analogs like exendin-4 has shown promise in specialized centers but isn't widely available. The theoretical advantage is that it targets the receptor that's driving tumor activity, but the practical reality is that resolution is still inferior to EUS for subcentimeter lesions. We use it selectively, mostly when EUS and multiphasic CT both come back negative but biochemical suspicion remains high.
What This Means for Treatment Decisions
If you've confirmed insulinoma and the patient was previously on a GLP-1 agonist for diabetes, the medication needs to be addressed. Surgical resection is curative in the vast majority of sporadic, localized insulinomas. For patients with metastatic disease or those who aren't surgical candidates, the pharmacological approach changes because you now have a drug that's actively stimulating the tumor. Diazoxide remains first-line for medical management. It inhibits ATP-sensitive potassium channels on beta cells, preventing depolarization and subsequent insulin exocytosis. Typical dosing starts at 150 mg three times daily and titrates upward based on glucose monitoring. The main limitation is tolerance—peripheral edema and hirsutism are common, and about a third of patients discontinue due to side effects. When diazoxide fails or isn't tolerated, everolimus and temozolomide-based regimens are options for advanced disease, though response rates are modest. The GLP-1 specific consideration: avoid starting a GLP-1 agonist in any patient with a history of or active insulinoma, even after documented resection. The risk of recurrence stimulating the tumor outweighs any glycemic benefit in the insulinoma population. For patients with concurrent diabetes and insulinoma who are difficult to manage post-resection, alternative agents like SGLT2 inhibitors or basal insulin with careful adjustment are safer options. We've had patients where post-resection hypoglycemia resolved completely and their diabetes medication could be tapered off entirely, which was unexpected but well-documented in the literature.

Common Pitfalls
The biggest mistake I see is drawing biochemical samples while the patient is still on a GLP-1 agonist and interpreting the results as definitive for or against insulinoma. The drug creates a false-positive pattern of hyperinsulinemia that can lead to unnecessary imaging, unnecessary surgery exploration, or worse, a missed diagnosis because the team attributes everything to the medication and stops looking. Always stop the agent first. If stopping isn't feasible for clinical reasons, document it clearly and interpret all subsequent results with that confounder in mind. A second pitfall is assuming that a negative standard working hyperinsulinism panel rules out insulinoma in a patient on GLP-1 therapy. The suppressed insulin you see might be genuine suppression or it might be artifact from receptor desensitization with chronic agonist exposure. The proinsulin-to-insulin ratio is more reliable in this context because insulinoma cells preferentially secrete proinsulin, and this pattern persists regardless of GLP-1 receptor status. A proinsulin level above 5 pmol/L during hypoglycemia is still significant even when the insulin value looks borderline. The third pitfall is less commonly discussed but equally important. Some insulinomas co-secrete other peptides—gastrin, VIP, pancreatic polypeptide. GLP-1 can stimulate release of these cot secreted peptides as well. A patient presenting with diarrhea and flushing alongside hypoglycemia might have a VIPoma component that's being amplified by the GLP-1 agonist, making the tumor appear more aggressive than it actually is. Checking baseline VIP, gastrin, and PP levels before starting any GLP-1 therapy in a suspected neuroendocrine case is reasonable and cheap insurance.
Bottom Line
The connection between GLP-1 and insulinoma is real and clinically meaningful but not common enough that every provider has thought through it. The practical takeaway is straightforward: in any patient on a GLP-1 receptor agonist who develops unexplained hypoglycemia, insulinoma should be on the differential regardless of how borderline the initial lab values look. Stop the medication, repeat the workup properly, and don't let the drug explanation close the case too early. A missed insulinoma is far more dangerous than a temporary interruption of diabetes management.