Understanding the Vascular Supply That Keeps Your Heart Beating
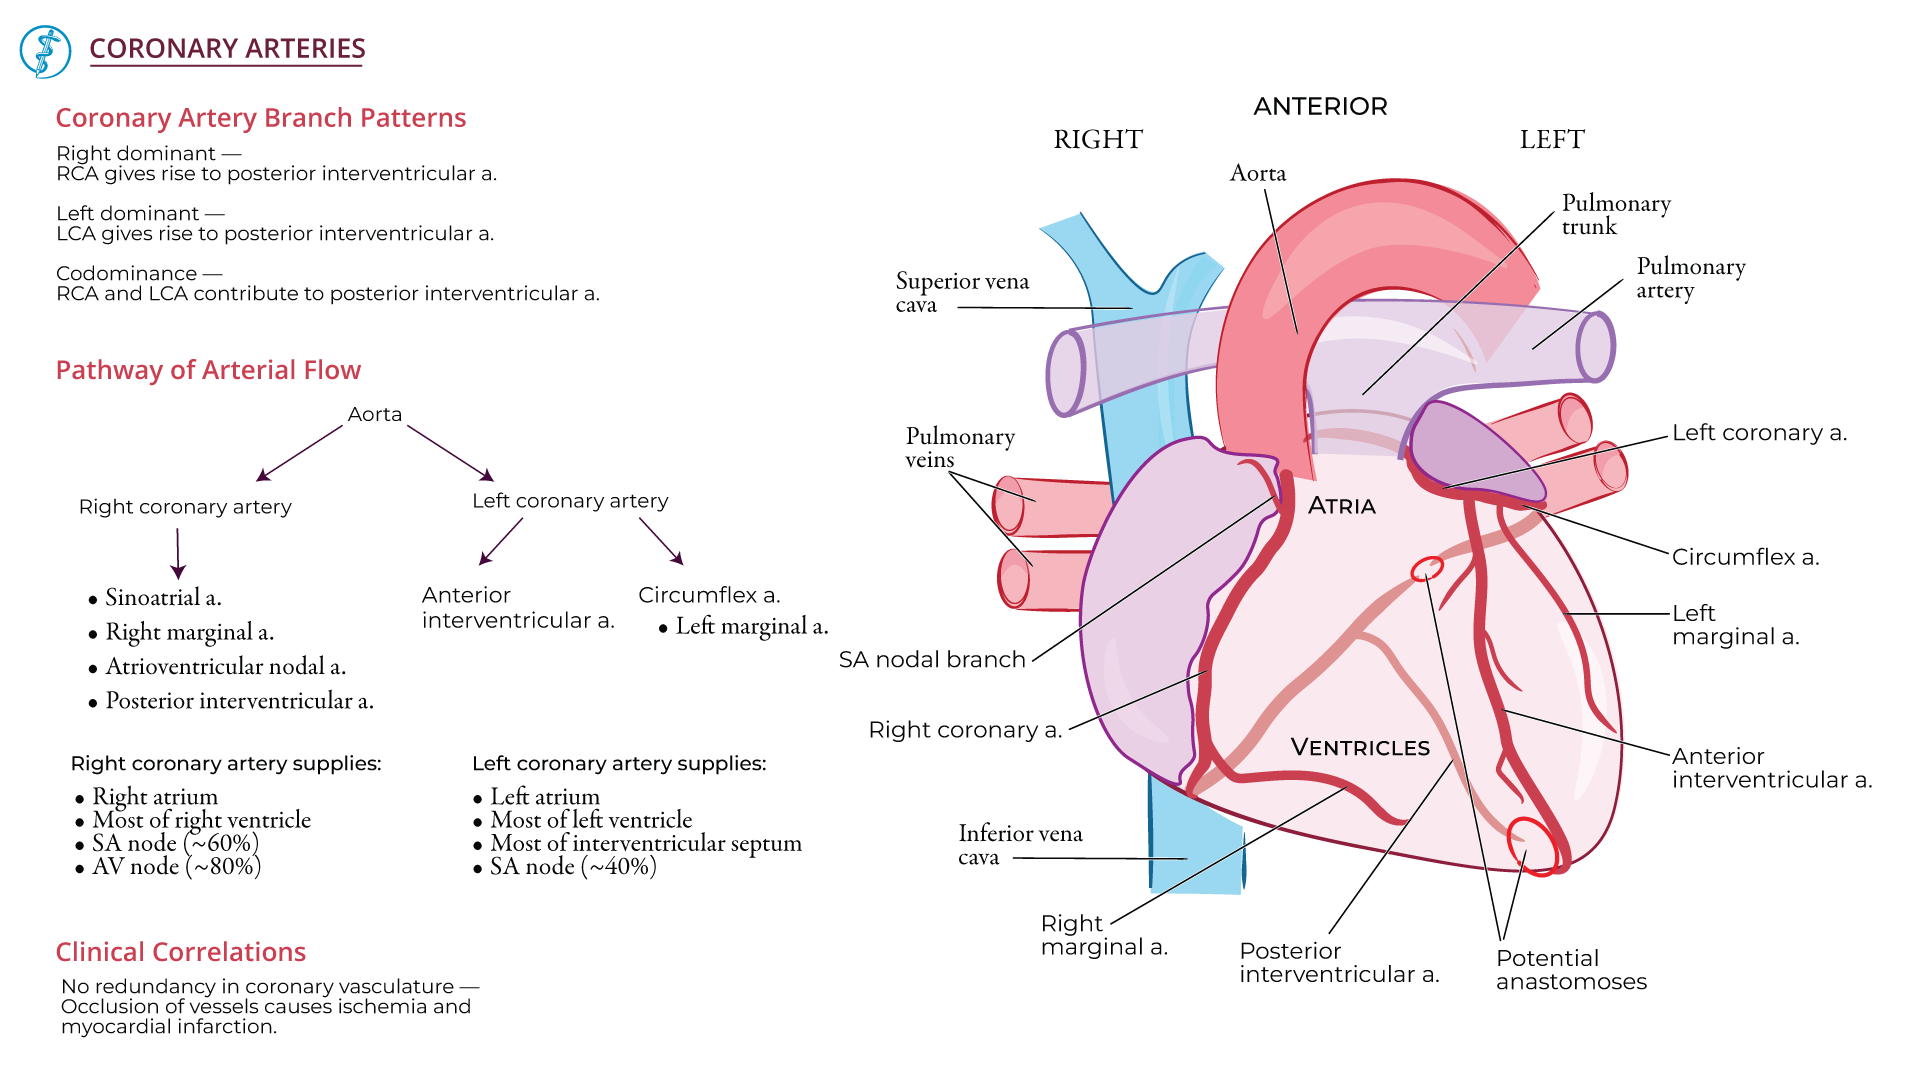
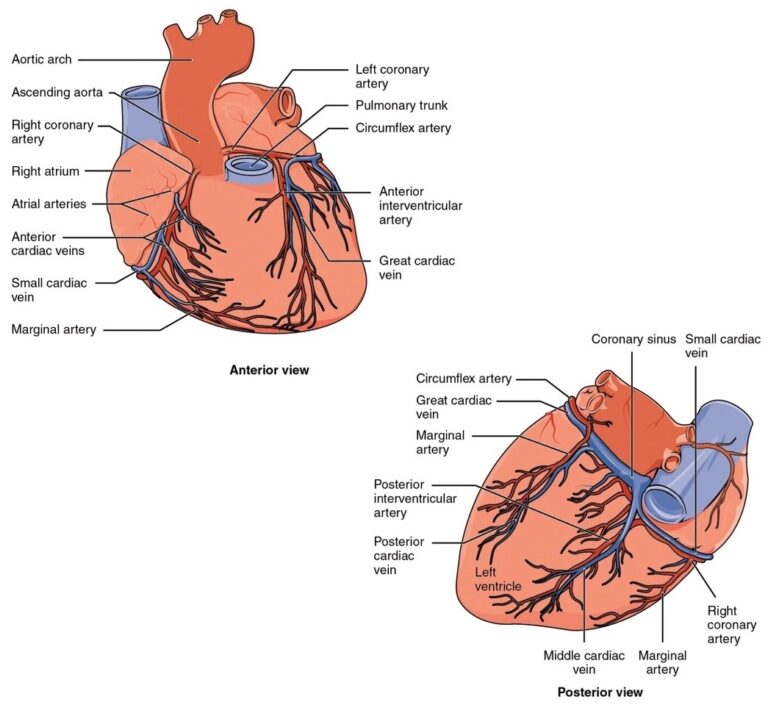
The heart runs on a network of arteries called the coronary circulation. These vessels branch off the aorta and wrap around the outside of the heart muscle before diving into the tissue itself. When they work properly, you don't think about them. When they narrow or block, everything changes fast. There are three main coronary arteries everyone references: the left anterior descending (LAD), the left circumflex (LCx), and the right coronary artery (RCA). The LAD supplies the front wall and the septum. The LCx covers the lateral and posterior walls. The RCA feeds the bottom of the heart and the electrical nodes in most people. Around 85% of the population is right-dominant, meaning the RCA gives off the posterior descending artery. The rest are left-dominant, and those cases can look very different on angiography. I spent years reading coronary CTAs and watching how these vessels actually present in living patients. One thing that surprises people is that a "critical" stenosis on paper doesn't always match what the patient feels. I had a case once where a patient had 90% blockage in a diagonal branch of the LAD but reported zero symptoms. Stress test came back clean. Why? Collateral flow had quietly developed over months. The heart rerouted blood through smaller vessels from the other coronary system. This is the kind of thing that only shows up when you're actually looking at the imaging day after day.
How Blood Flow Actually Reaches the Heart Muscle
Coronary blood flow isn't straightforward like systemic circulation. Most of the perfusion to the left ventricle happens during diastole, not systole. When the heart contracts, the muscle squeezes the intramural vessels shut. During relaxation, flow rebounds. This is why heart rate matters so much. A resting rate of 110 in someone with coronary disease can drop perfusion significantly because there's simply less diastolic time. That's why beta-blockers aren't just symptom relief — they're actually buying time for the myocardium to get enough blood. The microcirculation is where most resistance lives. You can have perfectly clean epicardial arteries and still have cardiac syndrome X, which is microvascular angina. The big vessels look fine on catheterization. The small arterioles down below aren't dilating properly. It's frustrating to diagnose because standard tests miss it. The workaround I learned is to look at coronary flow reserve — the ratio of maximum to baseline flow. If it's under 2.0, you've got a problem even if the LAD looks wide open.
What Happens When These Vessels Narrow
Atherosclerosis is the usual culprit. Plaque builds up inside the arterial wall, not on top of it. The vessel remodels outward at first to compensate, so a moderate plaque might not show a significant lumen narrowing on angiography. By the time it looks tight on a standard 2D projection, you're often looking at 70% or more diameter reduction. The FFR (fractional flow reserve) measurement tells you whether that narrowing is actually limiting flow under stress. An FFR below 0.80 means the lesion is hemodynamically significant. I've seen stents placed based on anatomy alone that turned out to be unnecessary once FFR was measured. Stenting a non-significant lesion adds risk without benefit. Plaque rupture is the event that causes most heart attacks. It's not always the most narrowed vessel that kills you. A 40% plaque with a thin fibrous cap can rupture, trigger thrombosis, and occlude the artery completely in minutes. The 80% plaque that's been there for years with a thick cap is often more stable. This is counterintuitive for a lot of people who think percentage of blockage tells the whole story. It doesn't. Plaque composition matters at least as much.
Get the Full Details
Diagnostic Approaches and What Actually Works
Stress echocardiography, nuclear perfusion scans, and stress MRI each have their place. Nuclear scans are sensitive but expose you to radiation. Stress MRI gives excellent detail and no radiation but isn't available everywhere. Coronary CTA has gotten good enough that for low-to-intermediate risk patients, it's often the first line. A normal CTA basically rules out obstructive disease with high confidence. The downside is calcium blooming — heavily calcified vessels can make it look like there's a blockage when there isn't. In those cases, you fall back to FFR-CT or invasive angiography. I'll be blunt about the limitations of non-invasive testing. They miss things. Small vessel disease doesn't show up on CTA. Early plaques that haven't caused luminal narrowing yet are invisible. Functional tests depend on your ability to exercise or Pharmacologically stress adequately. If you can't achieve 85% of your predicted maximum heart rate, the test is non-diagnostic and you need to repeat it or move to a different modality. That happens more often than you'd think in outpatient clinics.
Practical Steps for Protection
Managing risk factors is the only approach with strong evidence behind it. Blood pressure control, lipid management, smoking cessation, and glucose control each move the needle. Statins don't just lower LDL — they stabilize plaque by reducing the lipid core and thickening the fibrous cap. That's why someone can have a heart attack on a statin if they stop taking it; the protective effect reverses over weeks. Aspirin has a narrower role now. It's recommended after a cardiac event, not as primary prevention for most people anymore. The bleeding risk outweighs the benefit in low-risk individuals. Exercise improves endothelial function directly. Regular aerobic activity increases nitric oxide production, which keeps the coronary arterioles dilating properly. This is relevant even for people with established disease. Cardiac rehabilitation programs that include supervised exercise have shown mortality benefits that go beyond what medications alone achieve. The mechanism isn't completely mapped out, but improved collateral development and better autonomic tone are probably contributing factors.
When to Escalate
New chest discomfort with exertion, unexplained shortness of breath, or pain that radiates to the jaw or left arm deserves evaluation. Atypical presentations are common in women and diabetics. I've seen both groups dismissed initially because they didn't fit the classic picture. A woman in her fifties told me her fatigue was just stress. Two weeks later she was in the ER with an anterior MI. The LAD was 95% occluded. She'd had mild exertional chest pressure for months but chalked it up to age and work. Don't ignore subtle changes in your exercise tolerance. Family history matters more than people realize. A first-degree relative with early coronary disease — male under 55, female under 65 — shifts your risk category substantially. I always check this first because it changes how aggressively I pursue testing in borderline cases. Lipid panels should include ApoB if you're at elevated risk. Standard LDL cholesterol misses particles that are independently atherogenic. ApoB counts the actual number of atherogenic particles. It's a more accurate measure of risk but isn't ordered routinely everywhere yet. The coronary system is remarkably resilient until it isn't. Pay attention to what your body tells you while it still can.