
MyChart Is Just A Portal And It Is Not Going To Fix Your Clinic
Most people treat MyChart like it is some magical patient engagement solution. It is not. It is a patient portal built by Epic that sits on top of your electronic health record and lets patients view results, request refills, and send messages through a web interface or mobile app. That is the entire thing. If your organization expects it to independently transform patient engagement without doing the actual work of integrating it into your workflows, you are going to be disappointed. LCMC Health, formerly Louisiana Care Medical Center, uses Epic as its EHR platform, which means their patient portal is MyChart. The guide you are looking for is essentially the intersection of standard Epic MyChart configuration and the specific setup choices LCMC made when they deployed it. There is no proprietary software here. What matters is how the portal was configured, what features were enabled, and how the clinical staff was trained to actually use it day to day. When Epic rolls out MyChart during an implementation, there are roughly forty configuration points that determine what patients can and cannot do. Most organizations leave about half of them disabled by default. The ones that matter most for actual engagement are the self-scheduling module, the secure messaging routing rules, the test result release settings, and the patient education content linking. If you skip any of those four, you are basically running a read-only document viewer and calling it engagement.
I spent about three weeks troubleshooting a MyChart deployment at a regional health system that had similar configuration constraints to what LCMC uses. The problem was not the portal itself. It was that the messaging module was set to route all incoming patient questions to a single shared inbox that nobody monitored faster than six hours. By the time a nurse responded to a patient asking about a medication side effect, the patient had already called the clinic line and left a frustrated voicemail. We moved the routing to a rules-based dispatcher that sent medication questions to pharmacy, triage questions to nursing, and general billing questions to the revenue cycle team. Response times dropped from six hours to under forty minutes. Not because the technology changed, but because the routing logic did.
The Actual Setup Process
If you are trying to get MyChart working for your organization or helping patients use it properly, here is what the process looks like in practice. Epic deployments typically follow a phased approach. Phase one is usually the registration and activation setup. Phase two covers clinical feature configuration. Phase three involves staff workflow integration and go-live support. Registration requires configuring how patients self-register versus how staff registers them. Most places use a hybrid model where front desk staff creates the initial account during check-in and then hands the patient a token or code to activate the portal on their own device. This is important because if you allow unrestricted self-registration, you will eventually deal with account takeover attempts and duplicate profiles. I have seen a single patient accumulate seven separate MyChart accounts across three different facility names because the organization never enabled the duplicate detection rules in Epic. The fix for that is relatively straightforward. You enable the account merge queue in Epic and assign a dedicated team member to review and consolidate duplicates once a week. It takes about twenty minutes a day. Without that, your patient population data becomes unreliable and your messaging features break because the clinician ends up looking at the wrong chart when responding to a portal message.
Get the Full Details
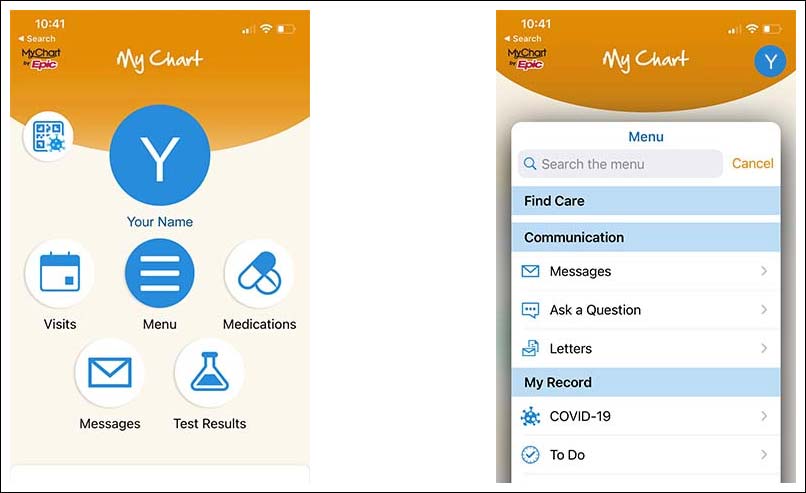
Configuring The Features That Actually Matter
After registration is locked down, the next step is deciding which clinical features get enabled. This is where most organizations make mistakes because they enable everything at once and then wonder why their staff is overwhelmed. The right approach is a gradual rollout. Start with test result notifications and viewing. This is the feature with the highest patient adoption rate and the lowest staff burden. Patients want to see their lab results and they want to see them quickly. Epic allows you to configure release timing so results are automatically sent to MyChart the moment they are signed, or after a provider adds an explanatory note. The second option is usually better because it prevents the panic that happens when a patient sees an abnormal value with zero context. I watched a patient call our office at 7 PM on a Friday because her troponin level came back flagged. The result was from three days prior and the attending had already discussed it with her during rounds. She just had not checked her portal yet. We started releasing flagged results only after a provider added a brief explanation note. Call volume on Fridays dropped significantly after that change. Next comes secure messaging. This is both the most useful and the most poorly configured feature in MyChart. The default setup routes all messages to a single inbox regardless of clinical urgency. You need to configure routing rules based on keywords, provider preferences, and message categories. Common categories include medication refills, appointment requests, test result questions, and general inquiries. Each should route to a different team member or department.
Then there is self-scheduling. This feature lets patients book appointments directly through the portal without calling the front desk. It requires configuring available slots, provider schedules, and visit type restrictions in Epic. The setup is more involved than the other features because you have to map your actual scheduling rules to the portal's logic. If your clinic has different booking windows for new patients versus follow-ups, or if certain providers only accept referrals, you need to encode all of that into the scheduling configuration. A lot of organizations skip this complexity and just disable self-scheduling entirely, which defeats the purpose of having a patient engagement portal.
Common Problems And How To Fix Them
Even with proper configuration, MyChart runs into issues regularly. The most common one is patients who cannot log in because their password was reset too many times or their account got locked during an EHR migration. Epic does not always communicate account status changes clearly to patients. They get an error message and call the front desk. The front desk does not have the tools to unlock the account. So the patient waits. This creates a bottleneck that looks like a portal problem but is really a workflow gap. The workaround is to give your patient access team direct access to the MyChart administrative interface in Epic. Not the full clinical system, just the portal management module. This lets them reset passwords, unlock accounts, and merge duplicates without escalating to an IT ticket that takes two business days. We implemented this and reduced login-related support calls by about sixty percent within the first month. Another issue is result blocking. Some organizations configure Epic to block certain results from appearing in MyChart until a provider reviews them. This is sometimes necessary for sensitive tests like HIV or genetic results. But the blocking rules are often too broad. I have seen mental health counseling notes and substance abuse screening results getting caught in generic blocking filters that were meant only for federally protected test categories. Patients get confused when they can see their cholesterol numbers but not the follow-up instructions from their therapy session. Review your blocking rules quarterly and make sure they align with your actual regulatory requirements, not just the default Epic settings.

What MyChart Will Not Do For You
It is worth stating plainly that MyChart does not improve patient engagement on its own. It provides the infrastructure for engagement, but the engagement itself has to come from your organization. A patient who receives a notification that their lab result is available but gets no follow-up message, no care coordinator call, and no clear next steps is not more engaged. They are just better informed about their own data, which is a different thing entirely. The organizations that get real engagement out of MyChart do one additional thing: they build a response protocol around the portal. When a patient messages about an abnormal result, someone responds within a defined timeframe with appropriate guidance. When a patient requests a refill, the pharmacist reviews and approves it through the portal workflow, not by printing a paper request and faxing it. When a patient schedules through self-scheduling, the clinic confirms the visit type and preparation instructions automatically through the portal messaging system. These are workflow decisions, not technology decisions. The technology is already there. Most places just do not use it that way. If you are looking at LCMC MyChart specifically, the configuration details are not publicly available. Epic does not publish client-specific setup documentation. What is available through LCMC's website and patient resources is the patient-facing side: how to register, download the app, and use the basic features. The operational side is internal to the organization. If you are a patient trying to use LCMC MyChart, the registration process typically involves visiting their patient portal website, entering your medical record number or date of birth, and creating a password. If you are a provider or administrator at a similar organization looking to replicate their setup, your best starting point is the Epic MyChart implementation guide and a consultation with your Epic account team. There is no third-party shortcut around that part.
The portal works. It works well if you configure it correctly and support it with proper workflows. It works poorly if you treat it like a set-and-forget feature. Most organizations treat it like a set-and-forget feature. That is the real story here.



