Finding the Right Spot on a Chest X-Ray
If you've ever tried to count intercostal spaces on a frontal chest radiograph and ended up off by one or two, you're not alone. The Angle of Louis, that little bump where the second rib meets the sternum, is supposed to be your anchor point. It usually is. But "usually" doesn't help when the patient has severe kyphosis or the image is a portable AP grab from 2 AM. I spent years doing this in the reading room, mostly under time pressure, with crummy contrast settings and technicians who didn't always get the positioning right. Here's what actually works when you need to nail the anatomy.
Unlocking The Accuracy Of Xray Imaging The Science Of Angle Of Louis Locating Intercostal Spaces
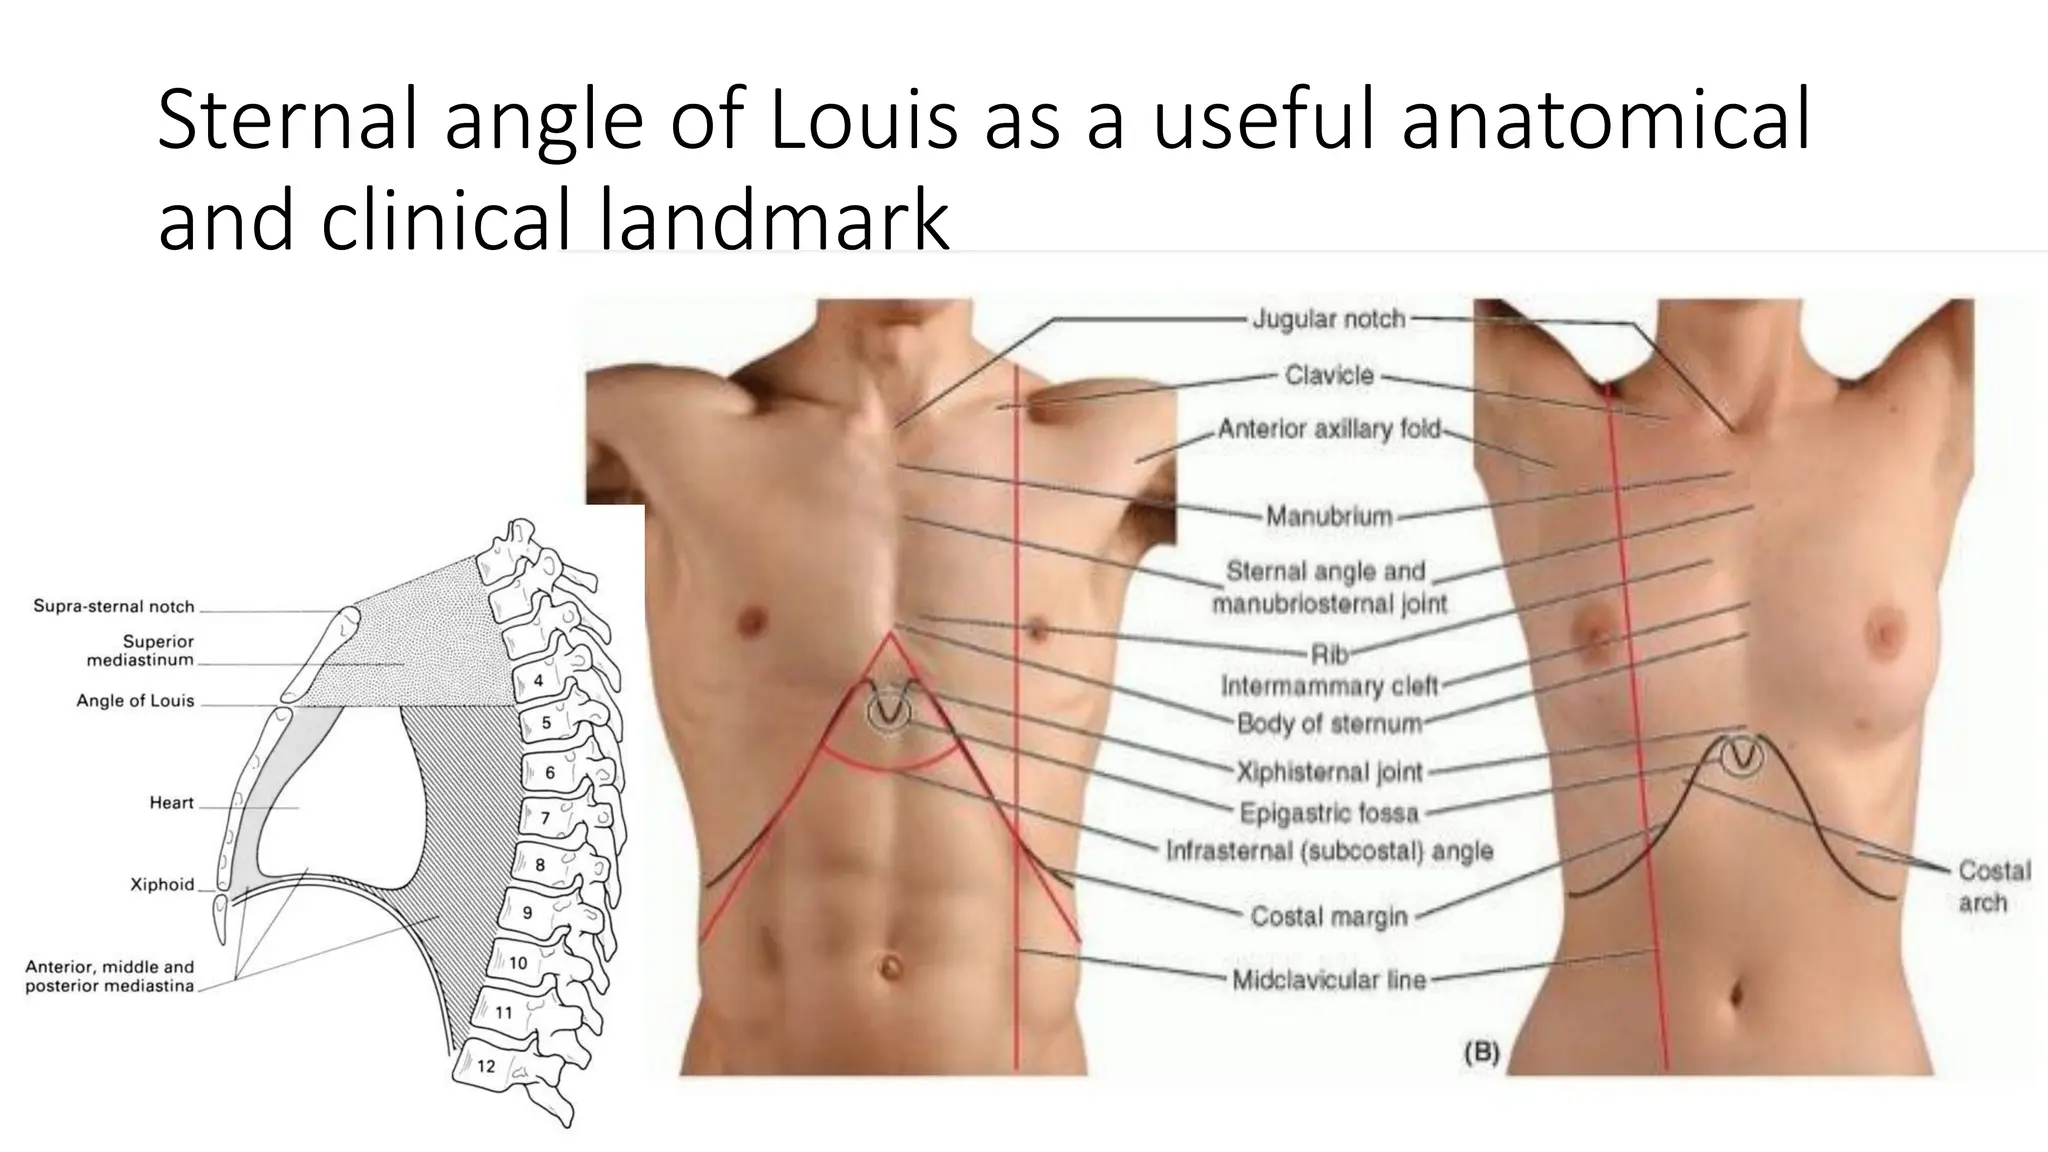
The Angle of Louis sits at the level of the second costal cartilage articulation with the sternum. From there, you count down: second space, third space, and so on. This matters because landmark-based procedures depend on it. Thoracentesis targets are typically the third through seventh intercostal spaces in the midclavicular to anterior axillary lines. Incorrect counting puts you either above a rib (risking neurovascular bundle injury) or too low (puncturing the diaphragm or liver/spleen). On ECG lead placement, V4 belongs in the fifth intercostal space at the midclavicular line. Miss that by one space and your axis shifts enough to muddy interpretation. The most common error I see is starting the count at the suprasternal notch instead of the Angle of Louis. The notch is roughly at the T2-T3 level, but the second rib attaches lower. That one mistake cascades into every subsequent landmark being off by a space. Another frequent issue is assuming the angle is always visible on the radiograph. In obese patients, patients with thick subcutaneous tissue, or those with prior sternotomy hardware, the anatomical landmark becomes nearly impossible to identify directly on the image. I had a case recently where a patient with significant pectus excavatum had the angle displaced anteriorly. On the PA film, it appeared at what looked like the fourth rib level rather than the second. Counting from there would have pushed every subsequent landmark down by two spaces. The workaround was simple once I caught it: I traced the manubrium down to where it met the body and then looked for the rib that angled posteriorly toward that junction on the lateral view. The lateral projection showed the true anatomical relationship because the deformity shifted the anterior surface more than the posterior rib cage. That lateral film became my reference, and I used it to recalibrate the count on the PA.
Practical Counting Method
Start by identifying the sternal angle. Look for the transverse ridge at the manubriosternal junction. The second rib attaches here. If you can see the second rib clearly, verify by noting that it has a characteristic shallow downward curve as it extends laterally. The first rib is short and nearly horizontal, which is another way to confirm you're not misidentifying it. Once you're confident at the second space, count down methodically, following each rib shadow as it courses laterally and inferiorly. When the angle isn't visible, use alternative reference points. The aortic knob sits at approximately the level of the fifth thoracic vertebra, which correlates with the fourth or fifth intercostal space depending on patient habitus. The carina bifurcates around T4-T5, giving you another landmark. For the lower limit, the xiphoid process generally aligns with the ninth or tenth costal cartilage region. These aren't as reliable as the Angle of Louis but they narrow the field enough to prevent gross errors.
Get the Full Details

Limitations You Need to Accept
This method breaks down in several scenarios. Severe scoliosis distorts the rib spacing asymmetrically, so counting from one side won't translate to the other. Patients with rib resections, fractures, or congenital rib anomalies obviously throw off the count. In pediatric patients, the cartilaginous ribs are less radiopaque, making direct visualization difficult until ossification progresses. Portable supine films compress the lung fields and crowd the intercostal spaces, making individual rib identification harder than on an upright PA. When none of the surface anatomy landmarks are trustworthy, fluoroscopic guidance or ultrasound becomes the practical alternative. Ultrasound can visualize the rib edges in real time and identify the intercostal space directly, which is particularly valuable for thoracentesis where the fluid level also needs mapping. CT scans provide definitive anatomical detail but aren't feasible for most bedside procedures. I tend to use ultrasound when the radiograph is ambiguous rather than relying on palpation alone, which has a significant error rate in overweight or edematous patients.
Quick Verification Checklist
Before proceeding with any procedure based on counted spaces, run through this: confirm the manubriosternal junction is identifiable, verify the second rib attachment, count down at least twice to check for consistency, correlate with vertebral landmarks where possible, and cross-reference with a lateral view if available. If any step feels uncertain, get an ultrasound rather than guessing. The Angle of Louis remains the standard teaching point for good reason. It's anatomically consistent in the vast majority of patients and provides a reliable starting position for intercostal counting. But the accuracy of any imaging-based procedure ultimately depends on recognizing when the standard approach isn't working and switching to a different modality rather than forcing a count that doesn't add up.