How to Code Articulation Disorders Correctly in ICD-10
Most people opening this page just want to know which box to check. It is simpler than you think and harder than you expect. The primary code for an articulation disorder is F80.0 — Specific developmental disorder of speech pronunciation. That is the code you will use most often. It covers childhood articulation problems where the person has trouble producing speech sounds correctly, without a broader language comprehension or expression issue. If you are coding for an adult with acquired articulation problems, you move to R47.0 — Speech sound disorder, which falls under symptoms rather than developmental conditions.Unlocking Speech Clarity How Articulation Disorder Is Delineated Through Icd10 Codes
Here is the part nobody tells you: the line between F80.0 and R47.0 is not always clean. F80.0 is specifically for developmental origins. If the patient was born with the disorder or it appeared during typical language development, use F80.0. If the articulation problem appeared after a brain injury, stroke, neurological disease, or surgery, you use R47.0. I once coded a 62-year-old who had developed clear articulation deficits after a traumatic brain injury two years prior. My initial instinct was F80.0 because the symptoms looked identical to childhood articulation disorder. The auditor caught it. F80.0 requires onset during development. We switched to R47.0 with an additional code for the underlying TBI etiology, and the claim went through without issue. The moral is that the origin of the disorder matters more than the surface symptoms. There are other codes people confuse with articulation disorder. F80.1 is expressive language disorder — that is a different problem entirely. The person struggles with vocabulary, sentence structure, and producing meaningful language, not just pronouncing sounds. F80.2 is receptive language disorder, where understanding spoken language is the primary deficit. R47.1 is apraxia of speech, which is a motor planning problem. People with apraxia know what they want to say but their brain cannot coordinate the muscle movements properly. It is not the same as articulation disorder, though they can overlap. Misusing R47.1 for a straightforward articulation problem will flag your chart for review. When you are documenting for F80.0, you should specify the type if possible. Some clinics add an additional code or use a descriptor like "phonological process disorder" to clarify. Insurance payers increasingly want to see that the diagnosis is not just a generic label. They want evidence that the problem is isolating to speech sound production. A simple note reading "difficulty with /r/ and /s/ sounds" is better than nothing but does not meet the threshold for medical necessity on its own. You need functional impact documented. I have found that including a sentence about how the disorder affects educational performance or workplace communication makes a real difference in authorization approvals. It usually cuts the back-and-forth with insurers down from three weeks to about five business days.
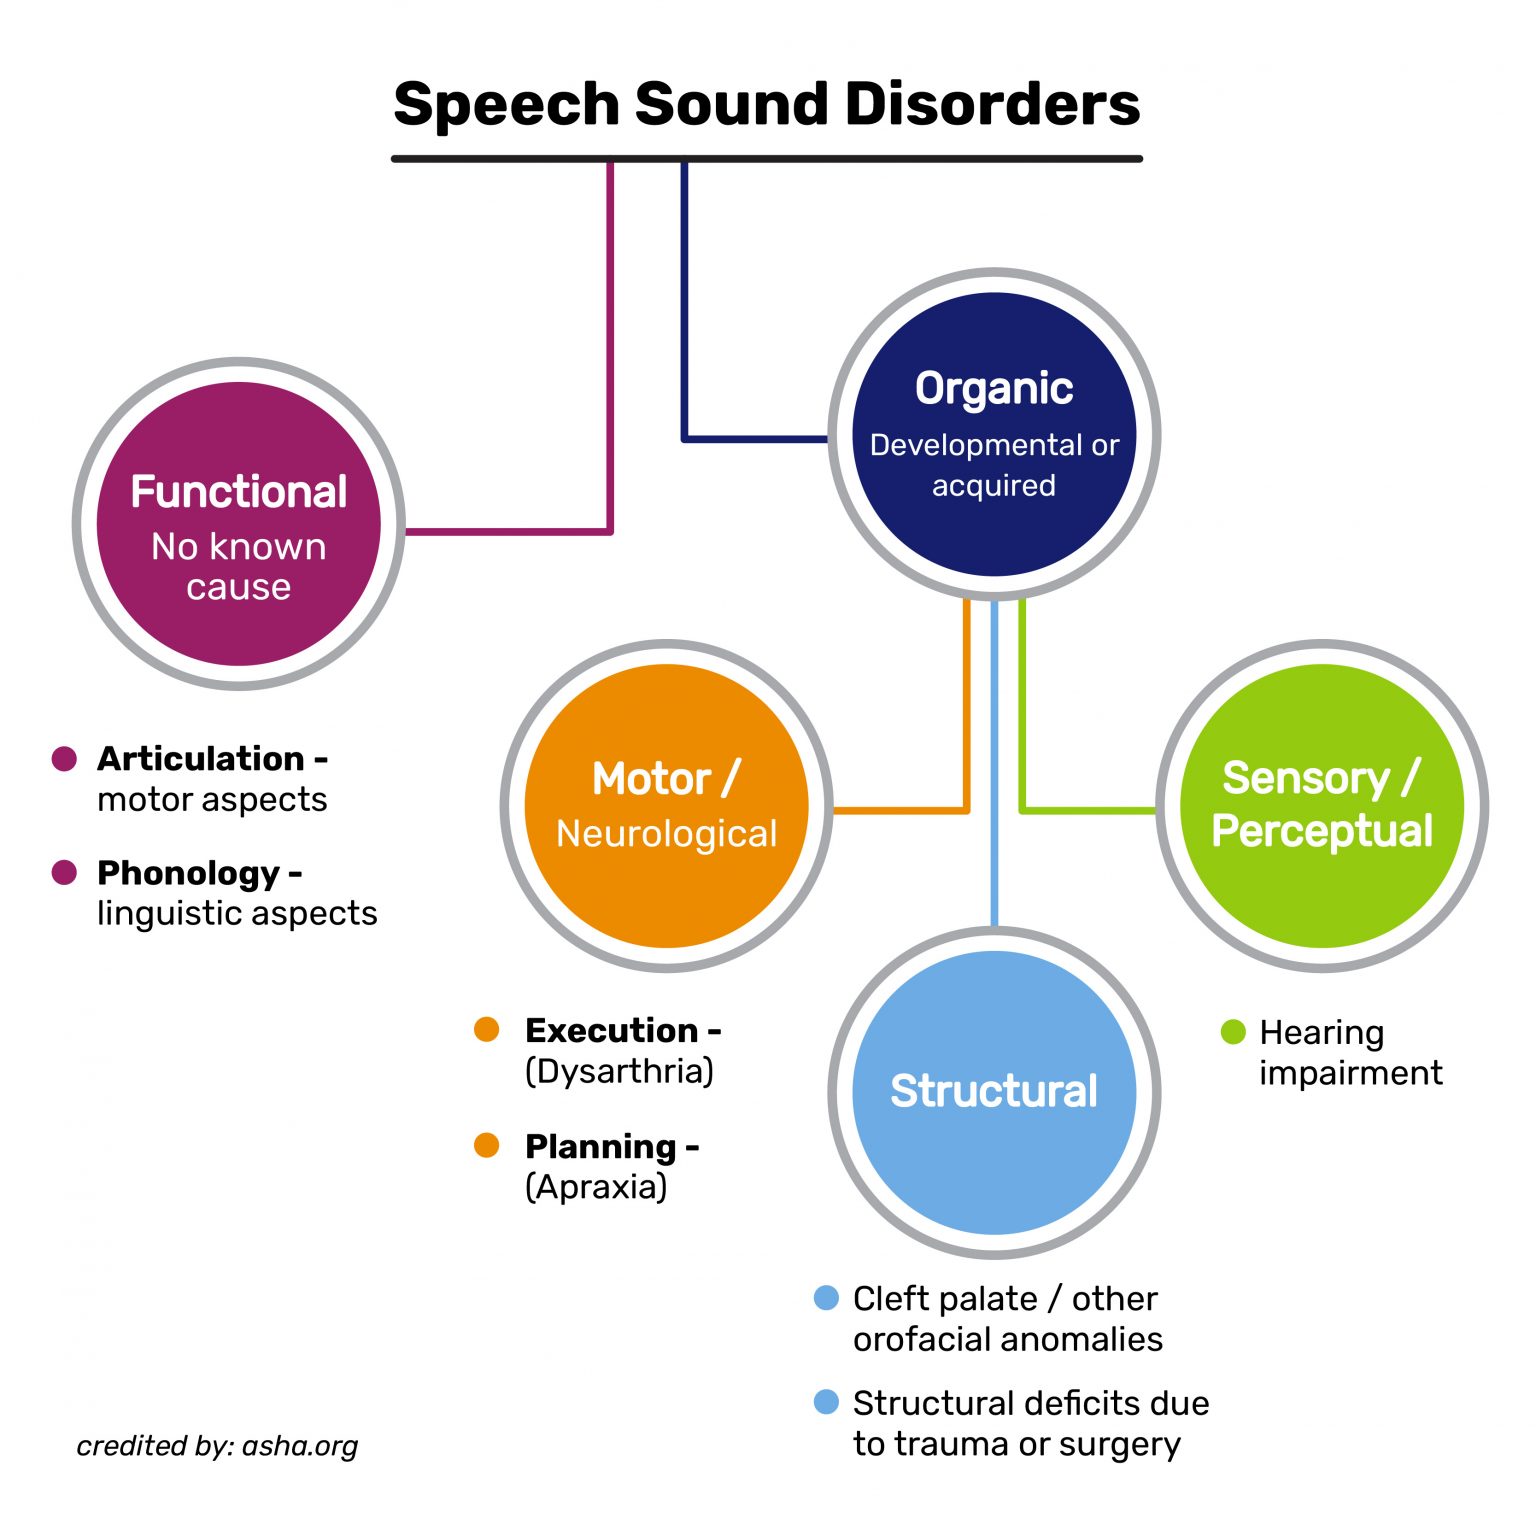
Another thing to watch: some coders use R40.2 for mutism or selectiveness in speech. That is a completely different category and applying it to articulation disorders is incorrect. It belongs to behavioral and emotional disorders, not speech sound production. Using the wrong code here will trigger an audit flag immediately. The limitations of ICD-10 for articulation disorders are worth stating plainly. The system does not capture severity well. There is no code that distinguishes mild, moderate, or severe articulation impairment. You can add Z codes for associated factors — like Z55.0 for educational problems or Z63.4 for family circumstances affecting care — but the core diagnostic codes are blunt instruments. If you are working in a setting that requires granular tracking of treatment progress, ICD-10 alone will not serve you. You need a separate speech-language pathology assessment tool alongside the coding. The ASHA standardized assessments or the Clinical Assessment of Speech Sound Production give you the detail that ICD-10 strips away. Also, ICD-10 does not differentiate between organic and functional articulation disorders within F80.0. A child with a structural anomaly like a short lingual frenulum and a child with purely learned incorrect sound patterns both map to the same code. The documentation needs to carry that distinction because it changes the treatment approach entirely. Structural cases may need surgical referral before therapy begins. Functional cases go straight to articulation therapy.
If you are building a billing workflow around this, here is a practical sequence that works. Review the patient's history first to determine developmental versus acquired onset. Then confirm with the diagnosing clinician whether there is any co-occurring language disorder. Code F80.0 only when articulation is the isolated deficit with developmental onset. Use R47.0 for acquired speech sound disorders. Cross-reference against R47.1 to make sure apraxia is not present but being miscoded. Document functional impact in the clinical notes even though the code itself does not reflect it. Run a secondary payer check if the claim involves a special education context, since some plans require IEP documentation alongside the diagnosis code. I have spent enough years watching articulation disorder coding get simplified into a single checkbox that I no longer trust the easy path. The codes exist to distinguish, not to lump. Getting them right takes a few extra minutes at the chart review stage but saves weeks of rework later.
Get the Full Details