The Actual Mechanics of Getting Your Records Out of MyChart
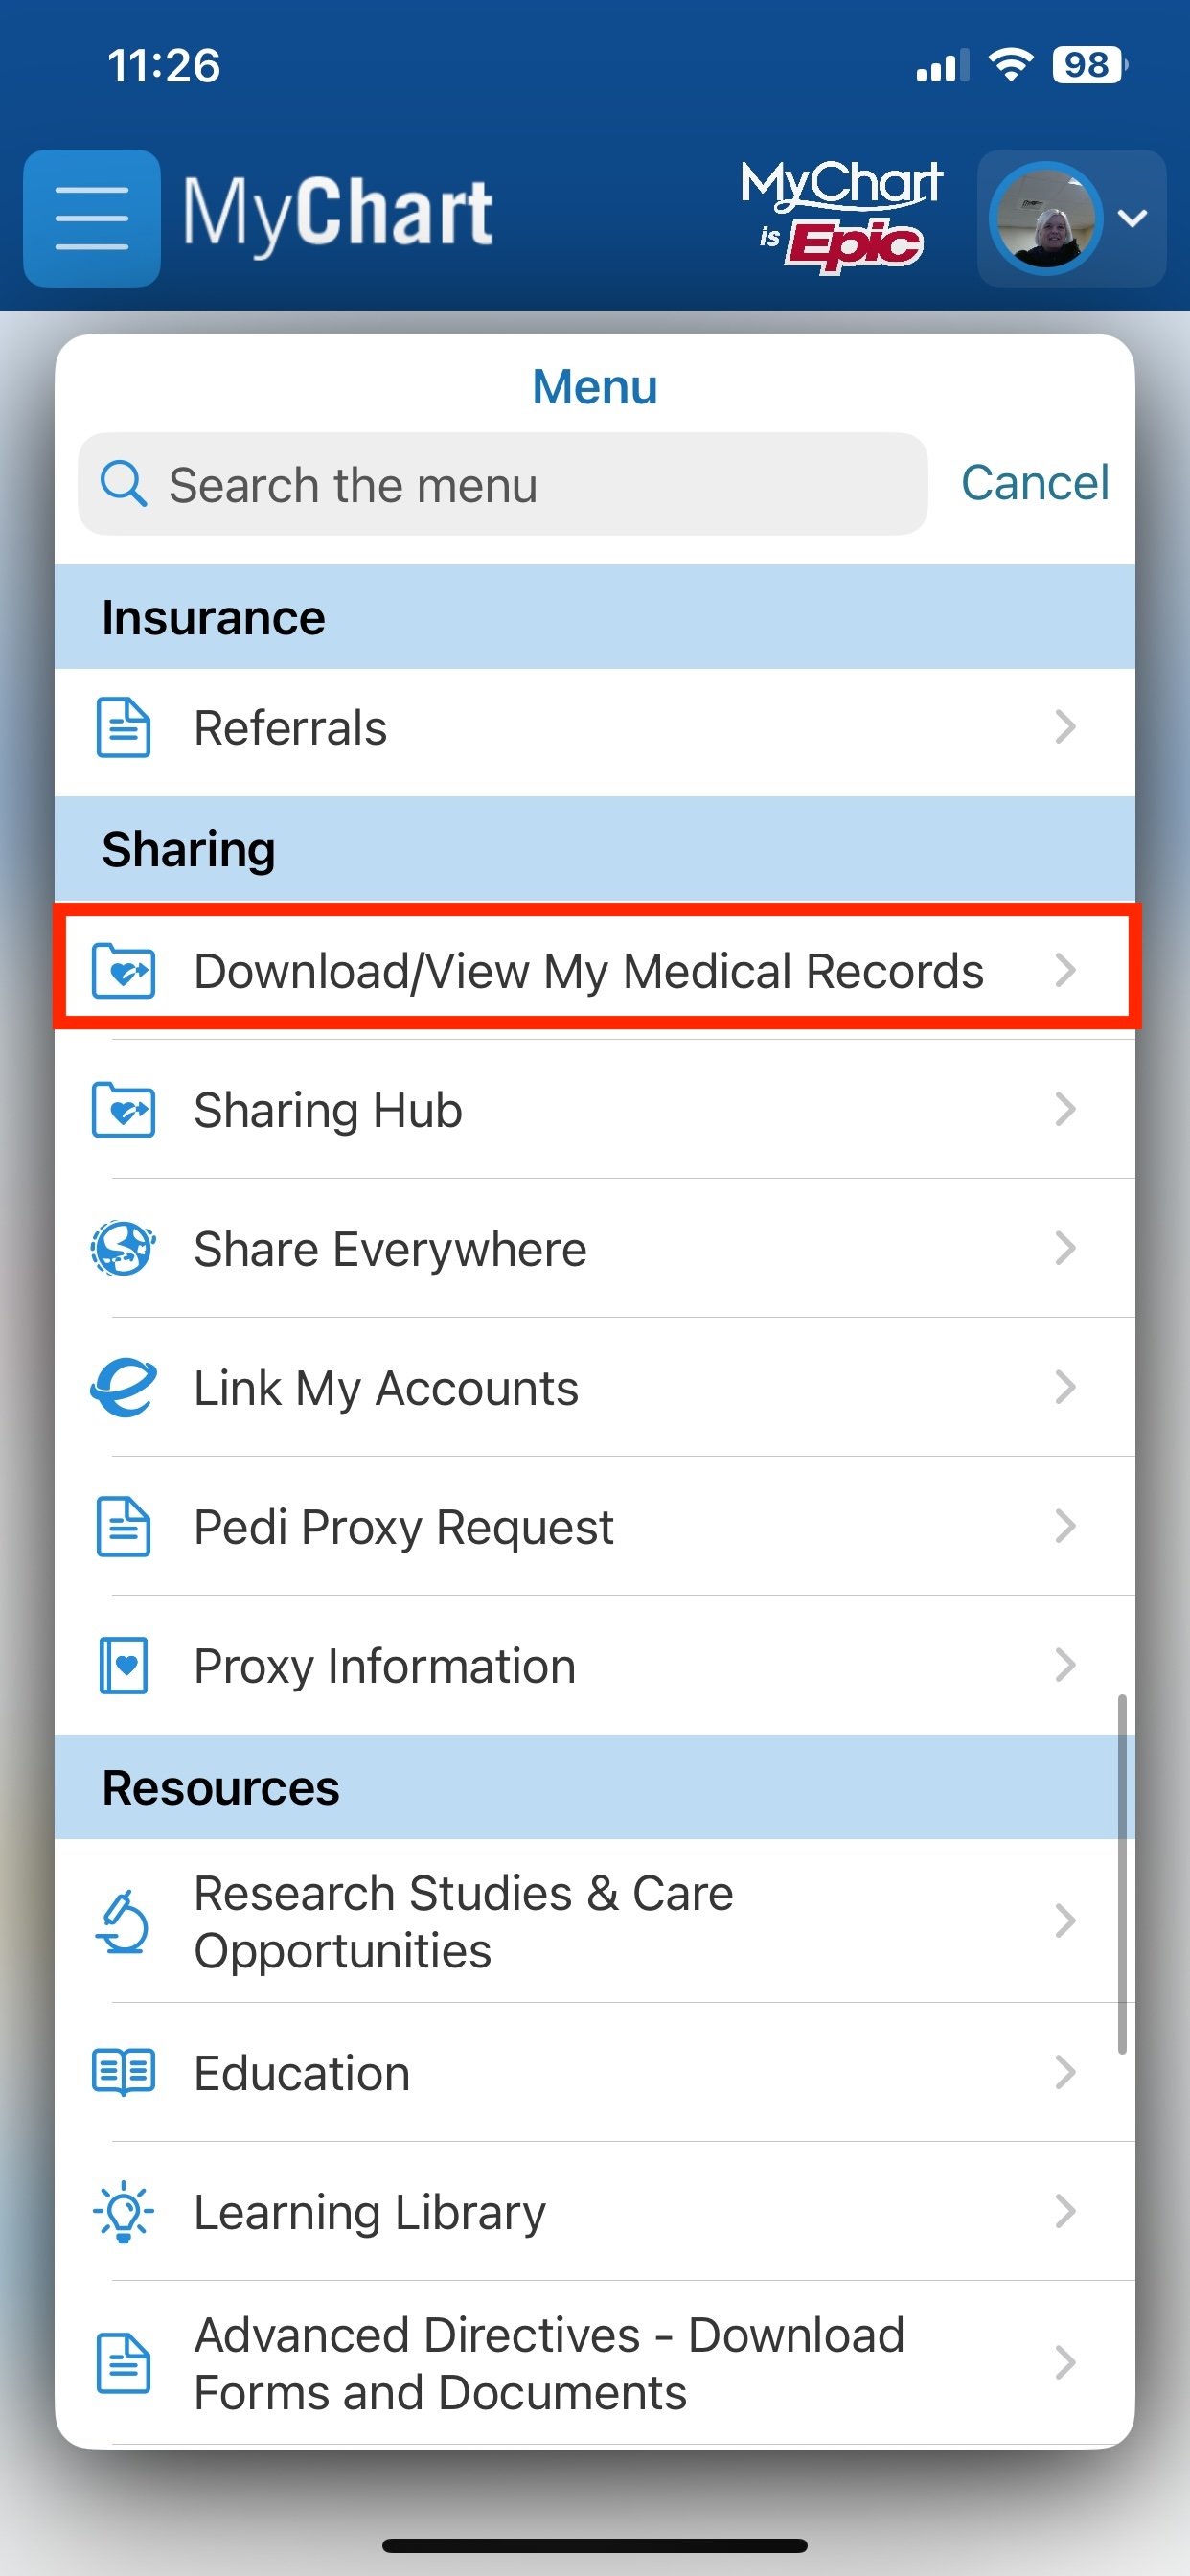
Most people I talk to think MyChart is just a glorified app for checking lab results. It isn't. It is an entire patient-facing layer on top of Epic's electronic health record system, and if you are trying to work with it at an administrative or technical level, treating it like a simple portal will get you nowhere fast. At my organization, we run Epic and have had to deal with the friction between what patients expect from MyChart and what the system actually delivers. The transformation is real, but it is uneven. Patients can request records, view medications, message providers, and see lab results without calling the medical records department. That cuts our release-of-information queue significantly. In a typical month, we went from processing roughly 400 manual requests down to about 80 after patients got comfortable with the portal. That is not a small number. Here is the part nobody puts in the marketing brochure: MyChart does not natively support bulk data export for patient populations. If you are a practice manager and you need to pull one year of records for fifty patients, you cannot just select them in MyChart and hit export. I learned that the hard way in 2023 when a compliance audit asked for a focused data set from our ambulatory clinics. The request came in on a Thursday. We had two weeks. My first instinct was to go through the patient portal and ask people to download their own records. That process took about eleven days and only forty-two percent of patients responded. The remaining fifty-eight percent were a mess of half-filled PDFs and corrupted attachments because the portal generates documents differently depending on browser, device, and Epic version.
The workaround I ended up using was to pull the data directly from Epic's reporting workbench using a custom SQL query that joined the patient encounter table with the document imaging repository, filtered by date range and encounter type, and then output to HL7-format messages for distribution. It took about four hours to build the query, another three to validate the output against a sample of paper records, and roughly two hours to send the files out through our secure upload system. Total time: about nine hours. Doing it through the portal would have dragged on for weeks and still come back incomplete. The key insight most people miss is that MyChart is not a data system. It is a presentation layer. The real data lives in Epic's underlying tables, and the portal just renders subsets of it in a patient-friendly format. When you are dealing with records management at scale, you need to think in terms of the backend first and the portal second. The portal is useful for individual patient engagement and routine access. It is not built for bulk operations, compliance requests, or interoperability workflows. Another counter-intuitive thing I discovered involves the way Epic handles document generation in MyChart. Different modules produce different output formats. Problem-based summaries come out as C-CDA documents. Lab results render as PDF tables. Clinician notes may appear as either PDFs or plain text snippets depending on how they were authored and whether dictation transcription happened. If you are building an automated pipeline that depends on consistent document structure, you will run into edge cases quickly. I spent about six weeks debugging a parsing script that kept choking on transcribed notes that had inline formatting artifacts from Epic's speech recognition engine. The fix was to strip non-printable characters at the ingestion point and normalize line breaks before any downstream processing.
If you are implementing MyChart at the organizational level, here is what actually matters: First, configure the identity proofing flow correctly from the start. Epic defaults to a fairly lenient activation process that allows patients to self-register with just an email address and a phone number verification code. This sounds convenient until you realize that any patient with a valid email and phone can activate an account tied to their record. I have seen cases where family members activated accounts for elderly relatives without consent, and a few incidents where patients accidentally linked to the wrong record because a clinic had duplicate MRNs. The fix is to require photo ID verification or at minimum a visit-to-activate model where patients get an activation code from their provider during an appointment. This adds about thirty seconds to the onboarding flow but eliminates the majority of linkage errors and unauthorized access complaints. Second, set up the secure messaging rules before you go live. MyChart messaging is asynchronous and stored in the clinical inbox system, but it is not equivalent to a traditional patient communication platform. Messages are logged in the medical record and are subject to the same retention and disclosure rules as clinical documentation. I saw a practice that treated MyChart messages as informal quick-check-ins and never assigned clinical staff to monitor them. Patients went months without responses and then filed grievances claiming lack of access. The workaround was to implement a triage workflow where messages were routed to the appropriate care team based on keywords, with a maximum response time of twenty-four hours for clinical questions and four hours for urgent flags. Response rates went from about thirty-five percent to nearly ninety percent within sixty days.
Get the Full Details
Third, understand the limitations around third-party app connections. Epic supports Apple Health and other consumer health apps through the FHIR API, but the data share is intentionally limited. Most third-party apps can pull problems, medications, allergies, and lab results. They cannot access clinical notes, care plans, or sensitive documents unless the organization explicitly enables those data sets through a configuration setting that is not exposed in the standard portal setup. I had a patient who was using a diabetes management app that kept showing incomplete data and she assumed the app was broken. It turned out her organization had not enabled the glucose log and continuous monitoring data export in Epic's external access settings. Once we enabled it, the app populated correctly. This is a configuration issue, not a technical limitation, and most organizations do not audit these settings after initial setup. The honest downsides are worth listing plainly. MyChart adoption rates vary wildly by patient population. In our geriatric clinics, roughly sixty percent of eligible patients never activate an account. The primary barriers are login complexity, lack of smartphone proficiency, and in some cases deliberate choice. Forcibly pushing digital access onto older patients without providing in-person onboarding support creates more frustration than it solves. We now require clinic staff to offer MyChart activation as part of the check-in process for patients over seventy-five, and we keep a stack of printed activation instructions at every desk. This takes about two minutes per patient and increases activation rates in that demographic to about eighty percent. Another limitation is the cost of customization. Epic environments are highly configurable, and every customization requires a certified implementation partner. Adding custom fields, modifying report templates, or building integrations outside the standard Epic ecosystem can cost anywhere from fifteen thousand dollars to over two hundred thousand dollars depending on scope. We budgeted for a basic MyChart rollout and ended up spending approximately forty-seven thousand dollars on identity verification configuration, messaging triage setup, and the custom reporting query framework that replaced our manual record-pulling process. That was a one-time cost, but it caught us off guard because the standard implementation package does not include these enhancements.
If your organization is small enough that Epic customization is not feasible, the alternative is to use a third-party patient engagement platform that integrates with Epic through the Cast integration framework. Platforms like MyWellConnection or Qvera Engage can handle patient communication, records requests, and engagement analytics without requiring deep Epic customization. They cost less upfront but introduce another vendor relationship and a different data flow to manage. Whether that tradeoff is worth it depends on your volume and staffing. The bottom line is that MyChart works well for what it was designed for: giving individual patients convenient access to their own health information. It does not work well for bulk records management, compliance reporting, or interoperability at scale. If you treat it as the former, you will be fine. If you try to make it do the latter without understanding the underlying system, you will waste time and money. The workarounds I described above are not elegant solutions. They are practical fixes that come from dealing with the system in production, not from reading the product documentation.