Setting Up Zoetis DXS Rapid Diagnostic Systems in a Busy Clinic
I spent about three years troubleshooting and optimizing our in-house diagnostic workflow after switching to the Zoetis DXS platform. Most people selling these systems talk about turnaround times in glossy brochures, but they rarely mention the setup headaches or the specific conditions where the whole thing falls apart. Here is what actually happens when you put this equipment on a clinic floor. The core concept behind the DXS line is straightforward. You load a cartridge, press a button, and the instrument runs a nucleic acid or immunoassay test and returns a quantitative result. The difference from older PCR systems is mostly in the cartridge design and software integration. Samples go in, results come out in roughly 15 to 45 minutes depending on which assay you run, and the system logs everything automatically for your medical records. Let me be direct about what this means in practice. Before we had DXS, a positive heartworm antigen test took 10 minutes and cost about $35 per cartridge. A canine respiratory panel using our old lab-based PCR might take 90 minutes to two hours if we ran it that day, or the next day if we had to batch specimens. With the DXS respiratory and GI panels, I routinely get full pathogen profiles back in under 30 minutes while the patient is still on the table. That changes the entire conversation with the client. You can prescribe the right antibiotic on the first visit instead of guessing and sending them home with doxycycline and a prayer.
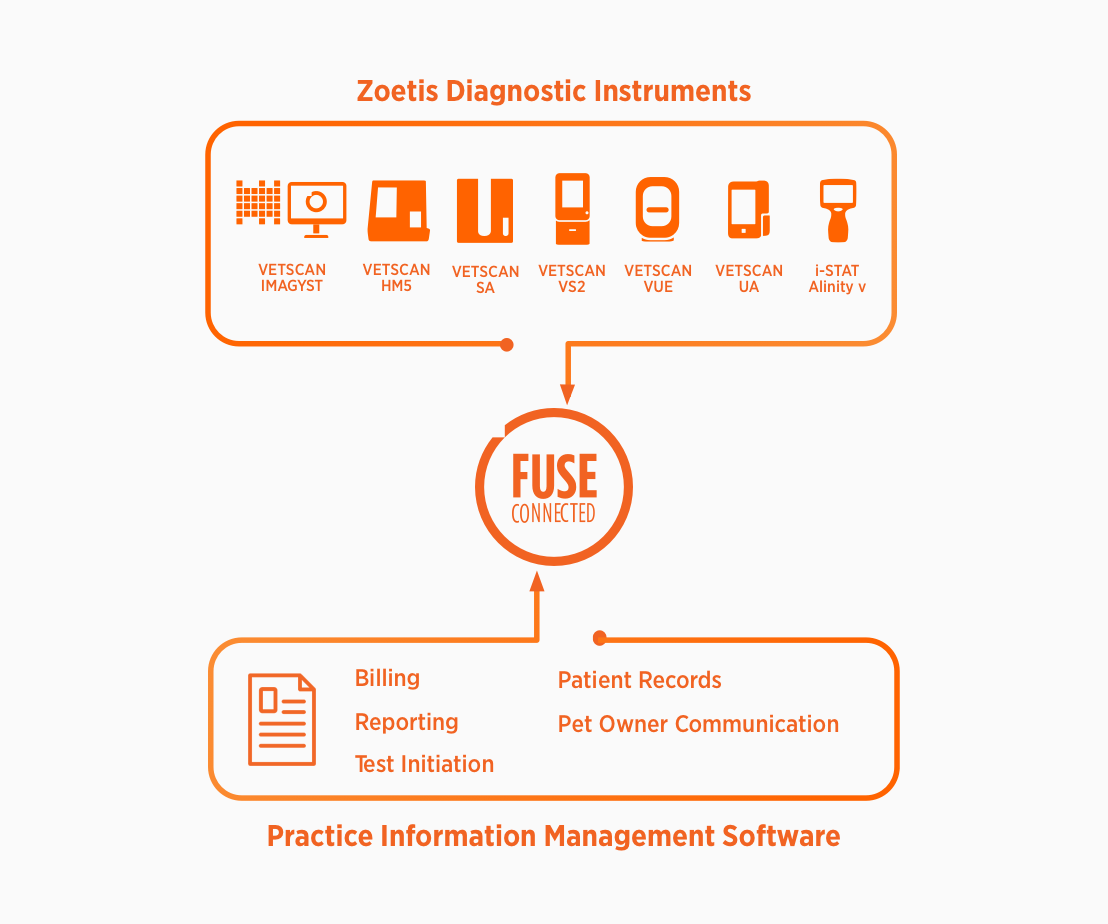
Here is the part nobody puts in the sales deck. The system is sensitive to ambient temperature and humidity in ways that are easy to overlook. Our clinic sits in a space where the HVAC cycles hard during winter, and for about six months we were getting sporadic instrument errors that traced back to the cartridge storage area. The solution was moving the instrument away from the wall, installing a small desk fan for air circulation, and keeping the reagent cartridges in a dedicated cabinet rather than the main exam room. Once I did that, failure rates dropped from roughly one in every 20 runs to maybe one in 80. The software side deserves attention too. DXS instruments integrate with most major practice management systems through HL7 messaging. Setting that up properly takes patience. I spent about a week working with our IT person and a Zoetis field rep to get the result routing correct. The default configuration will dump results into a generic inbox somewhere in your practice management software, which is useless if you are running multiple instruments or sharing a server. You need to map each instrument to its own workstation terminal and set up auto-populate rules for the diagnostic test fields. Without that, technicians end up manually typing results back in, which defeats the entire purpose of having the system. I ran into a specific edge case that almost made us return the instrument. We were running the canine tick-borne disease panel on a series of clients from an area with high Ehrlichia and Anaplasma prevalence. About a month in, I noticed that three dogs with confirmed clinical ehrlichiosis were testing negative on the DXS assay. I called Zoetis technical support and got put on a webinar with their clinical pathologist. The issue turned out to be the window for detecting chronic Ehrlichia infections. The DXS test uses a different primer target than some of the older PCR assays, and in chronic cases with lower organism loads in peripheral blood, the sensitivity drops noticeably. It is not a flaw in the system, it is a limitation of the assay design. For acute infections the results are solid. For chronicehrlichiosis you still need to supplement with IFA serology or send out to a reference lab. I now flag any chronic-appearing patient with negative DXS tick results for follow-up testing rather than dismissing them outright.
Another thing that catches people off guard is the cost per test calculation. The instruments themselves are reasonably priced, but the cartridges carry a premium. A single multi-pathogen panel can run you between $60 and $90 per test depending on which assay and which volume pricing tier you negotiate. That is significantly more than sending samples out to a reference lab, which might charge $45 to $65 per panel with slower turnaround. The tradeoff is the speed and the ability to make clinical decisions in real time. In my experience, the increased revenue from appropriately treated same-day cases more than offsets the higher per-test cost, but you have to do the math for your own client base. If your practice mostly sees low-income owners who bring in sick animals without much money to spend, the economics work differently than they do in a referral-heavy or suburban practice. Cartridge inventory management is its own small disaster waiting to happen. These things have expiry dates and they are not cheap to toss. I recommend ordering in smaller batches more frequently rather than stockpiling a year's supply. The reagents degrade over time even when stored properly, andZoetis does not typically honor returns on near-expired cartridges. Keep your par levels tight, track usage weekly, and adjust your ordering cadence based on actual test volume, not projected volume from six months ago. Quality control is another area where people get complacent. The instrument runs internal controls with every cartridge, which is good, but you should also be running external QC material at least once a week if you are running tests daily. Third-party QC material costs maybe $40 to $60 per run and gives you a paper trail that matters if a result ever gets questioned. I have seen practices skip this to save money and then struggle to defend their results when a client disputes a diagnosis. It is not worth the risk.
Get the Full Details

The technician training curve is gentler than older PCR systems but not flat. A competent vet tech can be running independent cases within about two weeks of initial training. The first week is mostly doing supervised runs and learning the troubleshooting protocols. After that, they handle it themselves. The interface is intuitive enough that you do not need a dedicated instrument specialist on staff. That said, someone needs to own the system. Without a designated person responsible for QC logging, cartridge ordering, and error resolution, the whole thing degrades into whatever technician happens to be working that day, and inconsistency creeps in fast. One counter-intuitive thing I learned the hard way: more testing is not always better. When we first installed the system, there was a temptation to run every possible panel on every respiratory or GI case. We went from ordering maybe 15 infectious disease panels a month to over 60. The data showed that roughly 40 percent of those additional panels returned negative results that did not change the treatment plan. The clinical takeaway was the same whether we tested or not because the empirical treatment approach for mild cases does not shift based on pathogen identification. The smart move is to restrict panel testing to moderate-to-severe cases, hospitalizations, and patients that are not responding to initial therapy. For mild upper respiratory cases that are going home with supportive care anyway, you are spending money for information that does not change the outcome. If you are considering this system, the practical steps are simpler than the literature makes it seem. Negotiate cartridge pricing aggressively, especially if you are committing to a multi-year equipment lease. Get the HL7 integration working correctly before you start running tests, because fixing it retroactively is painful. Assign one person to own the instrument. Track your per-test costs against your revenue impact monthly for the first six months. And accept that no single diagnostic platform covers every scenario, particularly chronic infections where older serological methods still hold an edge.
The bottom line is that DXS systems are a meaningful upgrade for clinics that run a high volume of infectious disease testing and want same-day results. They are not a magic bullet, they require ongoing management, and they have real limitations in certain clinical scenarios. But when they work, which is most of the time, they genuinely change the pace and quality of patient care in a way that is measurable and noticeable to both the staff and the clients.