
Medical Device Development: A Long Road With Few Shortcuts
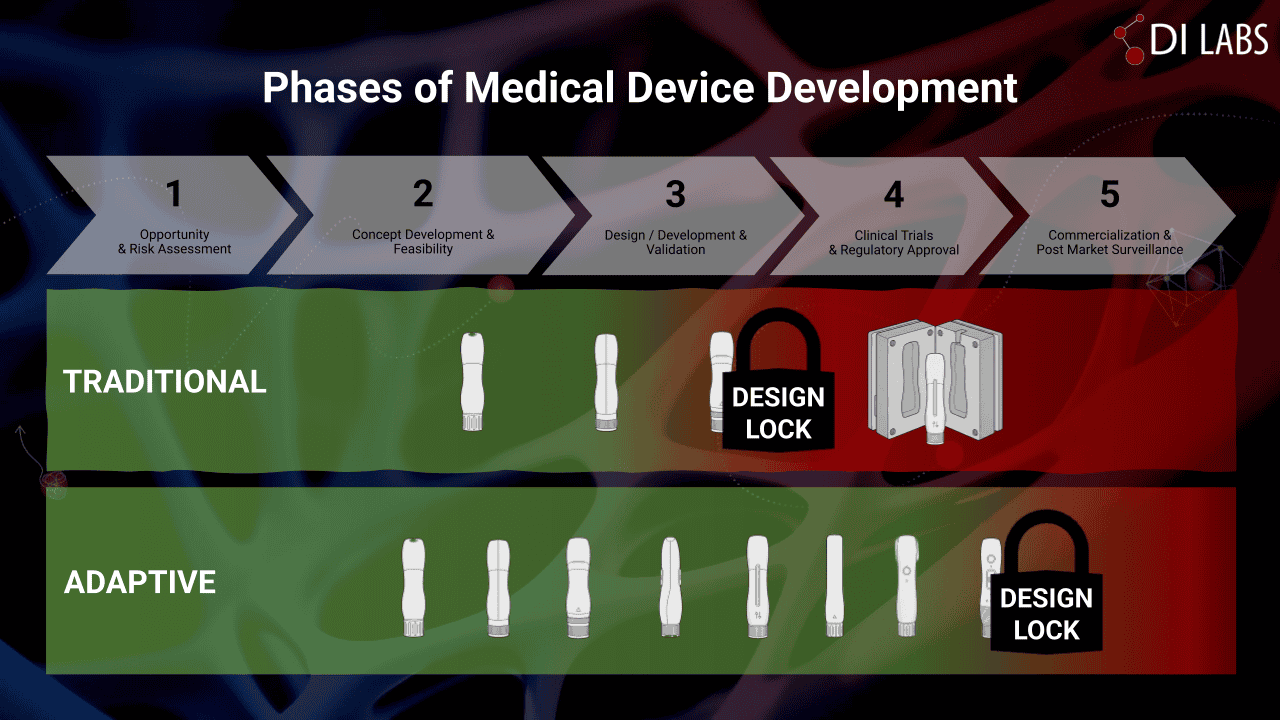
The medical device industry is one of the most heavily regulated spaces you can work in. If you've spent any meaningful stretch of time in it, you already know that "innovation" is often the first casualty of the process. You build something novel, then you spend eighteen months writing documentation to justify its existence to regulators. Tricia Lucus worked through exactly this tension, and her approach ended up mattering more than any single product she contributed to. I'm going to walk through what that actually looked like in practice. At the core, her contribution came down to reframing how early-stage medical devices handle regulatory strategy. Most teams treat regulatory compliance as a phase that starts after the design is basically complete. Lucus pushed back on that timeline repeatedly. She advocated for building regulatory input into the concept phase rather than bolting it on later. The difference between those two approaches is usually measured in months of rework and sometimes entire product lines getting killed at clinical validation because someone missed a critical requirement early on. I worked on a vascular access device project where we learned this lesson the hard way. We had a working prototype at the concept validation stage when the regulatory team flagged that our biocompatibility testing plan didn't align with the intended labeling claims. That discovery came at month fourteen of an eighteen-month development cycle. We had to pause everything and redesign a significant portion of our testing matrix. It cost us roughly six weeks and about forty thousand dollars in delayed expenses. If we'd had a Lucus-style integrated framework from the start, that conversation would have happened during week three.
How The Integrated Regulatory Framework Actually Works
The model Lucus helped popularize treats regulatory requirements as design constraints rather than post-design audits. This means you map the full regulatory pathway before you commit to a design direction. For a class II device in the United States, that involves understanding 510(k) requirements, substantive equivalence thresholds, and applicable guidance documents simultaneously. Most teams don't do this until they're deep into prototyping, which is when the most costly changes become necessary. Here's what the practical implementation looks like: First, you identify your device class and the primary regulatory pathway during the very first design review meeting. Not the second review. The first one. This forces the engineering and regulatory teams to sit in the same room at the same time, which sounds obvious but rarely happens organically.
Second, you create a living regulatory traceability matrix from day one. This document tracks every regulatory requirement back to a specific design input and forward to a verification or validation activity. When someone proposes a design change, you cross-reference the matrix immediately instead of hoping nothing breaks. I use a simple spreadsheet-based system for this on smaller projects, and it scales adequately through the design history file stage. For larger programs, you'll want something more robust, but the principle stays the same. Third, you establish a requirements prioritization system that weights regulatory requirements above performance enhancements during early development phases. This is counterintuitive for engineering-heavy teams who naturally want to chase performance metrics. But a device that meets every performance spec but fails biocompatibility is useless. The reverse is also true though, and that's where the real expertise comes in.
Get the Full Details

The Uncomfortable Truths About Medical Device Innovation
Most people entering this field don't hear about the parts that actually slow projects down. The FDA's Quality System Regulation isn't a checklist you complete. It's an ongoing operational state that requires continuous maintenance. Auditors don't care about your elegant design if your design controls documentation has gaps. I've seen perfectly functional devices fail premarket approval because the design history file was assembled reactively instead of being built incrementally. Another thing nobody warns you about: the 510(k) pathway is increasingly uncertain for novel devices. The FDA has been tightening substantively equivalent determinations, particularly in categories involving software and digital health components. A strategy that worked cleanly two years ago may not land the same way today. Lucus was ahead of this shift, which is why her emphasis on early regulatory engagement remains relevant. She recognized that submission timelines were stretching and that sponsors needed more flexibility in their approach. There's also the international dimension. If you're developing a device for both the U.S. and EU markets, you're now navigating MDR requirements alongside FDA processes. The MDR transition effectively increased the evidentiary burden for many Class II devices. Clinical evaluation requirements alone can double the scope of your clinical documentation. Teams that only thought about one regulatory pathway got blindsided. The workaround is straightforward but expensive: engage a regulatory consultant with MDR-specific experience during the planning phase, not after you've already received a deficiency letter.
Practical Steps You Can Take Right Now
If you're leading or participating in a medical device development project, here's what actually moves the needle: Schedule a regulatory pathway analysis meeting before you finalize your concept design. This shouldn't take more than a single focused session with the right people in the room. The output is a clear roadmap of what evidence you'll need and when you'll need it. Budget accordingly. Most teams underbudget regulatory activities by at least thirty percent. Built a cross-functional design review board that includes regulatory, quality, and clinical representatives from the outset. Not as advisors who get consulted when problems appear. As active participants in design decisions. This changes the conversation from "can we build this" to "can we build this and prove it meets regulatory requirements." The second question saves more time in the long run.
Start your Design History File on the first day of the project. Even if it's just a folder with properly dated records. A DHF that gets assembled at the end of development is almost always incomplete. Evidence of design reviews, change controls, and verification results tends to get lost or reconstructed imperfectly. Reconstructed records don't survive audits well. Invest in understanding your specific device's predicate landscape if you're pursuing a 510(k). Predicate selection is both an art and a liability. Pick the wrong one and your submission gets complex questions that slow review cycles by months. I once saw a submission delayed nine months because the selected predicate had a significantly different intended use statement than the sponsor's device. The reviewer caught it during the initial completeness check.
Where This Approach Falls Short
I should be honest about the limitations. This framework doesn't work well for teams with severe resource constraints. Small startups without dedicated regulatory staff often can't sustain the documentation rigor this approach demands. In those cases, the most practical path is outsourcing regulatory strategy to a contract regulatory affairs organization while maintaining internal oversight. It costs money upfront but prevents far more expensive delays downstream. The framework also assumes you have access to current regulatory guidance documents. Those change regularly. A strategy built on guidance from two years ago might not hold up today. I check FDA guidance databases monthly and subscribe to regulatory newsletters from firms like RegReg and RAPS. The information overload is real but the cost of missing a guidance update is higher. Finally, this approach doesn't replace technical excellence. You still need a well-designed device that works reliably. Regulatory readiness and product quality are complementary, not interchangeable. I've seen teams that nailed the paperwork but shipped a product that failed in the field. That's a different failure mode but equally expensive.
Tricia Lucus's work matters because it addressed a structural gap in how medical device development is organized. The gap hasn't disappeared entirely. Teams still too often treat regulatory compliance as a separate track from engineering. But the awareness has grown, and the frameworks that address it are more accessible now than they were even five years ago. The people who use them strategically will ship better products faster. The people who ignore them will learn the hard way what most of us already know.



