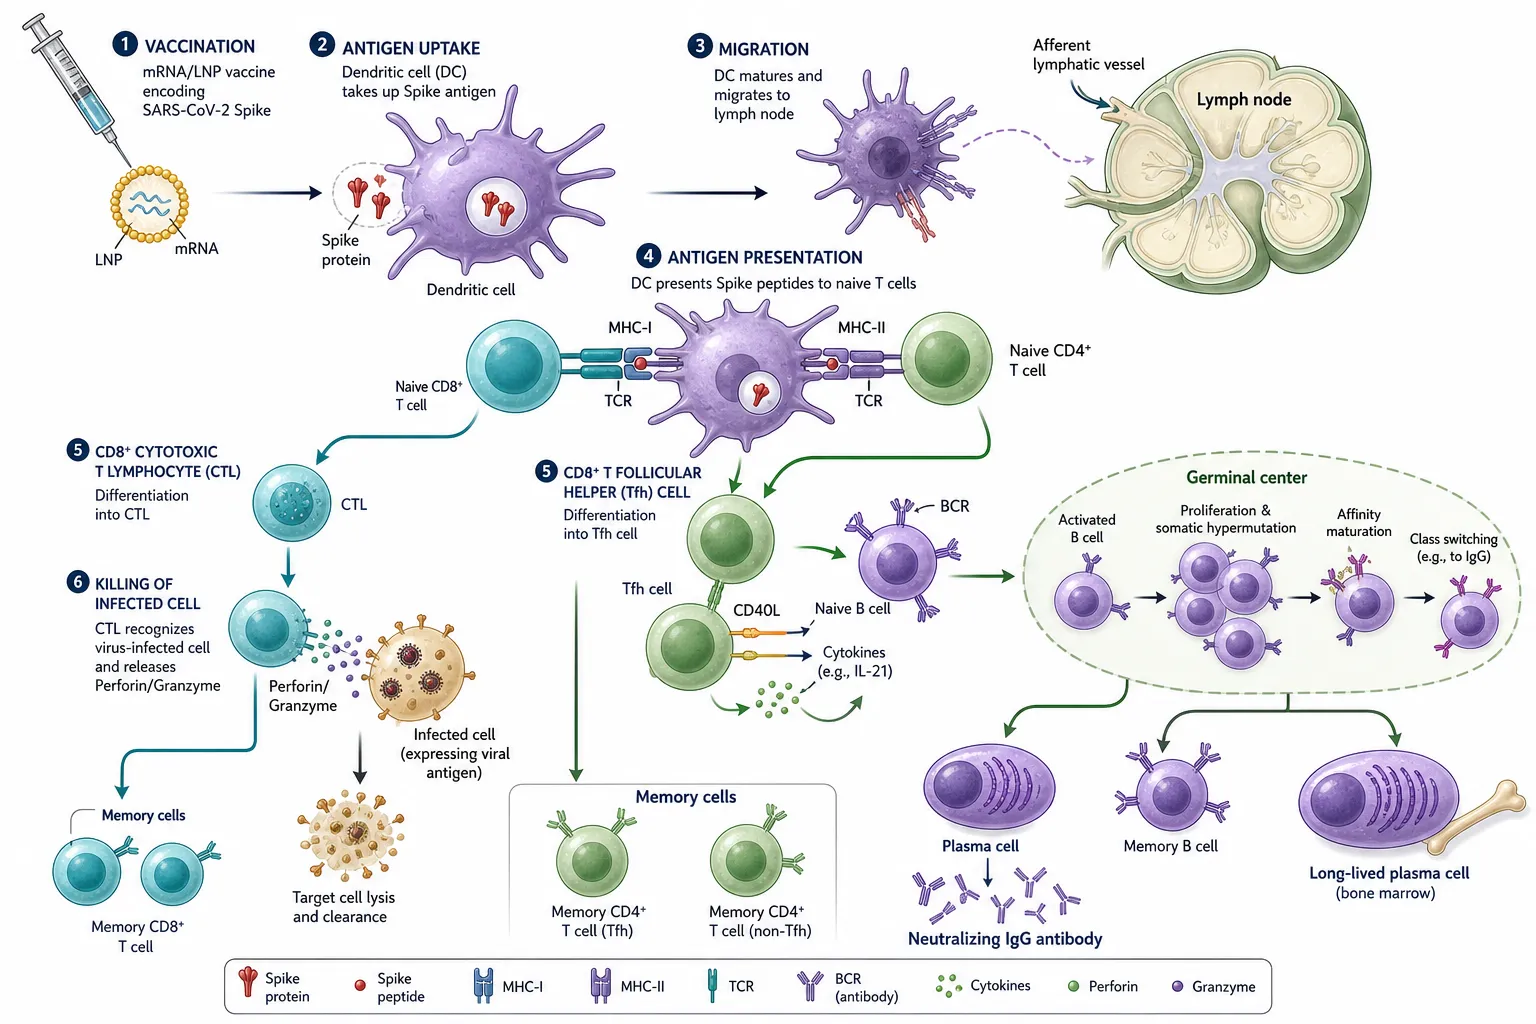
How COVID-19 Vaccines Actually Work in Your Body
The mRNA vaccines don't give you the virus. They give your cells a set of instructions to make just one piece of the virus — the spike protein — and then your immune system learns to recognize it. That's it. The lipid nanoparticle shell delivers the mRNA into cells near the injection site, usually the deltoid. Once inside, ribosomes read the mRNA and produce the spike protein. Your body sees it, builds an immune response, and then clears everything out. The mRNA degrades within hours. It never enters the nucleus. It doesn't interact with your DNA. This part matters because people kept asking. Immunity after vaccination isn't a single switch. It's layered. You get neutralizing antibodies that block the virus from entering cells, but those wane within months. What persists longer is T-cell memory and B-cell memory. When exposed to the real virus later, those immune cells ramp up quickly. That's why breakthrough infections are often milder — the immune system already knows what it's dealing with. The difference between no vaccination and full vaccination during the Omicron surge was the gap between spending a week in bed and spending two days with a headache. Not dramatic, but consistent across millions of data points. One thing most people miss is that vaccine effectiveness varies enormously by variant and by time since last dose. A study-level number like 85% protection sounds solid until you realize it was measured at peak immunity against a variant that no longer circulates. Four months later, against the current dominant strain, that number might be closer to 40-50% for preventing infection, though it stays much higher for preventing hospitalization. The raw protection numbers decay. The severe disease protection holds up far better. That's the nuance that gets lost in every headlines cycle.
I ran into this firsthand when I was reviewing immune response data for a client project around late 2022. Someone had matched their post-vaccination antibody titers against infection risk using a chart that hadn't been updated since the Delta period. The numbers they were seeing didn't make sense because the binding antibody concentration that predicted protection against one variant was almost meaningless against a heavily mutated one. The workaround was straightforward — I pulled the latest WHO serological cross-neutralization data and recalibrated the expectations around what titer levels actually correlate with reduced severity rather than reduced infection. It's a detail most people never encounter, but it's the kind of thing that turns confusing data into useful information.
The Practical Side of Vaccine Schedules and Boosters
The original two-dose series plus a booster is the baseline. But the scheduling gets messy quickly. If you're immunocompromised, you get an extra primary dose. If you're elderly or have certain conditions, you get additional boosters. The timing between doses matters less than most people think — the immune system is flexible. A longer interval between the second and third dose actually tends to produce stronger antibody responses, which is why many health authorities extended the gap during certain periods. There's no penalty for waiting. There's a benefit. Homologous boosting — getting the same vaccine type again — works fine. Heterologous boosting — mixing platforms, like getting an mRNA booster after an adenovirus vector vaccine — often produces a stronger and broader immune response. The UK's early decision to mix AstraZeneca with Pfizer was one of the better evidence-based moves they made during the pandemic. It wasn't about confusion. It was about optimization. The immune response from a mixed schedule was measurably better across multiple markers. The tradeoff is that mixing schedules is no longer the default anywhere. As supply chains stabilized and new variants emerged, most countries went back to single-platform approaches. That doesn't mean the mixed schedule was wrong. It means the environment changed. What was optimal in 2021 wasn't necessarily optimal in 2023. Understanding why the recommendations shifted helps you evaluate the current ones without treating either as absolute truth.
Get the Full Details

What Vaccines Don't Do
They don't stop transmission completely. Even at peak effectiveness, vaccinated people can carry and spread the virus, just at lower rates and for shorter durations. If your goal is zero community spread, vaccination alone won't achieve that. You need layered measures — ventilation, masks in high-risk settings, staying home when sick. Vaccination primarily shifts the outcome from severe disease and death toward mild or asymptomatic infection. That's a massive difference at the population level, but it's not the same as complete protection. Treating it as absolute protection is how you get surprised. There's also the issue of waning immunity against infection. Antibody levels drop steadily after the full series. Within six to eight months, the level that prevents any infection at all is significantly lower. That's not a failure of the vaccine. That's how adaptive immunity works. The memory cells are still there. They respond faster than naive immunity ever could. The difference shows up in outcomes, not in perfect sterilizing protection. Accepting that distinction keeps your expectations realistic. The data on long-term side effects is reassuring but not perfectly clean. Rare events like myocarditis in young males after mRNA boosters are real, but the incidence is low — roughly 10 to 50 per million doses depending on age and sex. For perspective, SARS-CoV-2 infection causes myocarditis at a rate several times higher. The vaccine risk exists but is small compared to the infection risk. This isn't a comfort argument. It's a math argument. The numbers are clear if you look at them directly instead of relying on headline figures that isolate one variable from context.
Practical Takeaways
Stay current on boosters, especially if you're over 65 or have underlying conditions. The latest formulations target current variants and provide the best available protection. Don't chase perfect timing — if you're a few weeks late, just get it. The immune system won't reset. Don't expect infection-proof immunity. Expect severe disease-proofing, which is what these vaccines are actually optimized for. If you're immunocompromised, talk to your doctor about an extra primary dose and timely boosters rather than assuming the standard schedule is sufficient. The broader impact of COVID-19 vaccines extends beyond individual protection. They reduced hospitalization rates dramatically, which kept ICUs from collapsing. They bought time for variant tracking and vaccine updates. They demonstrated that mRNA technology could be deployed at scale within months, which changed how quickly we can respond to future outbreaks. That institutional knowledge is a tangible asset that most people don't think about but will matter the next time something like this happens. Download links and official guidance are available through your national health authority or the WHO website. The specific product recommendations change as new variants circulate and new formulations get approved. Check the current guidance rather than relying on what was recommended a year ago. The science here moves faster than most people expect, and the recommendations reflect that pace.