Getting Work Done With the Tricare Provider Portal
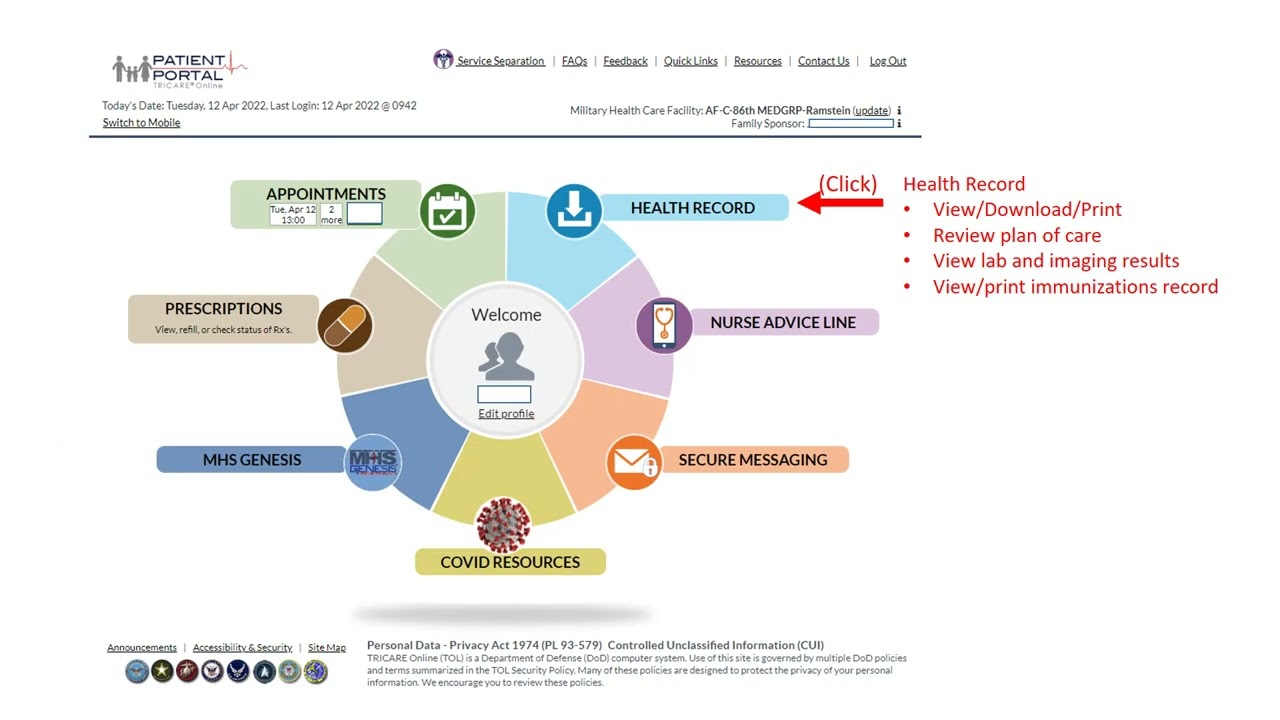
The Tricare Provider Portal is the primary web-based interface for military healthcare providers to manage claims, check eligibility, and access patient records across the defense health system. It replaces the older paper-heavy submission workflow that used to dominate billing cycles. Most clinics that contract with TRICARE eventually have to figure out how to use it, whether they want to or not. I spent about three years integrating our small orthopedic practice into the TRICARE ecosystem before I figured out the quirks. The portal itself is functional but stubborn. It loads slowly, its search functions are imprecise, and the training materials it points you toward are more aspirational than practical. What follows is what actually works when you stop trying to read the help documentation and start paying attention to the patterns.
Unlocking Healthcare Efficiency A Deep Dive Into The Tricare Provider Portal
Access and login You start at the DELOSA domain. If you are a provider, you need a validated DoD CAC or Common Access Card. The initial registration process routes through the Defense Enrollment Eligibility Reporting System, which means you cannot self-enroll from scratch — someone with supervisor privileges in your organization has to sponsor your account first. This is the first bottleneck. Our practice wasted two weeks waiting on a sponsor who kept deferring it because "someone else would handle it." Once your account is active, log in through the authorized DELOSA path. You will be routed to the main dashboard where claims, eligibility verification, and remittance advice live. The interface hasn't fundamentally changed since about 2019. It is what it is.
Eligibility checks that actually work Most people use the eligibility lookup as a one-time pre-visit step. That is inefficient. The real value is checking eligibility in real time during the encounter, especially for patients whose status changes frequently — active duty members getting reassigned, retirees turning 65, family members aging off at 21. I built a habit of running a quick eligibility check before every procedure, not just the first visit. It takes about thirty seconds and prevents the most common claim rejection reason: invalid benefit status at the time of service. Claim submission: the parts the help page doesn't explain
Get the Full Details
Claim submission through the portal supports both electronic CMS-1500 formats and institutional UB-04 files. The electronic claim process is straightforward if you have clean data. The problems arise from edge cases. Here is a specific issue I ran into repeatedly: secondary claim processing for beneficiaries who have both TRICARE and a commercial secondary payer. The portal's secondary claim workflow is buried under the claims module and not intuitively labeled. You cannot just attach a secondary claim to an already adjudicated primary claim. You have to submit it as a new claim with the primary payer information manually entered in the correct modifier fields. Our billing staff kept trying to use an "adjustment" function that doesn't exist in the way you'd expect. We lost about four days of cycle time per month on this until we realized we were submitting secondary claims incorrectly. The fix was documenting the primary adjudication details in the claim header and routing through the proper secondary submission path. Remittance advice and payment tracking
Remittance advice, or ERA, data becomes available in the portal typically within 7 to 14 business days after claim submission, depending on the regional TRICARE contractor processing your area. The ERA download is where most providers drop the ball. They check the payment notification and move on without reviewing the detail line. That is where you catch coding discrepancies, down-payments that don't match your fee schedule, and denials that slipped through the automated adjudication. I recommend running a weekly batch review of all ERA files rather than checking individual payments. It takes about twenty minutes for a small practice and surfaces issues that would otherwise sit undetected for a full billing cycle. Document retrieval and prior authorization
The prior authorization module is where the portal is most fragile. Requests submitted through the portal for specialty drugs, durable medical equipment, and certain surgical procedures often get flagged for manual review regardless of how complete your submission is. The portal doesn't give you a straight yes-or-no answer in most cases. You get a request ID and a waiting period that varies by request type. For standard authorizations, you can expect a response window of 3 to 5 business days. For complex cases involving investigational procedures or off-label drug requests, it can stretch to 15 days or more. The workaround I learned the hard way: if your authorization request hits the "pending manual review" status for more than 5 business days, call the TRICARE contractor directly for your region. The portal support line is not helpful for status escalation. Having your request ID and the exact date of submission when you call cuts the resolution time significantly. Practical limitations and where the portal fails

Let me be blunt about what this tool cannot do. It does not support bulk eligibility queries across large patient panels. If you are running a multi-provider clinic with hundreds of TRICARE beneficiaries, you will find yourself doing individual lookups instead. There is no batch verification endpoint that I am aware of, and the portal interface does not provide a spreadsheet export for eligibility data. This is a genuine workflow constraint that affects mid to large practices disproportionately. The portal also lacks real-time claim status updates. When you submit an electronic claim, the status does not update until the contractor processes it through their adjudication queue. There is no live tracking number you can check repeatedly. This means you cannot distinguish between "submitted and processing" and "submitted and rejected" without waiting for the next ERA cycle or checking manually through the claim search function, which only shows results after initial adjudication has occurred. For practices that handle high volumes of TRICARE claims, the portal works but it is not efficient by design. Some larger organizations bypass the portal entirely for claim submission and use direct EDI connections through a clearinghouse. The clearinghouse route requires a separate contractual setup and more technical integration effort, but it handles the volume problem and provides status tracking that the portal simply does not offer.
What to prioritize if you are setting this up for a new practice Start with eligibility verification workflows before you touch claim submission. Get your staff trained on the real-time eligibility check process. Then move to claim submission for straightforward outpatient services. Don't attempt inpatient or specialty drug workflows until you understand the basic claim cycle. The portal rewards gradual familiarity. Throwing complex authorization requests at it on day one usually results in confusion and missed details. Keep a internal log of request IDs, submission dates, and response times. This becomes useful when you need to escalate problems or audit your own processing timelines. The portal gives you limited reporting tools, so your own tracking spreadsheet fills the gap.
The portal is adequate for routine provider operations. It is not fast, it is not elegant, and it has gaps that will frustrate you at specific points. But it is the official channel, and learning its friction points saves more time than fighting against them.