Getting Started With the UC Davis Health Patient Portal
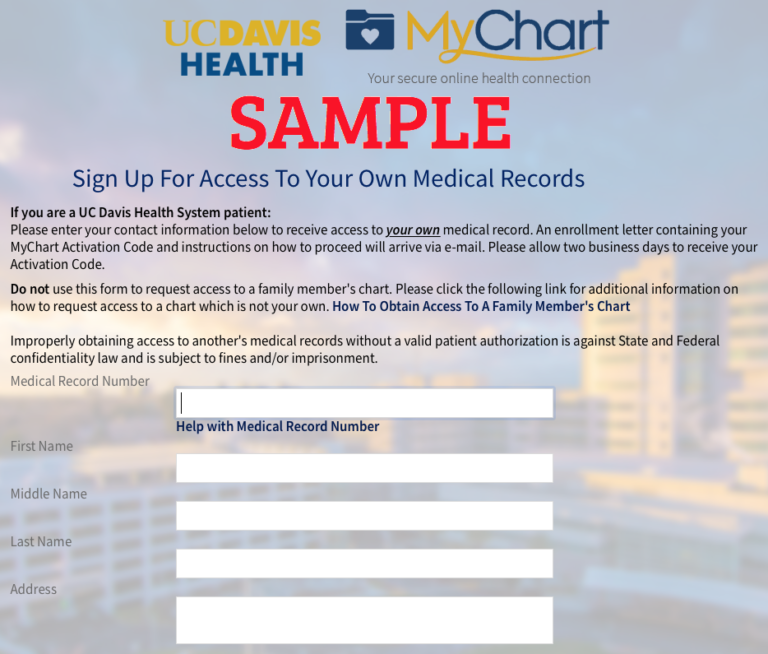
Setting up your account at uc davis health mychart is straightforward if you already have an active patient relationship with the system. You do not need to hunt down a special invitation code or call a help desk first. The portal pulls your demographics directly from the EHR, so as long as you have been seen at one of their facilities, the record exists. I walked a patient through this process last year who had been treated at the medical center for three years but never managed to activate his portal. He was frustrated because he kept getting the same password reset email loop for two days. The activation flow works through a time-limited join key that gets distributed either via mail or in-clinic at check-in. You go to the registration page, enter your date of birth, and the system matches it against the demographic table. If the match is clean, you create a password and you are in. If the system flags a potential duplicate—say someone else with the same name and DOB exists in the system—it pauses and asks you to verify additional identifiers. That is by design. It happens more often than people realize, especially with common names in a large academic medical center population. The actual transformation piece is not magic. It is just the shift from paper-based and phone-based access to a standardized digital interface. Before MyChart, lab results sat in a provider inbox until the next scheduled visit. Now they post automatically according to UC Davis' release policy, which typically means within 48 hours for most routine labs and immediately for imaging when the radiologist has signed the report. I have watched patients catch early abnormalities weeks sooner because they saw the result on their phone instead of waiting for a follow-up call that might take days to materialize.
There is a specific quirk with prescription refills through the portal that catches people off guard. The request goes to the ordering provider, but the pharmacy notification does not happen until a nurse or MA reviews it in the inbox. This usually takes one to two business days. During a recent winter flu surge, I had a patient who submitted a refill request on a Thursday evening and expected it by Friday morning. It did not go through until Monday. The delay was not a technical failure. It was staffing volume in the clinical review queue. If you need a refill sooner, calling the clinic directly is still the faster path, even though the portal makes that feel less necessary than it actually is. Results access itself has a tiered structure. Some test categories are held back for a set window before becoming visible to the patient. Infectious disease panels and certain genetic tests often have intentional delays so the provider can discuss findings before the patient sees them raw. This is a patient safety feature, not a gatekeeping one, but it frustrates people who expect instant access to everything. The system also flags abnormal results with color coding and adds clinical commentary on some reports. The commentary is not always written for a lay audience, which means you will occasionally see terminology like "atypical lymphocytes" or "mild dysplasia" without an obvious explanation. Calling your provider's office for a plain-language readout is the standard move here. Message triage is another area where expectations diverge from reality. The secure messaging feature routes to a shared inbox, and response time depends on which department you are messaging. Endocrinology typically replies within 24 to 48 hours on business days. Emergency department follow-up messages can take longer because they are not staffed through the portal during off hours. I once spent forty minutes troubleshooting why a message about a medication reaction was not getting a response. It turned out the patient had sent it from a phone number that did not match the one on file, and the system routed it to a different provider panel entirely. Updating your contact information in the patient demographic section before sending urgent messages is a small step that prevents this specific failure mode.
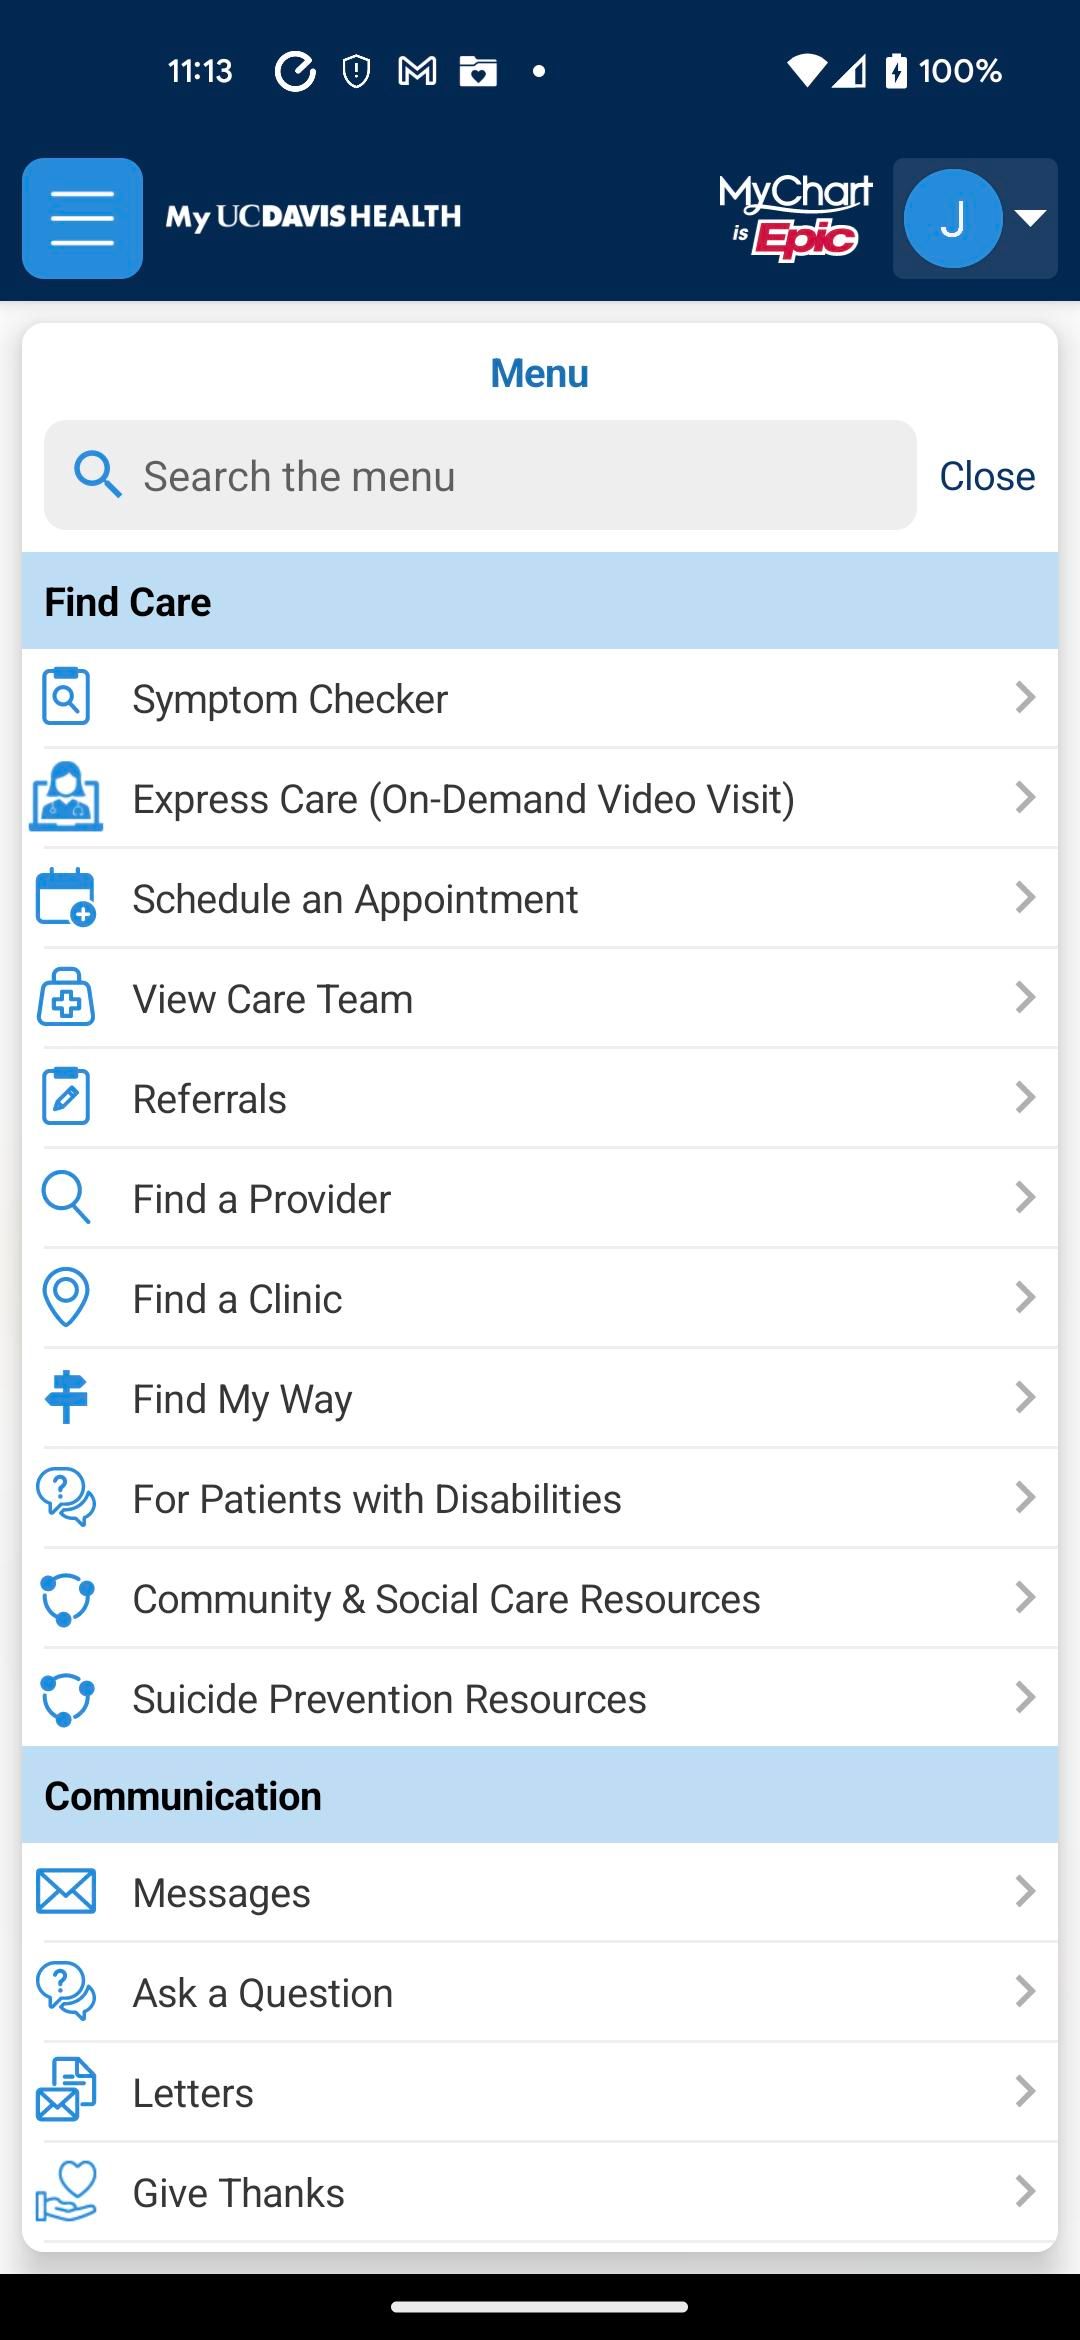
The billing and insurance section is functional but fragmented. You can view statements, set up payment plans, and download explanations of benefits, but linking to your insurer for real-time eligibility checks does not work consistently across all payer types. UC Davis contracts with several major employers and Medi-Cal managed care plans, and the integration depth varies by contract. If you are checking prior authorization status, the portal sometimes shows a pending flag without a date. At that point, the authorization management team is the correct contact, not the general patient line. Mobile app availability covers both iOS and Android, and the experience is roughly equivalent to the web version with the exception of document uploads. File uploads larger than ten megabytes fail silently on the app in most cases. If you need to submit a scanned insurance card or a photo of a rash for clinical review, use the browser version on a desktop or laptop instead. It handles the upload queue more reliably and gives you a confirmation number you can reference later. There are limitations worth stating plainly. The system does not integrate with external health systems in a way that allows cross-institutional record viewing without a formal health information exchange agreement. If you receive care at a different hospital network, those records will not appear in your UC Davis MyChart regardless of whether the other facility also uses MyChart. They may be visible through a regional HIE if you authorize that separately, but that is a different workflow entirely. Scheduling through the portal is limited to specific clinics. Urgent care appointments and surgical consults often require phone booking because the integration for those visit types has not been enabled in the scheduling module. Telehealth visits are accessible through the portal after your provider initiates the session, but you need a compatible browser and a stable internet connection. The built-in video feature occasionally drops audio on older Windows machines, and switching to the dedicated telehealth link from your email resolves that ninety percent of the time.
Get the Full Details

If you are trying to get the most out of this system, the practical approach is to treat it as a supplement to direct communication, not a replacement. The portal is excellent for routine refills, result checking, and administrative tasks. It is less reliable for urgent clinical decisions, complex care coordination across systems, and situations that require nuance in messaging. Understanding where it works well and where it breaks down is what separates people who get value from it from people who get frustrated.