Understanding the Female Reproductive System Diagram
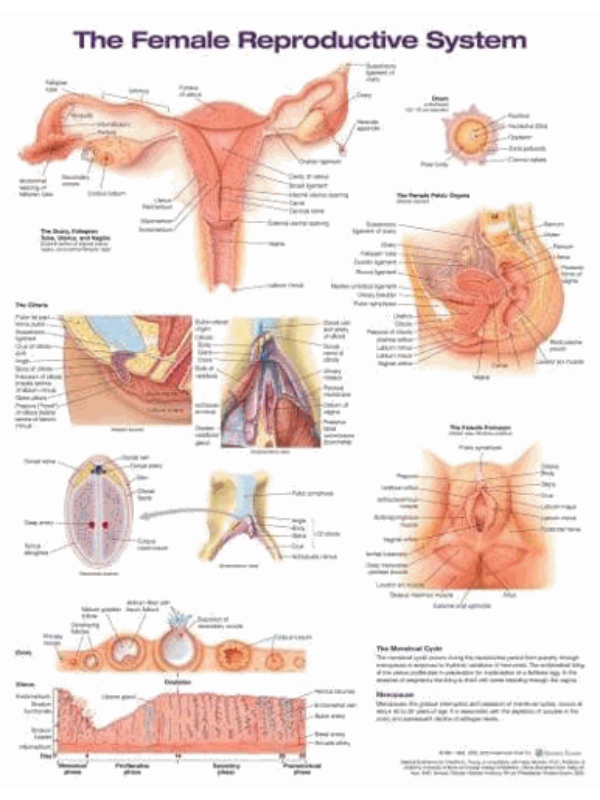
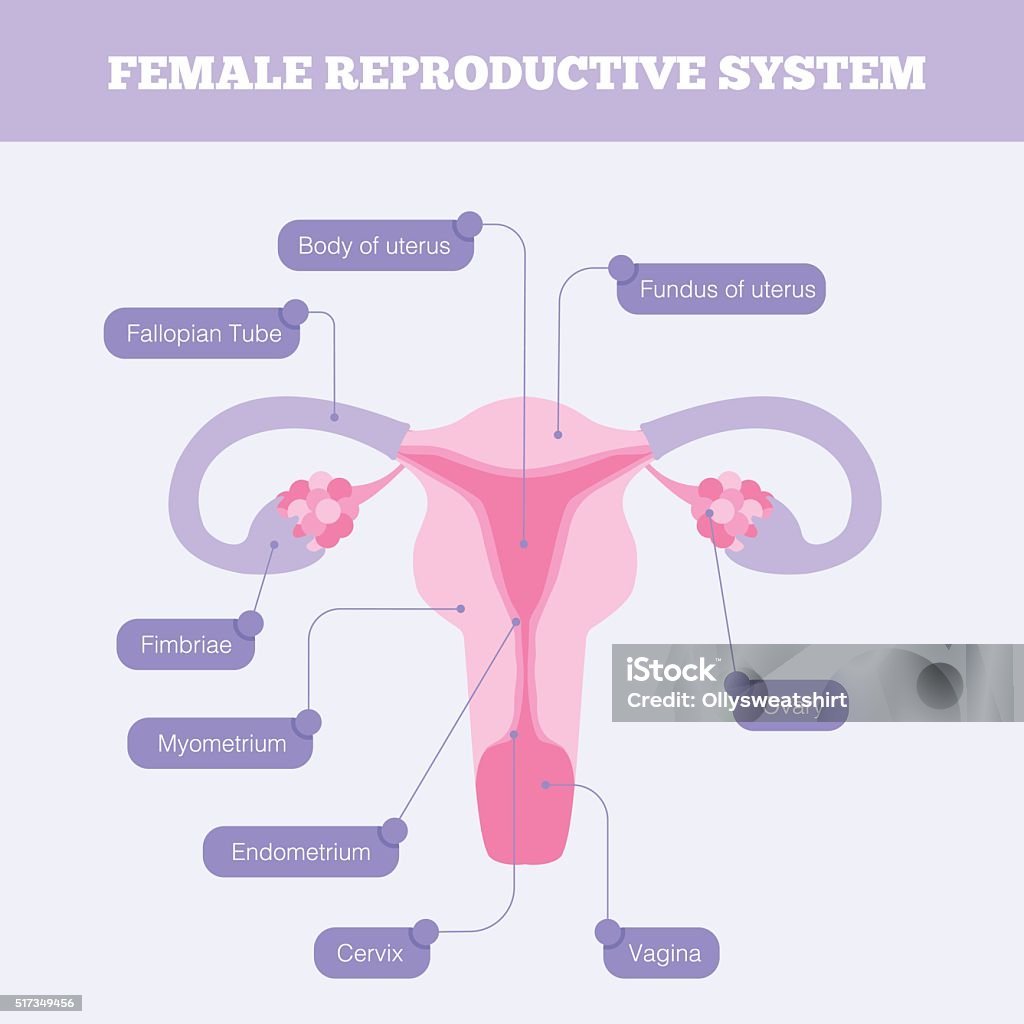
The female reproductive system diagram is one of those resources that looks simple at first glance but hides a lot of complexity once you start actually using it for patient education or personal health tracking. Most people grab a generic diagram from a textbook or a health website and assume they understand how everything connects. They don't. The labels look clean, the colors are neat, and the proportions are usually completely wrong compared to actual anatomy. I've spent years working with these diagrams in clinical settings and personal health contexts, and the gap between what a diagram shows and what's actually going on inside the body is where most confusion happens. What a good diagram gets right is the spatial relationship between organs. The ovaries sitting on either side of the uterus, the fallopian tubes extending from the uterine fundus toward the ovaries, the cervix forming the lower passage into the vagina. These connections matter. When someone is trying to understand why they have pain during certain points in their cycle, knowing which structure is where helps narrow down whether the issue might be ovarian, tubal, uterine, or something else entirely. A diagram gives you that geographic awareness that pure text descriptions struggle to convey.
Unlocking Female Reproductive Health A Visual Guide Through The Female Reproductive System Diagram
Here's the practical approach I recommend when you're working with a diagram to actually improve your understanding of reproductive health rather than just memorizing labels. First, pick a diagram that shows both the external and internal structures in a single view or in clearly labeled cross-sections. Anterior-posterior views that only show the outside are useless for understanding menstrual cycles or pregnancy. You need to see the endometrium, the myometrium, the endocervical canal. Look for diagrams that differentiate between these layers because the endometrial lining is where most clinical events happen — implantation, menstruation, abnormal bleeding — and if your diagram lumps it all into one pink shape, you're already working with incomplete information. Second, annotate your own diagram. I keep a personal version where I add notes about what each structure does during different phases of the cycle. The follicular phase affects the ovaries primarily. The luteal phase involves the corpus luteum and its hormone output. Ovulation is a transient event that most static diagrams can't capture well. Writing these dynamics next to the static image bridges the gap between structure and function.
Third, correlate the diagram with actual symptoms or cycle data. If you track your period and notice a pattern of mid-cycle pain on one side, go back to the diagram and trace which ovary and fallopian tube are involved on that side. This turns the diagram from a passive reference into an active diagnostic tool. It takes about ten minutes to set up this kind of personal tracking system with a printed diagram and a notebook, and it usually pays off within a few cycle observations. I ran into a specific problem about two years ago when a patient brought in a diagram she'd found online and was convinced it showed her having a duplicated uterus because of a faint line she spotted near the top of the uterine cavity. The diagram was actually a standard single-cavity illustration with a printing artifact that looked like a septum. She'd been stressed about an undiagnosed condition because a low-resolution commercial diagram had introduced visual noise she misinterpreted as anatomy. The workaround was straightforward: I had her get an actual transvaginal ultrasound, which resolved the uncertainty in fifteen minutes and confirmed normal anatomy. The lesson was that diagram quality matters enormously, and you should always verify anything that seems unusual against medical imaging rather than assuming the diagram is accurate.
Get the Full Details
Common Diagram Types and What They Actually Show
Not all diagrams are created equal. The type you choose depends entirely on what question you're trying to answer. A schematic diagram that uses simple colored shapes is fine for understanding basic organ relationships. A histological cross-section diagram is better if you need to understand what the endometrium looks like at the microscopic level during different cycle phases. An anatomical illustration with realistic proportions is useful for surgical planning or understanding spatial constraints. Mixing these up is a common mistake. One thing beginners consistently miss is that most diagrams show the reproductive organs in their resting, non-pregnant state. The uterus is roughly the size of a small pear, maybe seven centimeters long. The fallopian tubes are about ten centimeters each and have a very specific fimbriated end that sweeps over the ovary. But during pregnancy, the uterus can expand to fifteen centimeters or more and weigh nearly a kilogram. During ovulation, the dominant follicle in the ovary reaches about two centimeters before rupturing. None of this expansion or change is visible in a standard diagram, which is why people sometimes have unrealistic expectations about what these organs look like at different life stages. Another nuance that diagrams usually get wrong is the position of the uterus. Most show it in a midline, anteverted position. In reality, the uterus can be retroverted, midposition, or anteverted, and the angle affects everything from menstrual flow dynamics to how certain conditions present symptomatically. About twenty percent of women have a retroverted uterus, which is a normal variation but one that standard diagrams rarely acknowledge. If you're reading a diagram and wondering why your symptoms don't match the idealized version, this positional variation might be the explanation.
How to Use a Diagram for Cycle Tracking and Health Monitoring
The most practical application of a female reproductive system diagram is in understanding your own cycle. Here's how I suggest approaching it. Start by learning the five key structures and what each contributes to cycle function. The hypothalamus and pituitary gland regulate everything through hormonal signaling, though they're not always shown on basic diagrams. The ovaries produce eggs and hormones like estrogen and progesterone. The fallopian tubes are the site of fertilization and transport the egg toward the uterus. The uterus houses the endometrium where implantation occurs. The cervix controls passage between the uterus and vagina and produces mucus that changes consistency throughout the cycle. Mapping these functions onto the visual diagram creates a mental model that's easier to recall than a list of facts. When tracking your cycle, mark which side you ovulate from if you notice one-sided pain or use basal body temperature charting to confirm. Some women alternate sides each cycle. Some consistently ovulate from one ovary. The diagram helps you visualize which structures are active at each phase. During the proliferative phase, the endometrium is building under estrogen influence. During the secretory phase, progesterone from the corpus luteum prepares the endometrium for potential implantation. If your diagram doesn't show the endometrial changes across these phases, find one that does or draw them in yourself. This detail transforms a static picture into a dynamic understanding.
I've found that spending about twenty minutes each month reviewing your cycle data against the diagram reinforces the connection between what you feel physically and what's happening anatomically. It's not a substitute for medical evaluation when something seems wrong, but it does help you distinguish between normal cycle variations and patterns that warrant professional attention. Irregular cycle length, unusually heavy bleeding, pain that disrupts daily activities — these are the signals that a diagram alone can't address and that need clinical investigation.

Where Diagrams Fall Short
Every diagram has limitations, and being honest about them prevents misuse. A printed diagram cannot show blood flow, hormonal concentrations, or the real-time activity of organs. It cannot tell you whether your endometrium is thick enough for implantation or whether your ovaries are functioning optimally. For that information, you need blood work, ultrasound, and clinical assessment. The diagram is a map, not the territory. Something else to be aware of is that many free diagrams online have anatomical inaccuracies. The fallopian tubes are sometimes drawn too wide or with incorrect fimbrial detail. The ovarian ligament and suspensory ligament are frequently confused or omitted. The broad ligament is rarely shown at all despite being a significant structural component. If you're using a diagram for educational purposes or patient communication, verify it against a reputable source like a medical textbook or a peer-reviewed anatomy resource. A diagram with errors can create lasting misunderstandings that are harder to unlearn than not having a diagram at all. For people who need accurate, detailed diagrams for serious health management or professional use, I'd recommend looking into resources from medical publishers like Elsevier or Springer, or platforms like Visible Body and Kenhub that produce anatomically precise illustrations. These cost money but save time correcting mistakes later. Free diagrams from health blogs and general wellness sites are fine for basic orientation but should not be the sole reference for anything beyond casual curiosity.
The bottom line is that a female reproductive system diagram is a starting point, not an endpoint. It gives you vocabulary and spatial awareness. It doesn't replace understanding of hormonal mechanics, clinical evaluation, or personalized health data. Used correctly, it makes those other elements easier to grasp. Used as a replacement for actual medical knowledge, it becomes a source of confusion and anxiety. The difference comes down to how deliberately you engage with it and how honest you are about what it can and cannot tell you.