Wound Bed Preparation and Topical Support in Daily Practice
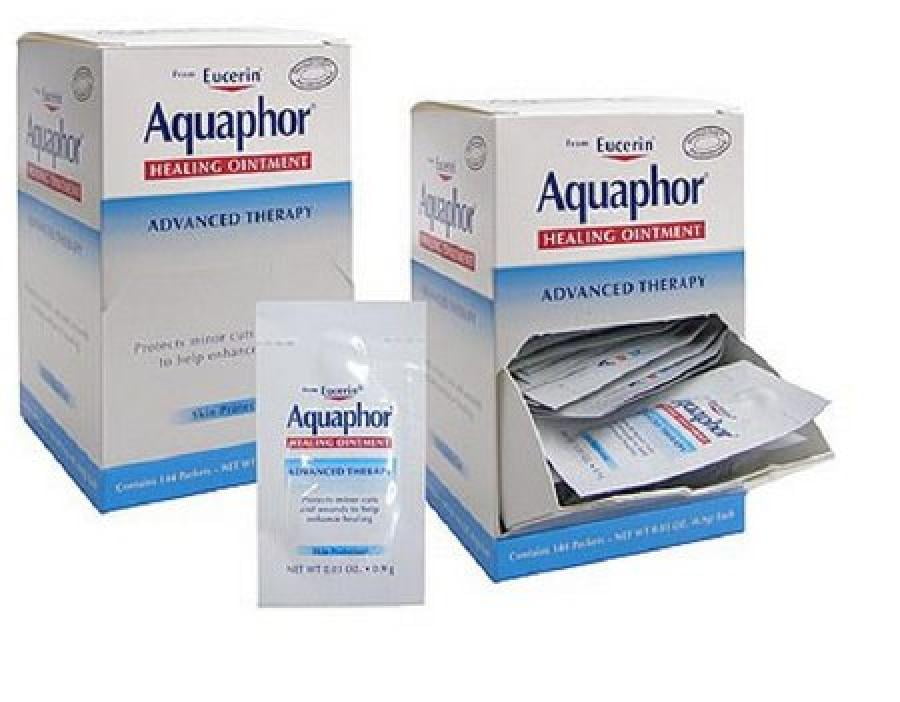
Aquaphor Healthcare Professional Samples are one of those things you'll see handed out at nurse staff meetings, posted on pharmacy carts, or slipped into wound care kits during formulary introductions. The product itself is a petrolatum-based ointment with panthenol and glycerin, designed primarily for skin barrier protection and supporting healing in minor cuts, scrapes, and post-procedural sites. It is not a advanced wound dressing, and it will not do anything meaningful for a Stage 3 or 4 pressure ulcer on its own. The actual value sits in the narrow indications where it is appropriate, which is why understanding the clinical context matters more than the marketing language on the sample packet. When used correctly, it can reduce transepidermal water loss around wound edges, protect periwound skin from excoriation, and provide a mild occlusive environment that supports re-epithelialization in superficial wounds. That last point is the one people usually miss. It works best as a adjunctive skin protectant, not as a standalone therapeutic agent for complex wounds.
Unlocking Clinical Excellence How Aquaphor Healthcare Professional Samples Drive Optimal Wound Outcomes
I have been placing Aquaphor samples with discharge instructions and wound care education materials for patients recovering from surgical incisions, minor laceration repairs, and donor sites after split-thickness skin grafts. The practical workflow is straightforward. You clean the area, apply a thin layer to intact surrounding skin and the superficial wound surface, then cover with an appropriate secondary dressing if needed. The sample packets are single-use, which actually helps with compliance in patients who might otherwise contaminate a large tube through repeated dip and reach cycles. There is a specific scenario where I found this genuinely useful beyond the standard recommendations. A patient came in for suture removal after an elective excision on the lower leg. The incision was healing well, but the surrounding skin was raw and erythematous from repeated povidone-iodine applications during daily dressing changes. The patient was also diabetic, which meant even minor skin breakdown could escalate quickly. I switched her from the iodine routine to gentle saline cleaning and applied a thin film of Aquaphor around the incision line on the periwound skin only. The redness resolved within four days. The sample size lasted her about five days, which aligned perfectly with the follow-up window. That is the kind of case where the product does something measurable without being the primary treatment.
When to Use It and When to Move On
The clinical sweet spot for Aquaphor in wound management includes superficial partial-thickness injuries, post-surgical incisions where the wound edges are approximated and dry, and dermatological procedures such as dermabrasion or laser treatments where the epidermis is compromised but the dermis remains intact. It is also reasonable for protecting skin around stoma appliances, infusion sites, and areas subject to repeated friction or moisture exposure. What it should not be used for includes infected wounds, wounds with significant exudate, chronic ulcers where the underlying pathology has not been addressed, and any situation requiring antimicrobial or debridement intervention. Putting an occlusive petrolatum-based ointment over a colonized or infected wound is counterproductive. It traps moisture and creates an environment where bacterial proliferation can accelerate. I have seen this happen when clinicians prescribe barrier ointments out of habit without reassessing whether infection is present. The ointment base contains alcohol, which some patients report as a brief stinging sensation on freshly disrupted skin. It is mild and transient, but it is worth mentioning during patient education so they do not assume the product is causing harm. The fragrance-free variant eliminates this variable entirely and is the version I prefer for post-surgical populations.
Get the Full Details

Practical Distribution and Compliance Considerations
From a distribution standpoint, the Healthcare Professional Sample format exists because insurers rarely cover these products directly, and patients frequently need something accessible after discharge when they do not want to purchase a full-size tube at the pharmacy. The single-use packets are cost-effective for clinical offices and eliminate cross-contamination concerns that come with shared multi-dose containers. I stock them in my wound clinic alongside standard dressing supplies and hand them out during the initial dressing change after any procedure involving epidermal disruption. The sample size is calibrated to roughly three to five days of use, which is intentionally short enough to require a follow-up or a pharmacy visit. This creates a natural checkpoint where I can reassess wound progress and ensure the patient is not developing complications. It is a small structural benefit that is often overlooked in discussions about wound care supply chains. There are situations where even the sample packets cause issues. Patients with known hypersensitivity to fragrance components or lanolin should avoid the standard formulation. The ingredient list is accessible on the manufacturer website, and I verify this during intake screening for patients with a history of contact dermatitis. A patch test is not always practical in an acute wound setting, so I default to the fragrance-free version when there is any uncertainty about skin tolerance.
Technical Nuances Beginners Miss
One detail that most wound care guides omit involves the interaction between Aquaphor and certain dressing adhesives. The petrolatum base can compromise the adhesive bond on some hydrocolloid and foam dressings, causing premature edge lift and reducing the dressing's ability to maintain a controlled moisture environment. If you are using Aquaphor in conjunction with an adhesive dressing, apply the ointment sparingly and avoid getting it on the areas where the dressing will contact the skin. A thin peripheral film around the wound margin is sufficient. The goal is periwound protection, not saturation of the entire area. Another nuance is the timing of application relative to debridement. If sharp or mechanical debridement has been performed, applying Aquaphor immediately over the debrided surface can create a barrier that impedes natural drainage and makes it difficult to assess whether additional debridement is needed in follow-up visits. I typically wait until the wound has passed the initial inflammatory phase and granulation tissue is beginning to form before introducing the ointment as a regular part of the dressing regimen. This usually means day three or four post-debridement for most superficial wounds.
Limitations and Alternatives
Aquaphor is a solid option for its designated use cases, but it is not a universal solution. For wounds requiring moisture retention with active exudate management, hydrogel dressings or alginate overlays are more appropriate. For antimicrobial needs, silver-impregnated dressings or medical-grade honey products should be considered instead. The ointment also lacks any proven bioactive wound-healing properties beyond barrier protection and hydration support. Claims about scar reduction are anecdotal at best, and the clinical evidence for long-term cosmetic outcomes is limited. If a patient presents with a wound that is already beyond the superficial range or showing signs of delayed healing, Aquaphor alone will not address the underlying issue. In those cases, referral to a wound care specialist or elevation of the treatment plan to include advanced modalities is the appropriate step. No amount of sample distribution changes the biology of a non-healing wound. The Healthcare Professional Sample program remains a practical tool for distributing these products to patients who need them during the early phases of wound recovery. Understanding the boundaries of when it helps and when it does not is what separates competent clinical practice from routine protocol following. The product works when the indication is right. It does not work when the clinician applies it out of rather than clinical judgment.




