What Simple Columnar Epithelium Actually Does In Your Body
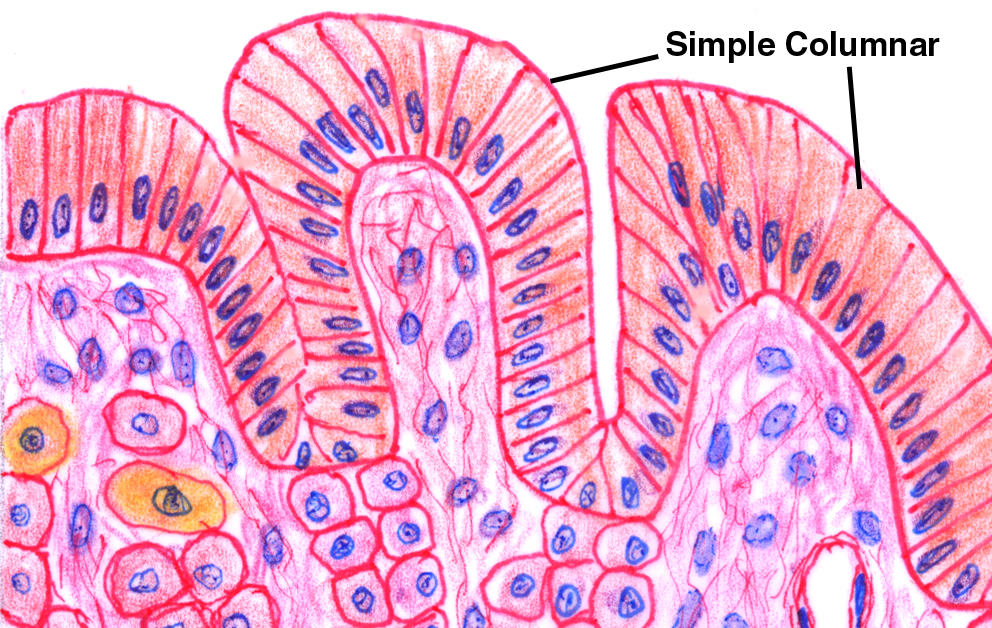
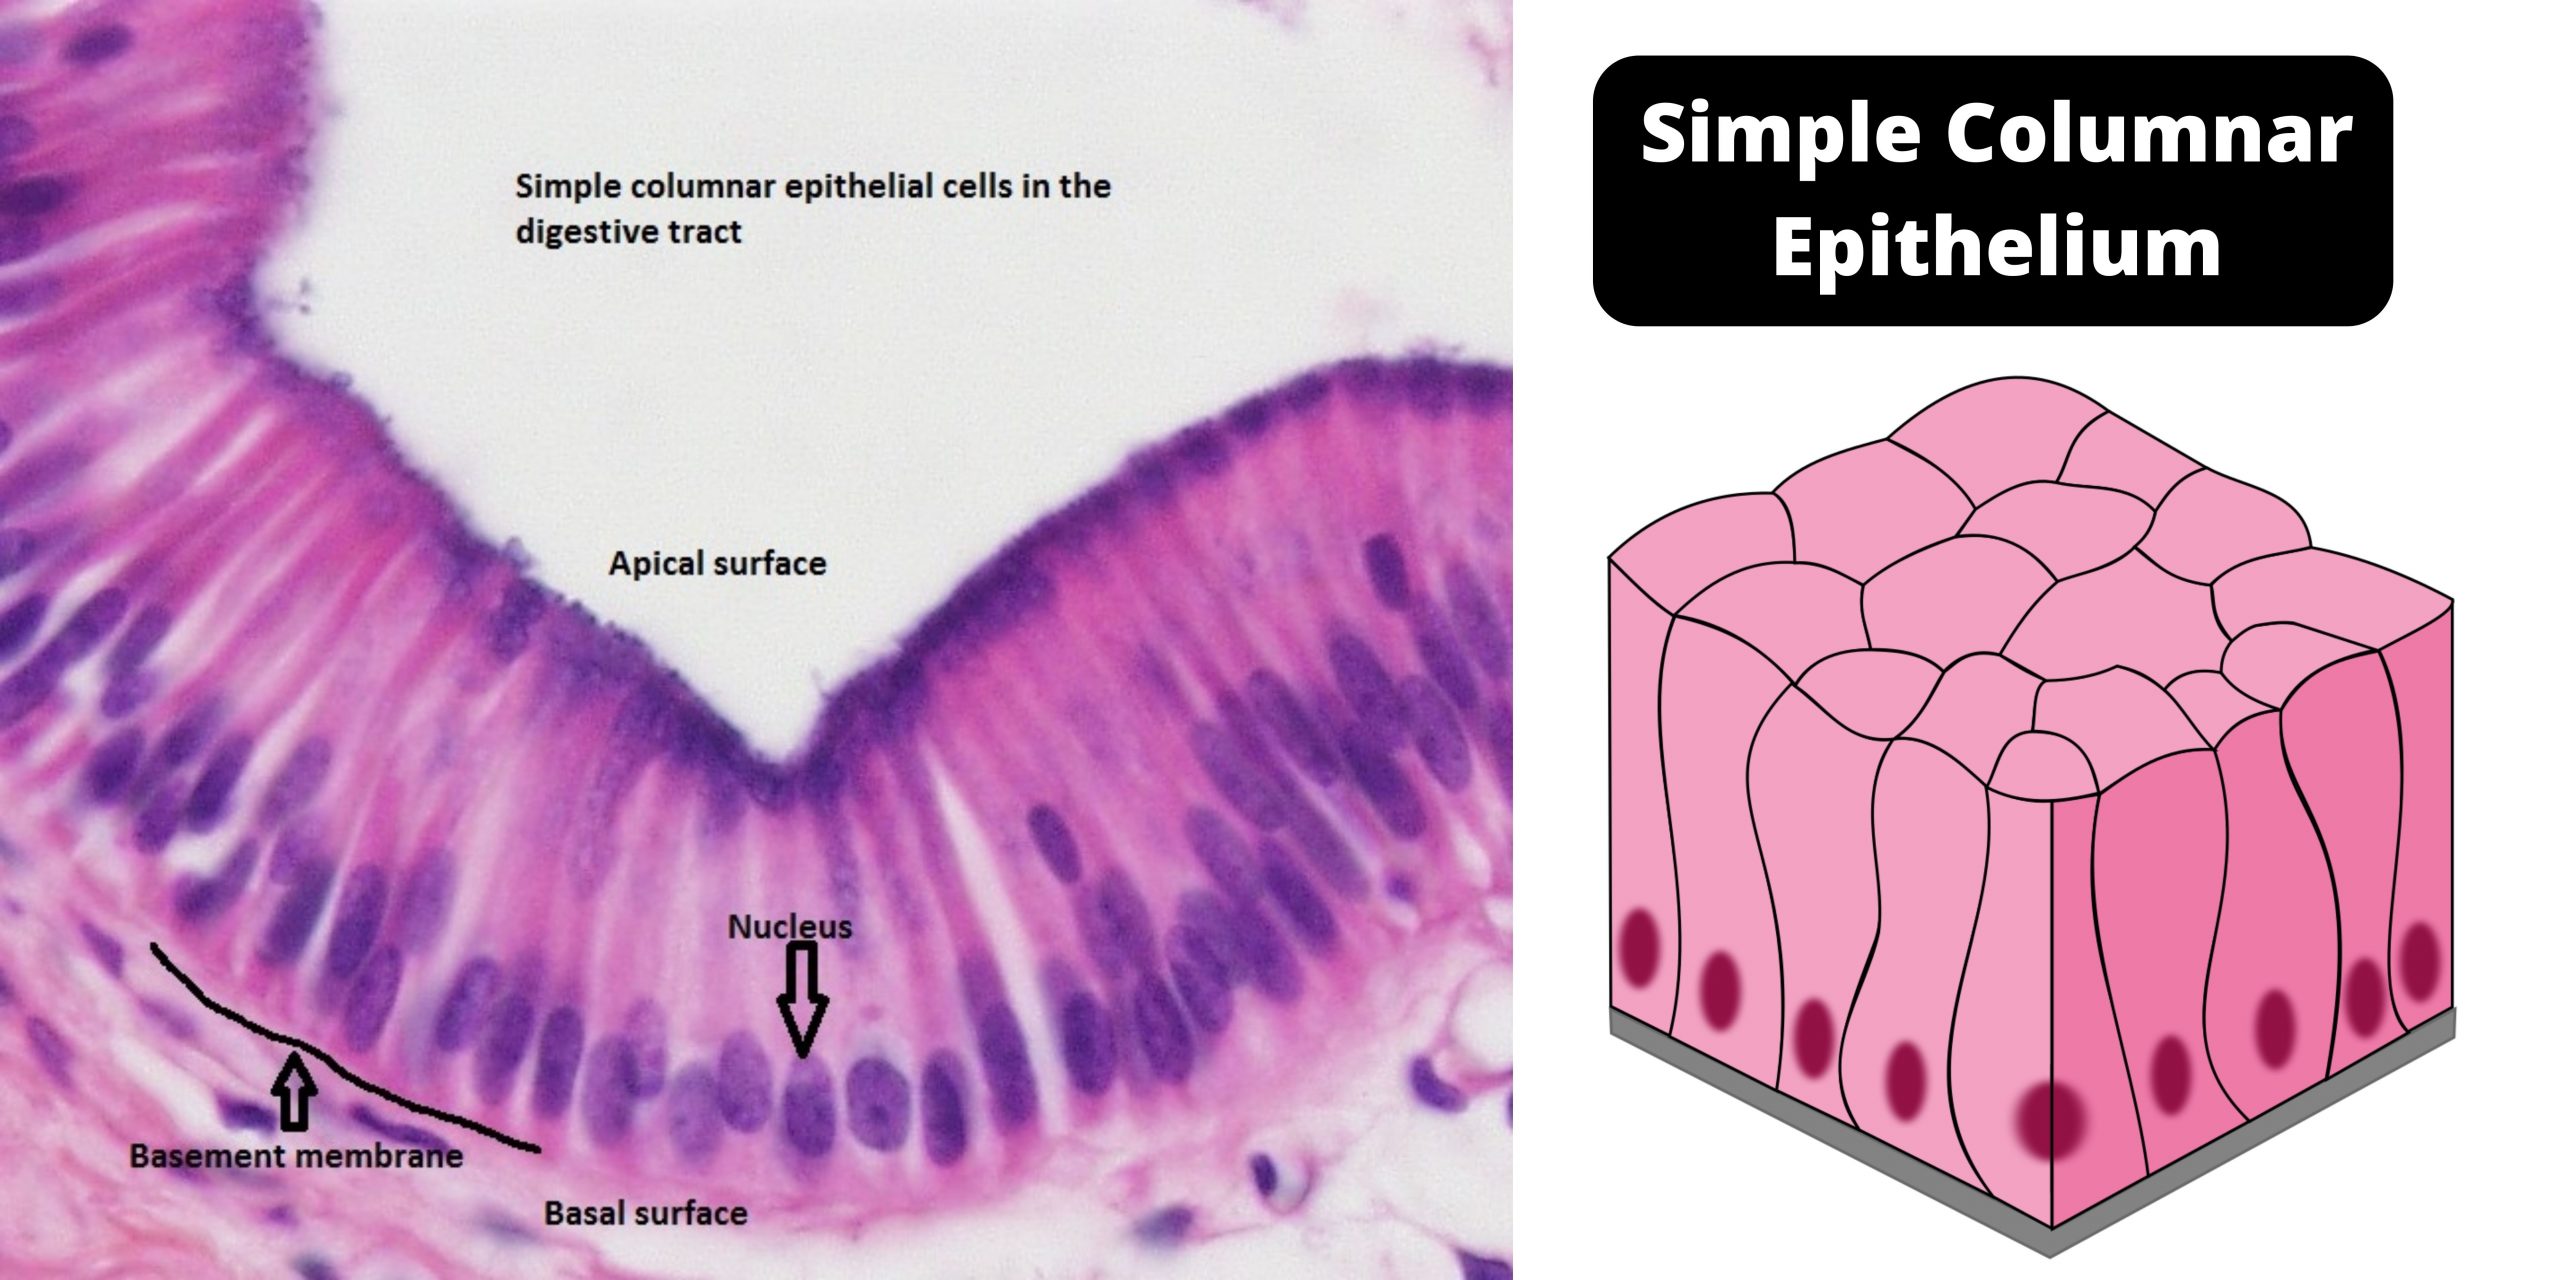
Simple columnar epithelium lines your small intestine, parts of your stomach, and the gallbladder. It is a single layer of tall, rectangular cells with nuclei near the base. You probably learned this in an intro biology class and moved on, but the details matter when you are actually working with it under a microscope or interpreting histology slides for a pathology report. Here is the thing most textbooks leave out: the presence or absence of microvilli completely changes how this tissue functions. In the small intestine, you have a brush border of dense microvilli that dramatically increases surface area for absorption. In the gallbladder, the same cell type loses those microvilli and instead focuses on water reabsorption. The cells look nearly identical at low magnification. If you do not check for the brush border, you can misidentify the tissue origin entirely. I spent about three days last month trying to figure out why a biopsy sample from a patient with unexplained malabsorption kept coming back as "normal" on the initial read. The problem was the section was cut at an oblique angle. When simple columnar epithelium is sliced diagonally, the nuclei appear scattered at different levels rather than neatly aligned at the base. It mimics dysplasia on first glance. The workaround was straightforward: I asked the tech to recut a perpendicular section, and the pseudo-dysplastic appearance vanished immediately. The cells were fine. The angle was the issue.
How To Recognize It Under The Microscope
Start at 10x objective. Look for a single row of cells that are clearly taller than they are wide. The nuclei should be oval or elongated and positioned toward the basal side of the cells. At 40x, you should be able to see whether there is a brush border present. At 100x oil immersion, you can resolve individual microvilli if the staining is decent. Common staining note: H&E is standard, but if you need to highlight mucin-producing goblet cells interspersed among the columnar cells, a PAS stain will make those mucus granules stand out clearly in magenta. This is useful in the intestine where goblet cells are abundant but in the stomach they are less frequent and sometimes hard to distinguish without special stains.
Where You Will Actually Encounter This Tissue
Beyond the textbook examples, simple columnar epithelium appears in places you might not expect. The endocervix is lined by it. The uterine tubes use it for ciliated transport of the oocyte. The excretory ducts of some glands contain it too. Each location adds a functional twist: cilia in the fallopian tubes, secretory activity in the stomach, absorptive function in the intestine. A practical pitfall: the transition zones. At the squamocolumnar junction in the cervix, the tissue switches from stratified squamous to simple columnar. This area is a common site for dysplasia because the metaplastic change creates cellular stress during repair. If you are reading a Pap smear or a cervical biopsy, knowing exactly where this junction sits matters more than you might think. It is not always in the same place between patients, and it shifts with hormonal changes over time.
Get the Full Details

Limitations And Where It Fails
Simple columnar epithelium is fragile. It does not handle mechanical stress well. That is why it is not found in the skin or the esophagus, which need stratified layers for protection. If you are studying a tissue that has been subjected to chronic irritation or acid reflux, you may see metaplastic changes where columnar cells are replaced by stratified squamous cells. This is the body adapting, but it also means the original tissue type is gone and you cannot assess it directly anymore. Another limitation: immunohistochemistry markers for simple columnar epithelium overlap significantly with other glandular tissues. CK7 and CK20 panels help, but they are not definitive on their own. CK20 positive and CK7 negative points toward intestinal origin, but a subset of gastric and biliary cancers break that pattern. You cannot rely on a single marker panel to tell you exactly where a tumor came from. Context from the H&E morphology still matters, and sometimes it still is not enough. If you are working with cultured cells rather than tissue sections, note that simple columnar epithelial cells from the intestine tend to lose their differentiated features within a few passages. They flatten out, stop producing mucin, and lose the brush border. If you need authentic phenotype data, primary cultures or organoid systems give you results that are closer to the in vivo state. Standard cell lines like Caco-2 are the exception because they differentiate into something resembling intestinal epithelium over 21 days, but even then the model is imperfect.